Acne
A guideline-supported treatment for comedones and inflammatory lesions.
Adapalene: Prevents clogged pores and treats inflammatory and non-inflammatory acne. Sulfur: Used in some acne products and prescribed or compounded scabies regimens.
Choose for clogged pores and ongoing acne prevention; introduce gradually.
Consider for an appropriate acne product; suspected scabies needs diagnosis and a complete plan.
Can you use both?
Sulfur spot treatments can be used on breakouts while using adapalene. Watch for dryness.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.




Binds retinoid receptors: Adapalene works without conversion to retinoic acid. Helps keep follicles clear: Regulates cell shedding and inflammatory pathways.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.
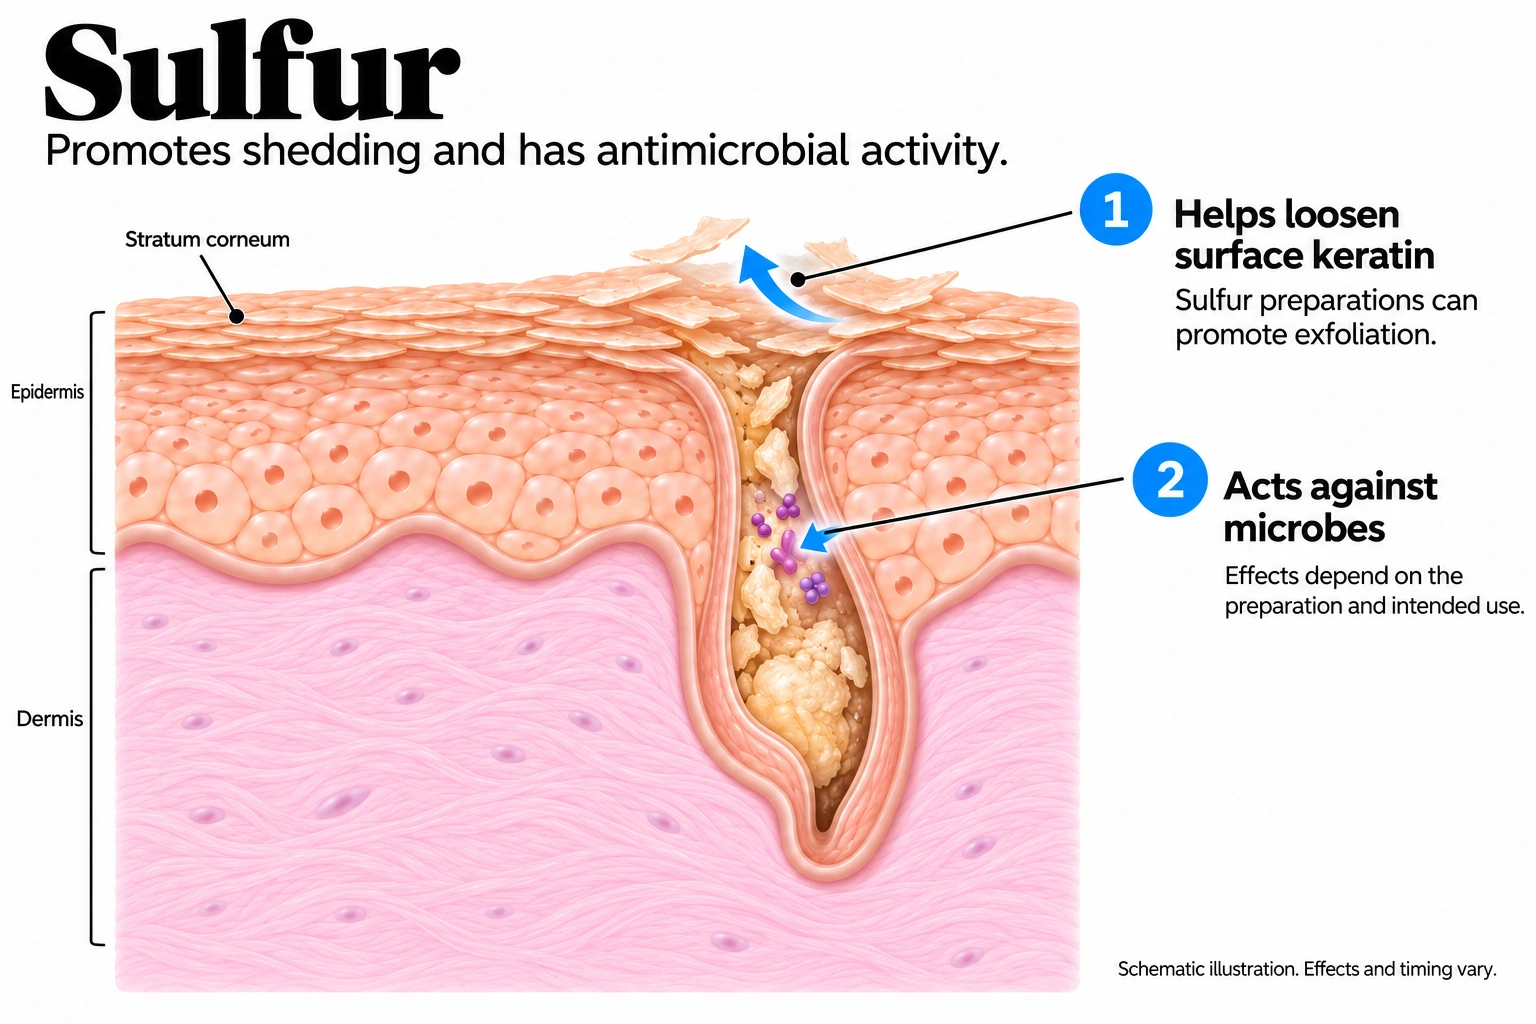
Helps loosen surface keratin: Sulfur preparations can promote exfoliation. Acts against microbes: Effects depend on the preparation and intended use.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.
Built from where each one usually sits in a routine. Introduce one at a time.
Adapalene is a medicine, not a cosmetic retinol. U.S. acne formulations include 0.1% and 0.3%; the higher strength is prescription.
0.1%
0.3%
OTC acne gel
A labeled acne treatment in the U.S. Improvement takes time; using extra product does not speed the result.
Prescription acne gel
A higher-strength formulation with comparative trial evidence. A clinician can weigh benefit against irritation.
Choosing a strength: Choose the medicine and vehicle for acne severity and tolerance. Adapalene percentages are not equivalent to retinol or retinaldehyde percentages.
Higher strengths: Dryness, peeling and irritation can occur. Do not step up strength or combine several retinoids just because improvement is slow.
Formula matters: Products combining adapalene with benzoyl peroxide have additional active ingredients and different labeling; read the whole product name.
Sulfur strength depends on the condition: U.S. OTC acne products use 3–10%, while compounded scabies ointments use a separate 5–10% range.
3–10%
5–10%
OTC acne range
For qualifying acne products. A wash, mask and leave-on product have different contact instructions.
Compounded scabies ointment
A clinician-directed alternative discussed by CDC. It is a separate treatment, not ordinary facial skincare.
Choosing a strength: Choose for the diagnosis and complete product. Sulfur-only acne products and prescription sulfacetamide/sulfur combinations are not the same.
Higher strengths: More sulfur is not automatically more useful, and dryness or irritation may limit use.
Formula matters: Wash-off versus leave-on use matters. Scabies treatment requires a whole treatment plan rather than choosing a percentage alone.
Approximate windows, not promises.
First few weeksDryness or irritation may occur; worsening is not required for benefit.
First few weeksAssess tolerance and texture; immediate softness can come from the base formula.
4–8 weeksFewer new lesions may become noticeable.
4–8 weeksSubtle changes may appear in some tested products; evidence varies.
8–12 weeksReassess acne control after a consistent course.
8–12 weeksCompare photographs in the same lighting and reassess benefit.
3–6 monthsMaintenance may help if the treatment works and remains comfortable.
3–6 monthsPhotoaging trials often need several months; expect modest rather than dramatic change.
6–12 monthsContinue only if appropriate; scarring or persistent acne warrants reassessment.
6–12 monthsLong-term evidence is limited for many cosmetic actives; continue only if useful.
Dryness, stinging and peeling can occur, especially early in use.
Odour, dryness and irritation can limit use; avoid strong products on inflamed eczema.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.
Choose a simple formula and test a small area first. Individual tolerance matters more than an ingredient’s reputation for being gentle.
Follow the age and use restrictions on the label; OTC adapalene 0.1% is labelled for ages 12 and older in the US.
Do not use a cosmetic product as a substitute for diagnosis of an unexplained, changing or persistent skin problem.
Retinoids are avoided in pregnancy and while trying to conceive.
Topical sulfur is generally considered acceptable in pregnancy; ask the clinician managing your pregnancy.
On the skin. The finished product delivers adapalene in a particular vehicle.
Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Conversion. Binds retinoid receptors directly; it does not need conversion into retinoic acid.
Skin response. Binds retinoid receptors directly, regulating follicular cell shedding and inflammatory pathways.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
On the skin. The finished product delivers sulfur in a particular vehicle.
Entering skin. Below 500 Da in this molecular form. Its useful surface action does not require deep delivery; the formula and skin condition matter.
Conversion. No activation step is established as necessary for its intended topical role.
Skin response. Promotes surface shedding and has antimicrobial activity; effects and instructions depend on the preparation.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
Choose for clogged pores and ongoing acne prevention; introduce gradually.
Guidelines and controlled acne trials support adapalene. Evidence for acne medicines should not be transferred automatically to retinol, and irritation does not indicate greater benefit.
Consider for an appropriate acne product; suspected scabies needs diagnosis and a complete plan.
Modern isolated-sulfur acne evidence is limited; studies of sulfacetamide/sulfur cannot isolate sulfur. CDC describes sulfur ointment as a scabies option, but an acne wash is not a substitute for that regimen.
Sources