Acne
Reduces inflamed breakouts in large trials.
Aczone: An anti-inflammatory gel for red, tender acne. It is not a retinoid and not a standard antibiotic, so it suits skin that cannot tolerate either. Finacea: The prescription strength of azelaic acid, made for the bumps and pustules of rosacea. It is the same ingredient sold at 10% over the counter, in a stronger and regulated formula.


Choose for red, tender acne when skin can't tolerate a retinoid or you want to avoid a standard antibiotic.
Choose for rosacea bumps and pustules, or acne with dark marks, when you want a gentle option that's often used in pregnancy.
Can you take them together?
These can be used together for acne with dark marks. Apply them at different times of day if the skin feels irritated.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

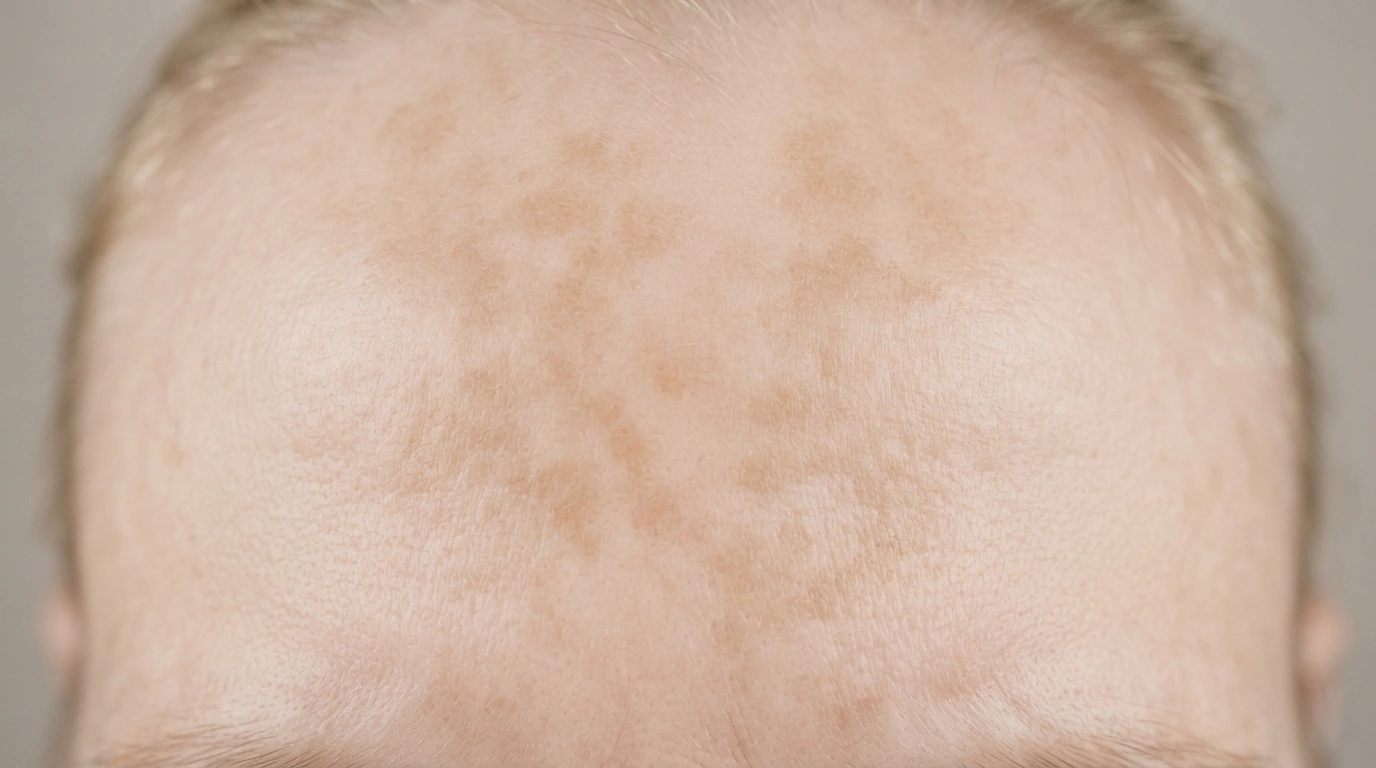

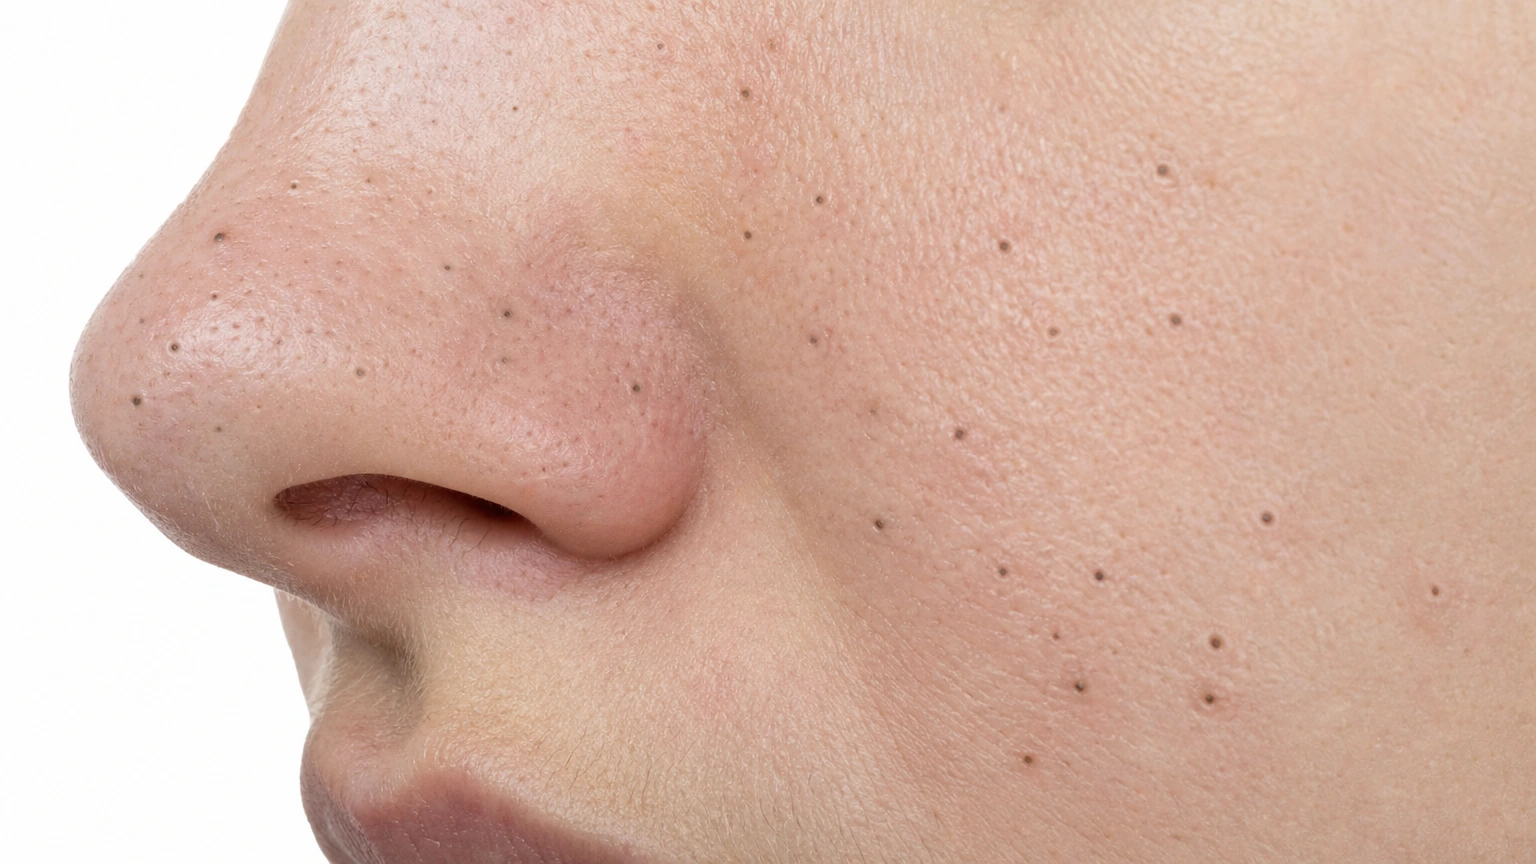
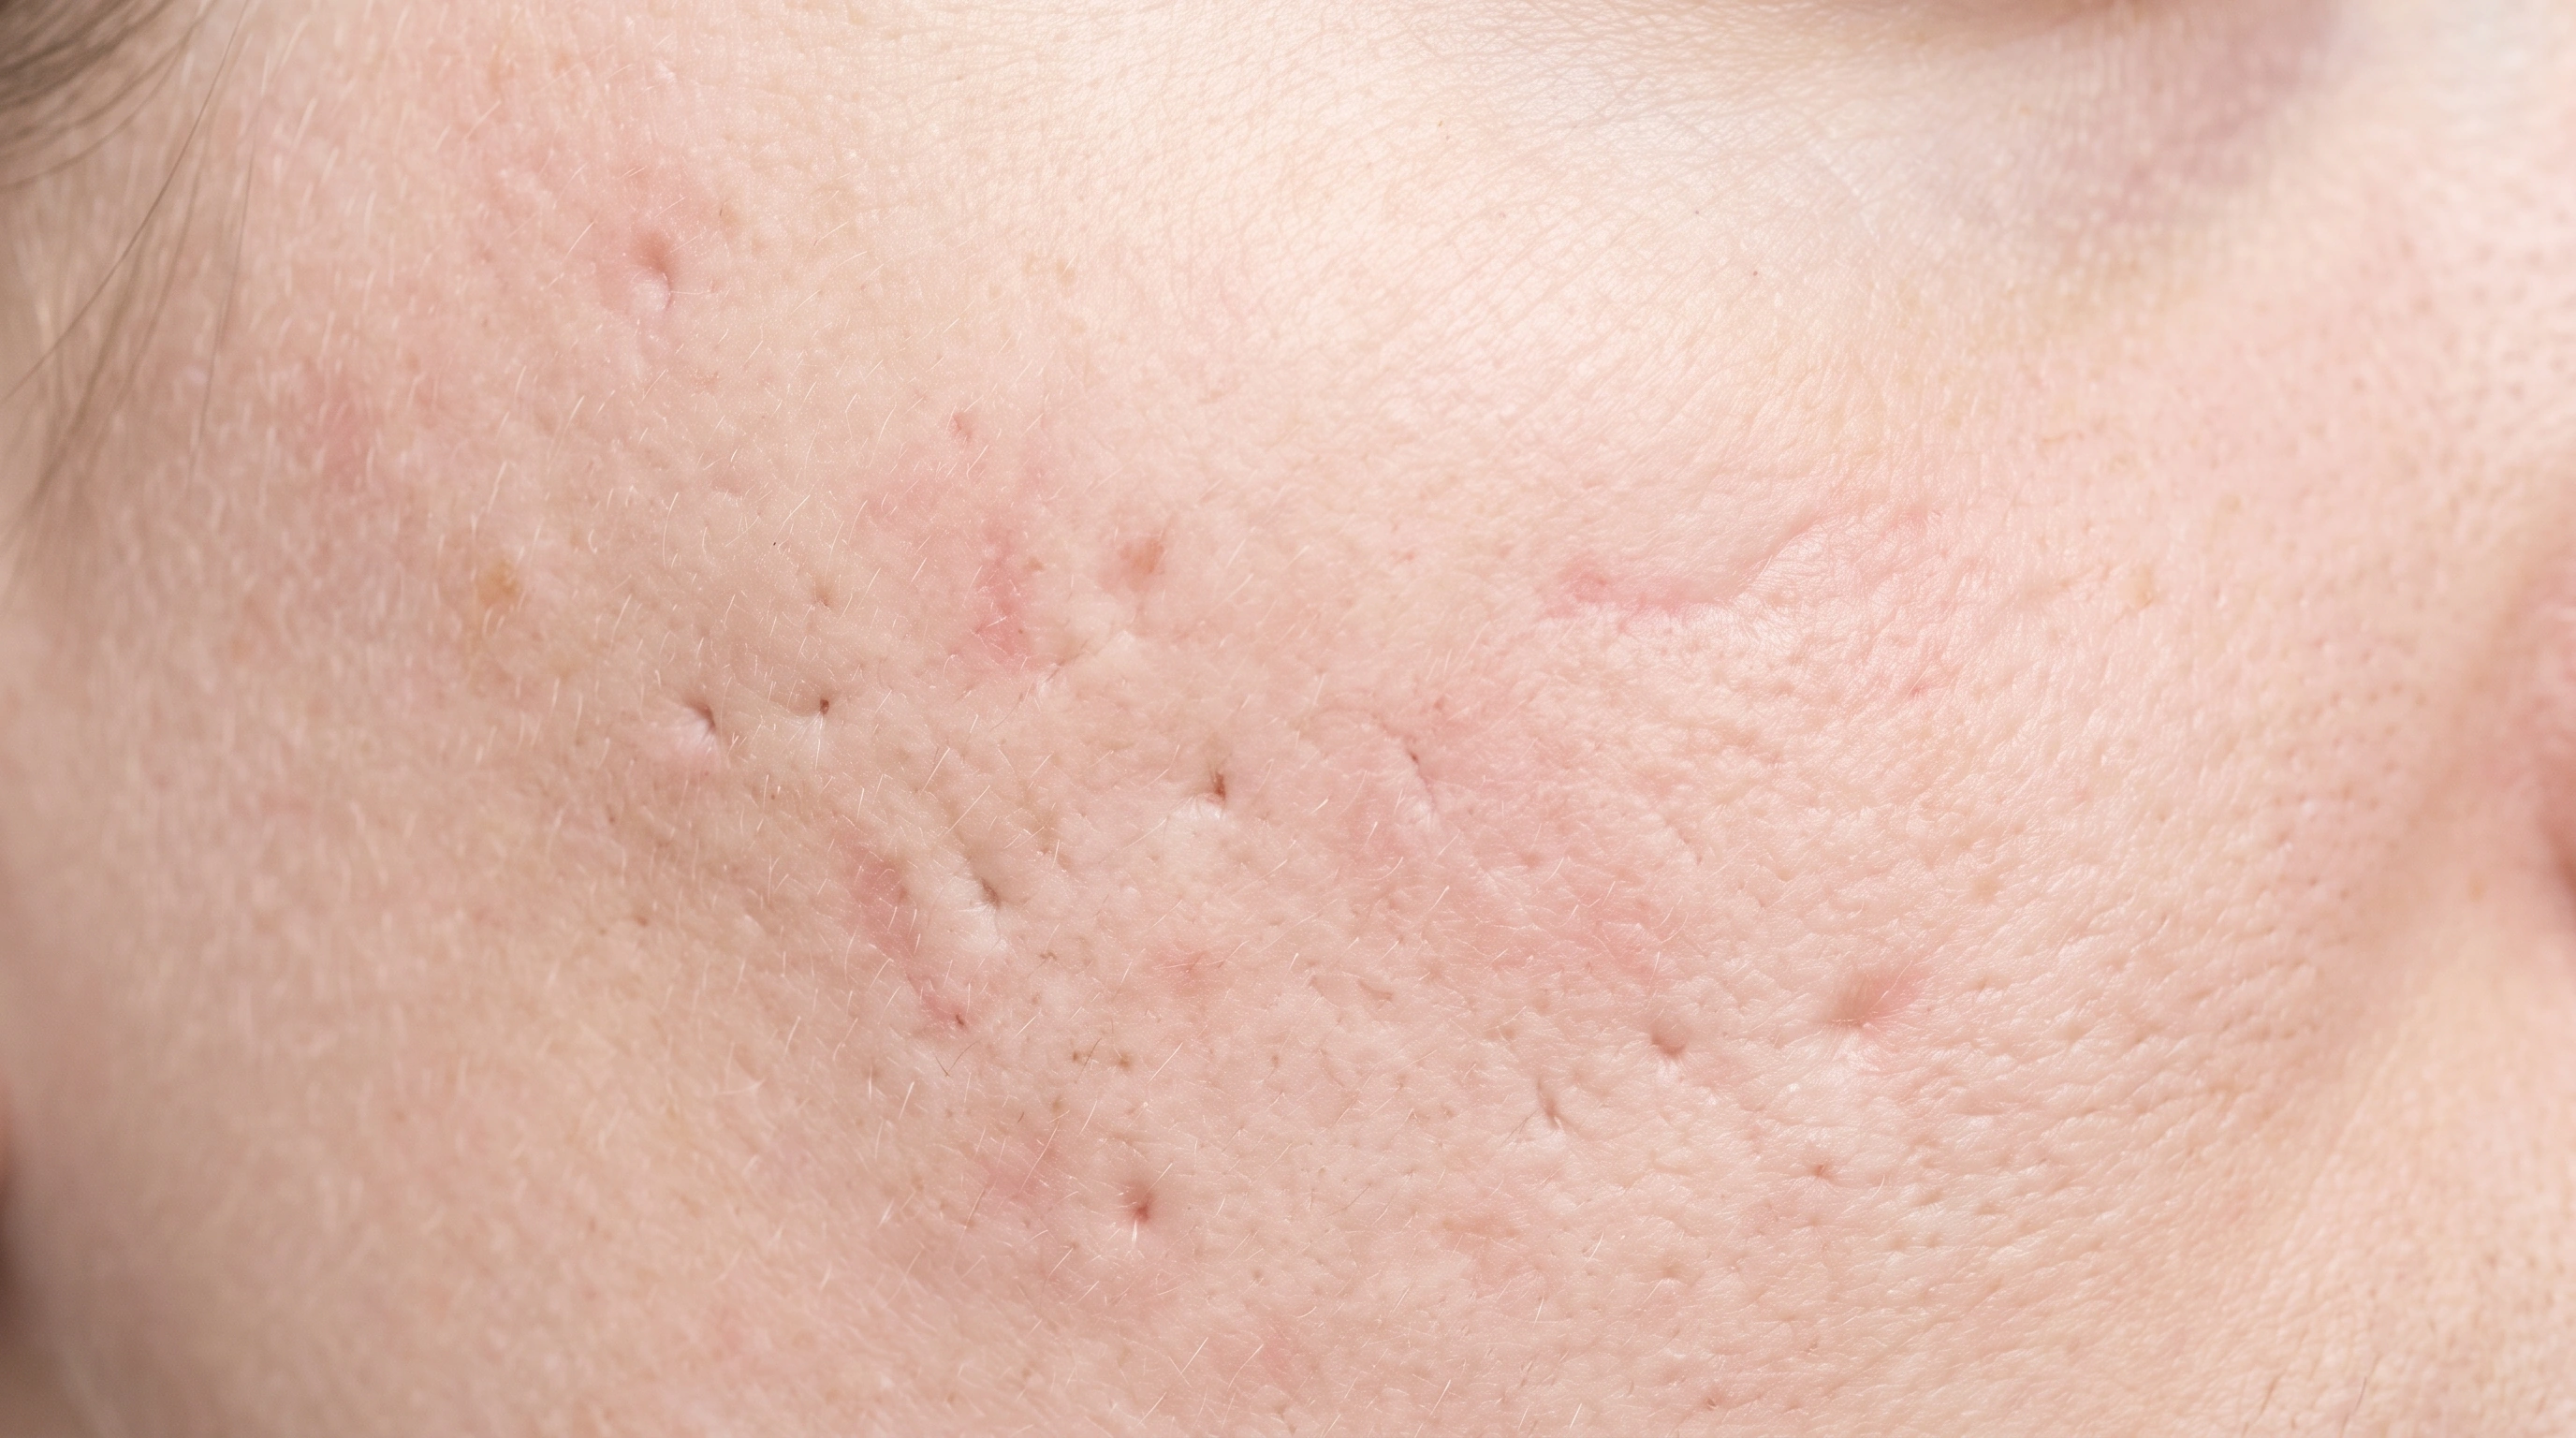
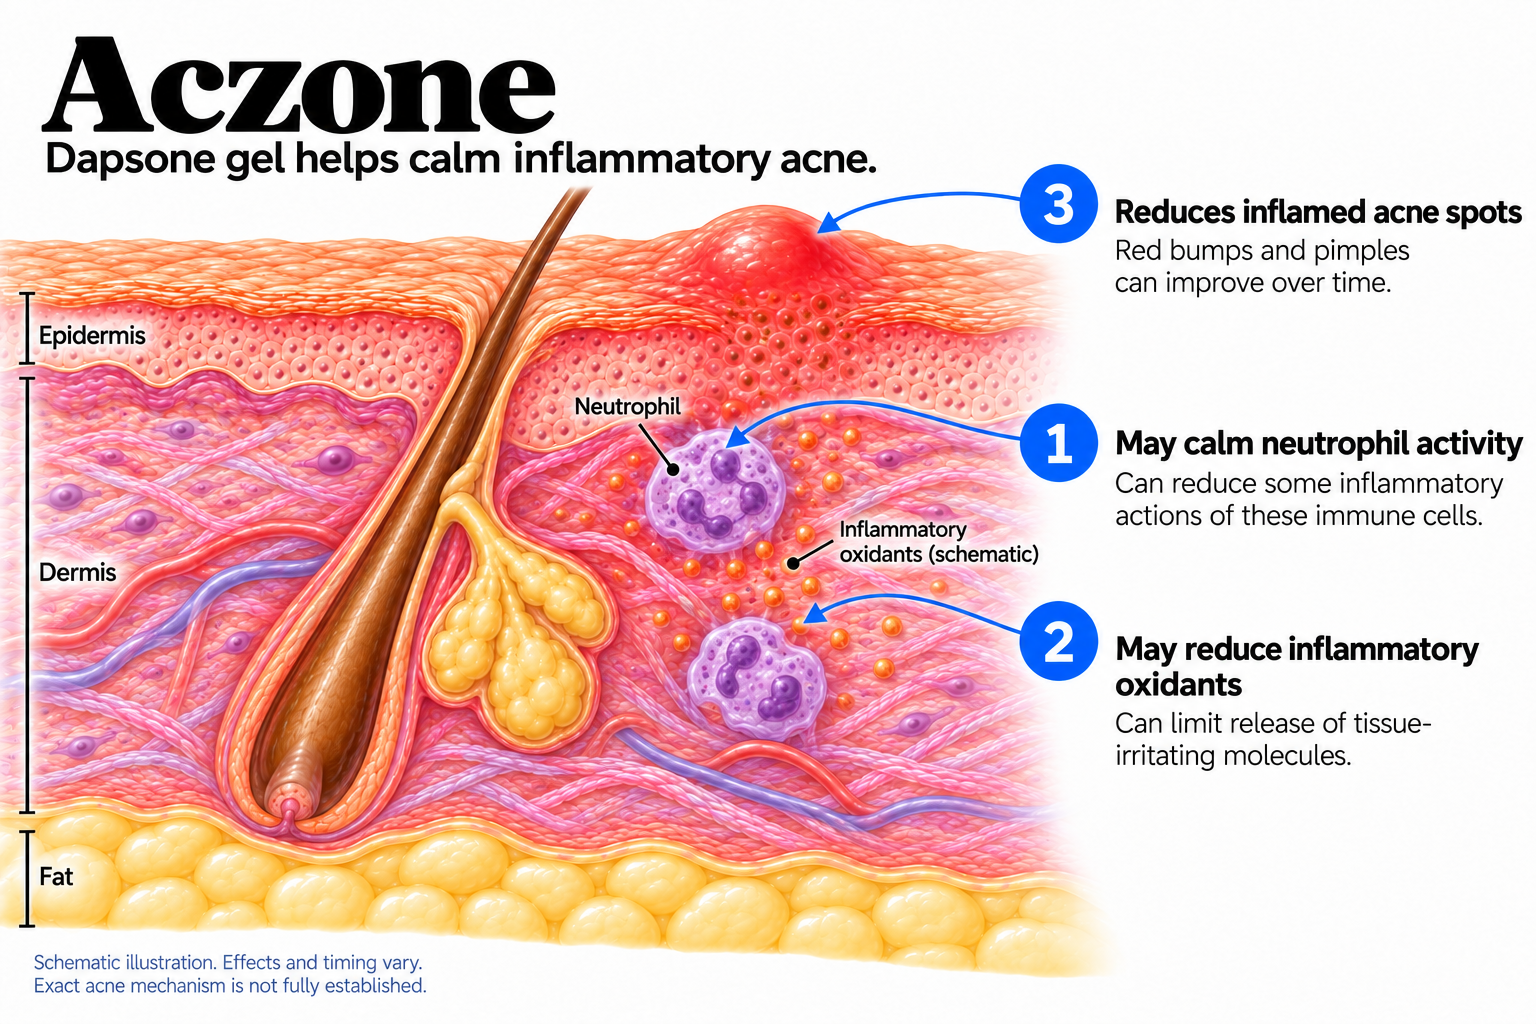
May calm neutrophil activity: Can reduce some inflammatory actions of these immune cells. May reduce inflammatory oxidants: Can limit release of tissue-irritating molecules. Reduces inflamed acne spots: Red bumps and pimples can improve over time.
The acne mechanism is unknown. Neutrophil and oxidant explanations are proposed based on experimental studies, not established as the cause of topical clinical benefit.

Calms inflammatory pathways: May reduce signals involved in rosacea inflammation. Normalizes cell buildup: Helps reduce excess keratin inside follicles. Limits acne bacteria: Has activity against susceptible C. acnes. Can help fade dark marks: Can inhibit tyrosinase, an enzyme used to make pigment.
Finacea 15% is labeled for rosacea inflammatory lesions; the full rosacea mechanism is unknown. Follicular, antimicrobial and pigment actions summarize azelaic-acid evidence across formulations, including 20%; acne and pigment use of this particular product may be off-label. KLK5/cathelicidin changes support a proposed inflammatory pathway. Tyrosinase inhibition is established in vitro; the complete clinical pigment mechanism is not established and 15% Finacea is labeled for rosacea rather than pigmentation.
When to Apply: Clean dry skin, whole affected area. The 7.5% gel once a day, the 5% gel twice, usually in the morning so the night is free for a retinoid.
How to Start: Full strength from day one. It dries clear and sits well under makeup and sunscreen.
If It Irritates: Uncommon — usually mild dryness a moisturizer settles. With benzoyl peroxide at the same moment it can turn skin temporarily orange-brown, which is harmless and avoided by using the two at different times of day.
If It’s Not Working: Give it twelve weeks. There is no step up in strength, so the next move is adding or changing a drug.
When to Apply: Twice a day on clean dry skin, a thin layer over the whole affected area, not on single spots. Moisturizer, sunscreen and makeup go on top once it has dried. Wash your hands afterwards.
How to Start: Once a day for the first week or two if your skin is reactive, then twice daily. Twice a day is what the trials did, and it is the part that quietly gets dropped.
If It Irritates: Stinging for a few minutes after applying is common in the first two weeks and usually stops. Moisturizer first, or back to once a day, settles it. The gel and the foam feel different, so switching form is worth asking about.
If It's Not Working: Give it twelve weeks of twice-daily use. There is no higher rosacea strength, so the next steps are ivermectin cream, an oral treatment such as doxycycline, or treating redness separately.
No routine blood tests for the gel. Unlike dapsone tablets, you do not need G6PD testing first, because so little is absorbed.
You can stay on this for years, and nothing accumulates. Review is clinical, at about twelve weeks and then yearly.
No blood tests or lab monitoring. Very little is absorbed, and what is absorbed is handled like the same compound from food.
Monitoring is a review at around twelve weeks: have the bumps reduced, is the twice-daily schedule being kept, is anything separate needed for redness. People stay on this for years.
Watch skin color. Pale patches on treated skin are reported, rarely, and are more noticeable in deeper skin tones. Show new lighter areas to a doctor.
Approximate windows, not promises.
Weeks 1 to 4Red, tender spots calm down. Blackheads and whiteheads look unchanged.
Weeks 4 to 8Fewer new inflamed spots.
Weeks 4 to 8Working: Fewer new bumps and pustules — the main target and the first thing to change. The face looks calmer before the count is obviously lower. Some background pink settles with it.
After 12 weeksIf inflamed acne has not improved, move on. Judge it on red spots only — it was never going to fix clogs.
First few minutesApplying it: Stinging, warmth or itching for a few minutes is common at the start.
Weeks 1 to 2Adjusting: Stinging settles, some dryness is normal, little visible change yet.
Weeks 8 to 12Judge it here: Most of the benefit seen in trials is in by twelve weeks of twice-daily use.
Weeks 12 to 16Dark marks: Brown marks left where spots healed start to fade. Slower than the bumps.
OngoingMaintenance: People who continue hold their improvement. Bumps return within a few months of stopping.
Sorted by what to do about them.
Generic dapsone gel comes in both strengths and costs far less than it used to, though still more than generic clindamycin or benzoyl peroxide. Some plans want prior authorization, usually after a retinoid.
Better than most rosacea options. The 15% gel has generics in many markets, which brings the price down a lot; the foam is more often brand priced. Coverage is easier than for the redness creams, because bumps and pustules count as medical rather than cosmetic.
Over-the-counter 10% costs less again and is a reasonable start for mild cases.
If cost is the issue, price the generic 15% gel first.
Benzoyl peroxide and dapsone applied together can leave a temporary orange-brown tint on skin and light-colored facial hair. It washes off and is harmless. Use them hours apart.
Not for the gel. That belongs to dapsone tablets, where far more of the drug reaches the bloodstream.
No. It works on inflammation. Blackheads need a retinoid.
No. It is a sulfone with anti-inflammatory action, which is why resistance is not the same concern.
For rosacea, the published evidence is at 15%. Ten percent is a reasonable start, but if three months has changed nothing, move to the prescription strength.
Both are 15% and studied for rosacea. The gel dries quickly and suits oilier skin; the foam spreads more easily and is more comfortable on dry or sensitive skin. Choose on feel.
Expected in the first couple of weeks. It lasts a few minutes after applying and stops as the skin adapts. Starting once daily makes it easier.
Partly. As the inflamed bumps settle, the pink around them settles too. It does not narrow blood vessels, so flushing and visible capillaries need something else.
Yes — routinely with a redness treatment, ivermectin cream, or oral doxycycline. Split them between morning and night to keep irritation down.
Doctors commonly consider azelaic acid when other treatments have to stop, but that decision belongs to the doctor managing your pregnancy.