Psoriasis
Clears or nearly clears skin in most patients.
Skyrizi: An injected biologic for moderate to severe plaque psoriasis. It blocks interleukin-23, a signal that sits high up in the psoriasis chain, and after two starting doses it is given about four times a year. Tazarotene: A strong prescription retinoid for acne, psoriasis and sun damage. It does more than the gentler retinoids and irritates more, and it must not be used in pregnancy.


Choose for moderate to severe psoriasis when you want high clearance with only about four injections a year.
Choose for acne or psoriasis that needs a stronger retinoid than tretinoin or adapalene, and you can tolerate more irritation.
Can you take them together?
Tazarotene can be used on remaining plaques while on Skyrizi. It does not interact with the biologic.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

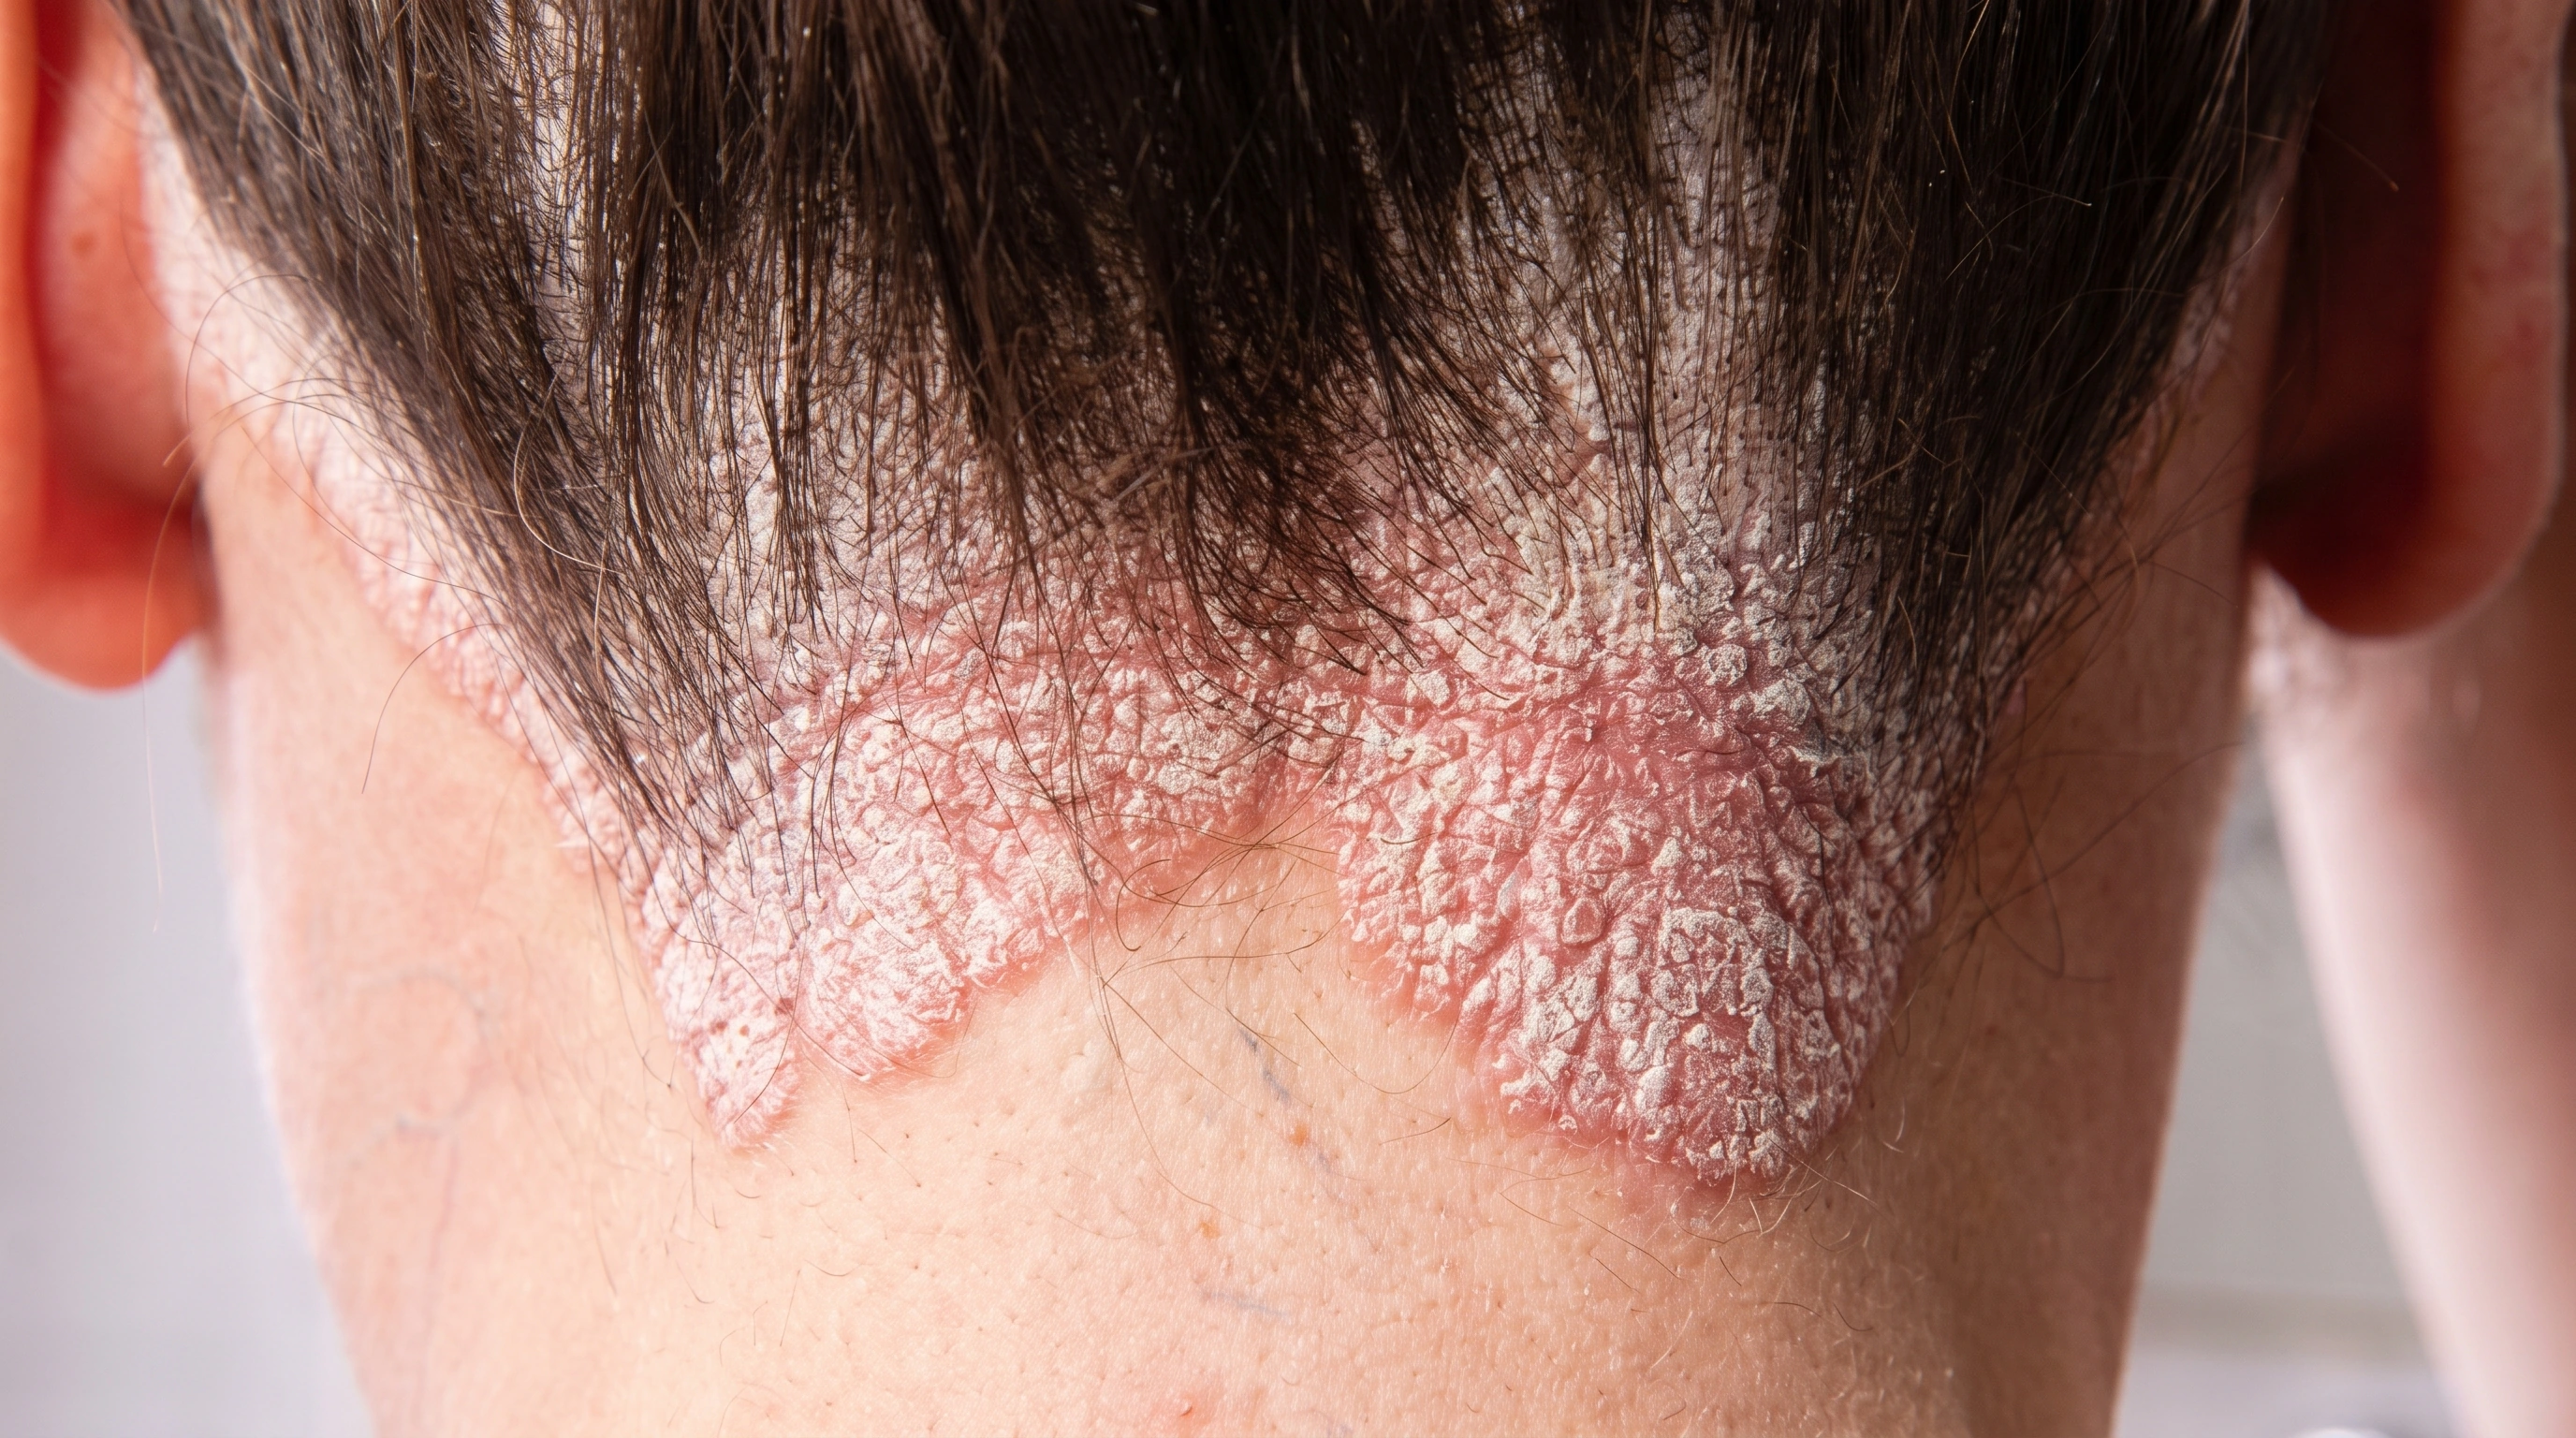



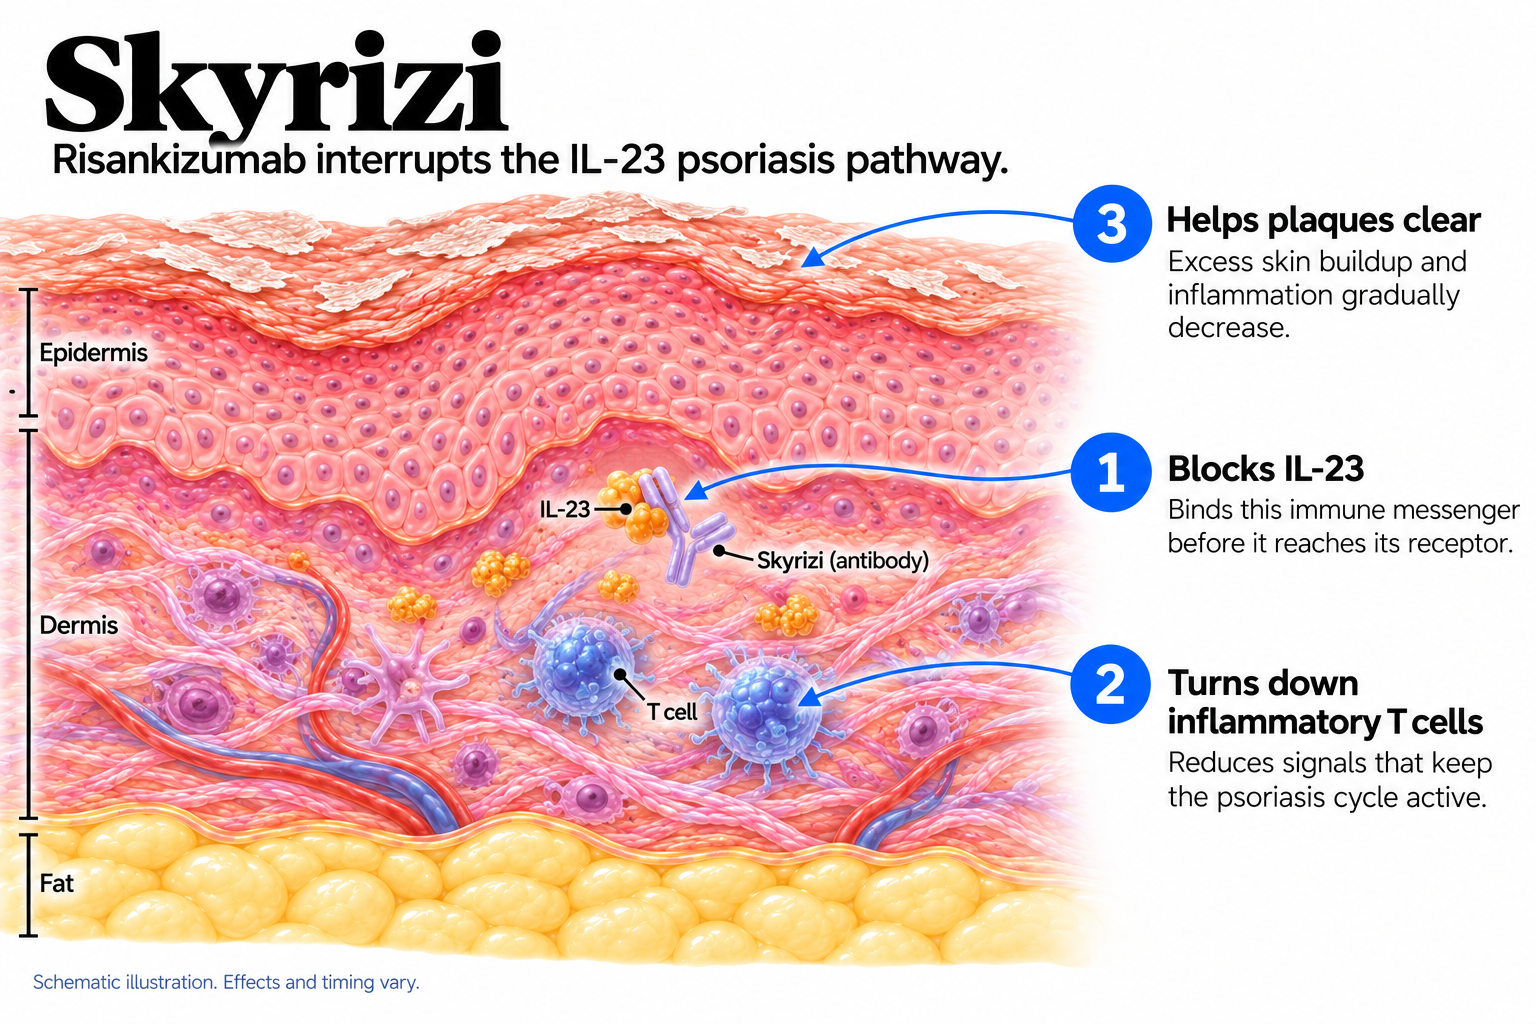
Blocks IL-23: Binds this immune messenger before it reaches its receptor. Turns down inflammatory T cells: Reduces signals that keep the psoriasis cycle active. Helps plaques clear: Excess skin buildup and inflammation gradually decrease.
Risankizumab selectively targets the p19 subunit of IL-23, not IL-12. The T-cell and skin changes are a simplified downstream interpretation.

Activates retinoid receptors: Skin converts it to an active form that changes gene signals. Helps unclog pores: Normalizes cell buildup inside follicles. Reduces excess skin growth: Helps psoriasis cells grow and mature more normally. Improves sun-damaged skin: Can improve fine wrinkles and uneven pigmentation.
Tazarotene is converted to tazarotenic acid, which preferentially activates RAR-beta/gamma. Full clinical mechanisms are not defined. Acne, psoriasis and photodamage evidence comes from different formulations/strengths; clinical benefits are not guaranteed.
Two starting doses close together, then a long steady interval. Not adjusted for body weight.
Starting dose: 150 mg as one injection.
Second dose: 150 mg, four weeks after the first.
Usual dose: 150 mg every 12 weeks — about four injections a year after the first year.
If it stops working: There is no approved higher dose or shorter interval for psoriasis. Losing response means reviewing the diagnosis, not injecting more often.
How long: Long term, with no set end point, while it works and is tolerated.
When to Apply: At night only, on completely dry skin — about twenty minutes after washing, because damp skin absorbs more and stings more. A pea-sized amount covers the whole face. Moisturizer underneath, on top, or both. Sunscreen every morning is part of the treatment.
How to Start: Two or three nights a week for the first two to four weeks, then build toward nightly as the skin allows. Most people who quit started nightly. For thick psoriasis plaques some doctors use short contact — applied, then washed off after twenty to thirty minutes — but only if you were told to.
If It Irritates: Moisturizer before and after, drop back a night or two a week, and take two or three nights off if the skin is raw. Do not scale up other actives at the same time. Cold, wind and hot showers make it worse.
If It’s Not Working: Give it a full twelve weeks. If acne is still active, step up the strength, change to the gel, or add benzoyl peroxide or an oral option. Check first that you are treating the whole area, not dabbing spots.
Any time of day. The calendar matters more here than with a weekly drug. Twelve weeks is long enough that people lose track, so put every dose date in your phone and book the next reminder the day you inject.
Take it out of the fridge 15 to 30 minutes before and let it warm on the counter. Cold liquid stings. No hot water, no microwave.
Inject into the front of the thigh or the belly, at least two inches from the navel. The back of the upper arm works if someone else is doing it. Rotate the site, avoid skin that is bruised, tender, hard or scarred, and never inject through a plaque. Ask for training before the first dose. Used devices go in a sharps container.
Inject as soon as you remember, then count twelve weeks from that day. If it has been much longer than twelve weeks, call the prescriber first so the schedule can be reset.
Everyone is screened for tuberculosis before the first dose — a skin test or TB blood test, plus a chest X-ray if that is positive. Dormant TB is treated first. This class probably carries less TB risk than the TNF blockers, but screening is not optional.
Hepatitis B and C are usually checked at the same time.
After that there is no fixed blood test schedule. Risankizumab does not need the regular liver and blood count testing methotrexate does. Monitoring is clinical: the skin, whether infections are more frequent, whether the dose dates are kept. TB testing is repeated yearly or by exposure risk.
There is no boxed warning. The most common side effects reported are upper respiratory infections, headache, tiredness, fungal skin infections and injection site reactions. Serious allergic reactions are rare but are why the first dose is often given with someone trained nearby.
No blood tests are needed. Two things get monitored: how the skin is tolerating it, and pregnancy status.
Because tazarotene is contraindicated in pregnancy, anyone who could become pregnant should expect a conversation about reliable contraception before starting, and in some settings a pregnancy test. Very little reaches the bloodstream, but the restriction is absolute.
The other checkpoint is a review at around twelve weeks: hold the strength, step up, or add something. People stay on this for years, and nothing accumulates that needs testing.
Approximate windows, not promises.
First few minutesThe injection: A sharp sting for a few seconds, then redness or a small welt. Settles within a day or two.
First few minutesApplying it: A pea-sized amount on dry skin at night. Mild stinging is normal.
Weeks 1 to 4Starting: Itch settles first. Scale lifts and plaques thin.
Weeks 1 to 4The adjustment: Dryness, flaking around the nose and mouth, mild redness, peaking in weeks two to three. Acne can look worse first as forming clogs surface.
Weeks 4 to 16Working: Most of the change happens here, from the second dose on. Plaques flatten and redness fades from the middle out, often leaving a paler or darker mark.
Week 16Judge it here: Most people reached 90 percent clearer skin, and many were clear or nearly clear. Joints improve on the same timeline.
3 to 6 monthsScalp, palms and soles: Slower than the trunk and limbs.
6 to 12 monthsNails: Last to change, because a nail takes months to grow out.
Between dosesSteady state: Most people notice no dip. If plaques reliably return in the last few weeks, say so.
Weeks 4 to 8Adapting: Peeling settles and new spots get less frequent. Most quit before reaching this.
Weeks 8 to 12Judge it here for acne: Fewer new spots, fewer blackheads and whiteheads. Trials measured here, and it keeps building. Psoriasis plaques thin on the same timeline and often stay thinner after stopping.
4 to 6 monthsTexture and fine lines: Gradual smoothing. A months-to-years treatment, not a course.
6 months or moreMottled pigment and dark marks: The slowest of all. Sunscreen does as much work as the retinoid.
ThroughoutSun and flushing: Skin burns more easily, so daily sunscreen is not optional. Stinging, and a flush after alcohol or hot drinks, settle.
Sorted by what to do about them.
The list price runs to tens of thousands of dollars a year. Almost nobody pays that; what you pay depends on your plan.
It is brand only — no generic, no biosimilar — so there is no cheaper equivalent to switch to. That is a real difference from adalimumab.
Prior authorization is close to universal. Most plans require documented failure of something cheaper first — phototherapy, methotrexate, sometimes another biologic. Denials are usually about missing records rather than the drug, and appeals succeed reasonably often when the history is documented.
Manufacturer copay cards can cut the cost to very little with commercial insurance. By law they cannot be used with Medicare or Medicaid. For those plans, or no insurance, the manufacturer's patient assistance program and independent foundations are the usual routes. Terms change often.
One practical note: because doses are twelve weeks apart, a change of insurance or a formulary switch in January can land in the middle of a dosing gap. Check coverage before the next dose is due, not the week it is.
This is the honest weak point. The lotion and the foam are brand-only and expensive, coverage is inconsistent, and prior authorization is common — plans usually want a cheaper retinoid tried first.
Generic cream and gel cost considerably less, though still more than tretinoin. Adapalene is sold without a prescription in many places and is the least expensive retinoid. If cost is the barrier, ask about generic cream or gel at 0.05%.
A large protein grown in living cells rather than a chemical made in a factory. That is why it is injected, and why it lives in the fridge.
After the first two doses, four weeks apart, yes. The drug stays in the body long enough that the gap can be twelve weeks.
A few seconds of stinging. Letting it warm to room temperature first makes a noticeable difference.
Tuberculosis and hepatitis before you start, and TB testing often repeated yearly. Beyond that, no routine schedule.
Inject when you remember and count twelve weeks from that day. If you are weeks or months late, call first.
Yes, apart from live ones. The flu shot, COVID vaccines and Shingrix are not live. Have any live ones before starting.
Little for the first month, real change between weeks eight and twelve. Texture and pigment take longer.
Clogs already forming are being pushed to the surface sooner. It settles by weeks six to eight.
No. Tazarotene is contraindicated in pregnancy and should be stopped before trying to conceive. Ask your doctor what to use instead.
Generally yes, and more irritating for the same reason. Whether it works better depends on whether you can use it consistently.
Yes — about a week beforehand, and tell whoever is treating you that you use a prescription retinoid.
Yes. Unlike tretinoin, it is not broken down by benzoyl peroxide. The pair can be drying, so use one in the morning and one at night.