Shingles vs Folliculitis

Shingles is a painful, blistering rash that follows one nerve on one side of the body. It is caused by the chickenpox virus waking up years later. Antiviral tablets help most when they are started within three days of the rash appearing.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
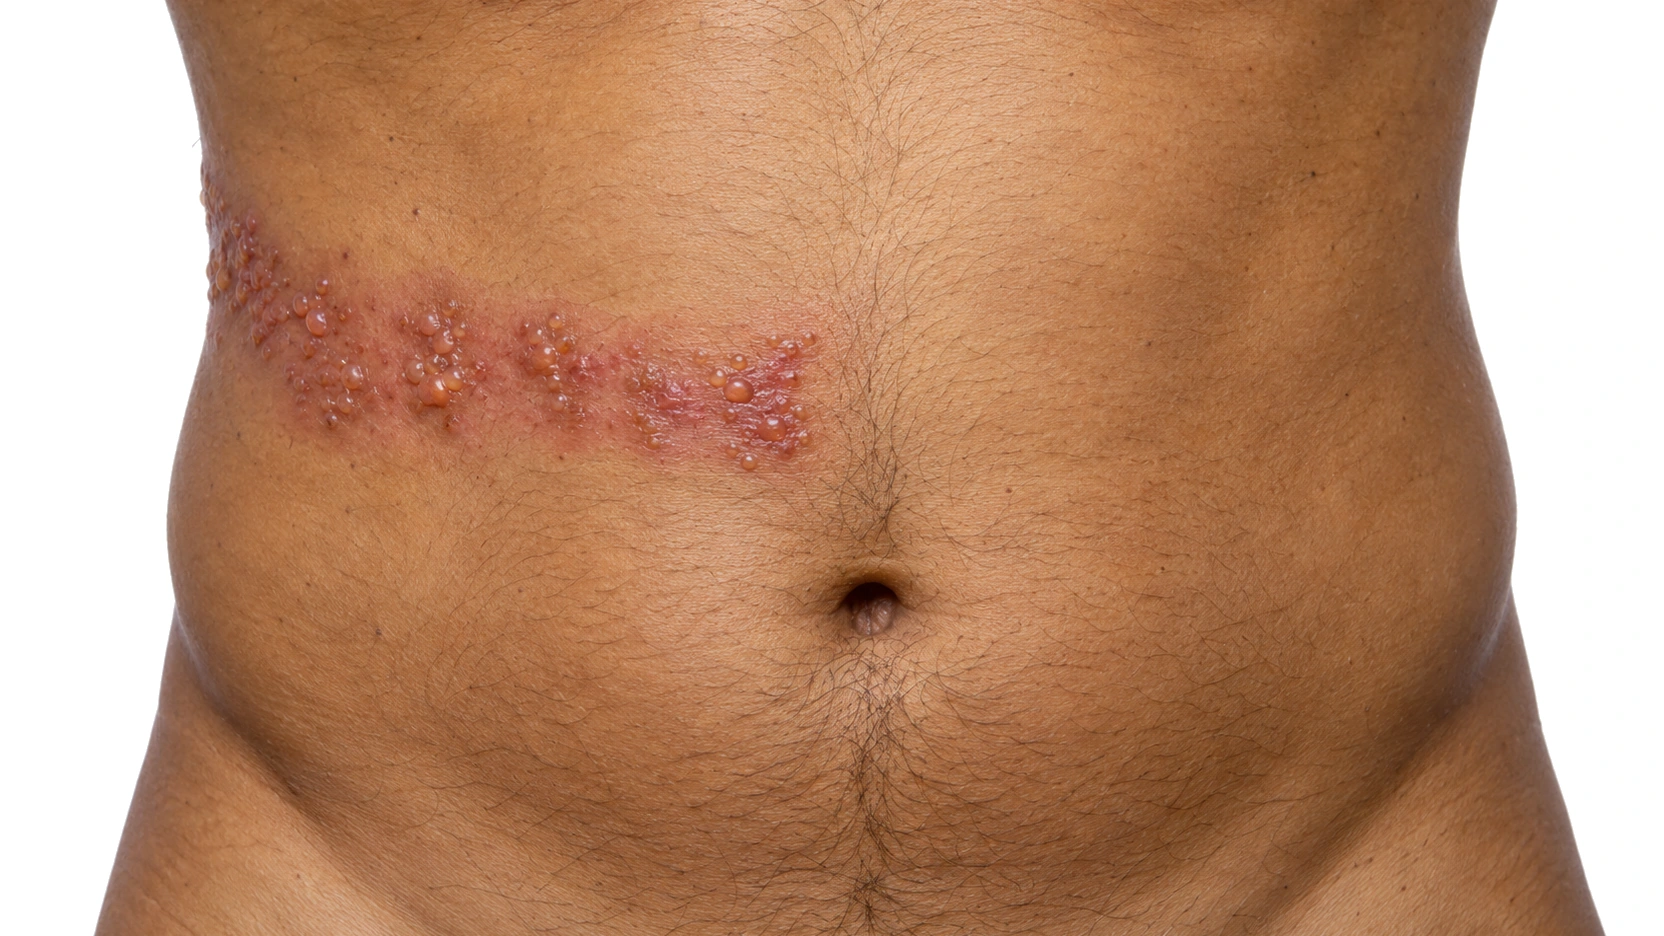
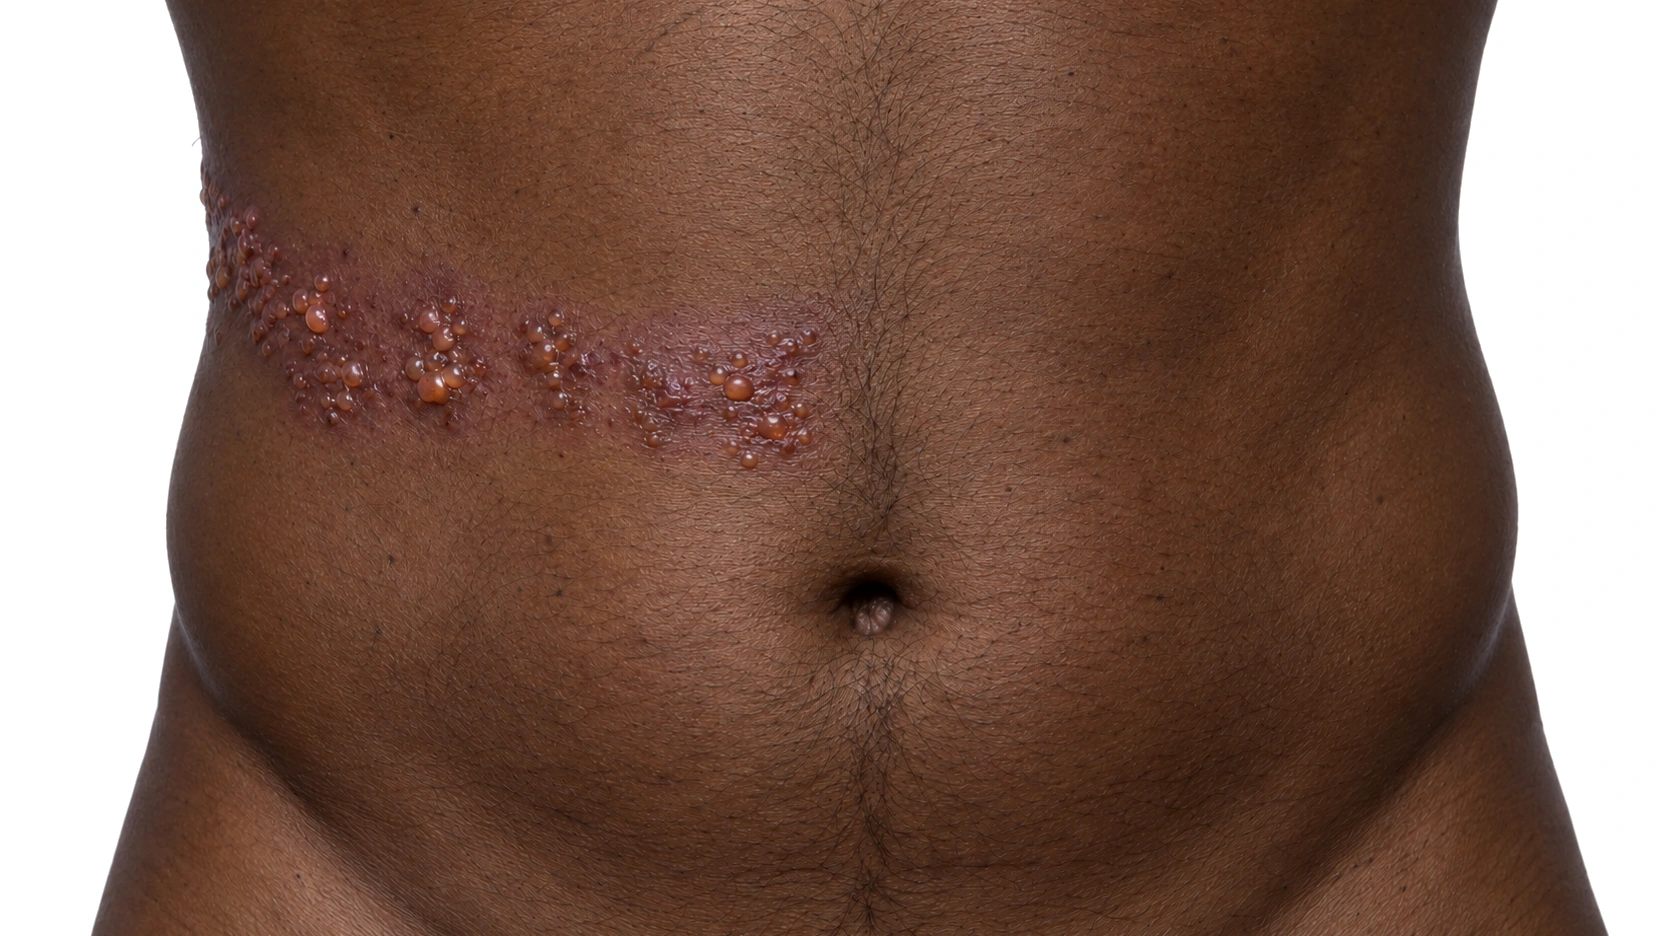
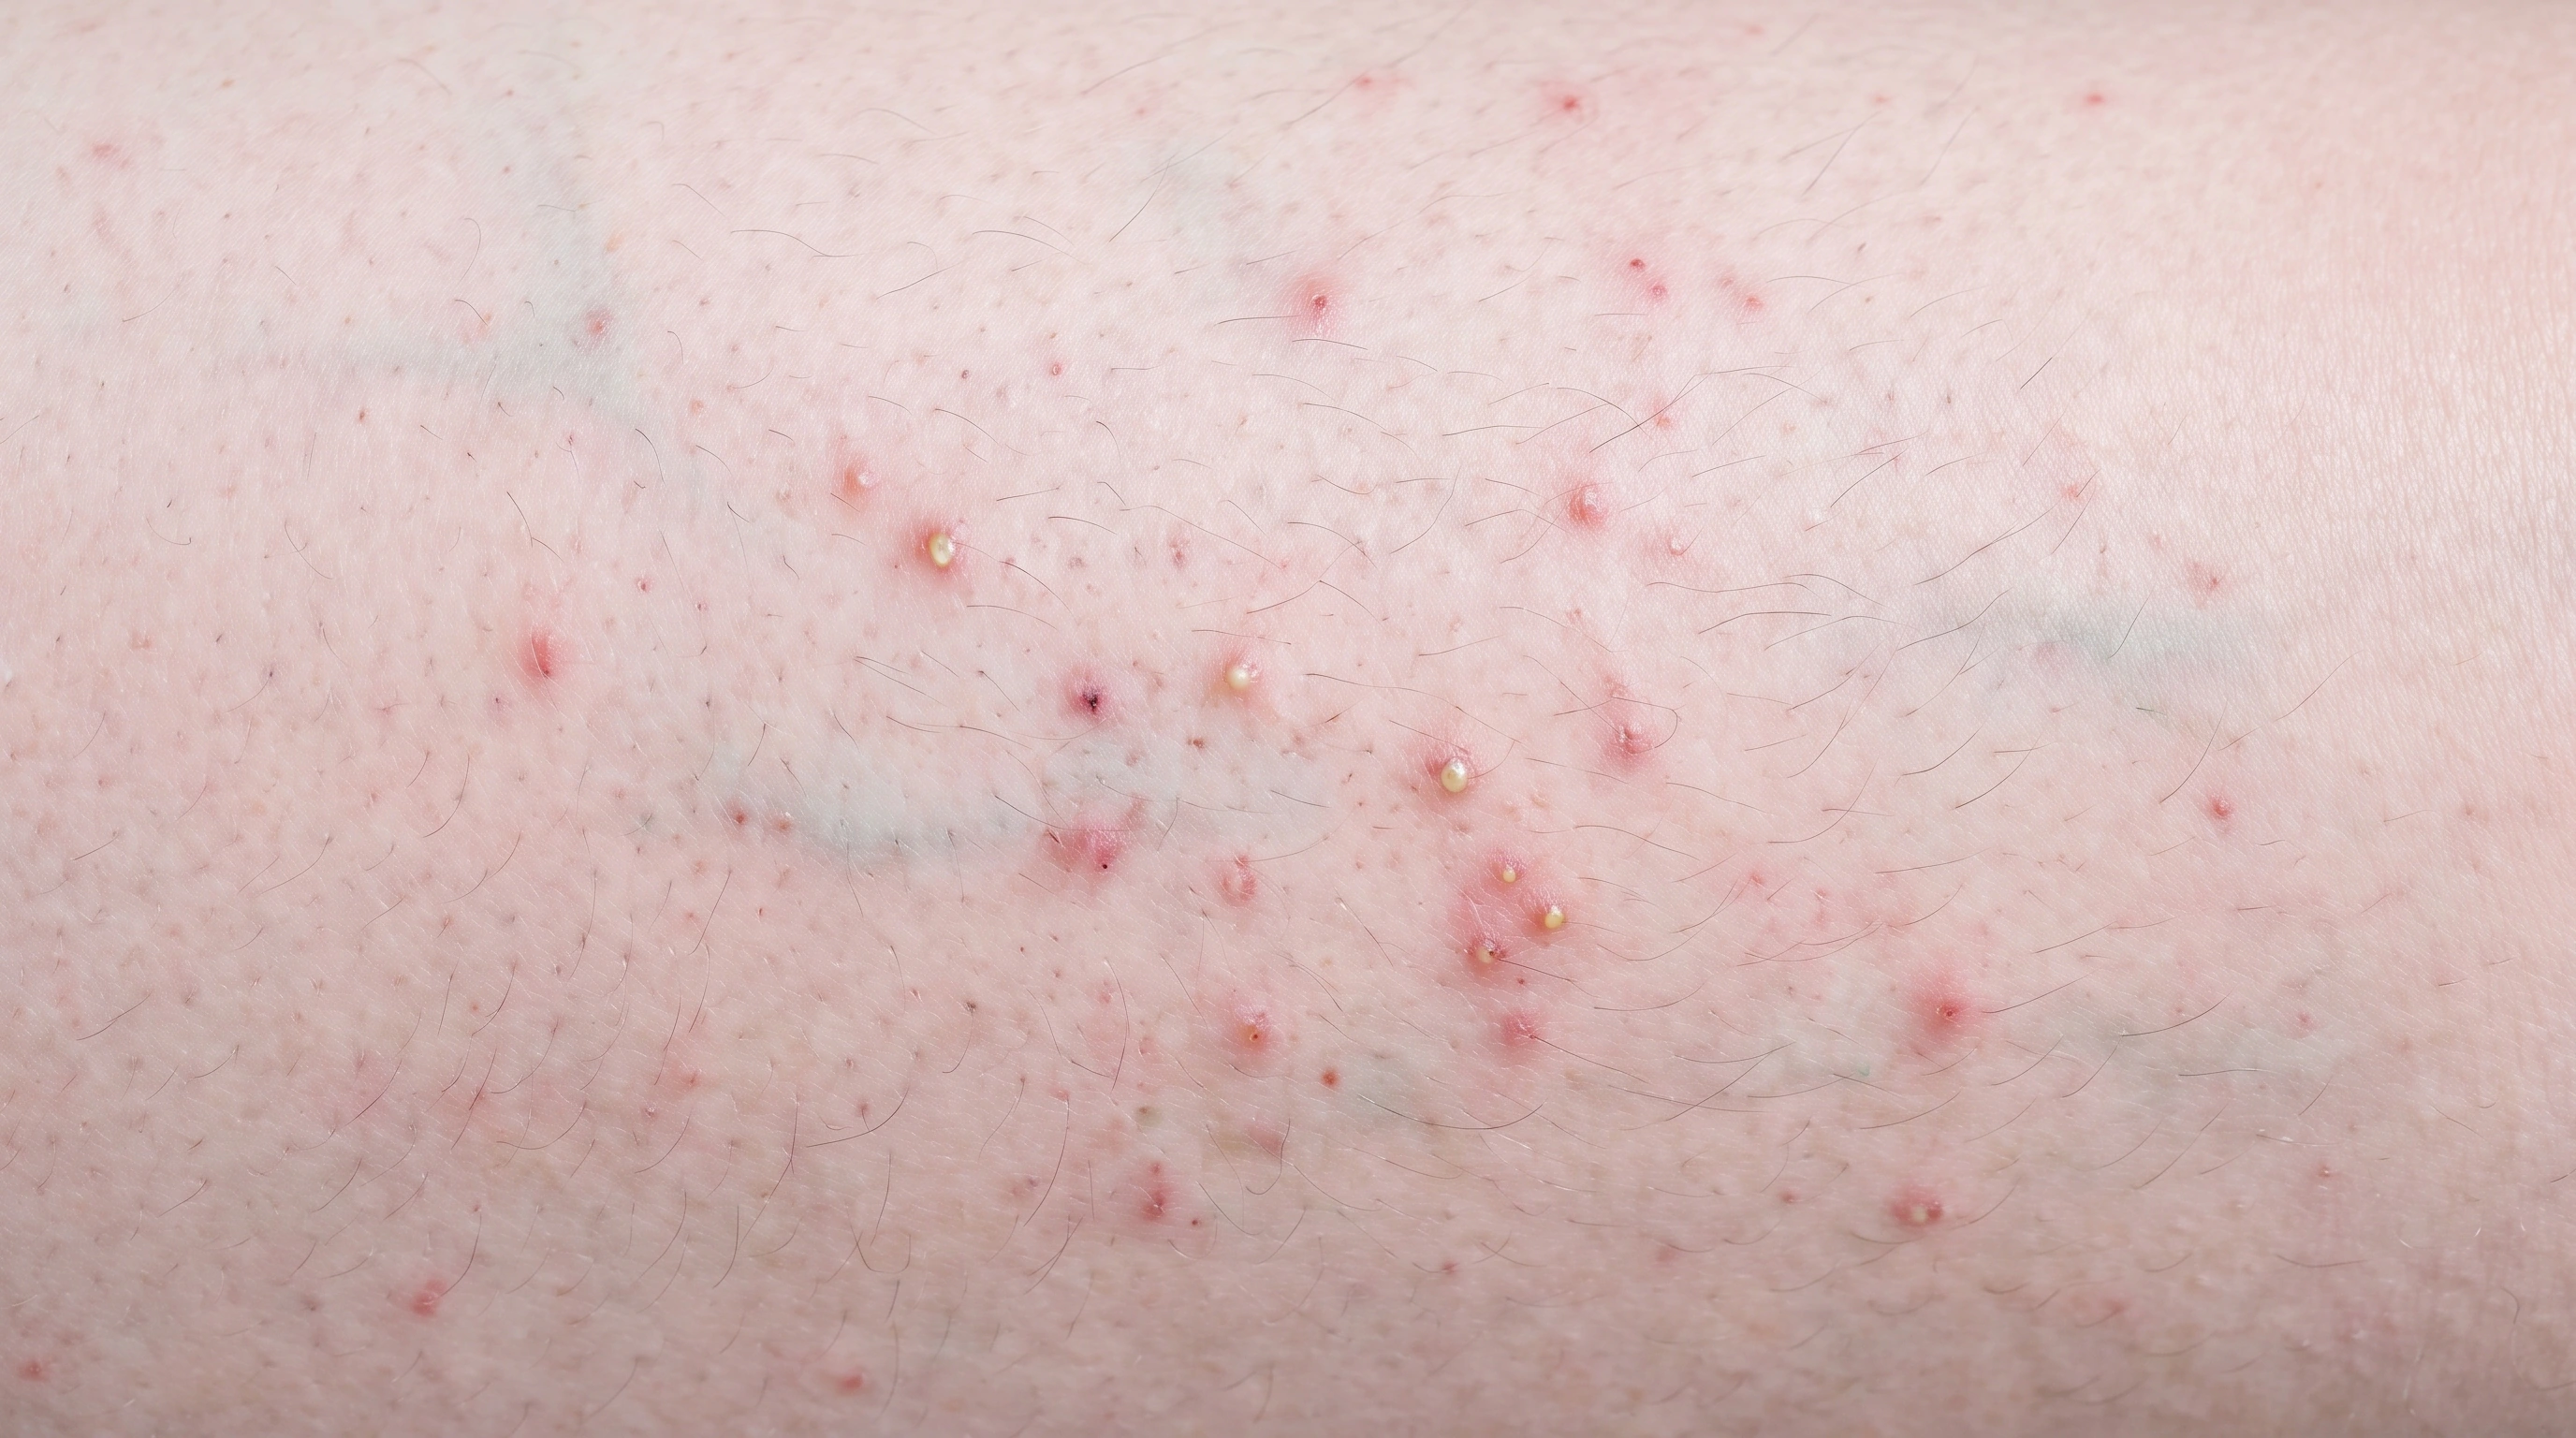
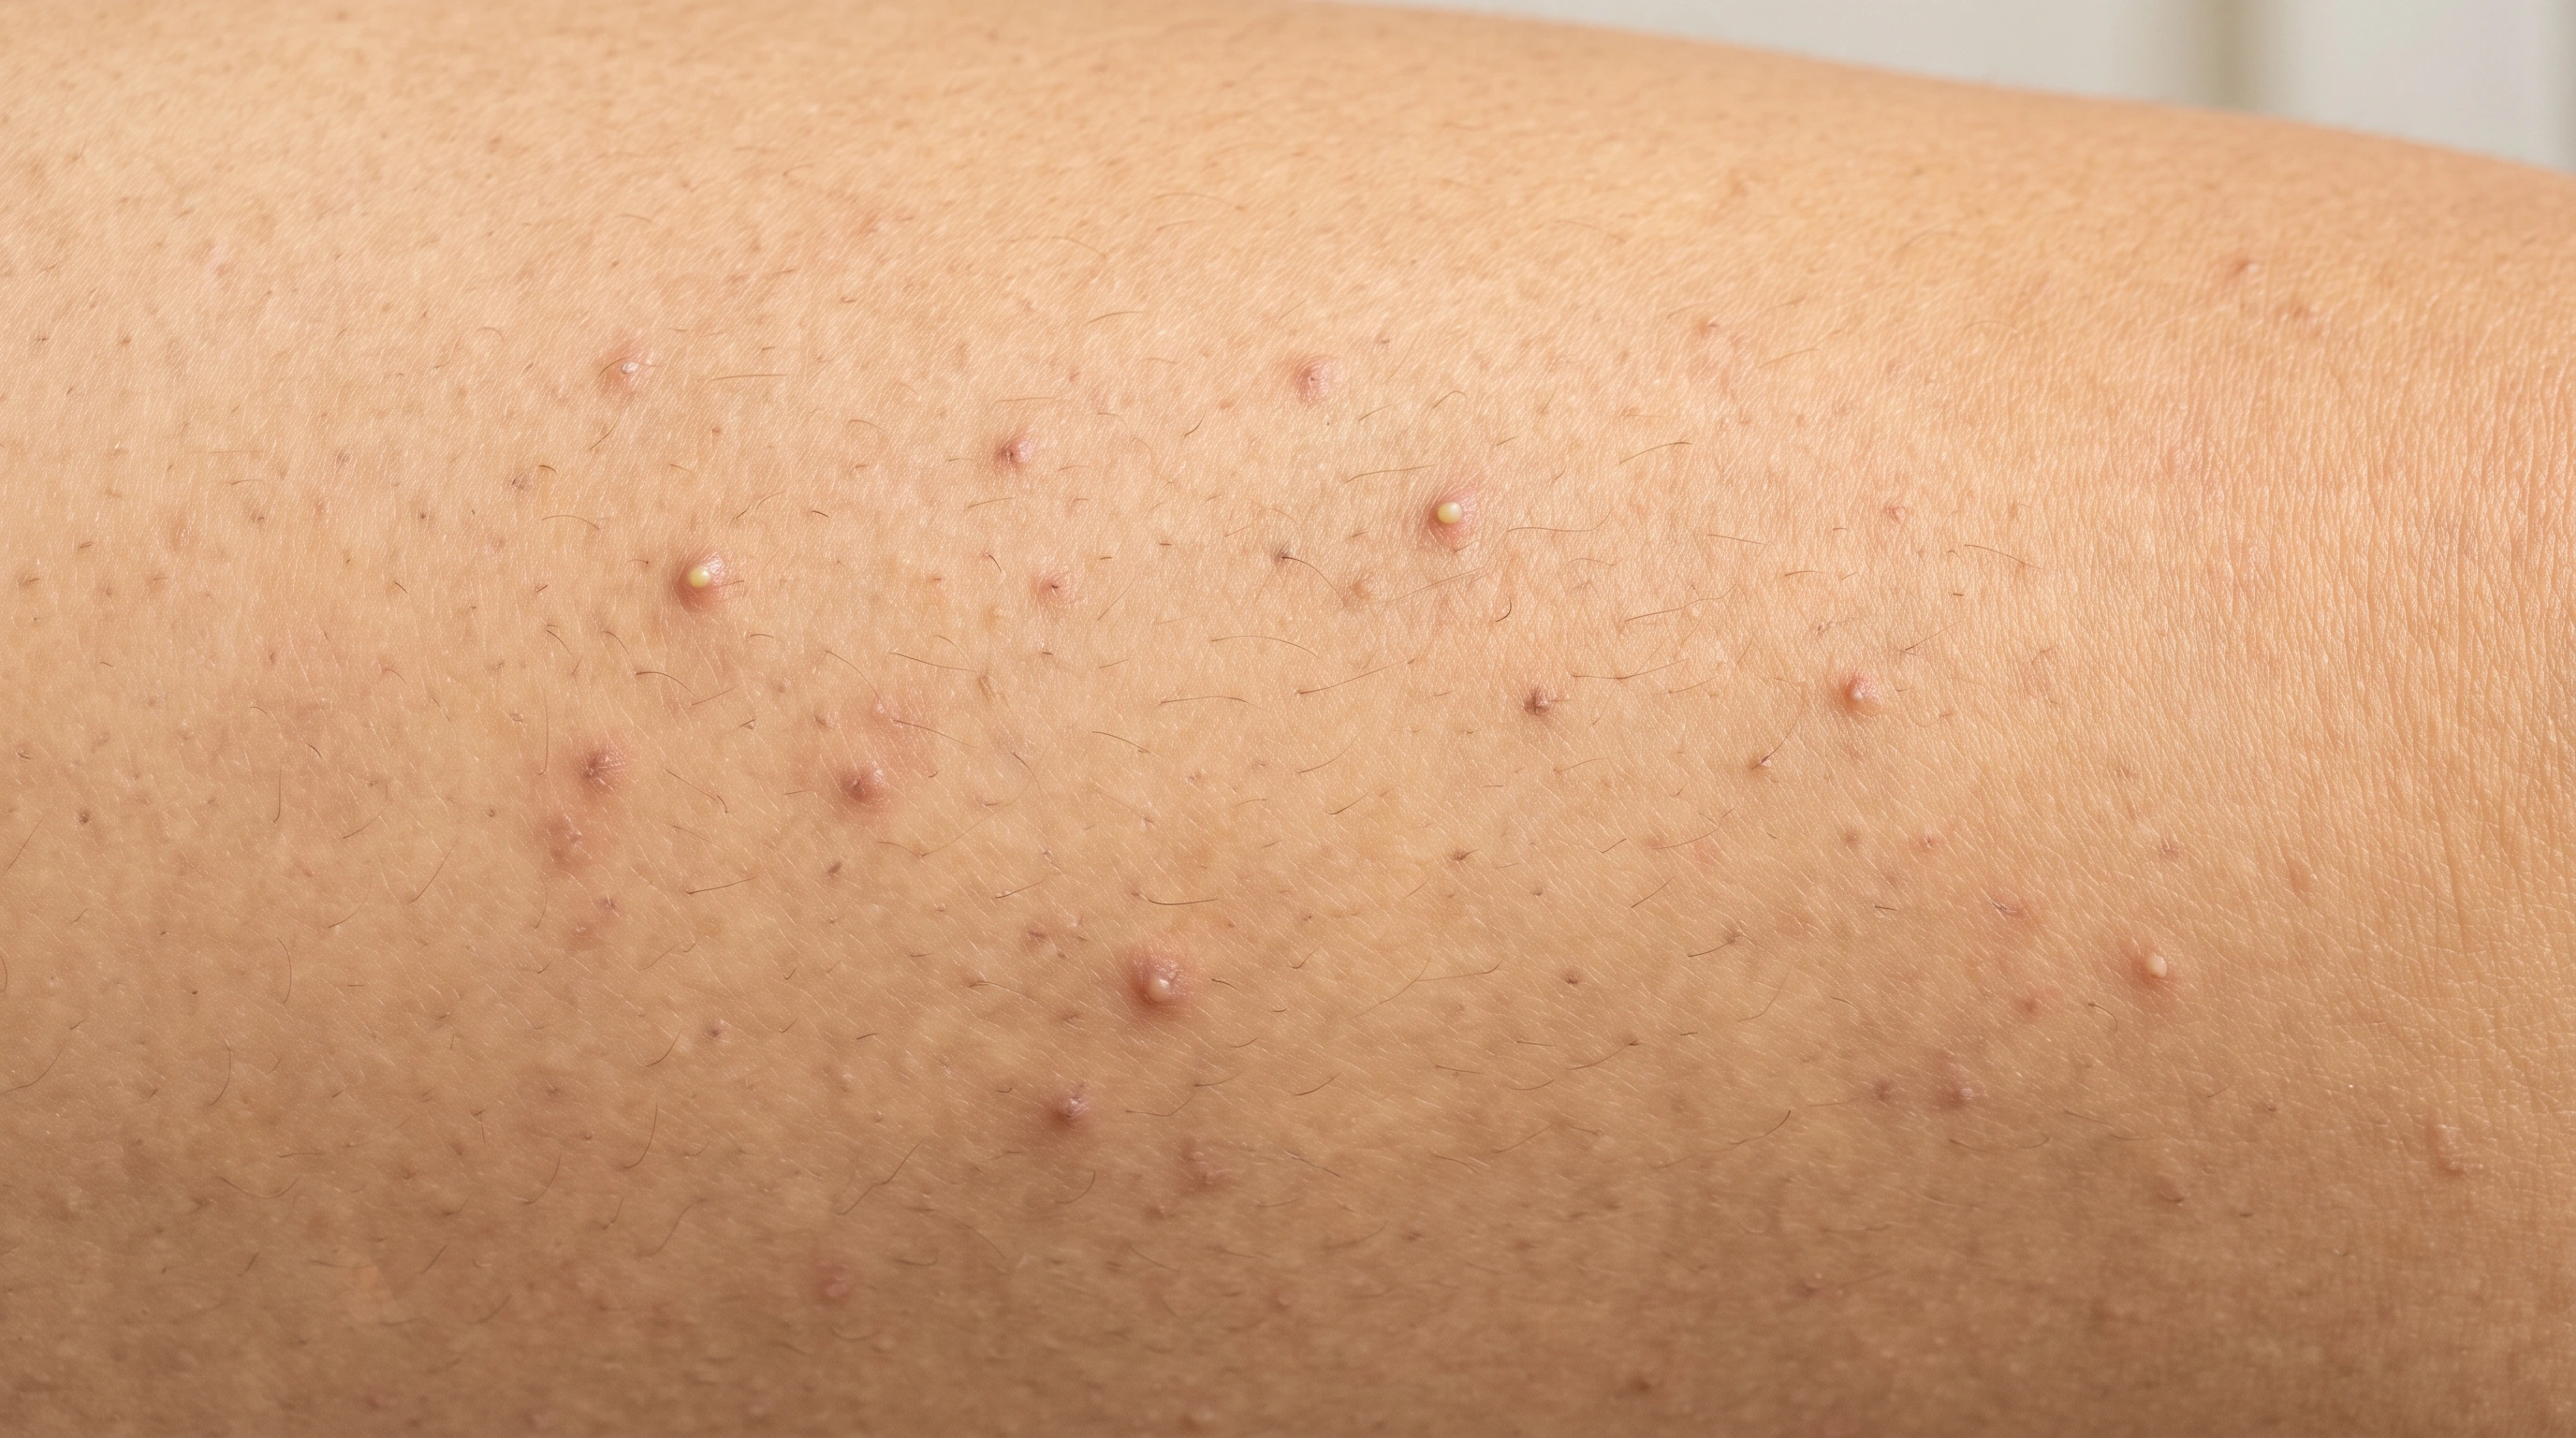
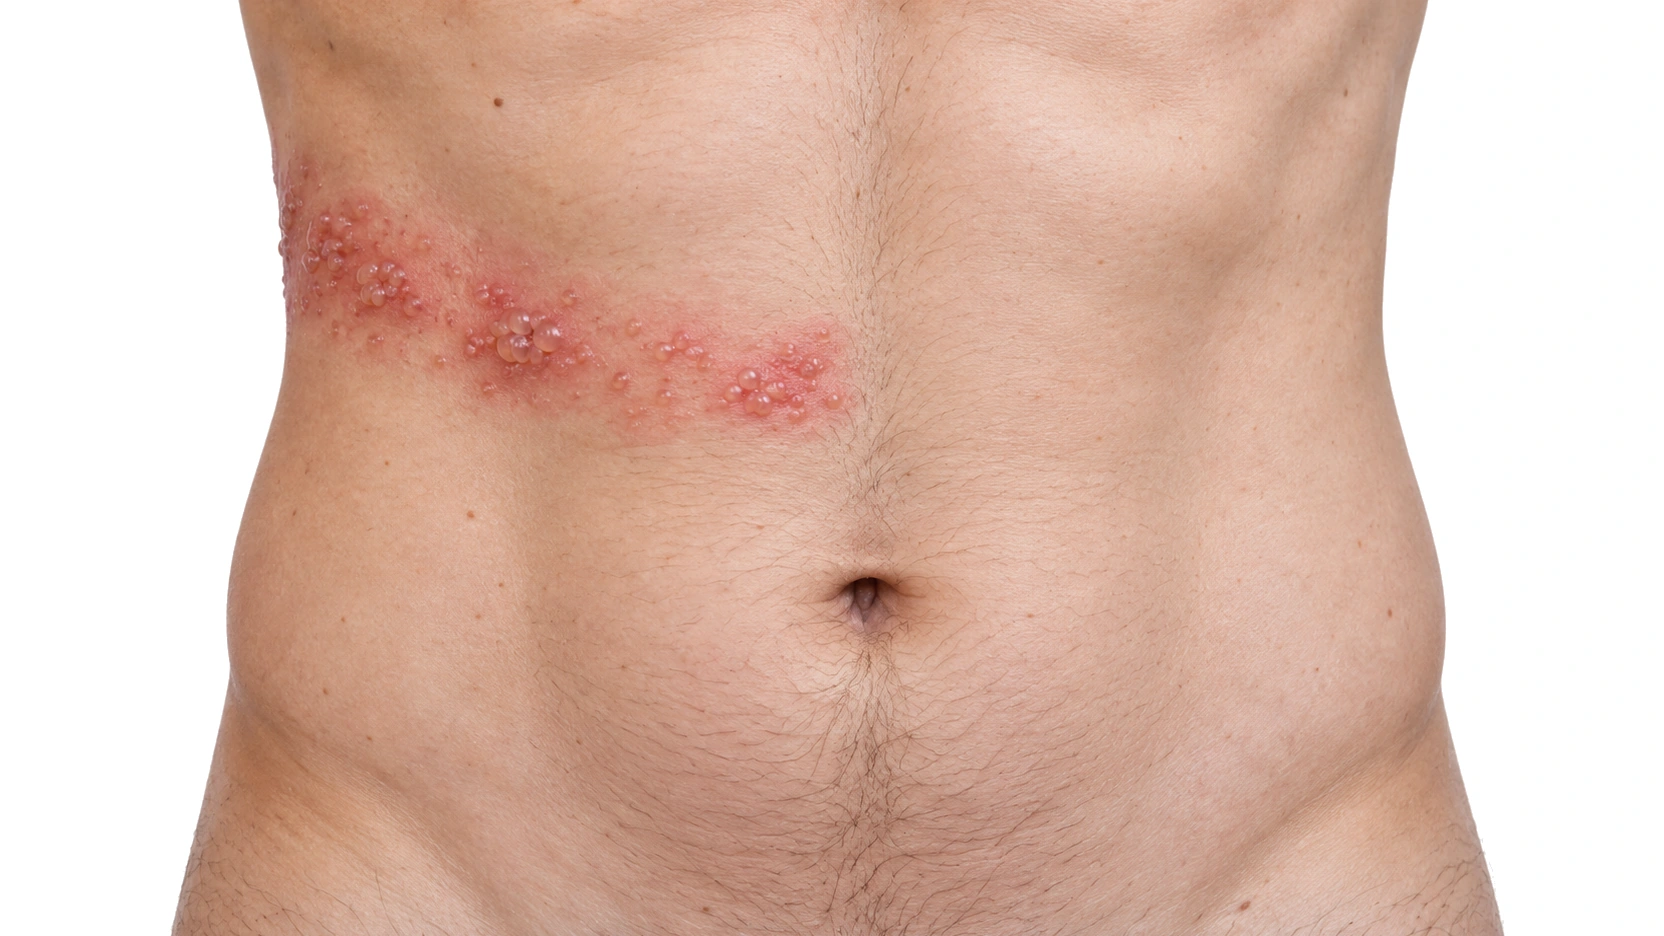
Grouped shingles blisters in a single narrow band on one side of the abdomen, stopping before the midline.The back of the neck and upper back on fair skin, covered in small red bumps of even size, each one at a hair opening, several with a pinpoint of yellow-white pus.

Key differences

The same eight facts on every condition comparison.

Usual age
50 and over
Any age
Where
A band on one side of the body
Hair-bearing skin
Main sign
Painful blisters in a stripe
Small pus spots, each at a hair
Itch or pain
Burning pain
Itchy or tender
Contagious
Chickenpox to those never exposed
Usually not
Long term
Heals in 2 to 4 weeks
Settles once the cause stops
Scars
Sometimes
Rarely; dark marks possible
Who gets it
Anyone who had chickenpox
Shaving, friction, hot tubs

What is it?

Shingles
Folliculitis
What is it?

It is a reactivated virus.
The chickenpox virus can lie dormant in nerves and later reactivate.

It follows a nerve.
Inflammation follows a nerve band and causes a skin eruption.

Risk rises with weaker immunity.
Age and immune-lowering treatment increase risk, but younger people can get it.

Care has several parts.
Antivirals, pain control and checking for complications are each addressed.

It is inflammation of hair follicles.
It can be superficial or deeper.

It ranges in severity.
A small pustule can sit around a hair, while deeper infection can form a boil.

Not every case is infection.
Irritation after hair removal or reactions to products can look similar.

Scalp scarring needs attention.
Some follicle disorders can permanently damage hair.

Overview
Inflammation around hair follicles can produce itchy or sore bumps and pustules. Bacteria, yeast, irritation and occlusion are among the causes. This broad category includes Malassezia folliculitis; the cause determines treatment. Inflammation around hair follicles can produce itchy or sore bumps and pustules. Bacteria, yeast, irritation and occlusion are among the causes. This broad category includes Malassezia folliculitis; the cause determines treatment.

What it looks like

Shingles

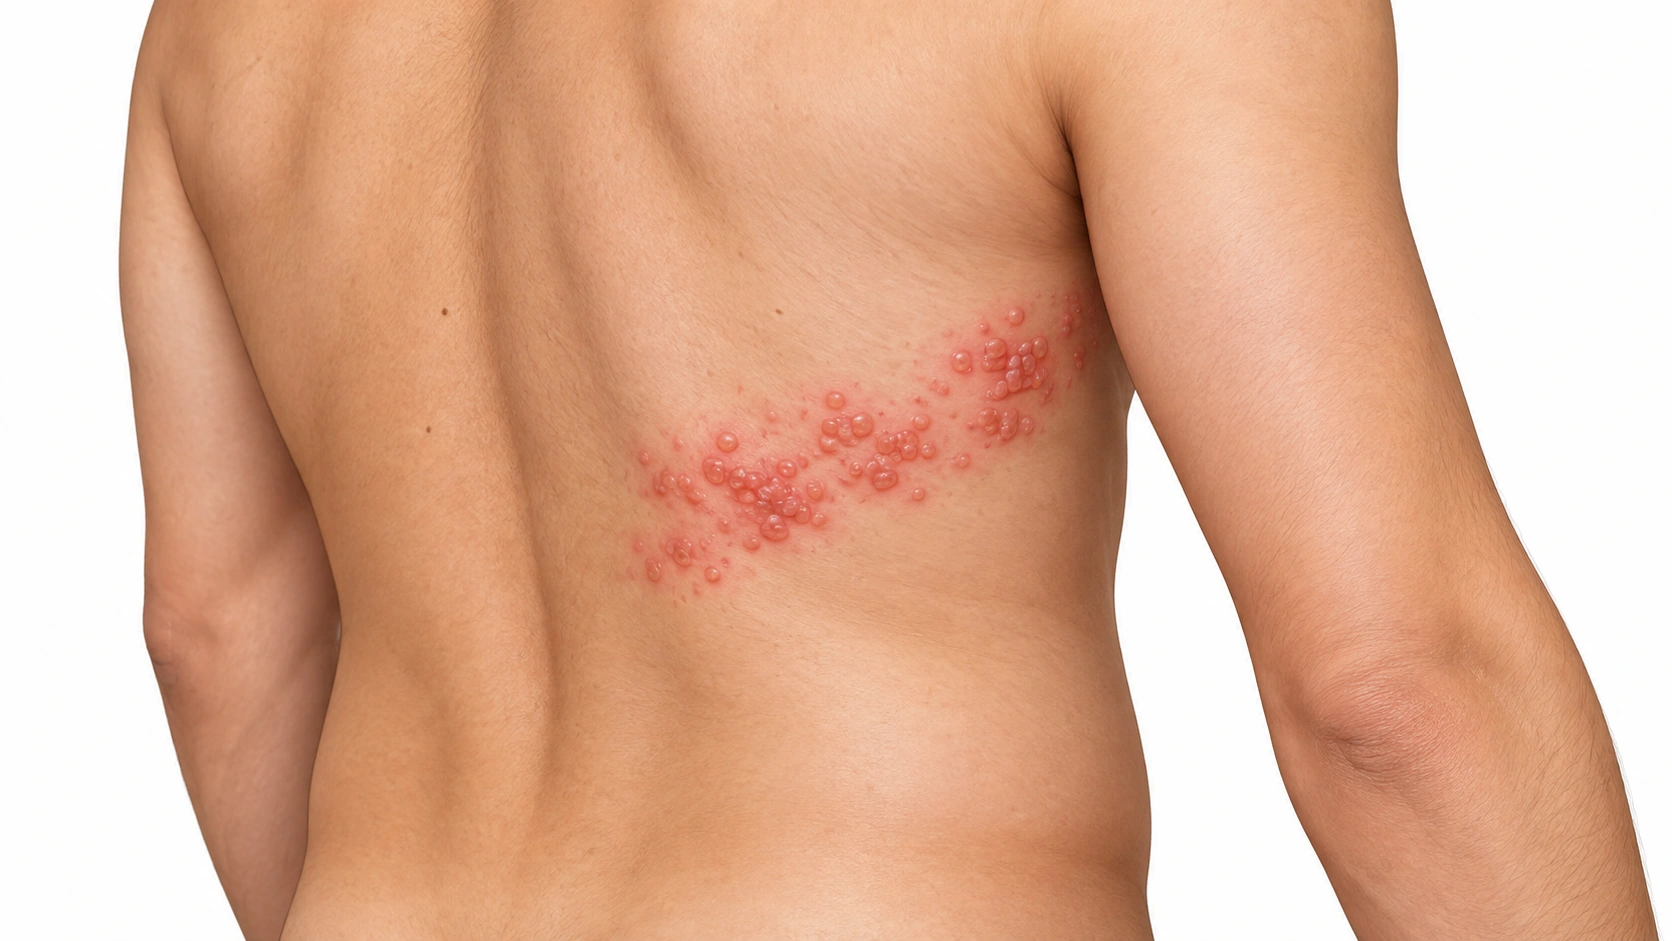
Representative image of shingles torso. Reused for related Supporting concepts; it is not an exact depiction of every subtype, location or stage, or a diagnostic reference.

Truncal shingles A band around one side of the chest or back.

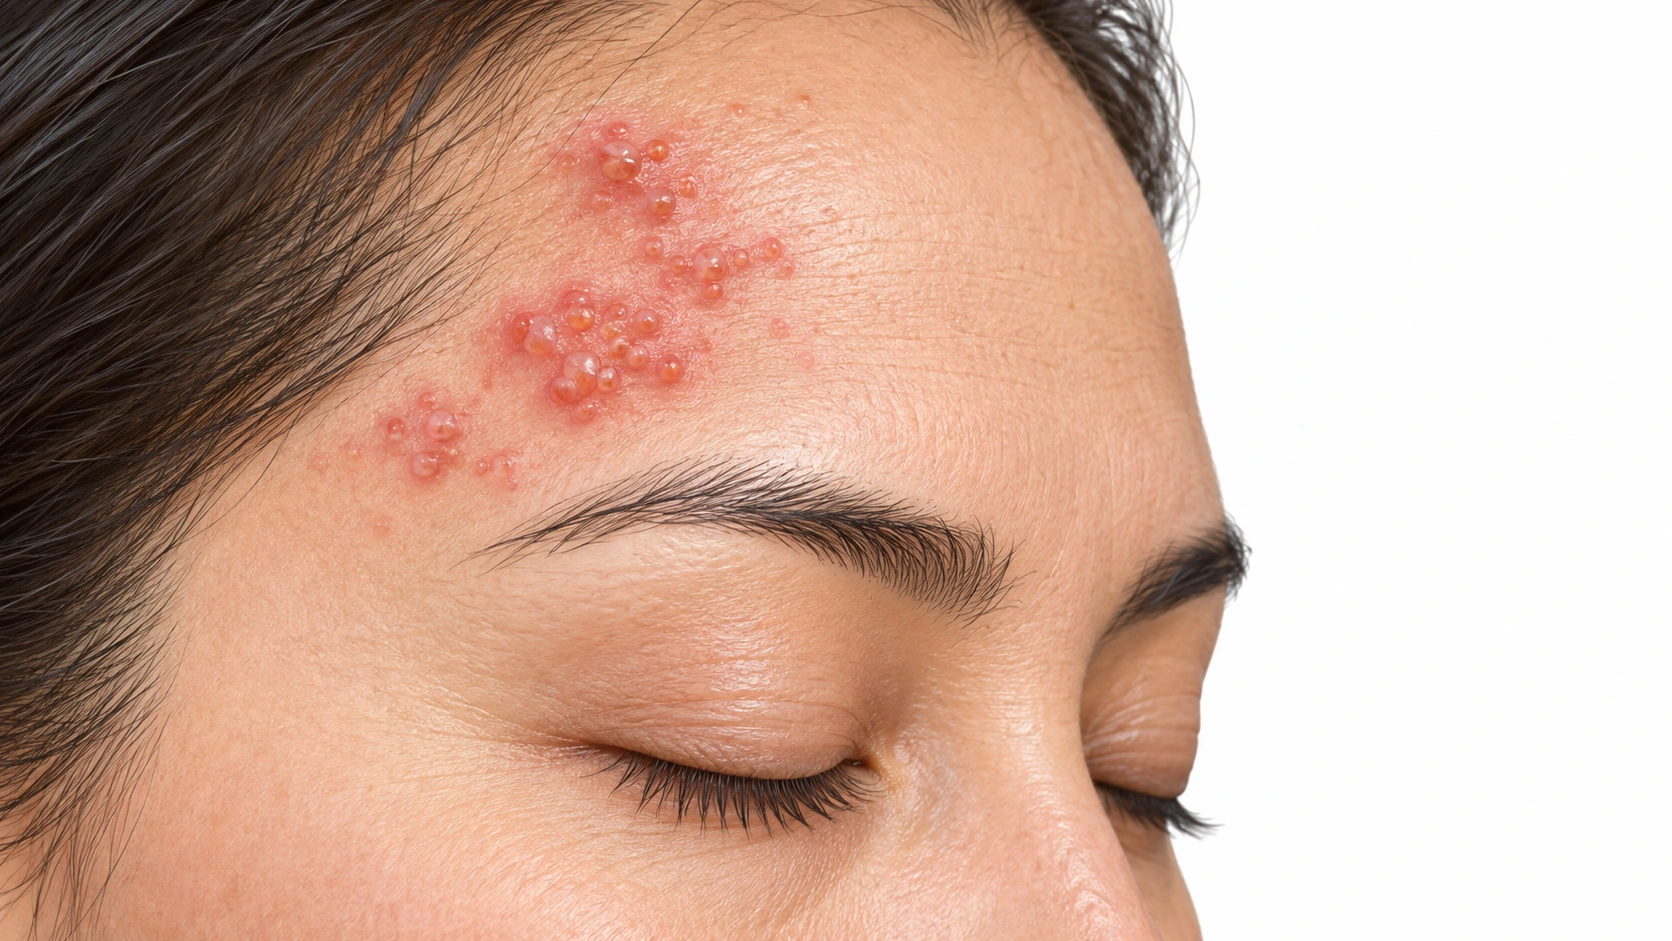
Representative image of shingles forehead. It is not a diagnostic reference or an exact depiction of every subtype, stage or location.

Facial and ocular shingles Forehead, scalp or around the eye.

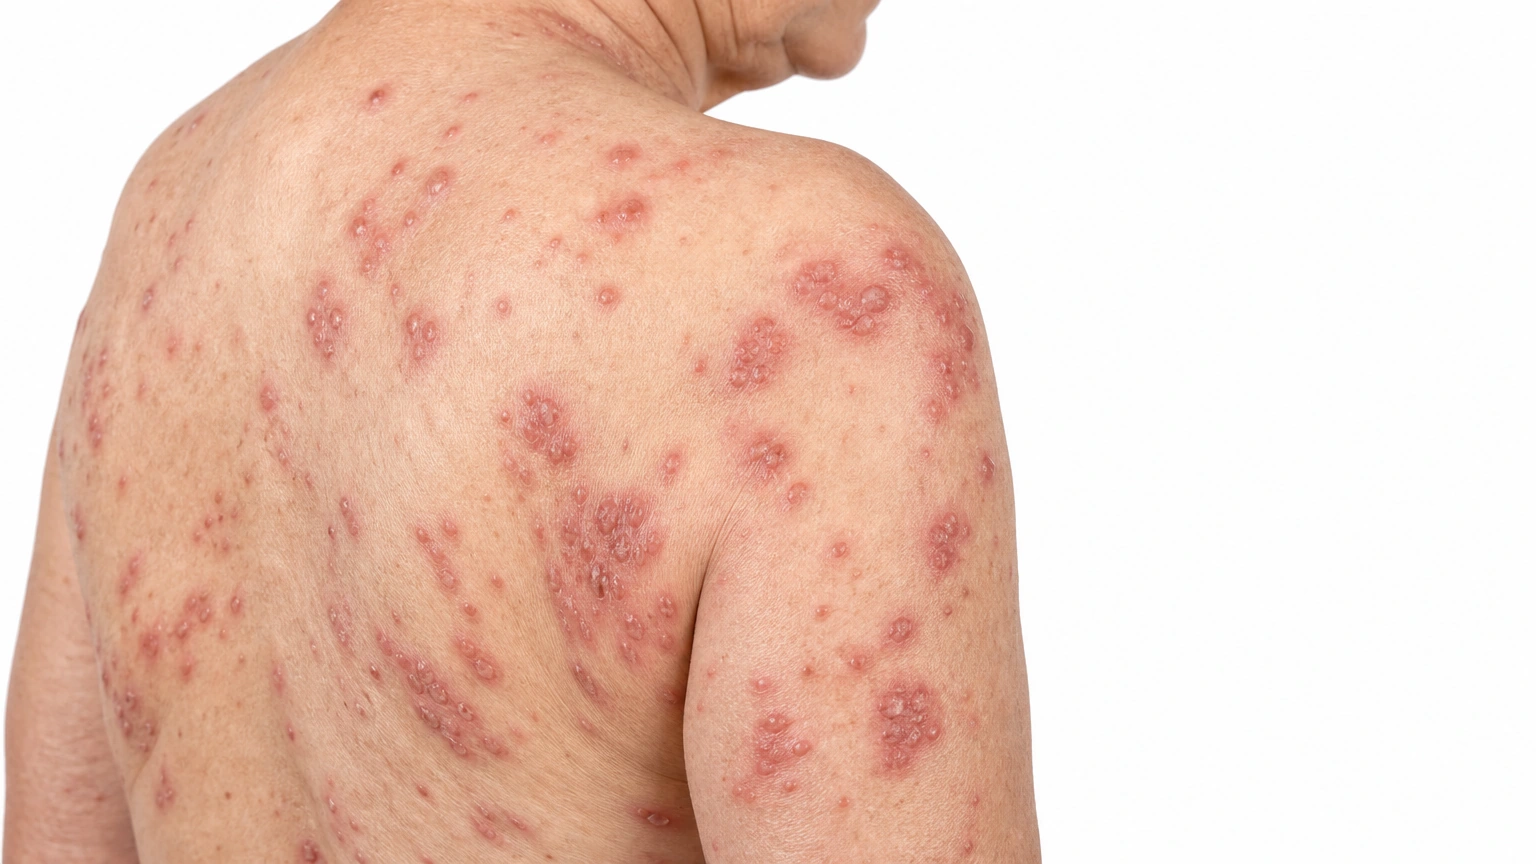
Widespread clusters of red vesicles across the back and shoulder, representing disseminated shingles.

Disseminated shingles Widespread; in weakened immunity.

Folliculitis

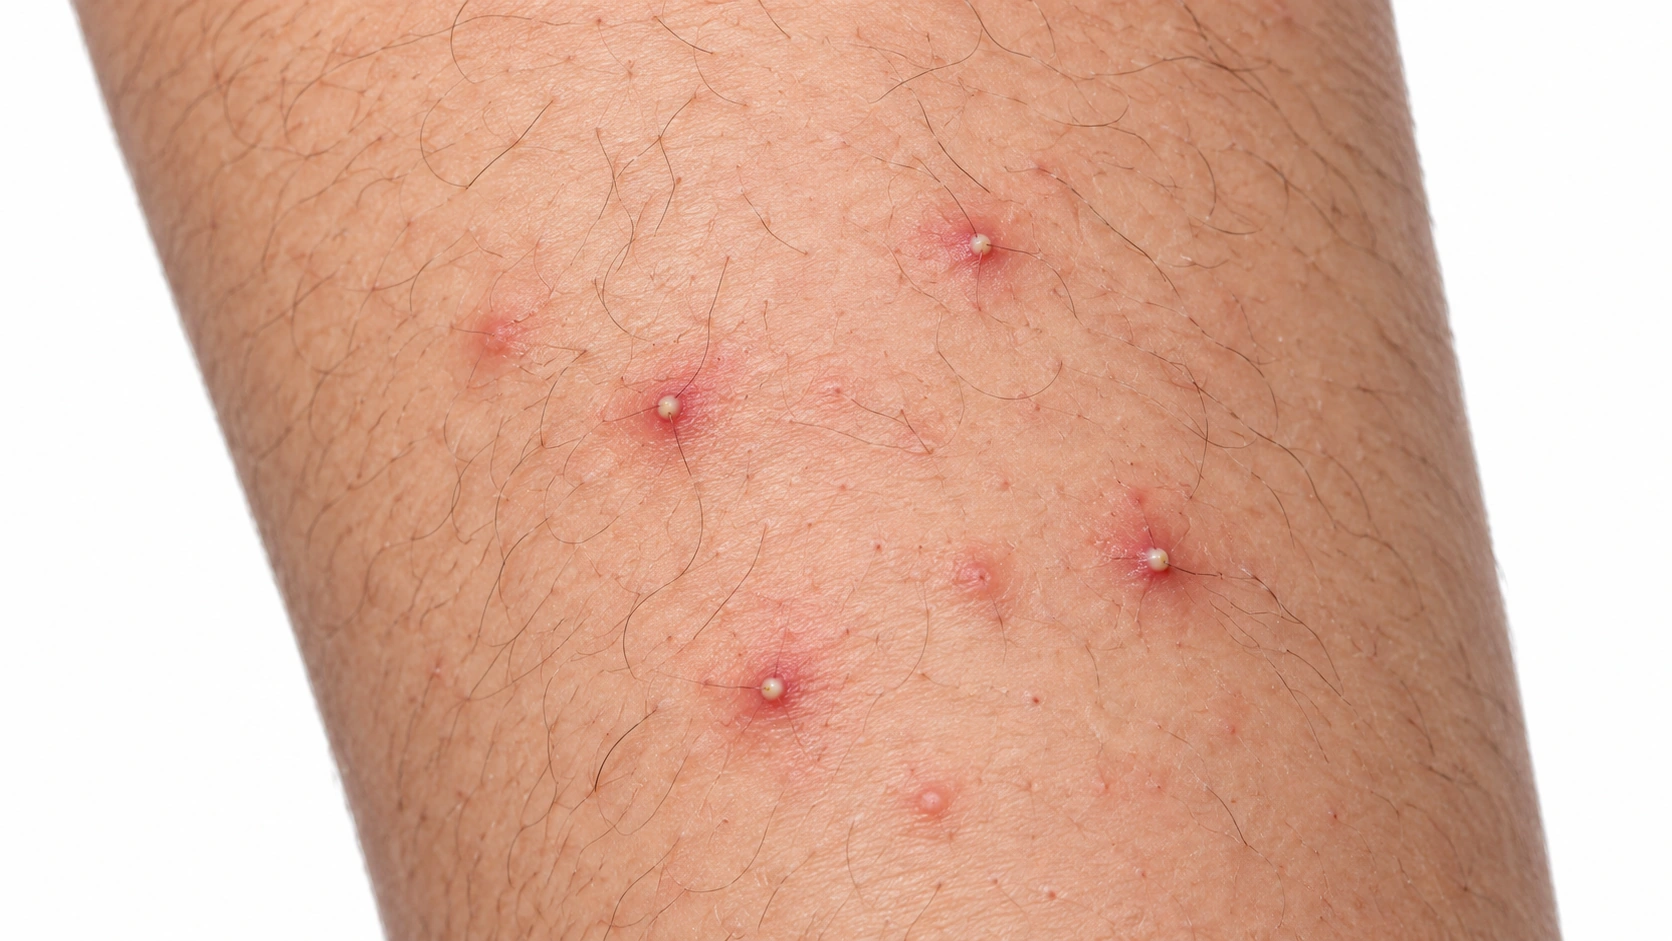
mild folliculitis on an adult thigh, close-up small field of skin with fine leg hair and a few discrete small red papules and tiny white pustules centered exactly on hair follicles. No large abscesses, no boils.

Bacterial folliculitis Staph infection, the most common.

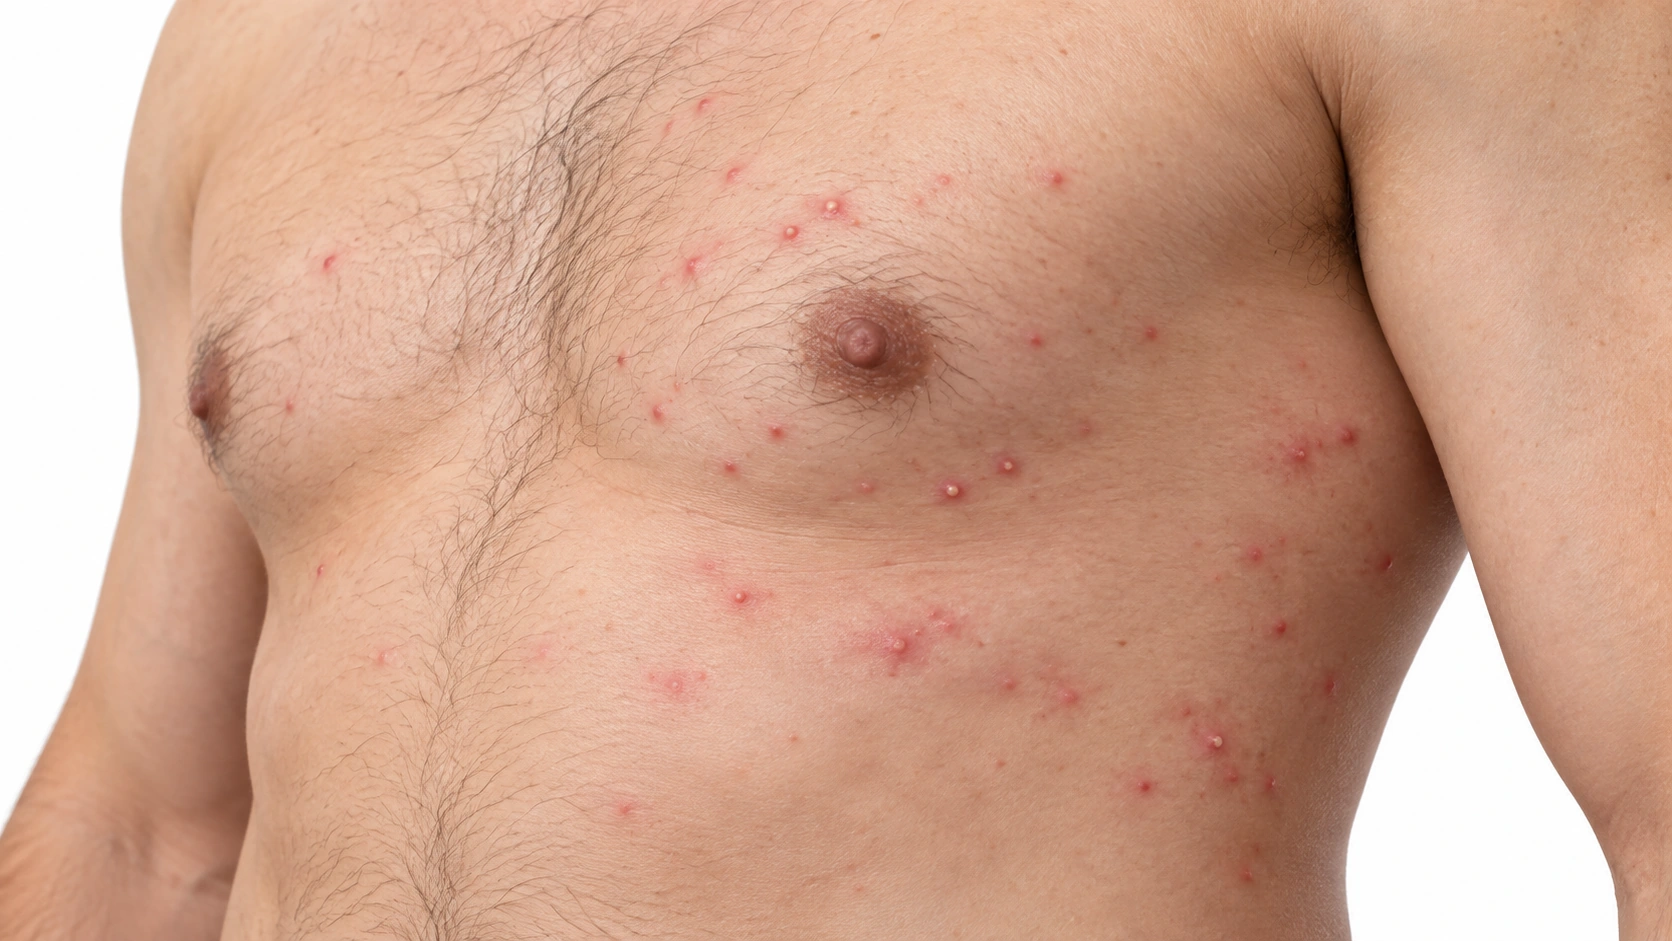
hot-tub folliculitis on an adult upper torso, a small field of discrete red follicle-centered papules and a few tiny pustules, scattered across chest and flank, mild realistic findings. No swimwear, no hot tub scene, no exaggerated infection.

Hot-tub folliculitis From bacteria in poorly treated water.

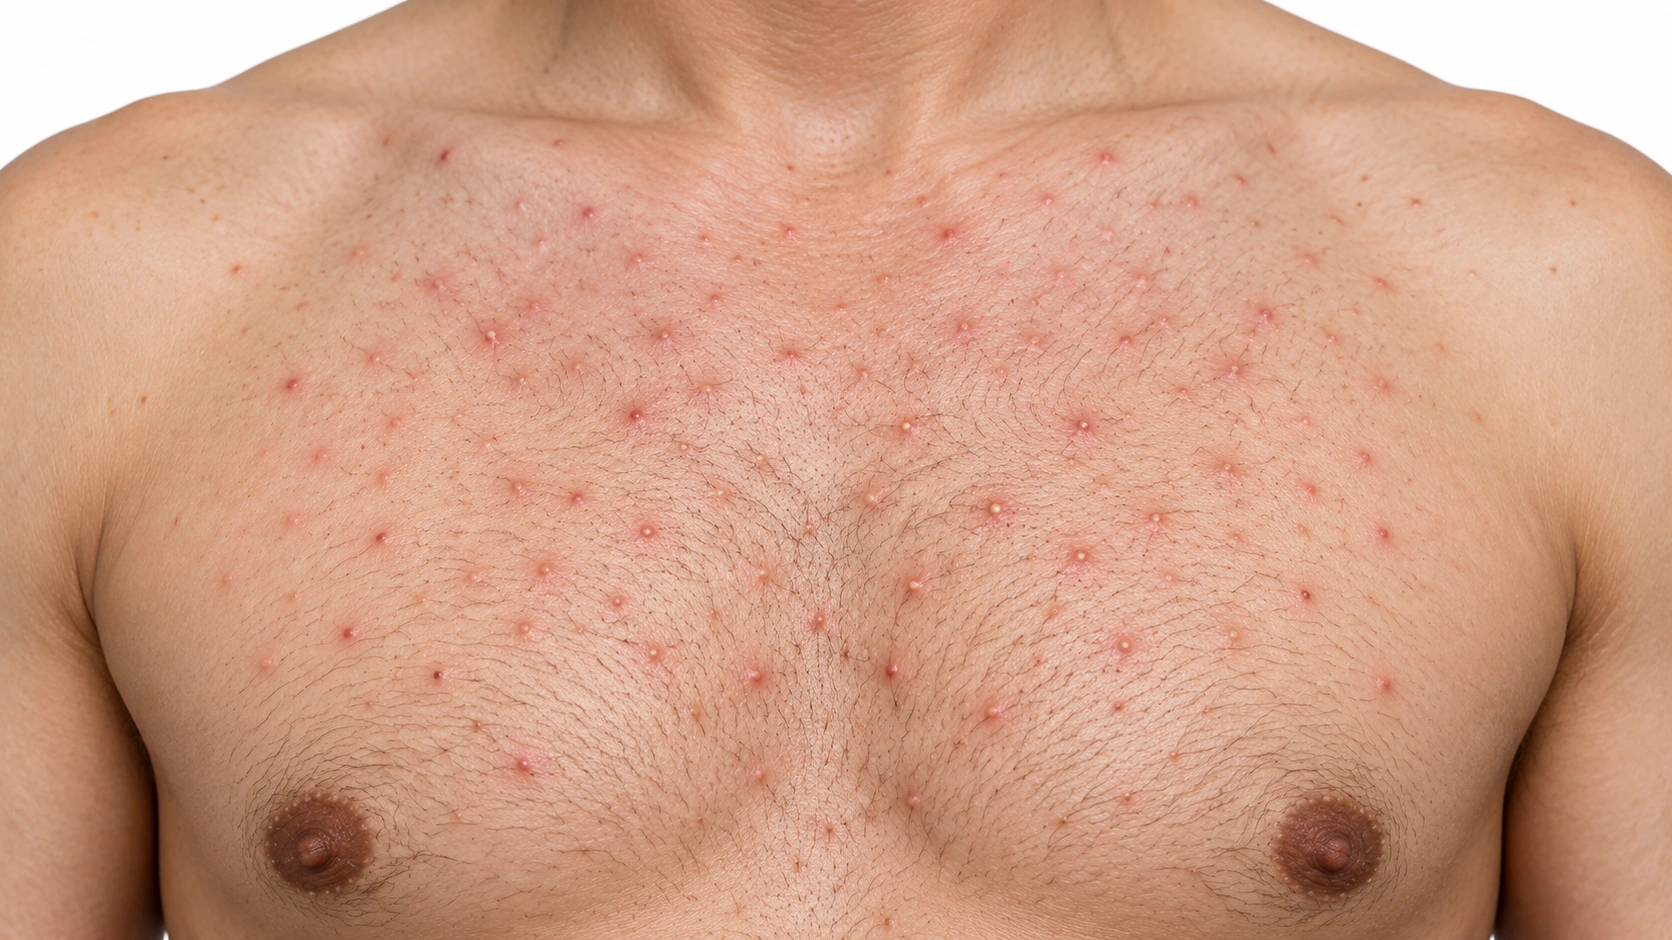
Malassezia (yeast) folliculitis on an adult chest, showing numerous small monomorphic follicle-centered red papules and a few tiny pustules, all similar size. No comedones, no nodules, no confluent rash.

Yeast folliculitis Uniform itchy bumps on chest and back.

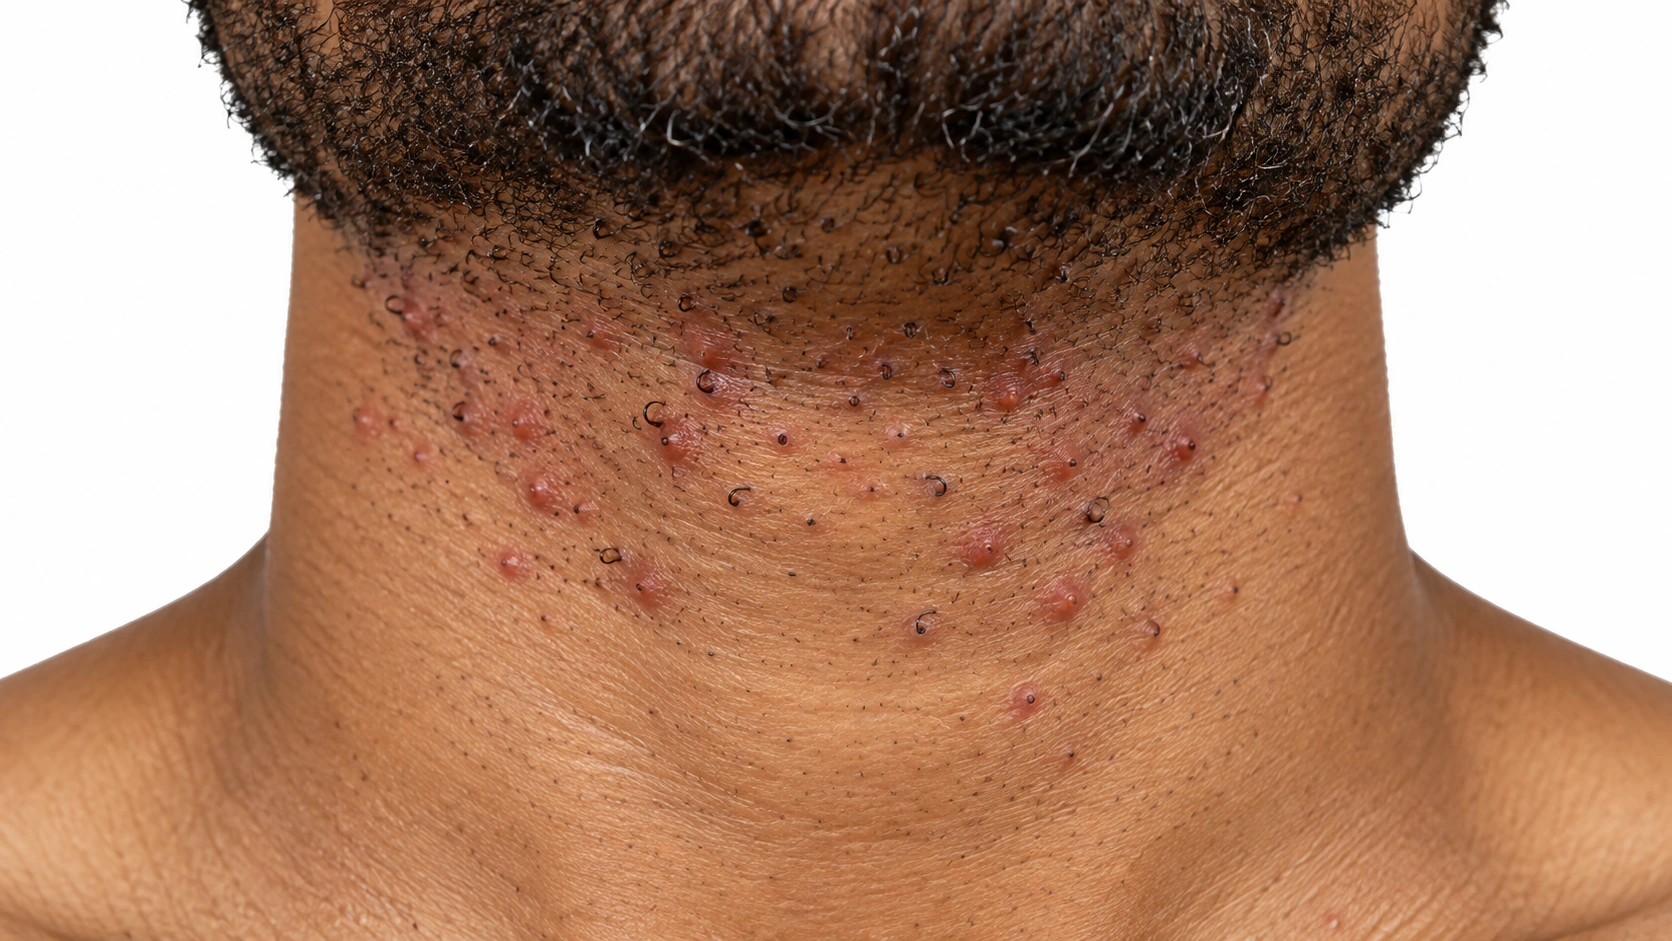
pseudofolliculitis barbae, razor bumps on the anterior neck below an adult beard, showing scattered small inflamed follicular bumps with short tightly curled dark stubble and a few visible curved ingrown hairs; medium-brown skin. No pus-filled abscesses.

Razor bumps (pseudofolliculitis) From hairs curling into skin.

Skin tones
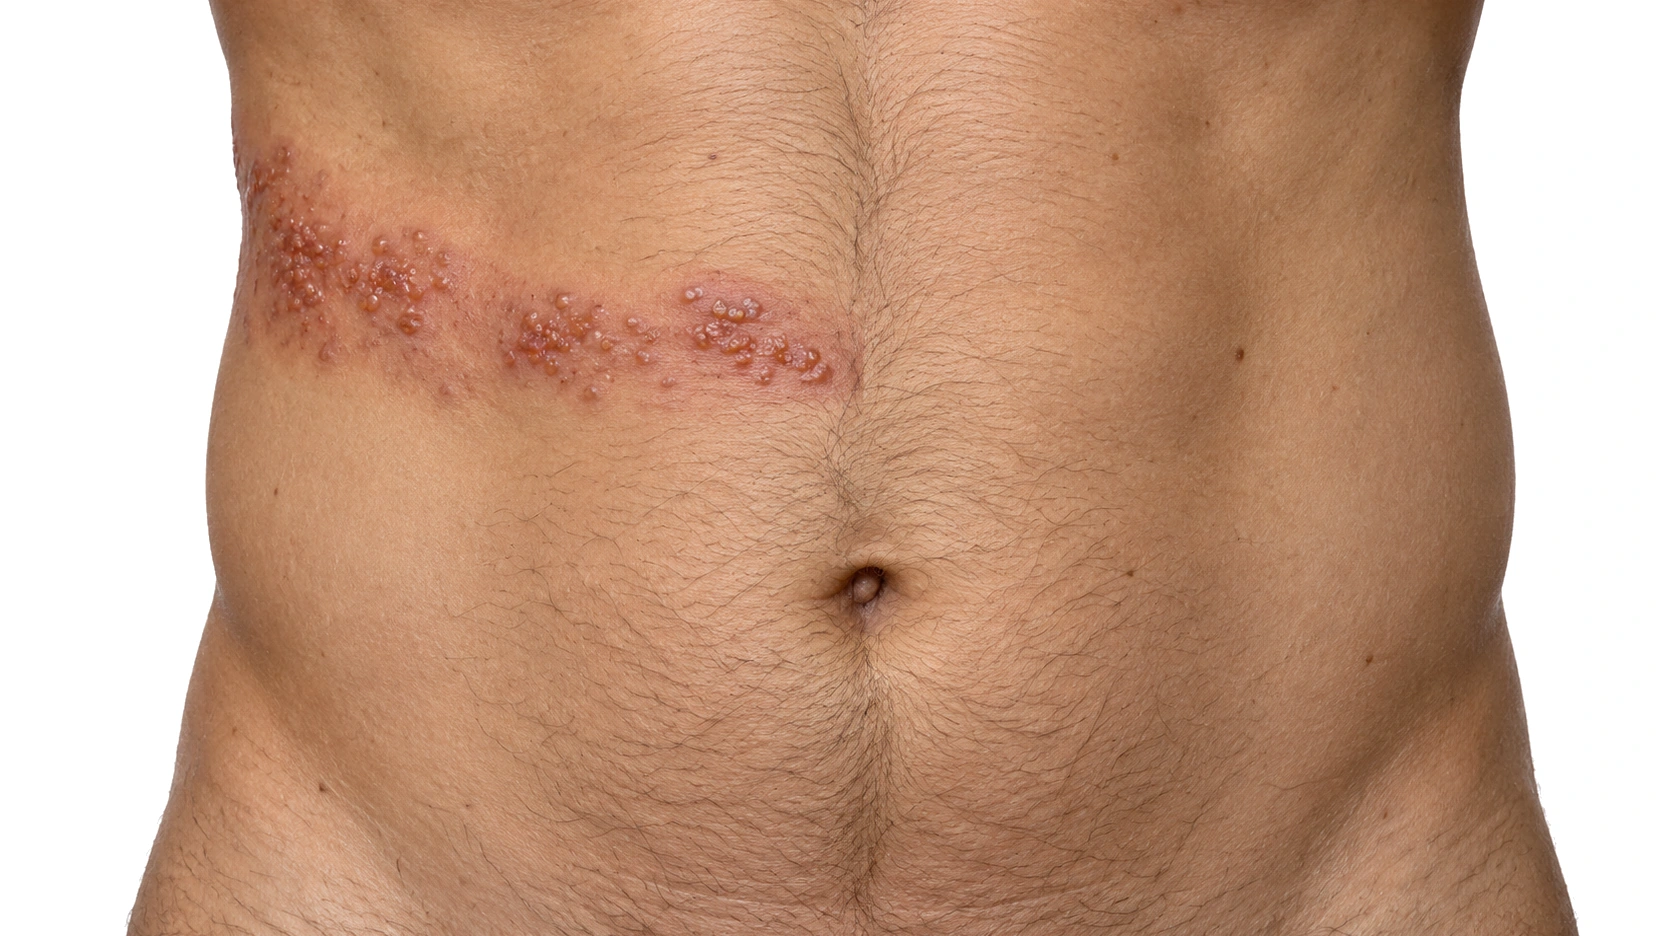
Grouped shingles blisters in a single narrow band on one side of the abdomen, stopping before the midline.
The back of the neck and upper back on fair skin, covered in small red bumps of even size, each one at a hair opening, several with a pinpoint of yellow-white pus.
The back of the neck and upper back on medium olive skin, with small dull pink-brown bumps of even size, each one at a hair opening, a few with a pale point of pus.
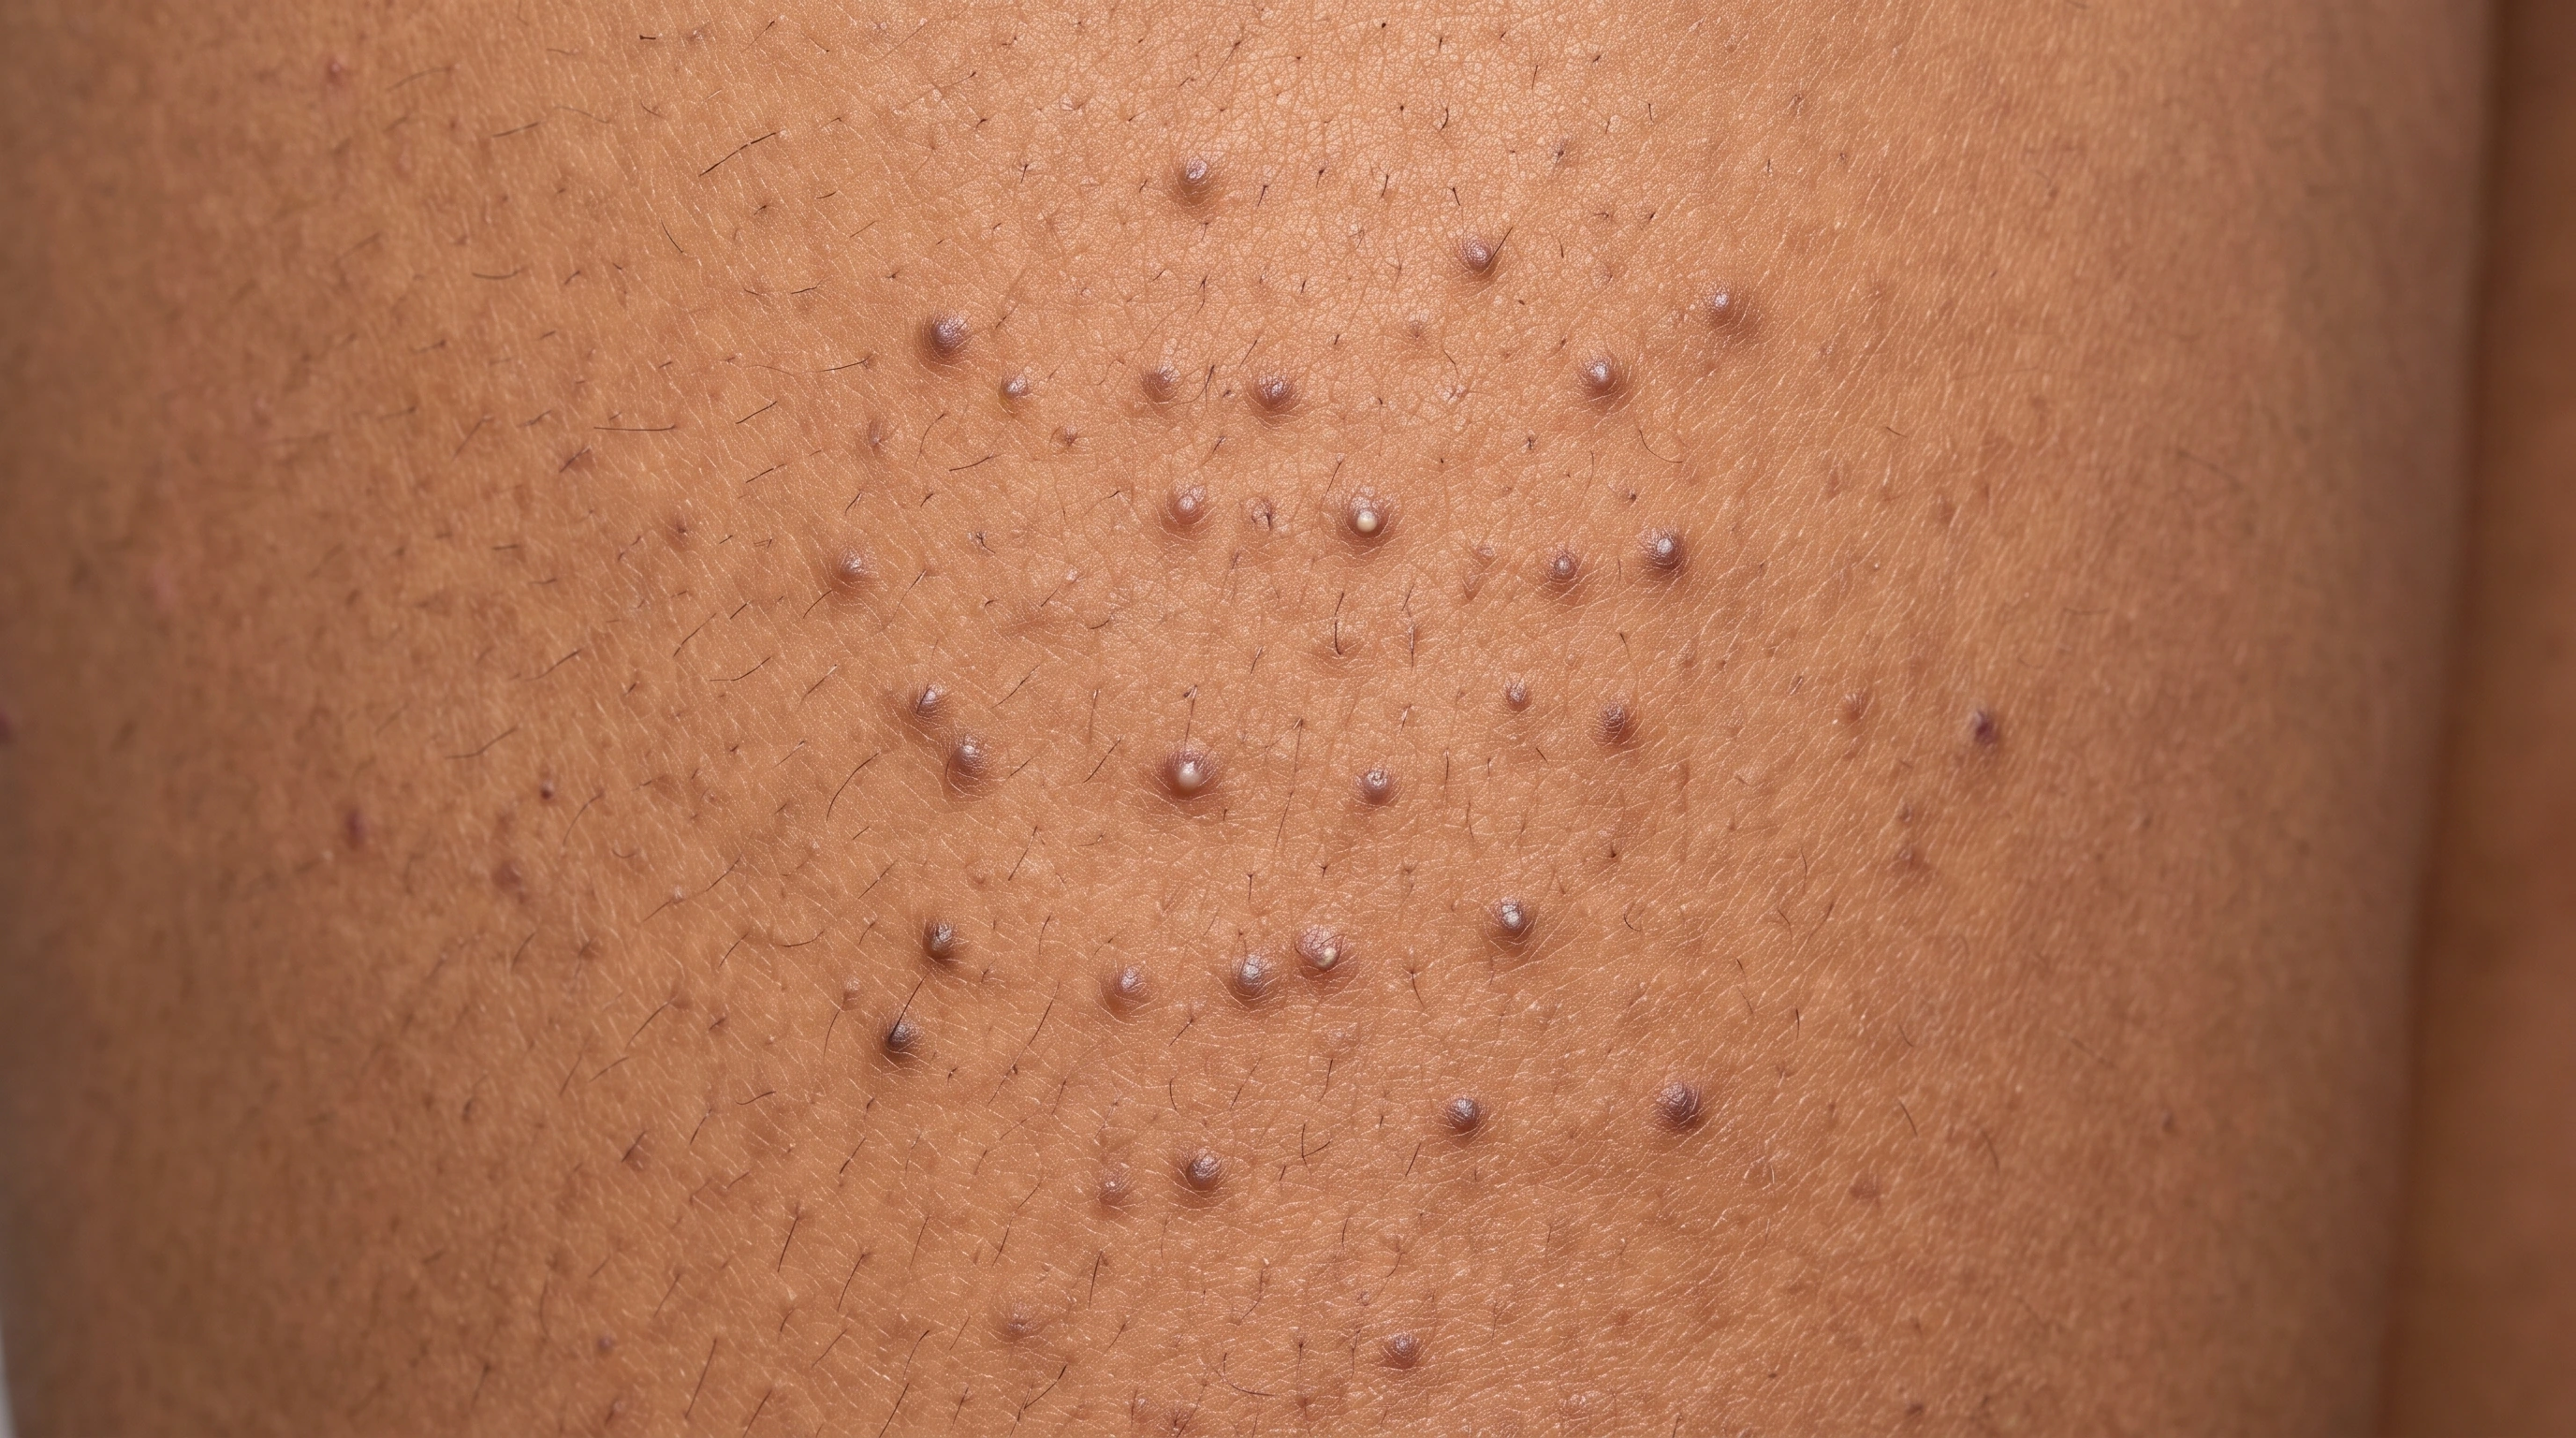
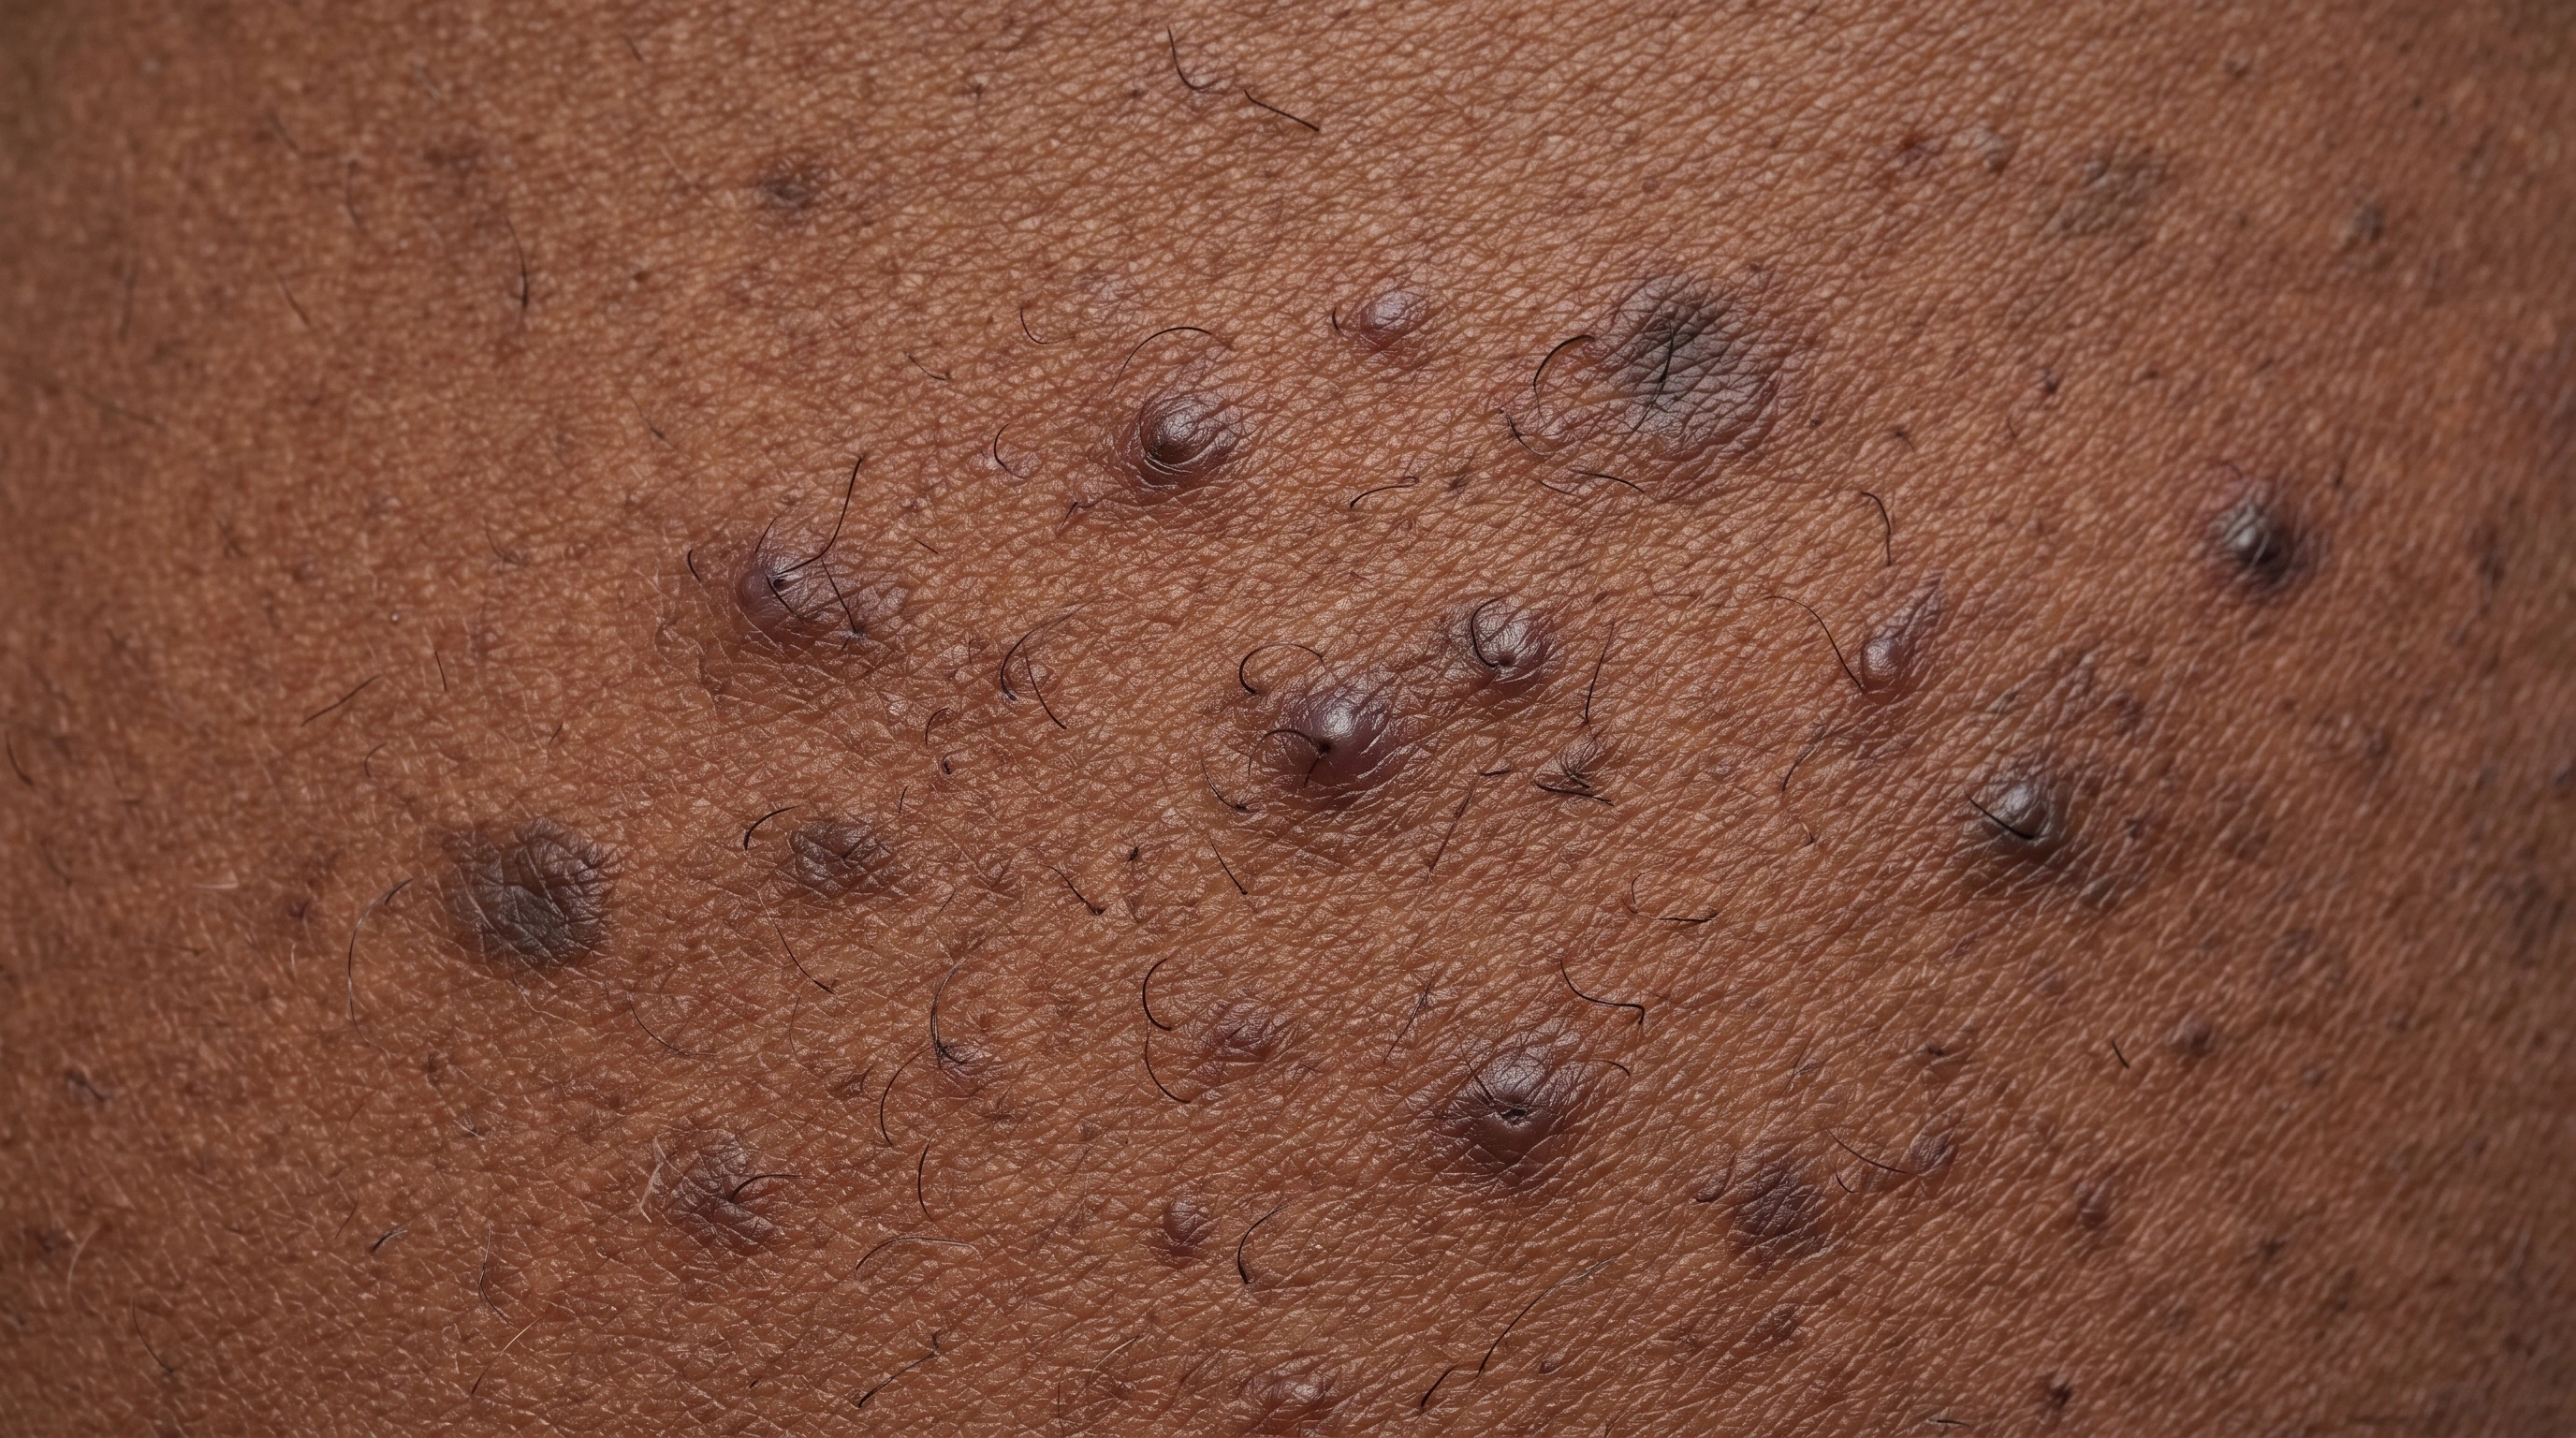
The back of the neck and upper back on brown skin, with small bumps of even size that read brown and violet rather than red, each one sitting at a hair opening.
The back of the neck and upper back on deep brown skin, with bumps of even size at the hair openings that read dark brown, and a few flat darker marks beside them where earlier bumps have healed.
Diagram
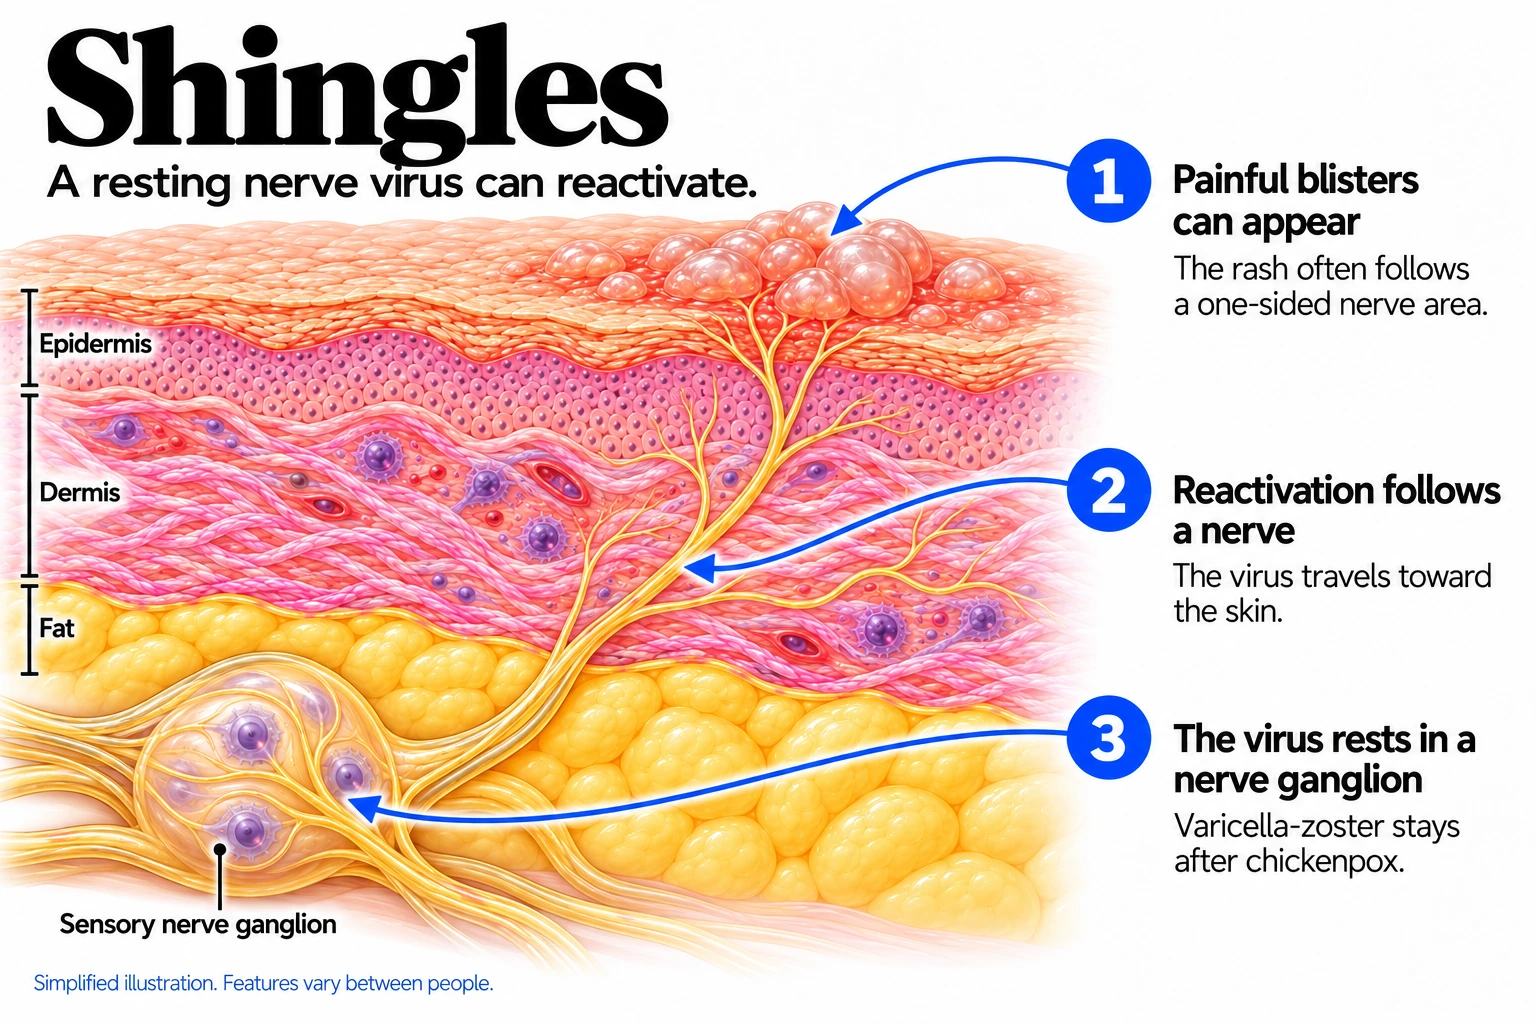
Shingles mechanism diagram. Painful blisters can appear: The rash often follows a one-sided nerve area. Reactivation follows a nerve: The virus travels toward the skin. The virus rests in a nerve ganglion: Varicella-zoster stays after chickenpox.
Folliculitis mechanism diagram. A follicle becomes irritated: Microbes or physical irritation can start inflammation. Immune cells gather: The response surrounds the affected follicle. A small pustule may form: A tender bump appears around the opening.
In the skin

Varicella-zoster virus remains dormant in sensory nerves after chickenpox. When it reactivates, it travels toward the skin and can cause pain and grouped blisters in a one-sided nerve distribution.

Infection, irritation or blockage can cause inflammation around a hair follicle. The response may produce a small tender bump or pustule around the follicular opening.

Where it shows up

A one-sided nerve distribution
Hair-bearing skin

When it usually starts

010203040506070+

Shingles. Risk rises with age, particularly after age 50, but younger people can be affected.

Folliculitis. Folliculitis Any age There is no single typical starting-age range. Bumps can follow shaving, friction, sweating or hot-tub exposure. Recurrent or unexplained episodes deserve an assessment of the cause.

Causes and triggers

Causes

Shingles is caused by the chickenpox virus waking up years after it first infected you. The virus stays dormant in nerves and can reactivate later.

Folliculitis is inflammation of hair follicles, usually from bacteria, yeast or irritation.

Folliculitis describes a pattern of inflammation rather than one organism. Damaged or occluded follicles may become infected; shaving-related irritation can produce similar bumps without infection.

Family tendency

Most everyday folliculitis is not considered an inherited disorder. Skin conditions and individual susceptibility can influence risk.

Risk factors
Age over 50, Weakened immunity, Cancer treatment, Never vaccinated
Shaving, Diabetes, Obesity, Weakened immunity, Shaving or waxing, Sweat and occlusion, Reduced immunity
Trigger
● Shingles
● Folliculitis
Weakened immunity
Well established
Not listed
Illness
Strong link
Not listed
Immune-suppressing medicines
Well established
Not listed
Stress
Possible
Not a typical trigger
Shaving and waxing
Not listed
Well established
Hot tubs
Not listed
Well established
Tight clothing and sweat
Not listed
Strong link
Antibiotics or steroid creams
Not listed
Possible
Hormonal changes
Not listed
Not a typical trigger
Pore-clogging products
Not listed
Can contribute
Sun exposure
Not listed
Not a typical trigger
Heat and sweating
Not listed
Common trigger
Alcohol
Not listed
Not a typical trigger
Spicy foods
Not listed
Not a typical trigger
Harsh skin care
Not listed
Can contribute
Friction and tight clothing
Not listed
Common trigger
Shaving or waxing
Not listed
Common trigger
Poorly maintained hot tubs
Not listed
Can contribute
Prolonged antibiotic use
Not listed
Can contribute

Daily Care

Shingles
Folliculitis
Daily care

Habits that help

  • Keeping the rash covered
    A loose, non-adhesive dressing until it crusts.
  • Loose cotton clothing
    Less pressure over the band, less pain.
  • Plain petrolatum on broken areas
    Stops cracking and lowers infection risk.
  • Rest, and lowering expectations
    Pushing through shingles is not rewarded.
  • The shingles vaccine
    Two doses, more than 90 percent effective after 50.
  • Getting vaccinated after an episode
    One episode does not protect you.
  • Seek early treatment for suspected shingles, ideally within 72 hours
    Early treatment is most effective. Eye involvement, immune suppression or new lesions can warrant treatment even after 72 hours; do not assume it is too late to seek care.
  • Discuss how age affects monitoring and recovery
    Longer episodes and more lasting nerve pain.
  • Discuss immune suppression and the need for earlier assessment
    Raises reactivation, spread and complications.

Avoid

  • Avoid: Breaking or scratching the blisters
    Spreads virus and turns marks into scars.
  • Avoid: Ignoring a rash near the eye
    Forehead, eyelid or nose blisters, same day.
  • Avoid: Ear blisters with facial weakness
    Droop, hearing change or dizziness is urgent.
  • Avoid: Not covering the rash
    Blister fluid gives chickenpox to anyone not immune.
  • Avoid: Tight clothing and adhesive dressings
    Pressure worsens pain and tears blisters.
  • Avoid: Poor sleep during the episode
    Pain and sleep loss feed each other.
  • Avoid: Waiting to see if it settles
    Antivirals work best within 72 hours.
  • Avoid: Leaving severe pain untreated
    Linked with worse nerve pain later.
  • Avoid: Topical antiviral cream
    Antiviral creams sold for cold sores do not work for shingles. The virus is in the nerve, not just on the surface, so treatment has to be swallowed or given by drip. Reaching for a cream instead is one of the ways the 72-hour window gets missed.

Habits that help

  • Change how you shave
    Fresh single blade, with the grain, with gel, days off when sore.
  • Shower and change after sweating
    The most effective habit for trunk, buttocks and thighs.
  • Warm compresses on a tender lump
    Help a boil come to a head and drain.
  • A gentle cleanser and moisturizer
    An intact barrier means fewer inflamed follicles.
  • Loose clothing over the area
    Remove the occlusion and mild folliculitis often settles.
  • An antifungal shampoo as a body wash
    The standard approach for Malassezia yeast.
  • Prescription treatment when needed
    The wrong class is a common reason for failure.

Avoid

  • Avoid: Close shaving with a dull razor
    Cutting below the surface damages the follicle.
  • Avoid: Shaving against the grain
    Stretching the skin does the same.
  • Avoid: Dry shaving
    More drag, more nicks, more inflamed follicles.
  • Avoid: Staying in damp workout clothes
    A reliable way to bring on a crop.
  • Avoid: Tight, non-breathable fabrics
    Trap heat and sweat over the follicles.
  • Avoid: Squeezing and picking
    Pushes infection deeper, turning a spot into a boil.
  • Avoid: Scrubbing and exfoliating
    Damages the follicle openings and the barrier.
  • Avoid: Heavy oils and pomades
    Especially under clothing or a hat.
  • Avoid: Poorly maintained hot tubs and pools
    Weak disinfection lets Pseudomonas survive.
  • Avoid: Sharing razors and towels
    Moves Staphylococcus aureus around.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Shingles
● Folliculitis
Filter by type
All types
Folliculitis type

Select one or more.

Over-the-counter
Existing Dermapedia illustration of acetaminophen and ibuprofen.

Acetaminophen and ibuprofen

Limited evidence

The first step for shingles pain, and enough on their own for a milder episode. They work better taken regularly than only when the pain peaks. Shingles pain is nerve pain, so if these are not holding it, that is a reason to ring your doctor rather than to take more.

Existing Dermapedia illustration of calamine lotion.

Calamine lotion

Limited evidence

Dabbed on while the blisters are present, it cools the skin and takes the edge off the itching. A cool compress does much the same thing. Neither shortens the episode, and neither should be rubbed in, because breaking the blisters spreads virus and can leave scars.

Five colloidal oatmeal eczema products lined up on white: tubes, a jar and a pump lotion

Colloidal Oatmeal

Limited evidence

An oatmeal soak can settle itching while the rash is blistering, in cool rather than hot water. It is comfort only. It does not change how long shingles lasts or whether nerve pain follows.

Four ointments on white: CeraVe Healing Ointment, a Vaseline jar, a petroleum jelly tube and Aquaphor

Petrolatum

Listed

A thin layer of plain petroleum jelly on broken or crusting areas stops them drying and cracking, which lowers the risk of bacteria getting in. It has no effect on the virus itself. Use it under a loose, non-stick dressing rather than an adhesive one, which tears blisters when it comes off.

Three acne wash tubes on white: Differin Deep Cleanser, CeraVe Acne Foaming Cream Cleanser and PanOxyl.

Benzoyl Peroxide wash

Limited evidence

A 4 to 10 percent wash lathered on in the shower and left for a minute before rinsing, for the bacterial kind on the thighs, buttocks, chest and back. It lowers the bacteria on the skin without an antibiotic, which is why it also works as a maintenance measure for people who keep getting crops. It bleaches towels, sheets and colored clothing, so use white ones.

Existing Dermapedia illustration of chlorhexidine wash.

Chlorhexidine wash

Limited evidence

An antiseptic wash used two or three times a week over the affected area, and a good option for someone whose bumps keep coming back in the same place. It lowers the bacterial load on the skin rather than treating an established infection. Keep it away from the eyes and ears, and stop if it stings or dries the skin, since damaged skin is the problem you started with.

Existing Dermapedia image for Ketoconazole shampoo as a wash.

Ketoconazole shampoo as a wash

Limited evidence

The standard first move for the yeast kind: itchy, uniform bumps on the chest, back and shoulders, often worse after a course of antibiotics. Use the shampoo as a body wash a few times a week and leave it on for several minutes before rinsing. It does nothing for bacterial folliculitis or razor bumps, and yeast folliculitis tends to come back, so many people keep using it once a week.

A plain white ointment tube lying on its side, labeled Hydrocortisone with a blue swoosh

Hydrocortisone

Limited evidence

It is the obvious thing to reach for because the bumps itch, and it is usually the wrong one. Steroid cream quietens the itch for a few days while the infection in the follicles carries on underneath, and the rash that comes back is often more widespread. It also changes how things look, which makes the diagnosis harder afterward. Cool compresses and a medicated wash are the safer starting point.

Paula's Choice 2% BHA exfoliant, La Roche-Posay Effaclar cleanser and a CeraVe psoriasis cream pump

Salicylic Acid

Limited evidence

A leave-on 2 percent lotion or pad on the beard, neck or bikini line, where the problem is hairs curling back into the skin rather than an infection. It keeps the follicle opening clear so fewer hairs get trapped, and it is used between shaves rather than on raw skin. It will not touch a bacterial or yeast folliculitis, and on already inflamed skin it stings and can make things worse.

Five dark glass tea tree essential oil bottles with glass droppers and one green box on white

Tea Tree Oil

Limited evidence

It does have some activity against bacteria and yeast in the laboratory, which is why it appears in so many folliculitis remedies. There are almost no proper trials of it in folliculitis, and undiluted tea tree oil is a common cause of allergic contact dermatitis, which produces an itchy rash on top of the one you were treating. A benzoyl peroxide or antifungal wash is the better use of the same shower.

Prescription topicals
An illustrative lidocaine patch pouch and rectangular skin patch.

Lidocaine 5% patch

Moderate evidence

A numbing patch worn over the area for pain that carries on after the rash has healed. It goes only on intact skin, never on blisters or open areas. It helps some people a great deal and others hardly at all, so it is worth a proper trial before deciding.

An illustrative capsaicin patch pouch and rectangular skin patch.

Capsaicin 8% patch

Moderate evidence

A high-strength patch applied in a clinic for lasting nerve pain, with one treatment lasting up to three months. It burns while it is on, so the skin is numbed first. It is used after simpler options, and only once the skin has fully healed.

Mupirocin — Header Image

Mupirocin

Limited evidence

An antibiotic ointment used only if the crusts turn hot, swollen or start oozing pus, which means bacteria have moved in on top. It does nothing to the shingles virus. If the infection is spreading, antibiotic tablets are needed instead.

Mupirocin — Header Image

Mupirocin

Moderate evidence

Clearing Staph from the nose. Some people carry Staphylococcus aureus in the nostrils or skin folds, which is one reason boils keep returning to the same person. A course of antibiotic ointment inside the nostrils, together with antiseptic washes and hot washing of towels and bedding, can reduce that. It is used for repeated boils rather than for a single episode, and it does not always hold, so household measures matter alongside it.

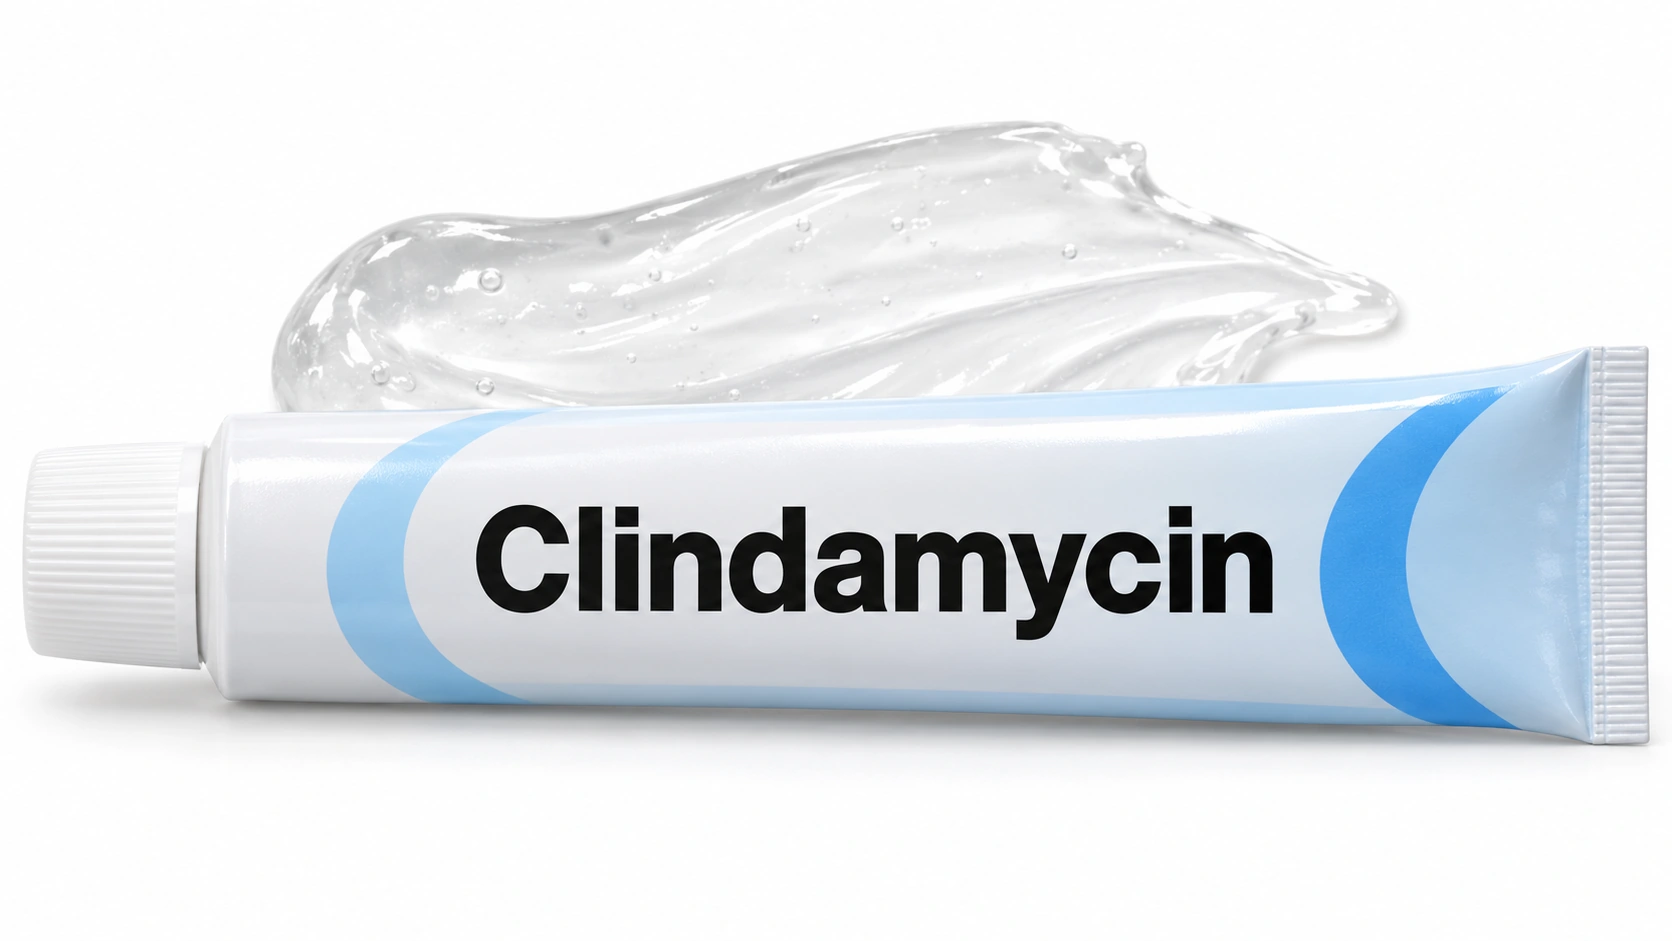
A white metal tube lying at an angle on a white background, white ribbed cap to the left, labeled Clindamycin in black lettering with a teal swoosh curving beneath the word.

Clindamycin

Limited evidence

A lotion or solution for bacterial folliculitis spread over a wider area than an ointment can cover, such as the beard or the back. It is usually paired with a benzoyl peroxide wash, which both improves it and reduces resistance. It is not the answer if the same patch keeps returning, because that is a shaving, friction or occlusion problem rather than an antibiotic one.

Prescription pills
Valacyclovir — Header Image

Valacyclovir

Strong evidence

The usual first choice for shingles: three doses a day for seven days. Started within 72 hours of the rash it shortens the episode and lowers the chance of lasting nerve pain. It does not clear the virus from the body, and it does much less once everything has crusted over.

Representative medication packaging labelled Famciclovir, lying sideways on a white background.

Famciclovir

Strong evidence

An equally effective alternative to valacyclovir, taken three times a day for seven days. It is used when valacyclovir does not suit. The same 72-hour clock applies, and it is usually the more expensive option.

Tablets — stock illustration

Acyclovir

Strong evidence

The oldest of the three antiviral tablets and the cheapest. It works just as well, but it has to be taken five times a day for seven days, which is harder to keep up. The dose is lowered if your kidneys are not working well.

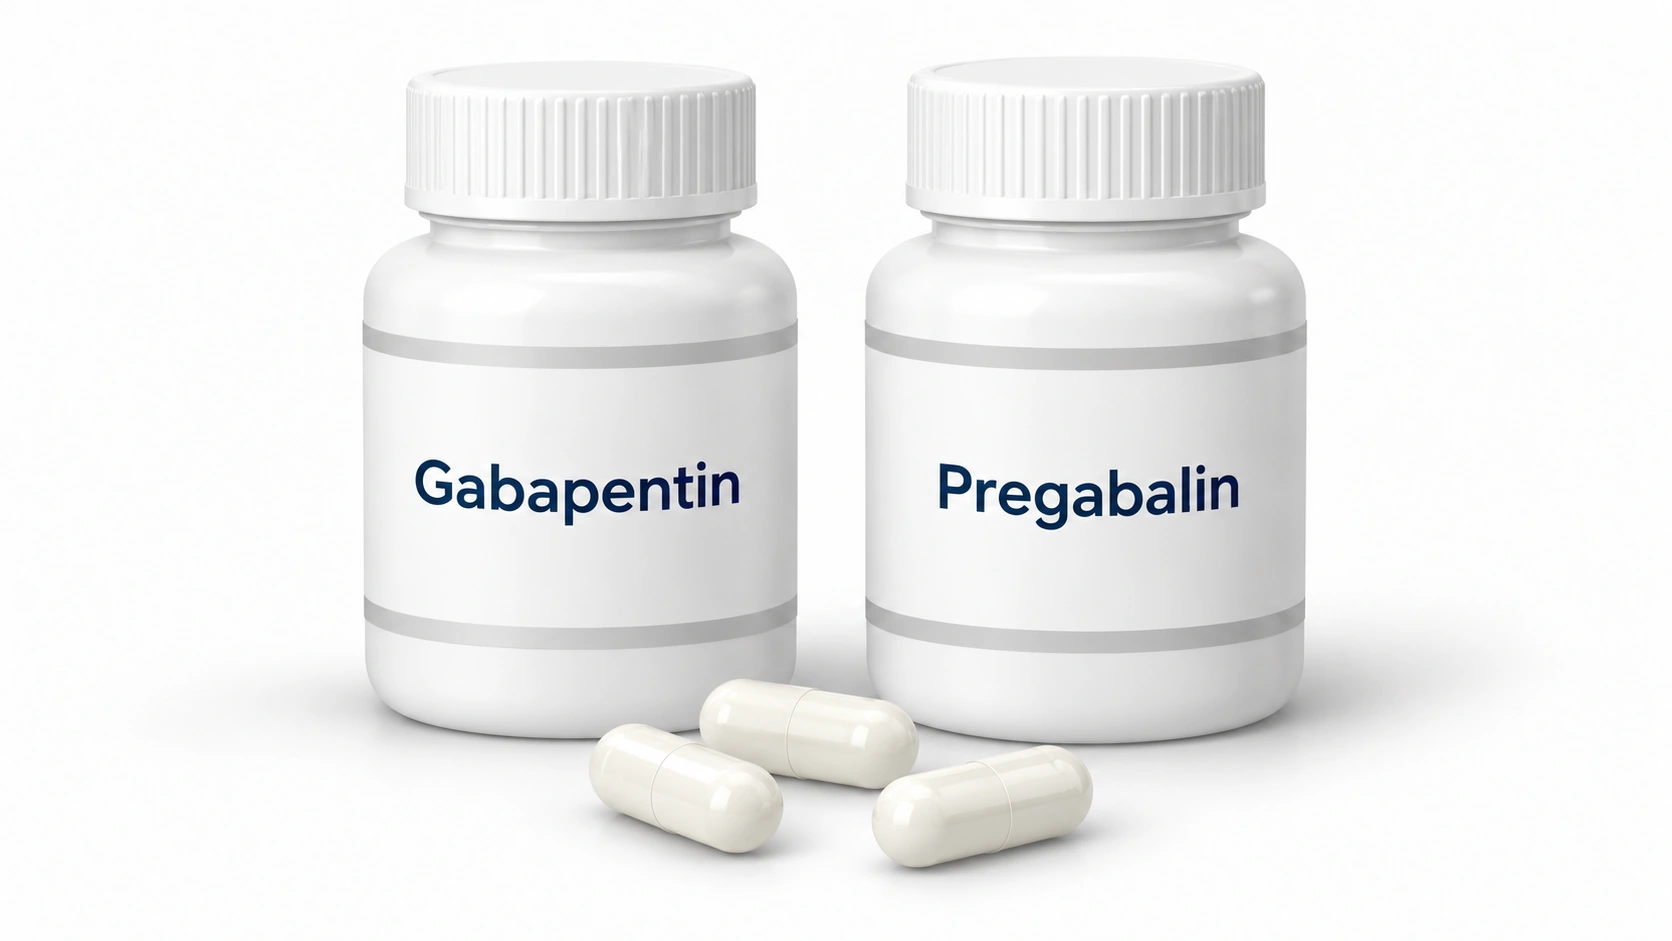
Two separate illustrative bottles labeled Gabapentin and Pregabalin beside plain capsules.

Gabapentin and pregabalin

Strong evidence

Nerve pain medicines rather than ordinary painkillers. They are the main treatment for pain that carries on after the rash heals, and they are often started during the episode when pain is severe. The dose is built up slowly, and they can make you drowsy or unsteady at first.

An illustrative bottle labeled Amitriptyline beside plain tablets.

Amitriptyline

Moderate evidence

A low dose of an old antidepressant, taken at night for nerve pain. It suits people whose shingles pain is keeping them awake. It takes a few weeks before you can judge it, and it is used carefully in older adults because of dry mouth, dizziness and confusion.

Prednisone — Header Image

Prednisone

Limited evidence

A short course of steroid tablets is sometimes added to antivirals for severe pain or when the facial nerve is involved. It can speed up rash healing and early pain a little. Studies have not shown that it prevents lasting nerve pain, and it is never given on its own for shingles.

Cephalexin

Cephalexin

Moderate evidence

The usual first antibiotic tablet for bacterial folliculitis that is deep, spreading or too widespread for a cream, and for boils with surrounding redness. A course is normally about seven days. It has no effect on yeast folliculitis or razor bumps, and if the same area keeps flaring after each course, the cause is still there rather than the antibiotic being wrong.

Trimethoprim-sulfamethoxazole

Trimethoprim-sulfamethoxazole

Moderate evidence

Used when resistant Staphylococcus aureus is likely or has been grown on a swab, which is the situation in which the first antibiotic did not work. This is the main reason for swabbing a spot before starting treatment. It is avoided in pregnancy and with some other medicines, so tell the prescriber everything you take.

16:9 hero for Fluconazole. Never cropped: the tone strip and the corner logo depend on the full frame.

Fluconazole

Limited evidence

An antifungal tablet, usually a short weekly course, for yeast folliculitis that is widespread or has not cleared with washes alone. It works faster and more completely than topical treatment on the chest and back. The yeast lives on everyone and comes back, so it is normally followed by an antifungal wash once a week to hold it.

An amber prescription bottle lying on its side on a white background with a plain white label reading Doxycycline, and six small round white tablets spilled out in front of it.

Doxycycline

Limited evidence

A longer course is sometimes used for stubborn or recurring folliculitis, partly for the bacteria and partly because it calms inflammation. It is a second choice rather than a first one, since it can allow yeast folliculitis to take hold. It also causes sunburn easily, so it needs daily sunscreen on anything the sun reaches.

Injections

Shingrix

Strong evidence

Two injections a few months apart, more than 90 percent effective at preventing shingles in adults 50 and over. It prevents rather than treats, so it is not used during an episode. It is still recommended once an episode has cleared, because having had shingles does not protect you from having it again.

None listed
Procedures
None listed
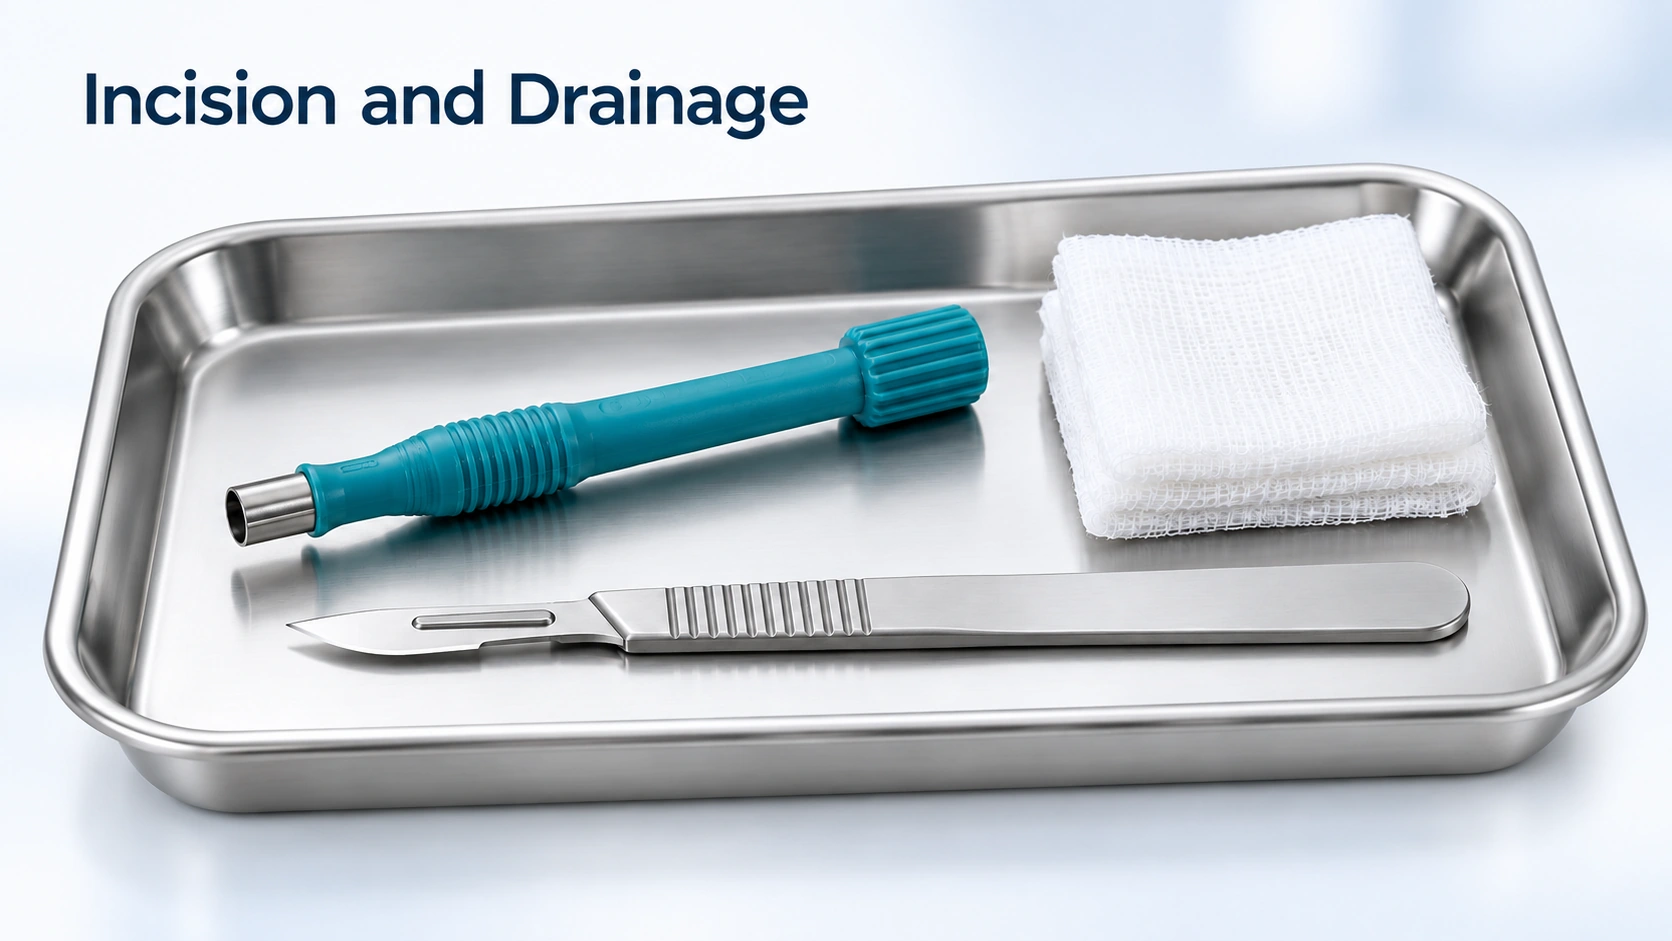
Editorial illustration for Incision and Drainage, based on the entry’s treatment or equipment reference.

Incision and Drainage

Moderate evidence

Draining a boil. A boil that has come to a head is opened with a small blade under local anesthetic and the pus is let out, which relieves the pain almost immediately. It is often the whole treatment, with antibiotics only added if the redness is spreading. Done properly it heals with a much smaller mark than a squeezed boil, which is the argument for having it done rather than attempting it at home.

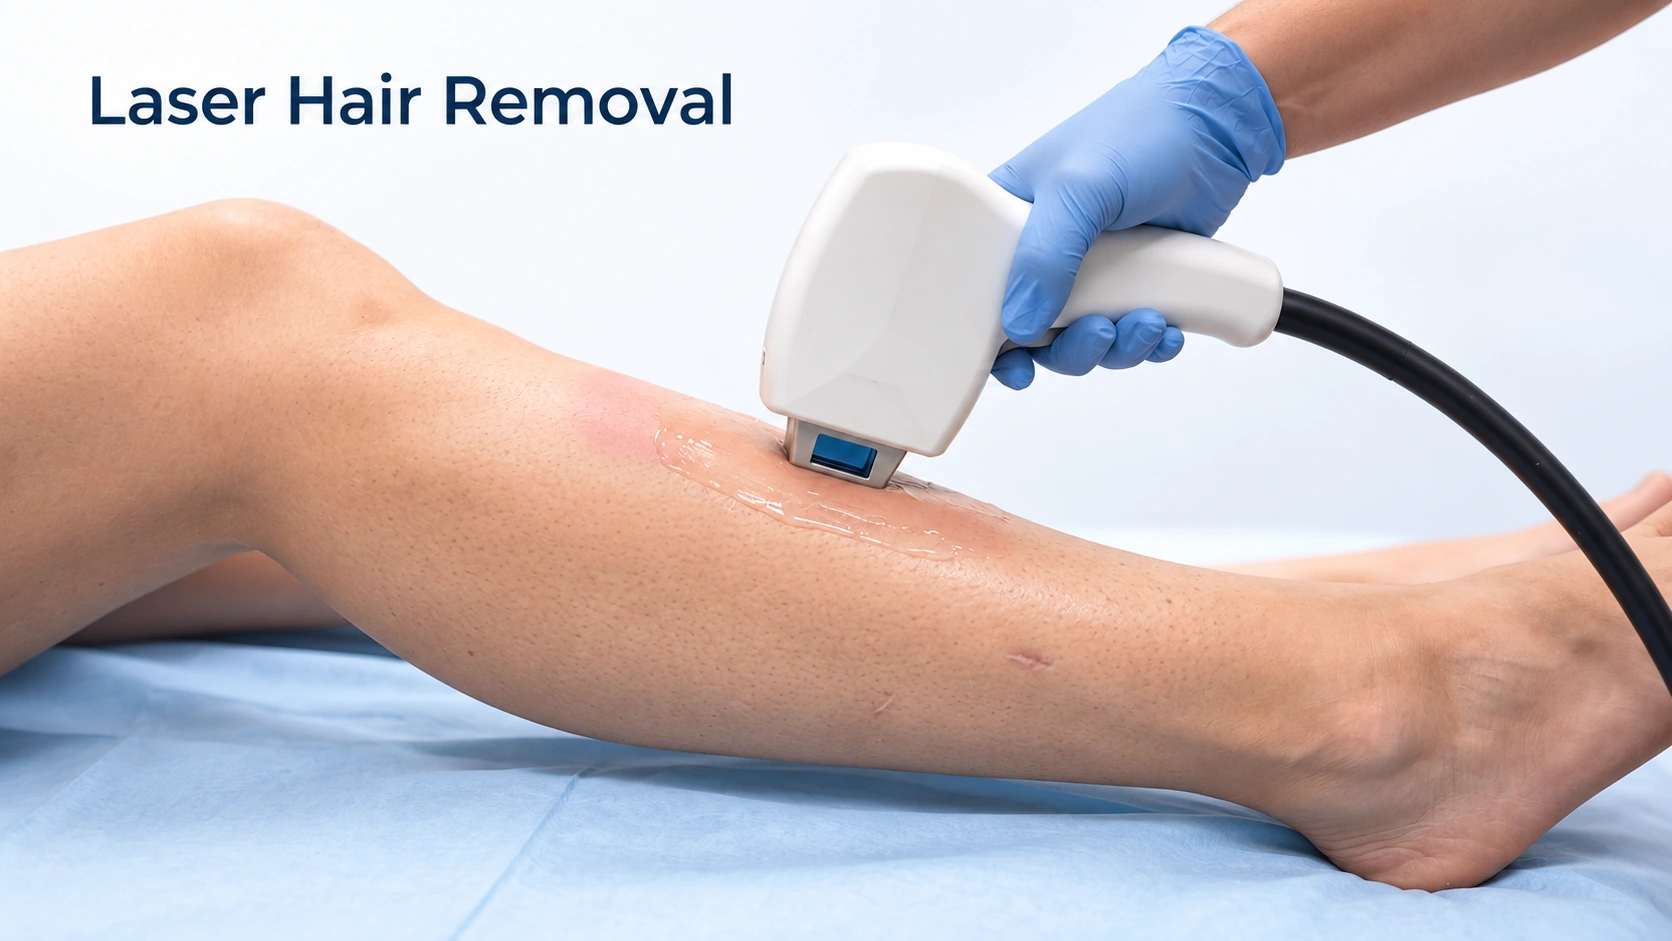
Editorial illustration for Laser Hair Removal, based on the entry’s treatment or equipment reference.

Laser Hair Removal

Limited evidence

For folliculitis and razor bumps driven entirely by shaving, particularly in the beard and neck, reducing the hair removes the cause instead of treating the result. It usually takes six or more sessions and works best with a device suited to your skin tone, since the wrong one can burn or leave marks on deeper skin. It is worth considering after months of the same bumps rather than after one crop.

Outlook

Long term

An episode runs two to four weeks, the pain sometimes longer. Most people get it once, though it can recur if the immune system is suppressed.

Many superficial cases settle with appropriate care, but repeated episodes need assessment for an ongoing contributor such as shaving, friction or infection. The course depends on the type; deeper inflammation can take longer to heal and may scar.

Complications

Possible complications
  • Postherpetic neuralgia
  • Shingles in the eye
  • Shingles in the ear
More details

Postherpetic neuralgia
Nerve pain that carries on after the skin has healed, because the virus damaged the nerve it traveled down. It is the most common complication of shingles, and the risk climbs steeply with age. Starting antiviral tablets within 72 hours and controlling the pain properly from day one both lower the chance of it. It is treatable, so it is worth going back rather than waiting for it to fade.

Shingles in the eye
When the affected nerve serves the forehead and eye, blisters appear on the forehead, the eyelid or the tip and side of the nose, and the eye itself can be involved. It can cause lasting damage to sight. Blisters anywhere in this area are a same-day problem, and often need an eye specialist as well as antiviral tablets.

Shingles in the ear
Blisters in or around one ear, together with weakness on that side of the face, and sometimes a change in hearing, ringing or dizziness. It is uncommon. It needs urgent treatment, because the facial nerve recovers better the sooner antiviral tablets and steroids are started.

  • Boils and carbuncles
  • Cellulitis
  • Keloid scars
More details

Boils and carbuncles
When the infection goes further down the follicle it becomes a boil: a tender, swollen lump that comes to a head over several days. Several joined together are called a carbuncle. Squeezing is what turns a surface bump into one of these, so warm compresses and leaving it alone are the right first move. Boils often need draining or oral antibiotics, and they can leave a scar.

Cellulitis
Sometimes the infection leaves the follicle and spreads into the surrounding skin. The signs are redness, swelling and warmth spreading outward from the spot rather than staying in it, sometimes red streaks running away from it, and often a fever. That is a same-day problem needing oral antibiotics, and it is more likely in people with diabetes or a weakened immune system.

Keloid scars
Deep folliculitis on the chest, shoulders, jawline and the back of the neck can heal into raised, thickened scars, and that risk is higher on deeper skin tones. At the nape there is a specific pattern, acne keloidalis nuchae, where the bumps become firm and permanent and the hair in that patch is lost. It responds far better to early treatment than to waiting, so firm bumps building at the back of the neck are a reason to be seen rather than to keep treating at home.

When to get help

When to get help

Seek prompt care when shingles is suspected because antivirals work best early. Eye or ear involvement, widespread blisters or weakened immunity needs urgent assessment.

Arrange assessment if the rash persists, keeps returning, is extensive or has not responded to treatment. A pustule swab may help distinguish bacteria and guide treatment.

Seek prompt medical care for fever, rapidly spreading redness or warmth, worsening pain, a large deep lump, or feeling unwell. Seek care earlier if your immune system is suppressed.

Bumps around the eye with eye pain, swelling, light sensitivity or vision change need prompt assessment. Do not apply body washes or skin medicines into the eye.

Common questions

Shingles:Am I contagious?

Not with shingles - nobody catches shingles from you. But the blister fluid can give chickenpox to someone who has never had chickenpox and never been vaccinated. Keep the rash covered, wash your hands, and stay away from newborns, pregnant people who are not immune, and anyone immunosuppressed until it crusts.

Shingles:Is it too late for antivirals if I am past 72 hours?

Possibly not. The evidence is strongest inside 72 hours, but treatment is often still given if new blisters are forming, if you are older, if the rash involves the face or eye, or if you are immunosuppressed. Being late is a reason to be seen today.

Shingles:What is postherpetic neuralgia?

Nerve pain that continues after the rash heals, from damage to the nerve the virus traveled down. Much more common in older adults, and it can last months. It is treatable with different drugs from ordinary painkillers, so go back rather than waiting it out.

Shingles:Should I get the vaccine if I have already had shingles?

Generally yes. One episode does not protect you from another, and vaccination is recommended once an episode has cleared. Ask your doctor about timing.

Shingles:Why is it only on one side?

The virus travels down a single sensory nerve, and each nerve supplies a strip of skin on one side. That is also why the rash stops abruptly at the midline - one of the clearest clues.

Shingles:Can I get it more than once?

Yes, though most people do not. Recurrence is more likely if your immune system is suppressed. If it has happened more than once, ask whether anything underlying should be looked into.

Folliculitis:How do I tell folliculitis from acne?

Look for blackheads and whiteheads. Acne has them, folliculitis does not. Folliculitis bumps are all the same size, each sits at a hair, they itch more than they hurt, and they appear where you shave, sweat or rub - thighs, buttocks, beard, chest, back. Acne sits on the face, chest and upper back, has spots of different sizes, and is not itchy.

Folliculitis:Is it contagious?

Mostly not in ordinary contact. The bacteria can pass through shared razors, towels, unwashed sports gear and close skin contact - avoid those while it is active. Yeast folliculitis and razor bumps are not caught.

Folliculitis:Why does it keep coming back in the same place?

Because the cause is still there - the shaving method, friction, damp clothes, or a yeast cause treated as bacterial. Some people also carry Staphylococcus aureus long term, which can be tested and treated.

Folliculitis:Can I still shave?

Yes, but change how. A fresh single-blade or safety razor, with the grain, with gel, and no stretching the skin. Take days off while the skin is inflamed. For persistent razor bumps, laser hair reduction is a longer-term option.

Folliculitis:Should I use hydrocortisone on the itch?

Not on undiagnosed bumps. Steroid creams calm the itch for days while the infection carries on underneath, and the rash comes back more widespread. If itch is the main problem, a medicated wash and cool compresses are safer.

Folliculitis:Will it scar?

Superficial folliculitis heals without scarring, though flat dark marks take months to fade on deeper skin tones. Deep folliculitis and boils can scar, and firm raised bumps at the back of the neck can scar permanently - reasons to be seen early rather than keep treating at home.
Sources

Sources and further reading

  1. DermNet

  2. DermNet: Folliculitis
  3. DermNet: Bacterial folliculitis
  4. American Academy of Dermatology: Acne-like breakouts could be folliculitis
Dermapedia on YouTube