Post-Inflammatory Hyperpigmentation vs Sun Spots

Post-inflammatory hyperpigmentation is the flat brown or gray mark left behind after a spot, rash or injury heals. It is not a scar, and given time and sun protection it fades. Sun spots are flat brown patches that build up on the skin the sun reaches most, such as the face, the backs of the hands and the chest. They are harmless, but they are a record of past sun exposure.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
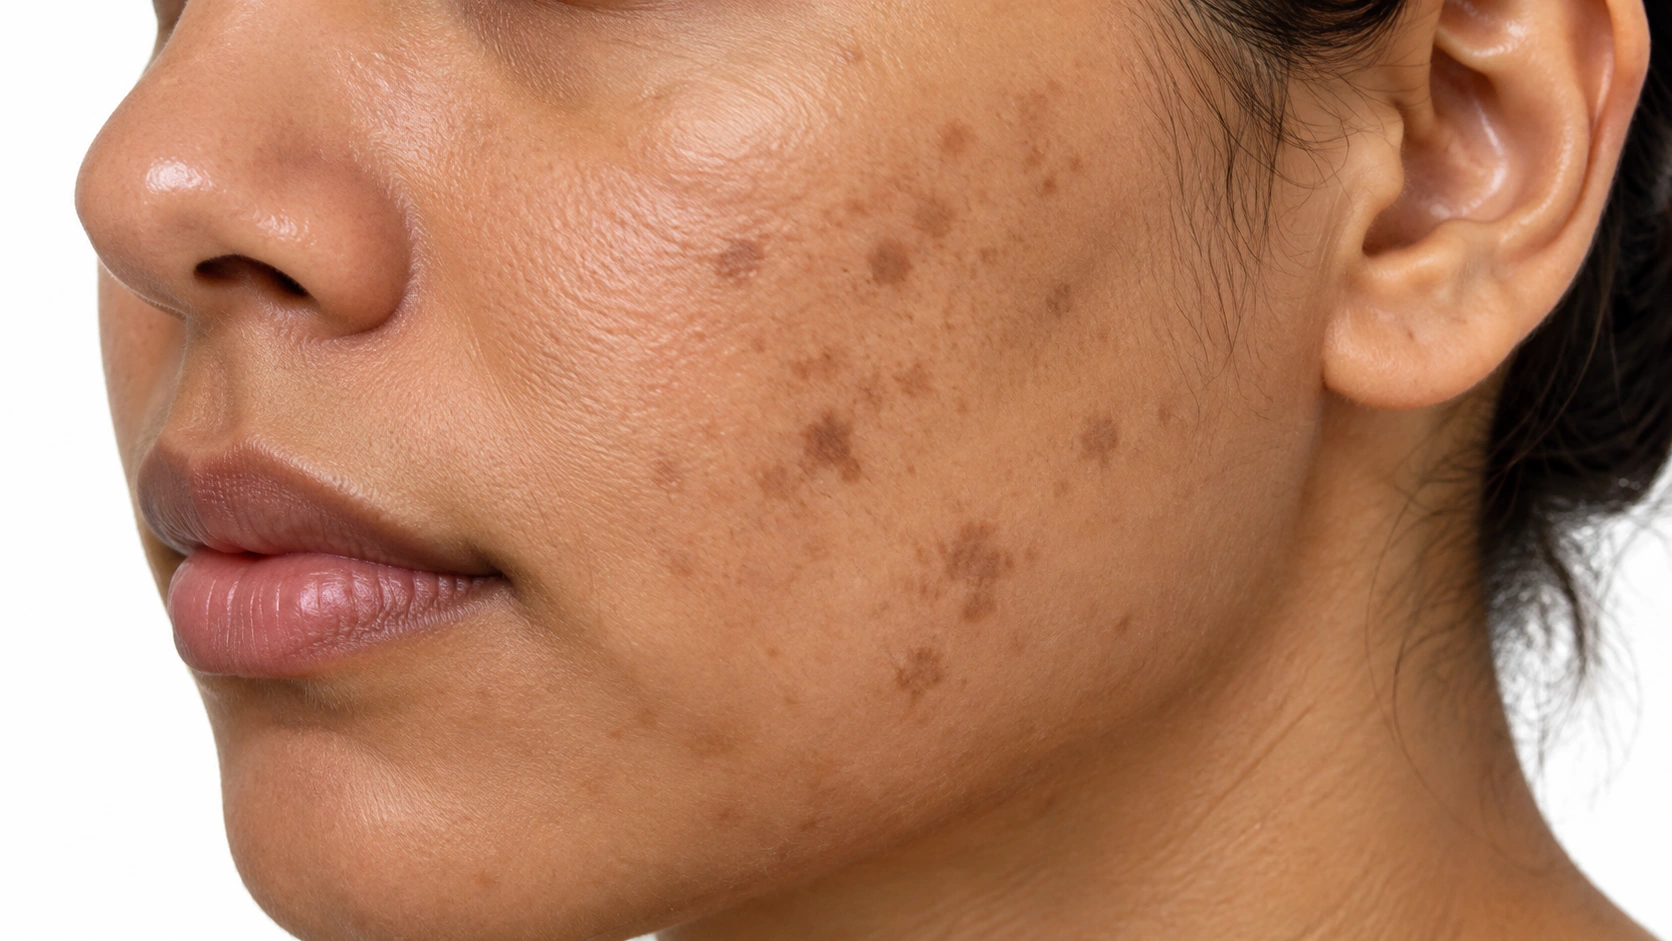
Flat light-brown residual marks on a fair cheek.AI-generated educational illustration of Sun Spots: 1. Sun Spots Header — Light Skin; Lighter skin. Not a clinical photograph.

Key differences

The same eight facts on every condition comparison.

Usual age
Any age
40 and over
Where
Where skin was inflamed
Face, hands, chest, forearms
Main sign
Flat brown or grey mark
Flat even brown patches
Itch or pain
Neither
Neither
Contagious
No
No
Long term
Fades over months
Stay; more appear
Scars
No
No
Who gets it
Darker skin tones most
Fair skin, sun exposure

What is it?

Post-Inflammatory Hyperpigmentation
Sun Spots
What is it?

It is pigment left after inflammation.
Inflammation increases or redistributes pigment in the skin.

It mirrors the original lesion.
Marks often follow the shape and location of the earlier spot.

Active disease may coexist.
Old pigment does not mean inflammation is controlled.

Pigment differs from scarring.
A flat dark mark is not the same as a raised or sunken scar.

It is a flat area of pigment.
A solar lentigo is a defined patch of increased pigmentation linked to ultraviolet exposure.

It appears on sun-exposed skin.
Spots often develop on the face, hands, forearms and shoulders.

"Liver spot" is a misnomer.
The common name does not mean the liver is involved.

Diagnosis comes first.
Atypical spots can resemble melanoma in situ, so uncertain lesions are examined before any cosmetic treatment.

What it looks like

Post-Inflammatory Hyperpigmentation

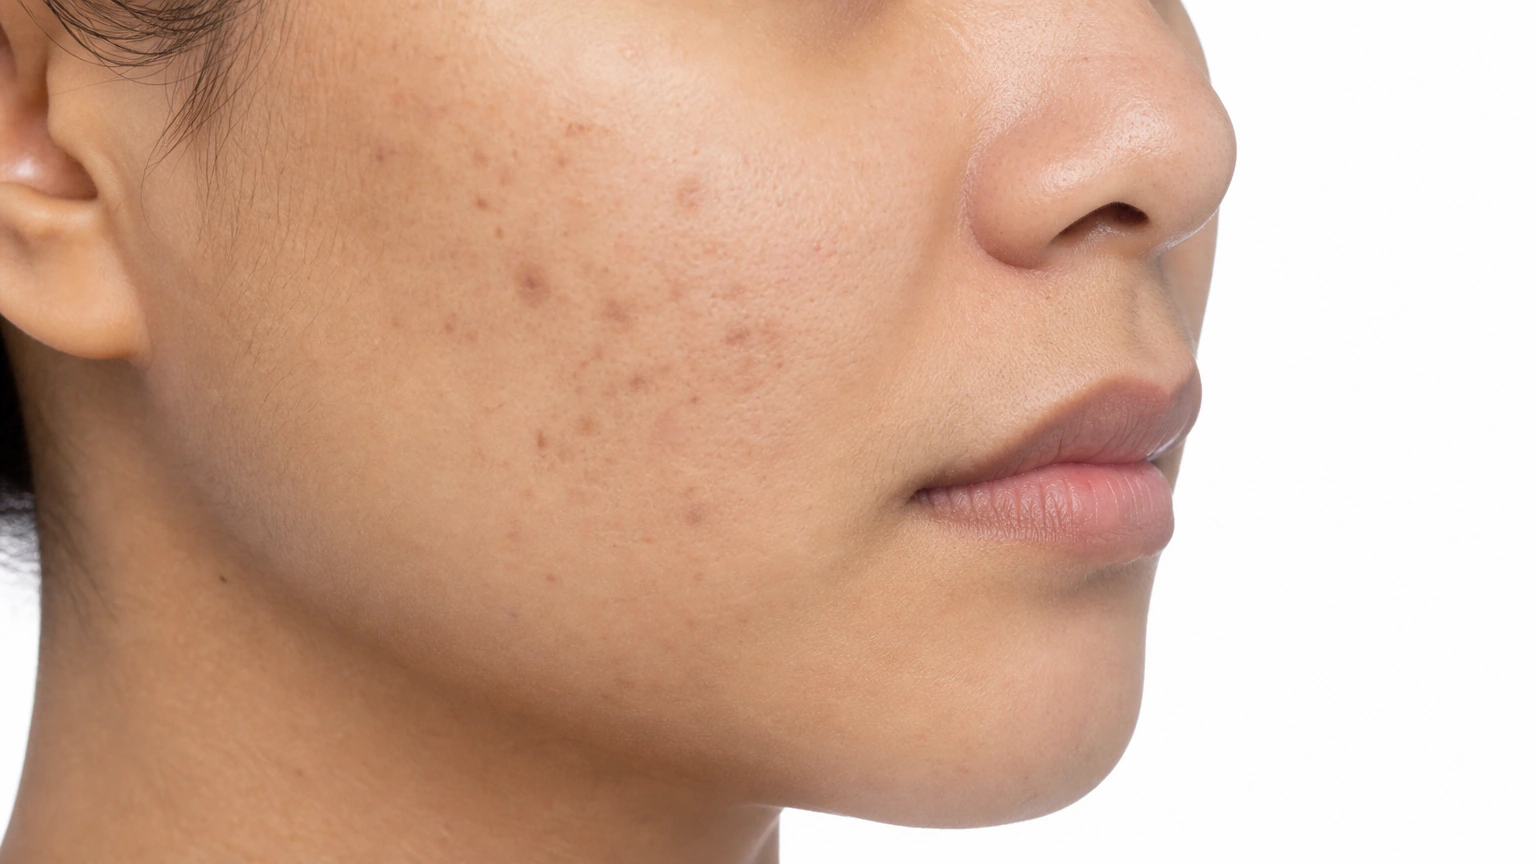
Flat brown residual marks after acne on the cheek, representing epidermal post-inflammatory pigmentation.

Epidermal hyperpigmentation Brown, in the surface; fades faster.

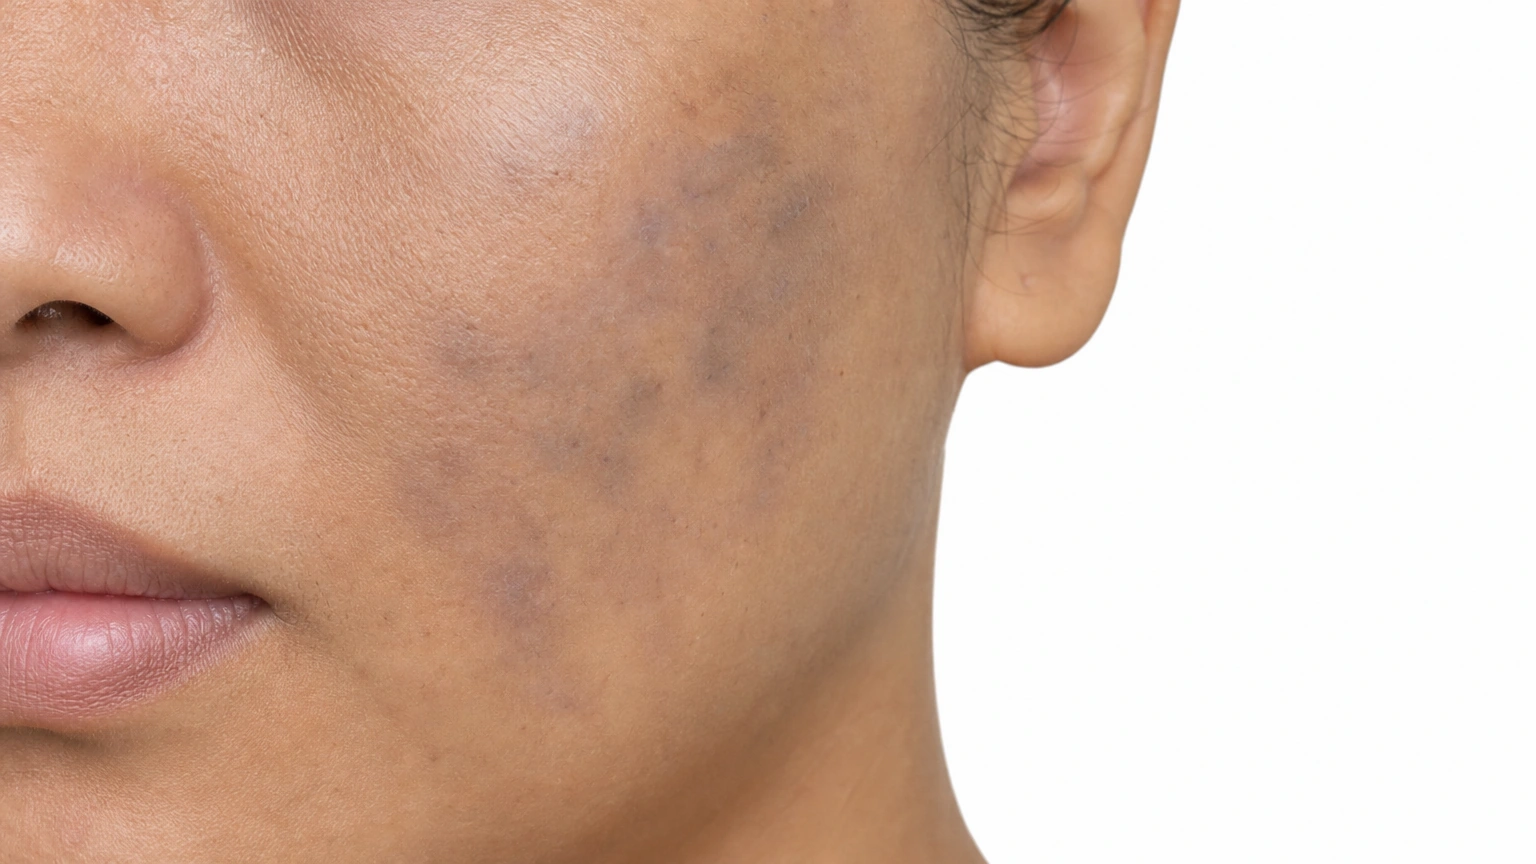
Flat blue-gray residual marks on the cheek, representing deeper post-inflammatory pigment.

Dermal hyperpigmentation Blue-gray, deeper; fades slowly.

Sun Spots

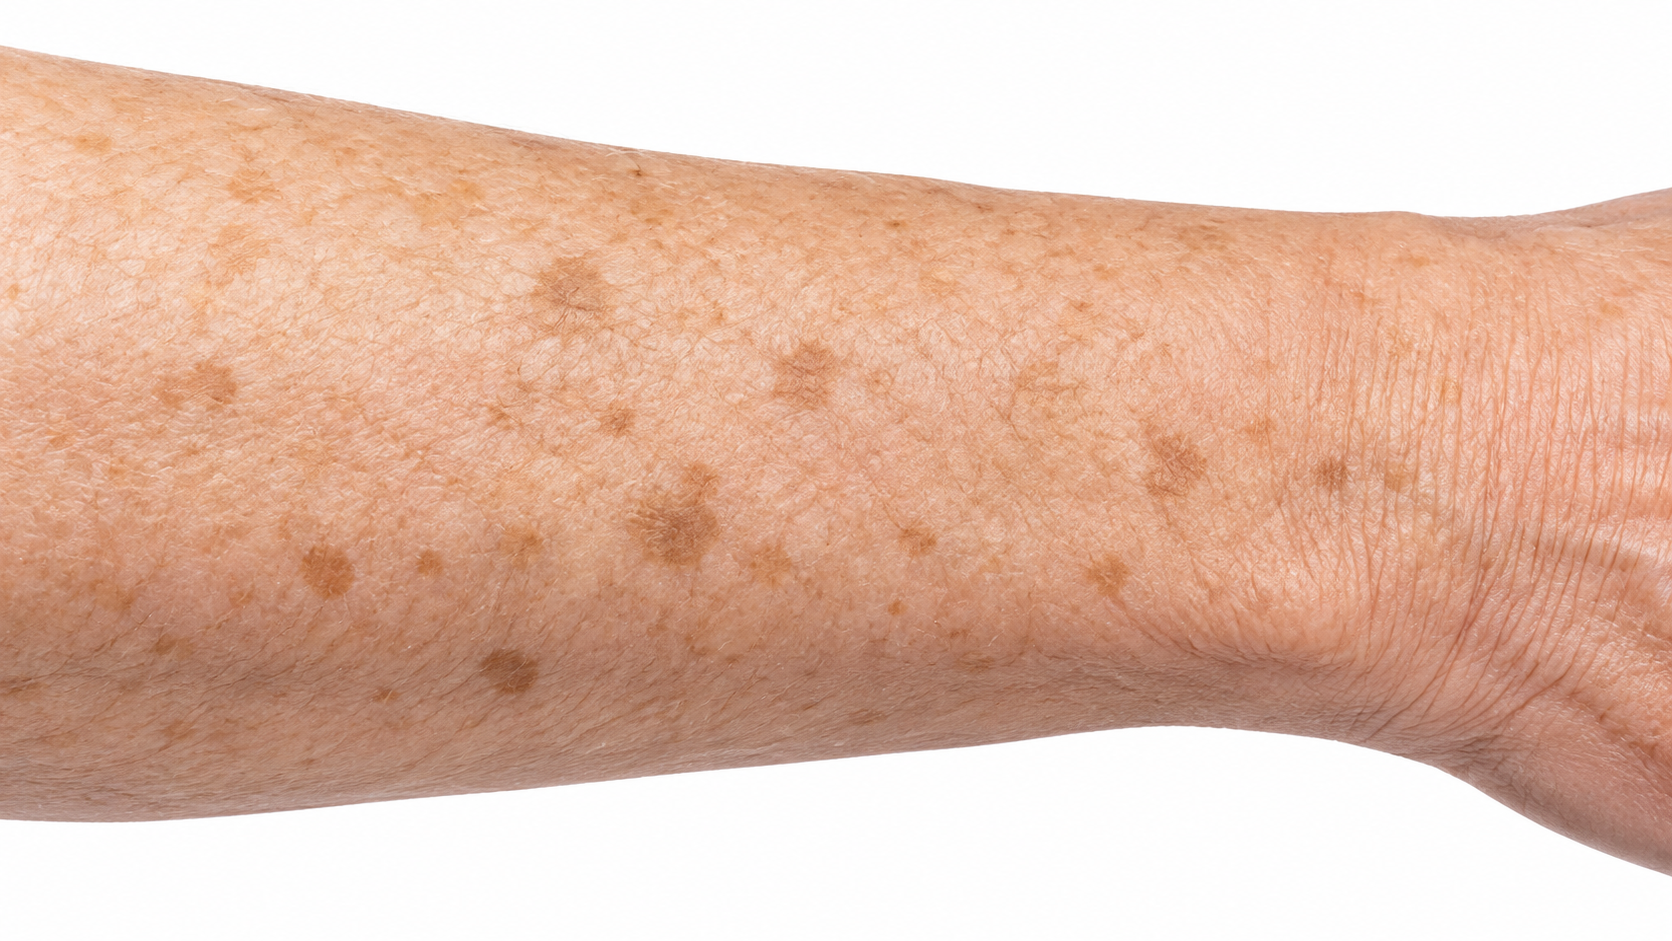
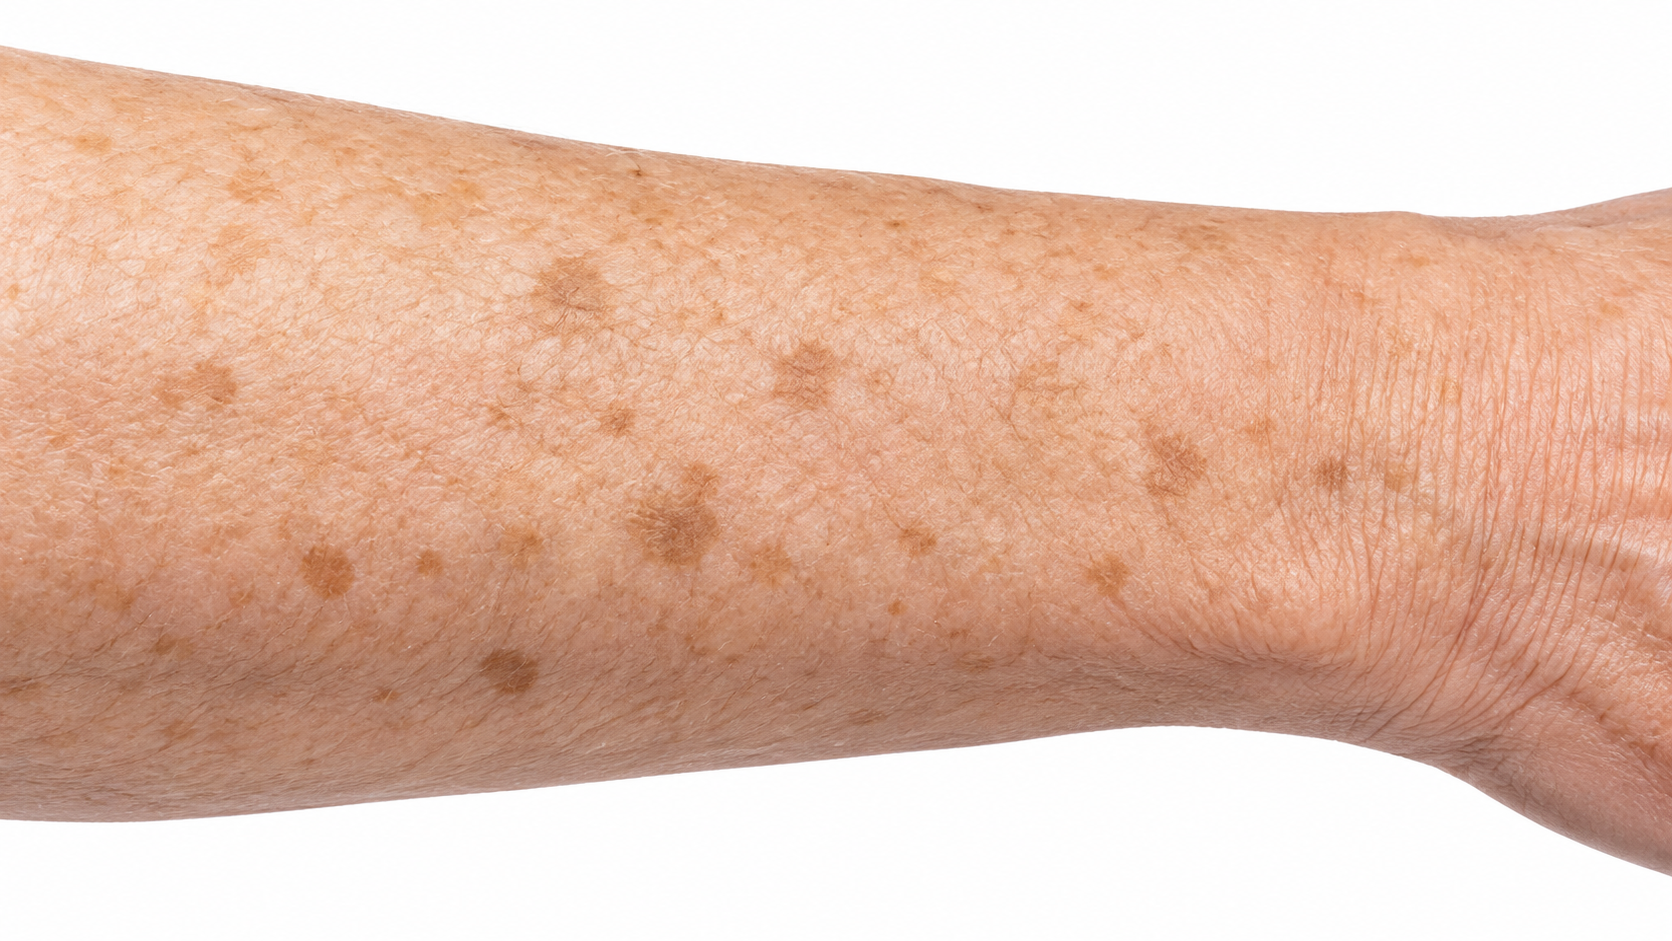
Sun Spots: Flat brown spots.

Flat brown spots Even tan to brown color.

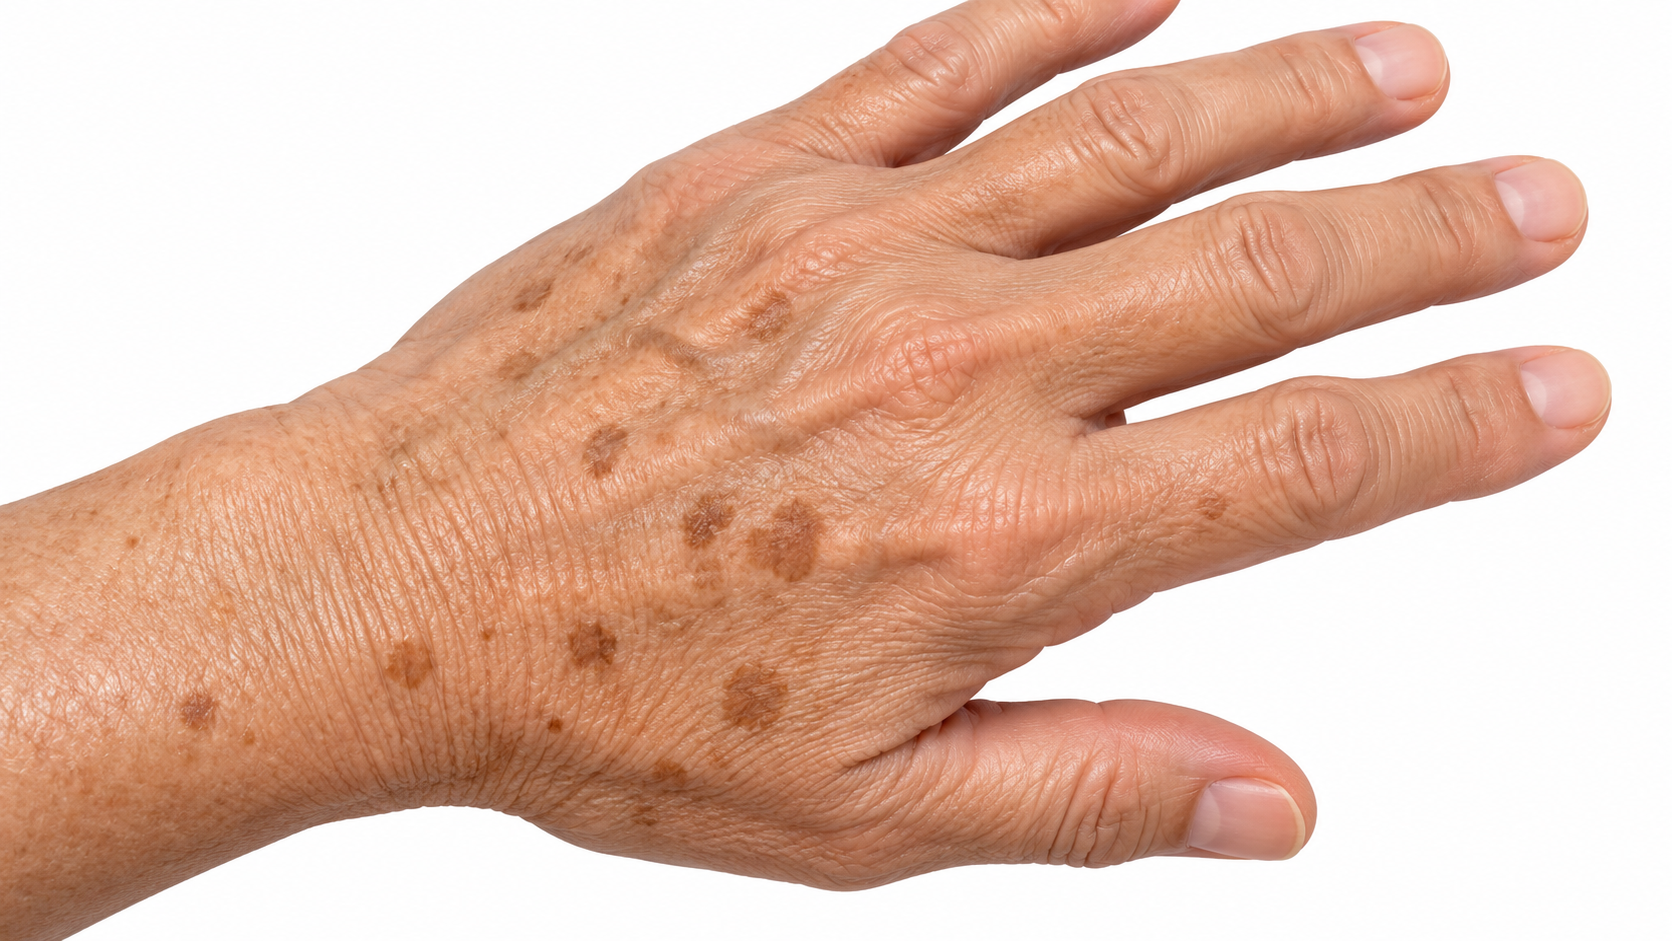
Sun Spots: Backs of the hands.

Backs of the hands One of the most common sites.

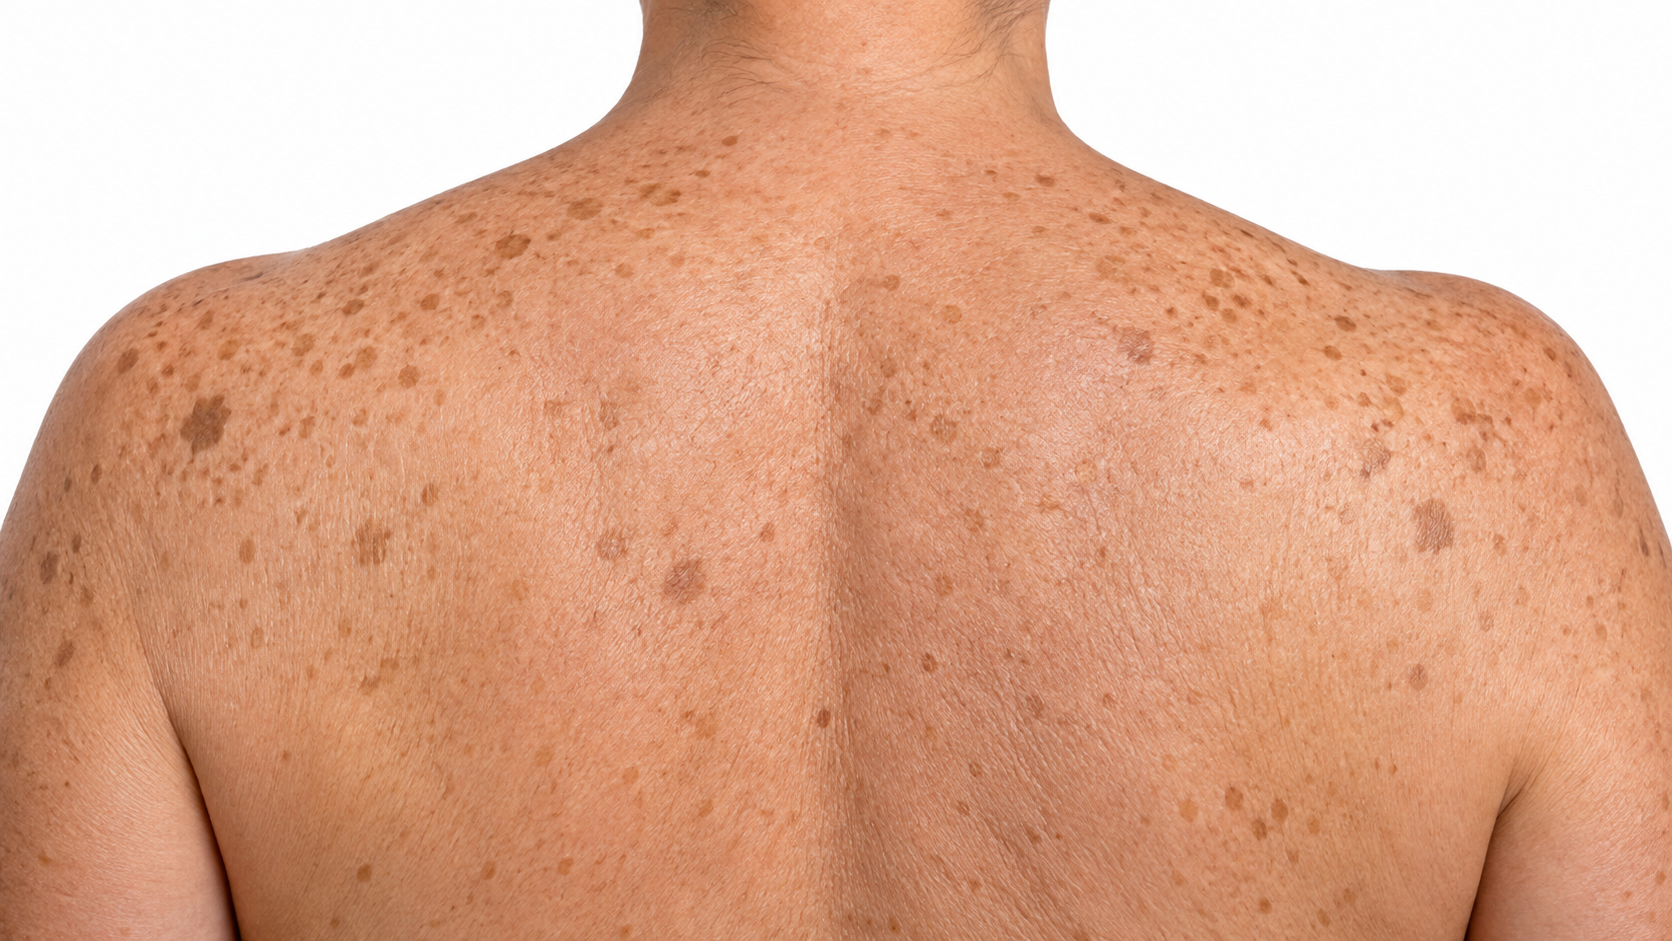
Sun Spots: Shoulders.

Shoulders Clusters after years of sun.

Skin tones
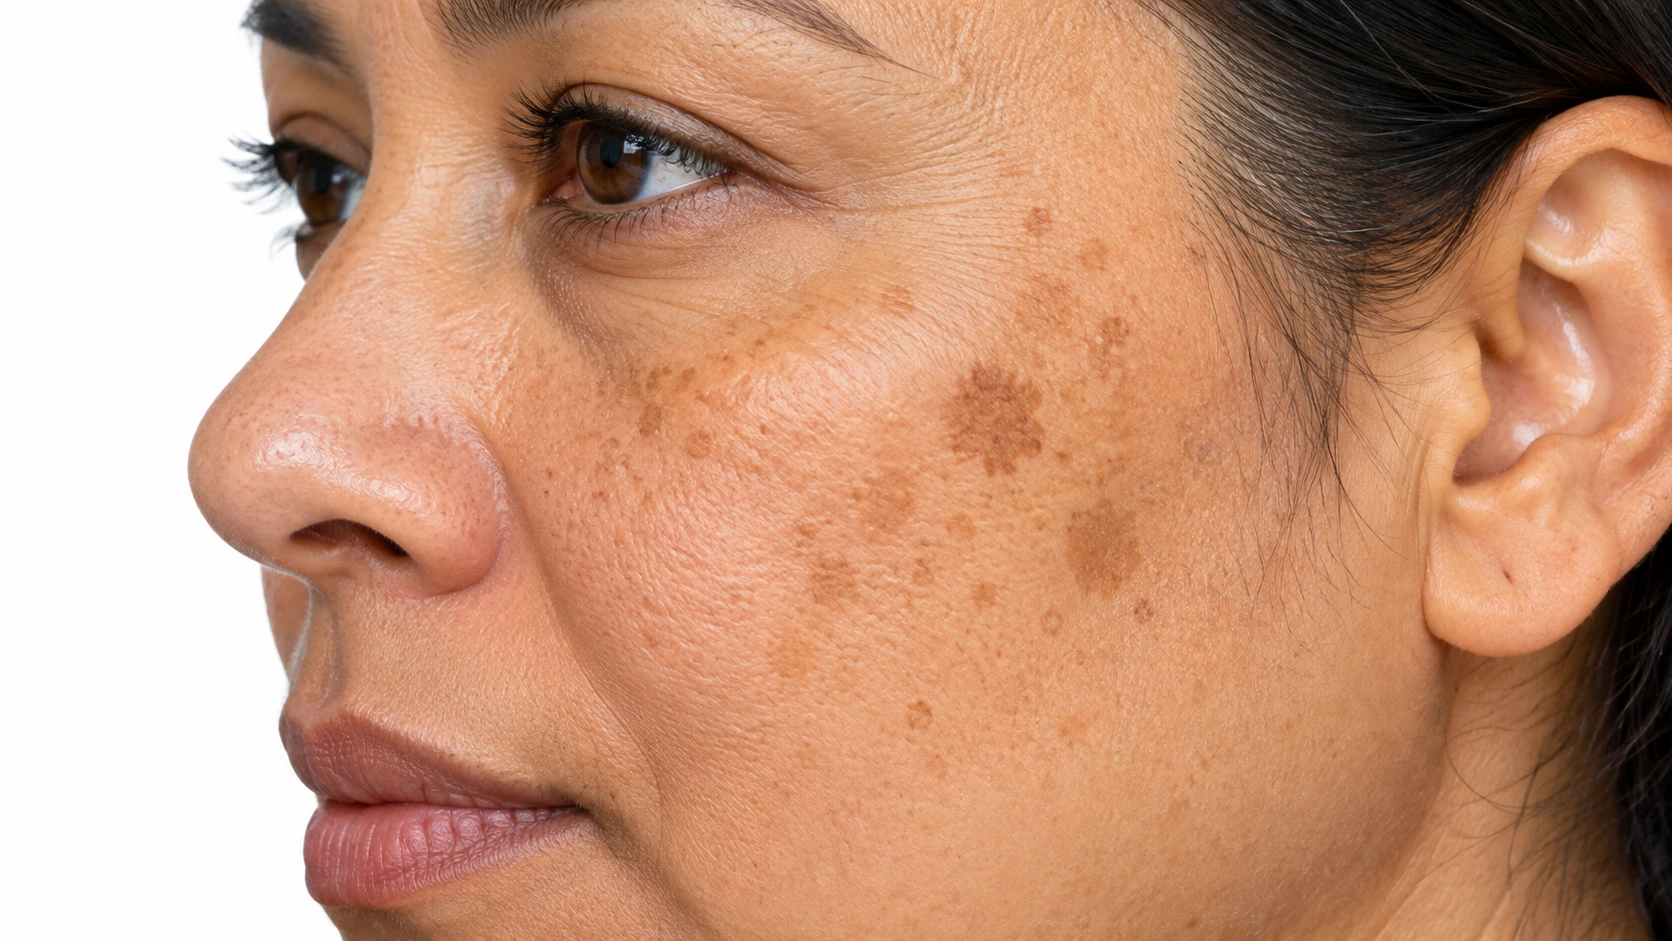
Flat light-brown residual marks on a fair cheek.
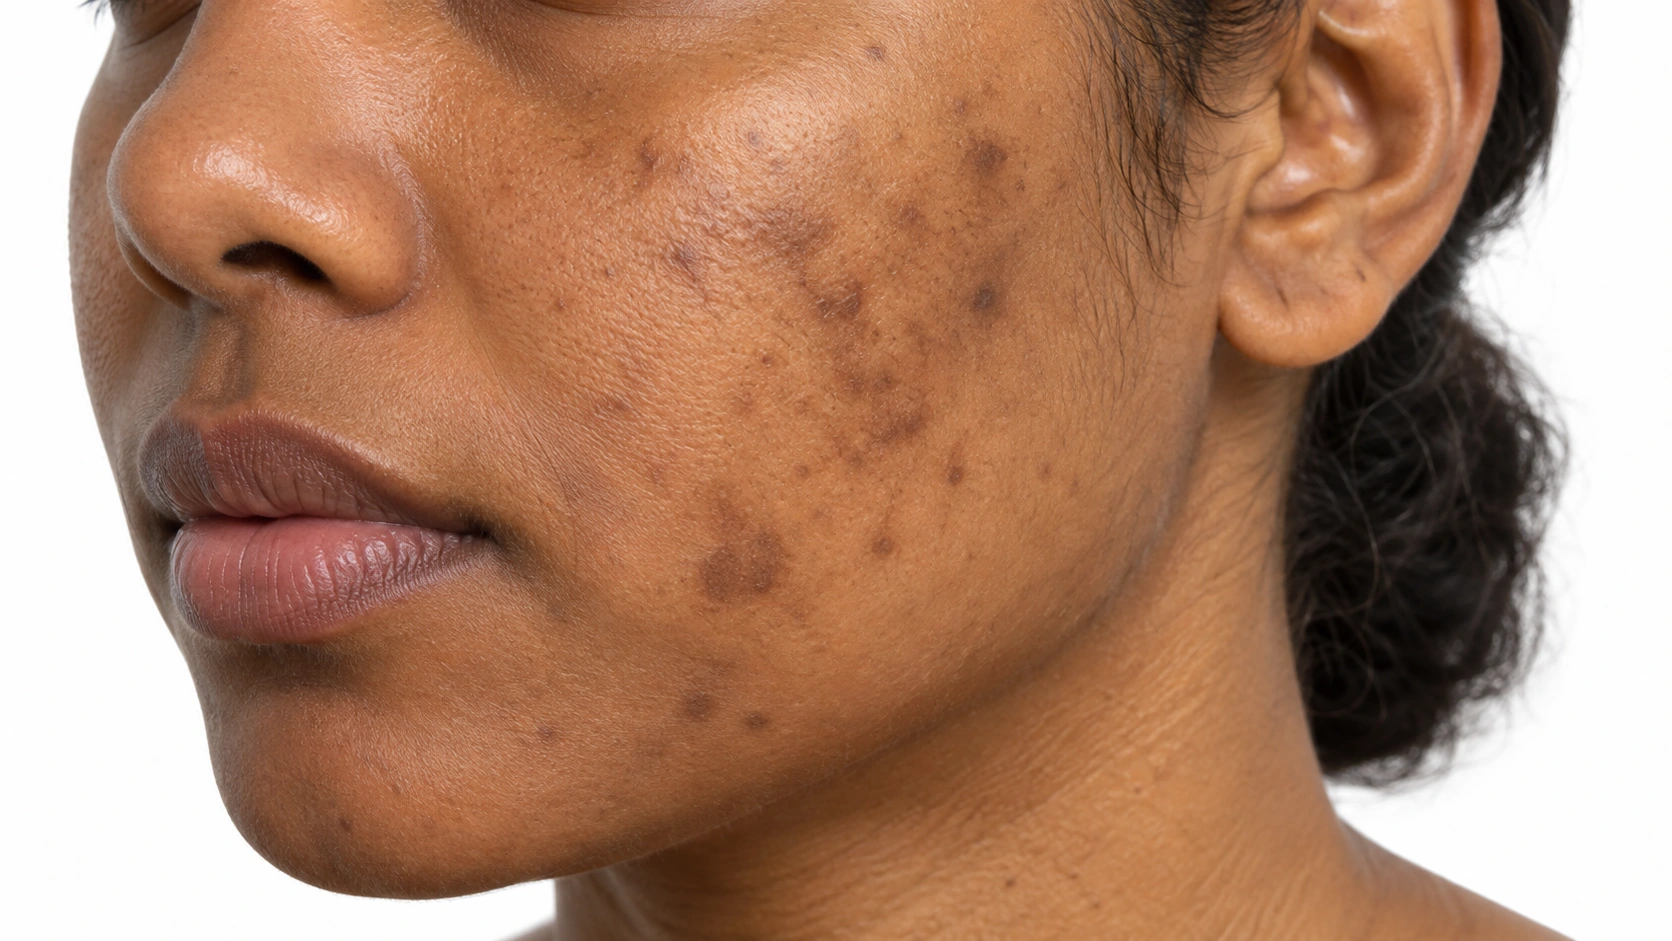
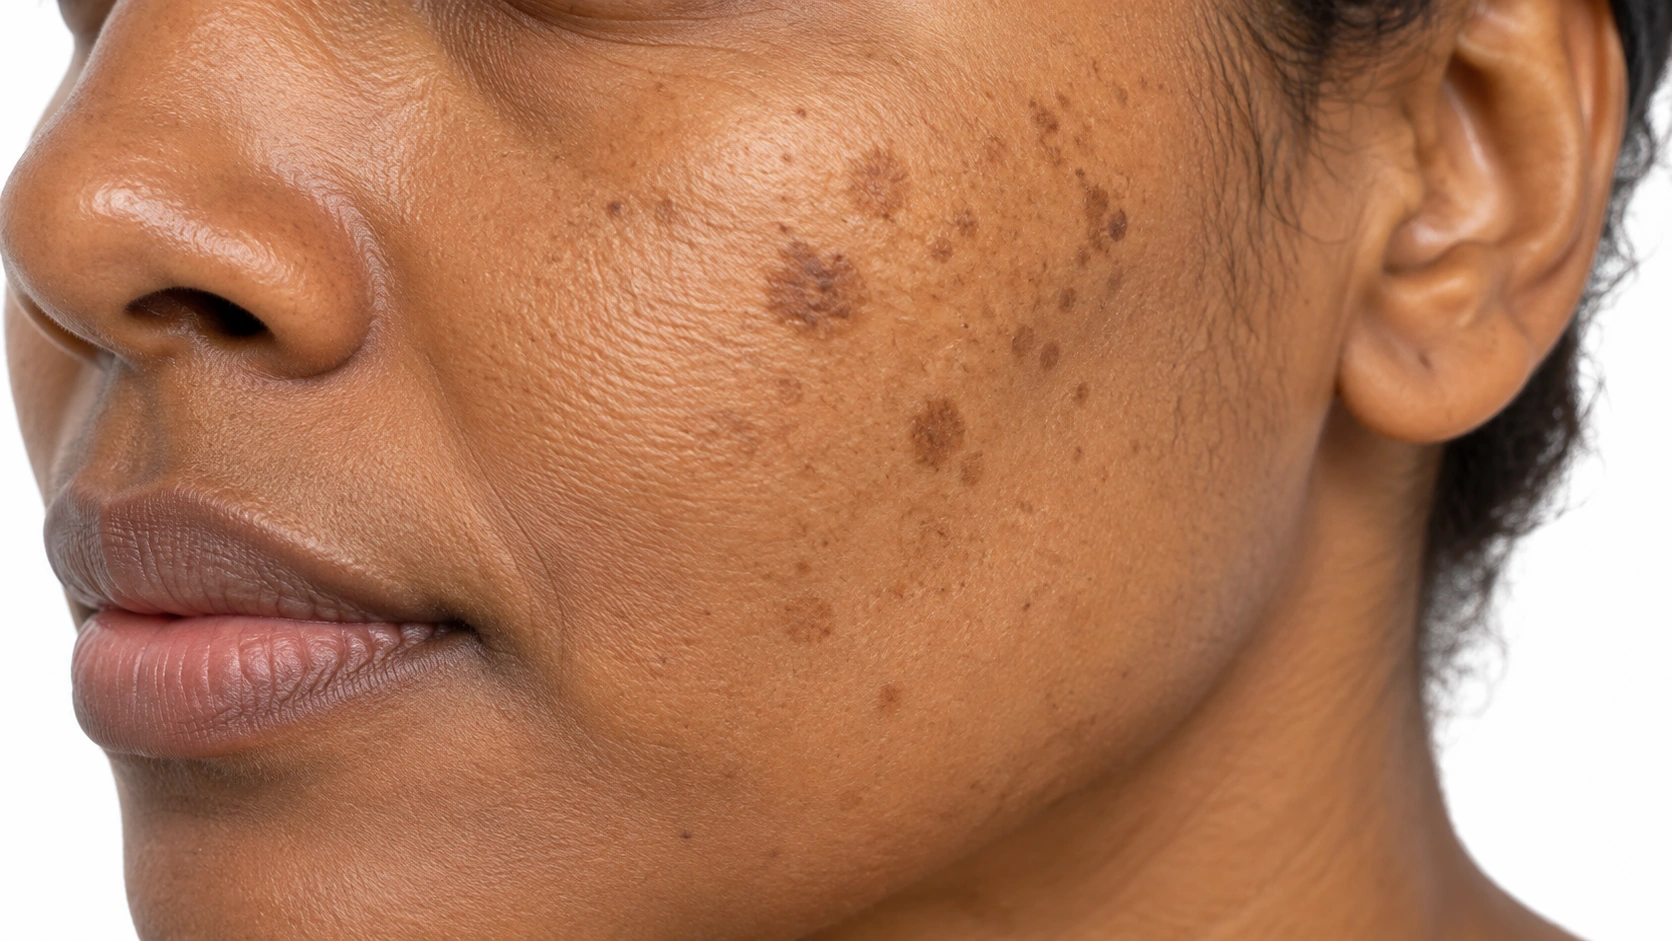
Flat residual brown marks on a medium-toned cheek.
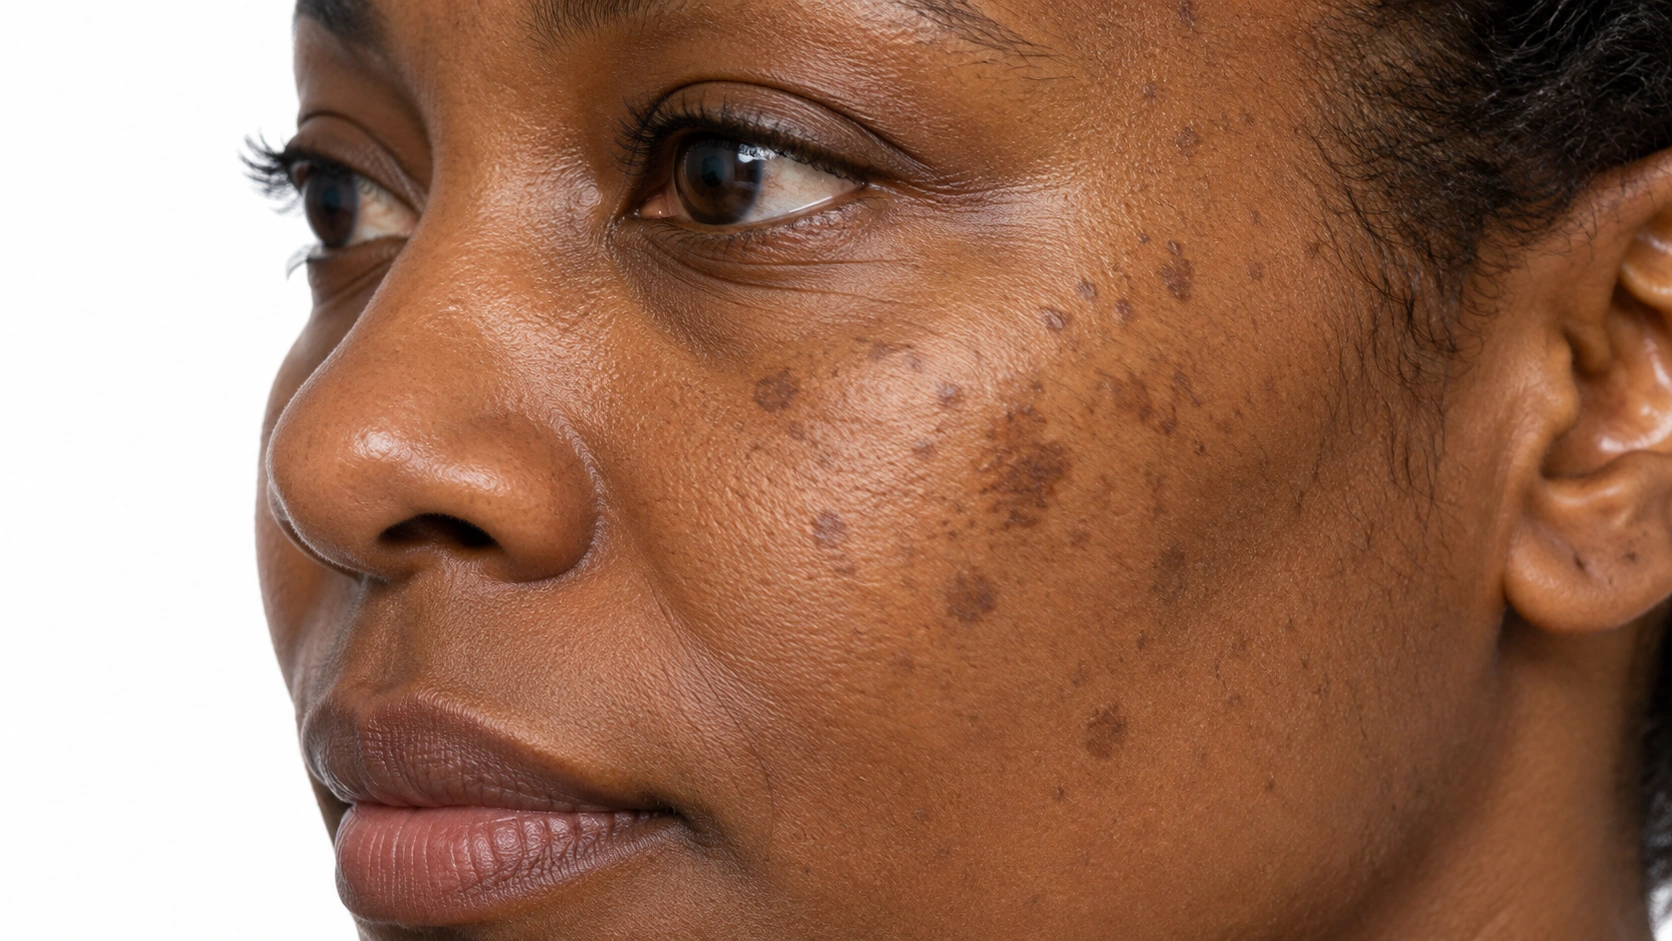
flat residual brown marks on a brown-skinned cheek, representing post-inflammatory hyperpigmentation.
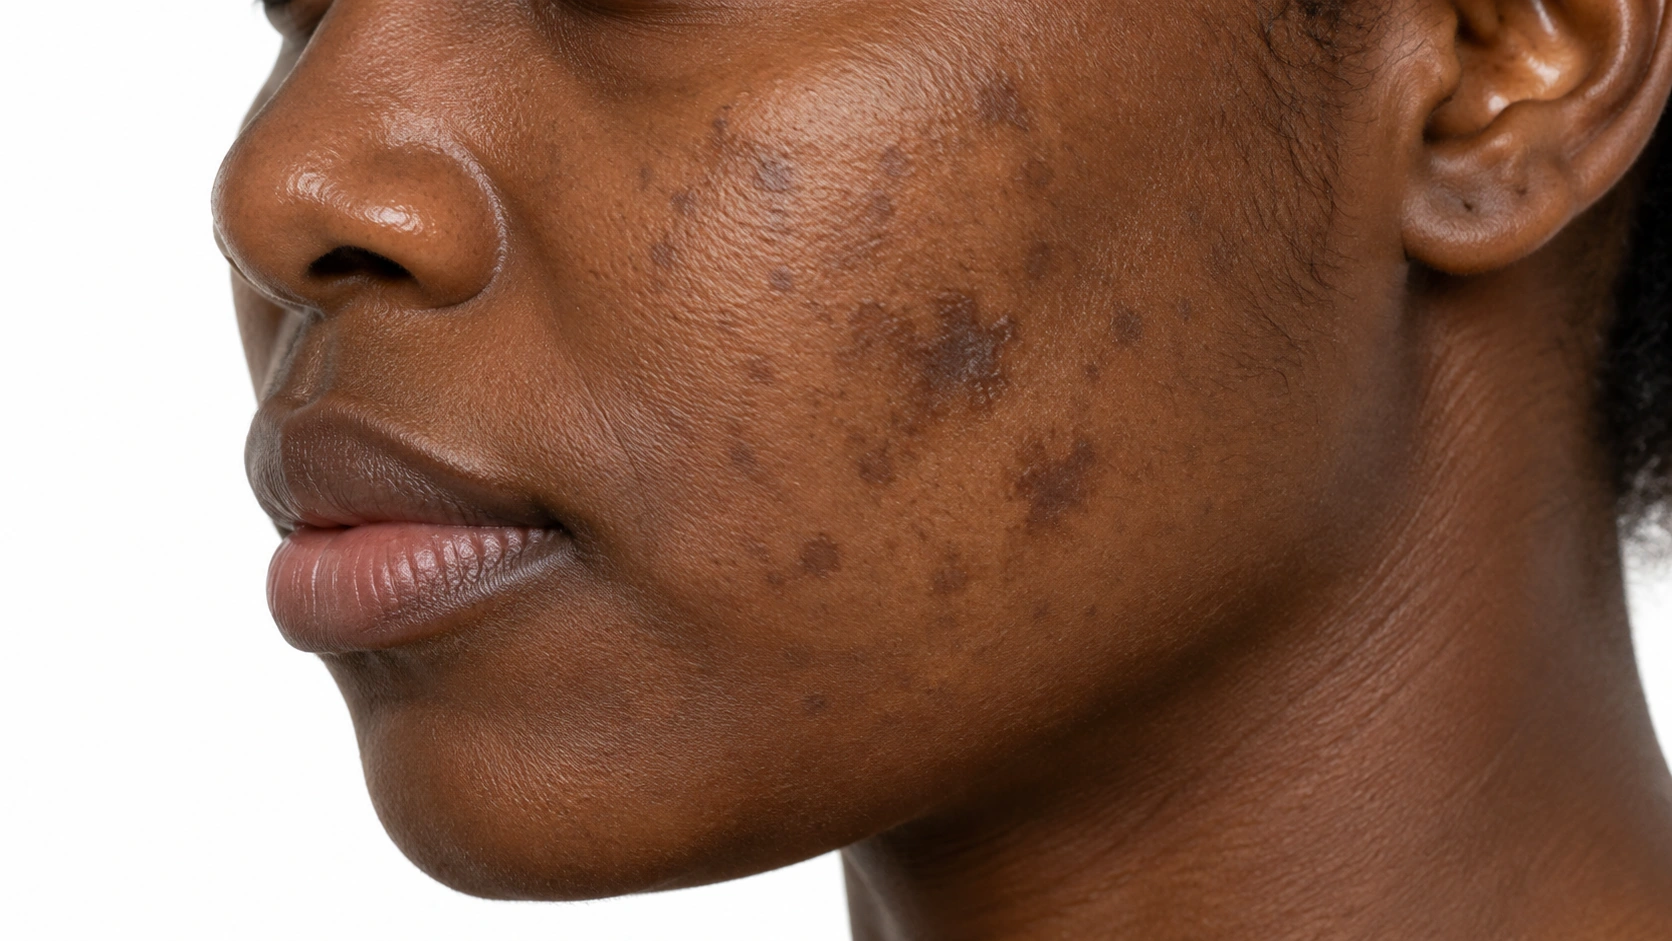
flat residual brown marks on deep brown cheek skin.
Sun Spots: 1. Sun Spots Header — Light Skin; Lighter skin.
Sun Spots: 2. Sun Spots Header — Medium Skin; Medium skin.
discrete flat brown sun spots on a brown-skinned cheek.
discrete flat dark-brown sun spots on a deep brown cheek.
Diagram
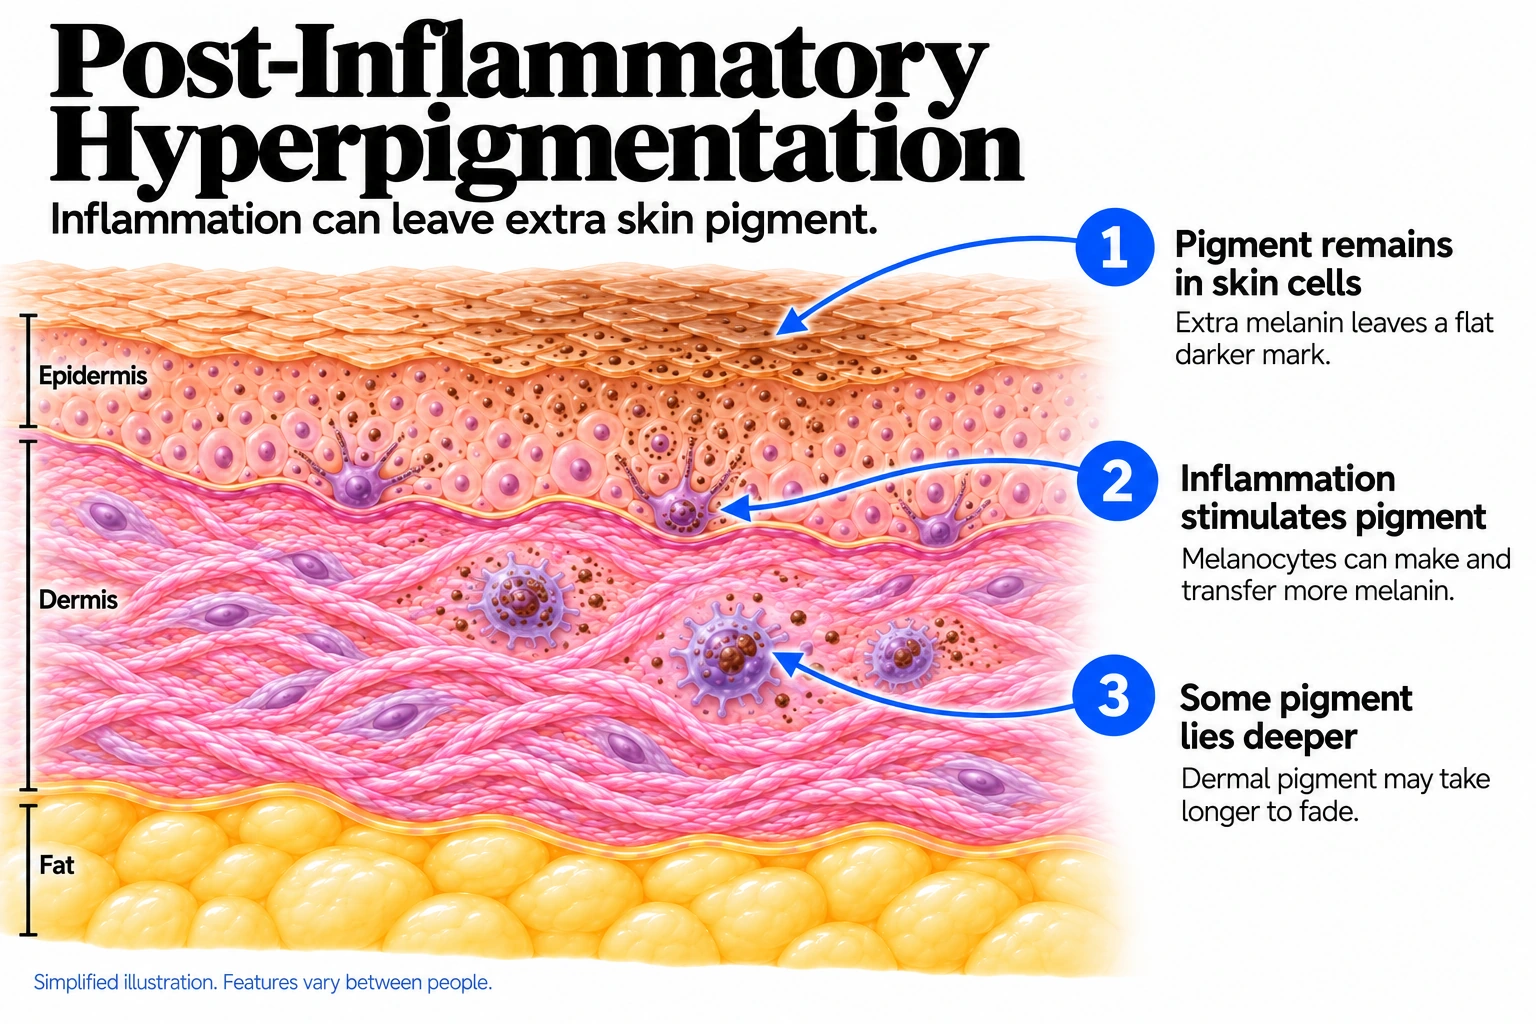
Post-Inflammatory Hyperpigmentation mechanism diagram. Pigment remains in skin cells: Extra melanin leaves a flat darker mark. Inflammation stimulates pigment: Melanocytes can make and transfer more melanin. Some pigment lies deeper: Dermal pigment may take longer to fade.
Sun Spots mechanism diagram. Sun exposure leaves lasting changes: Repeated ultraviolet exposure affects pigment cells. More pigment gathers locally: Melanin increases in a small area. A flat brown spot appears: The patch stays level with surrounding skin.
In the skin

Inflammation stimulates pigment cells to make and transfer extra melanin. Pigment left in surface cells or deeper tissue can create a flat dark mark after the original rash or injury heals.

Repeated ultraviolet exposure changes pigment activity in a small area of skin. Extra melanin produces a persistent flat brown spot, rather than a raised growth.

Where it shows up

Sites of previous inflammation
Sun-exposed face, hands and forearms

When it usually starts

010203040506070+

Post-Inflammatory Hyperpigmentation. Can follow inflammation at any age and is often more pronounced in darker skin.

Sun Spots. Usually become more noticeable in adult life after cumulative sun exposure.

Causes and triggers

Causes

Post-inflammatory hyperpigmentation happens when inflammation or injury tells pigment cells to make extra melanin, leaving a dark mark.

Sun spots form when years of ultraviolet light make pigment cells produce extra melanin in one place. They build up slowly over decades.

Family tendency

Medium and darker skin, which has more active pigment cells, is much more prone.

Fair skin that burns easily and a family history of sun spots make them more likely.

Risk factors
Medium to darker skin, Acne, Eczema
Age over 40, Fair skin, Outdoor work or hobbies, Tanning beds
Trigger
● Post-Inflammatory Hyperpigmentation
● Sun Spots
Picking at spots
Well established
Not listed
Sun exposure
Well established
Not listed
Harsh treatments or peels
Strong link
Not listed
Burns and cuts
Strong link
Not listed
Unprotected sun exposure
Not listed
Well established
Tanning beds
Not listed
Well established
Sunburns
Not listed
Strong link

Daily Care

Post-Inflammatory Hyperpigmentation
Sun Spots
Daily care

Habits that help

  • A tinted mineral sunscreen every day
    Iron oxides block visible light, which re-darkens marks.
  • Keep the barrier healthy
    Calm skin makes less pigment; irritated skin more.
  • Leave the spot alone while it heals
    Not picking beats most products here.
  • Give it months, and take photographs
    Same light every four weeks is the only reliable check.
  • Treat what caused it first
    The highest-value step, most often skipped.
  • Cysteamine
    An over-the-counter short contact treatment; cuts pigment production.

Avoid

  • Avoid: Picking and squeezing
    The largest avoidable cause. Pushes inflammation deeper.
  • Avoid: Sun without protection
    Re-activates pigment cells in a fading mark.
  • Avoid: Scrubbing and stacking strong actives
    Irritation is inflammation, which is step one.
  • Avoid: Hair removal over inflamed skin
    Adds inflammation where the marks are.
  • Avoid: Friction and pressure
    Tight straps and rubbing keep inflammation going.
  • Avoid: Unsupervised skin lightening creams
    Months of use cause lasting discoloration.
  • Avoid: Judging it week to week
    Switching products every few weeks ends up irritating.
  • Avoid: Leaving the underlying cause untreated
    Every new spot writes a mark.
  • Avoid: Stopping acne treatment when spots clear
    Marks are still fading, and the acne returns.

Habits that help

  • Daily broad-spectrum sunscreen
    SPF 30 or higher, hands and chest included, reapplied on days outside.
  • Shade, sleeves and a wide-brimmed hat
    Add shade and protective clothing to your daily sun protection.
  • Have spots checked before treating them
    Removing a spot that needed a biopsy is the one bad outcome here.
  • Ask about sun precautions for photosensitizing medicines; do not stop them yourself
    Ask your prescriber rather than stopping anything yourself.

Avoid

  • Avoid: Sun on unprotected skin
    Daily incidental exposure adds up to more than holidays do.
  • Avoid: Tanning beds
    A concentrated dose of the wavelengths that cause sun spots.
  • Avoid: Forgetting the hands, chest, ears and neck
    Where the most noticeable spots turn up later.
  • Avoid: Sunscreen applied too thinly
    Real-world protection is far below the number on the bottle.
  • Avoid: Window glass
    Protect exposed skin near sunny windows; ordinary glass lets UVA through.
  • Avoid: Believing a base tan protects you
    A tan is damage, and it protects very little.
  • Avoid: Picking or scratching a treated spot
    A reliable way to swap it for a longer-lasting dark mark.
  • Avoid: Freezing kits sold for warts
    Do not use wart-freezing kits on pigmented spots; they can scar unexamined skin.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Post-Inflammatory Hyperpigmentation
● Sun Spots
Over-the-counter
Existing Dermapedia illustration of scrubs and exfoliating pads.

Scrubs and exfoliating pads

Limited evidence

Surface pigment sits inside living skin cells rather than on top of the skin, and deep pigment sits below where any scrub can reach, so there is nothing to rub off. Scrubbing adds inflammation, and inflammation is step one of the whole process. This is one of the most common ways a mark is made worse while trying to fix it.

Five azelaic acid tubes and bottles on white, most marked 10 percent, from Peach Slices, Paula's Choice, Facetheory, The Ordinary and Naturium

Azelaic Acid

Moderate evidence

The best all-rounder here, because it calms inflammation and quietens overactive pigment cells at the same time, which means it treats the marks and the acne producing them. It is gentle enough to use for the many months this takes, and it suits deeper skin tones well. Expect slow, steady lightening rather than a quick change.

Six retinol products lined up, including SkinCeuticals Retinol 0.5, Murad, CeraVe, First Aid Beauty, RoC and Replenix

Retinol

Limited evidence

Speeds up how fast the top layer of skin turns over, which is the route surface pigment leaves by, and it treats acne while it does so. Start two nights a week and build up, because irritation is inflammation and inflammation is what made the mark. Use it at night and pair it with sunscreen in the morning.

Six niacinamide products on white, including The Ordinary 10% + Zinc 1%, Paula's Choice Booster and EltaMD UV Clear

Niacinamide

Limited evidence

Works one step later in the chain than most brightening ingredients: it reduces how much pigment gets passed from the pigment cells into the surrounding skin cells. It is mild, it rarely irritates, and it layers with almost anything. On its own it is a supporting player rather than the backbone of a plan.

Vitamin C

Limited evidence

Slows one of the enzymes that makes pigment, and adds some protection against the light that re-darkens marks, which is why it is used in the morning under sunscreen. It is a useful addition rather than the main treatment. Higher strengths sting and can irritate, and irritated skin makes more pigment, so gentler is often better here.

Four cysteamine products: a Senté tube, an Omic+ cream and box, a 5% cysteamine serum dropper and a Cyspera bottle

Cysteamine

Limited evidence

An over-the-counter option for stubborn brown marks, applied for a short contact time and then washed off, so it is a step rather than a leave-on product. It is the closest thing available without a prescription to a strong pigment treatment. The smell is unpleasant and some people find it stings, which is the usual reason people stop.

Four glycolic acid toner and liquid bottles lined up on white, one with its box

Glycolic Acid

Limited evidence

Loosens the pigmented cells at the surface so they shed sooner, which helps brown marks more than gray ones. A low-strength product two or three nights a week is plenty. Stacking it with a retinoid on the same night is the classic way people end up red and peeling, which adds inflammation and slows everything down.

Five serums lined up on white, labeled tranexamic acid or niacinamide with TXA, including SkinCeuticals Discoloration Defense

Tranexamic Acid

Limited evidence

Interrupts the messages inflammation sends to pigment cells, and it is well studied in melasma with far less evidence in dark marks specifically. It is gentle and easy to add to a routine that is already working. Treat it as an extra rather than a replacement for sunscreen and azelaic acid.

Four alpha arbutin products lined up on white: three dropper serums and a pink cream tube

Alpha Arbutin

Limited evidence

A mild pigment blocker that is popular because it rarely irritates, which matters on skin that marks easily. The trade-off is that it works slowly and modestly, and most of the research is laboratory work rather than trials in dark marks. Reasonable to include, not something to build a plan around.

Five kojic acid products on white, including a turmeric serum, Medicube capsule cream, Admire My Skin and Seoul Ceuticals

Kojic Acid

Limited evidence

Another mild pigment blocker, usually found combined with other brightening ingredients rather than on its own. Evidence in dark marks is thin, and it causes contact allergy more often than the alternatives. If a product containing it makes the skin red or itchy, stop, because that irritation will darken the mark further.

Six retinol products lined up, including SkinCeuticals Retinol 0.5, Murad, CeraVe, First Aid Beauty, RoC and Replenix

Retinol

Limited evidence

Speeds up how quickly pigmented surface cells are shed, so spots lighten gradually from the top down. It is the over-the-counter option with the best evidence in sun spots, and it improves the surrounding sun-damaged skin at the same time. Start two or three nights a week to avoid irritation, and expect three to six months before the difference is obvious.

Six niacinamide products on white, including The Ordinary 10% + Zinc 1%, Paula's Choice Booster and EltaMD UV Clear

Niacinamide

Limited evidence

Slows the handover of pigment from pigment cells to the skin cells above them, so a spot fades a little rather than disappears. Its strength is that it is well tolerated and does not sting, so it sits comfortably alongside a retinol without making the skin sore. Modest on its own.

Vitamin C

Limited evidence

Lightens surface pigment modestly and adds a little to what sunscreen is doing during the day. It is easy to keep using for years, which is its real advantage here, since sun spots are a long game. On its own it will not clear an established spot.

Four cysteamine products: a Senté tube, an Omic+ cream and box, a 5% cysteamine serum dropper and a Cyspera bottle

Cysteamine

Limited evidence

Applied to dry skin, left for about fifteen minutes and washed off rather than left on overnight. It suits people who want a lightening step without hydroquinone, or something to hold a result between courses of it. Most of the trial evidence is in melasma rather than sun spots, and the smell is the usual reason people stop.

Four glycolic acid toner and liquid bottles lined up on white, one with its box

Glycolic Acid

Limited evidence

Loosens the pigmented cells at the surface so they shed sooner, which lifts a little color out of a spot over months. It works better as the thing that helps a lightening cream get in than as a treatment on its own. Used too often it leaves skin irritated and more sun-sensitive, which on this page is exactly the wrong direction.

Four alpha arbutin products lined up on white: three dropper serums and a pink cream tube

Alpha Arbutin

Limited evidence

A gentler relative of hydroquinone that releases a small amount of it slowly in the skin. It is a reasonable long-term option on a spot you are lightening slowly, and it does not sting, which matters because irritation on a sun spot can leave a darker mark. The effect is mild and takes months.

Five kojic acid products on white, including a turmeric serum, Medicube capsule cream, Admire My Skin and Seoul Ceuticals

Kojic Acid

Limited evidence

Blocks the same pigment-making enzyme hydroquinone does, more weakly. It is nearly always sold combined with other lightening ingredients, and the studies behind it are studies of those combinations. It stings some people, and irritation on a sun spot is not a neutral event, particularly on medium and deeper skin tones.

Prescription topicals
Hydroquinone 4% — Header Image

Hydroquinone 4%

Moderate evidence

The most powerful topical option for stubborn brown marks, used as a short course of around three months rather than continuously. It blocks the enzyme that makes pigment, so it lightens the mark without touching the cause. Long unsupervised use is what leads to ochronosis, which is why this is prescribed and reviewed rather than bought and forgotten.

Tretinoin — Header Image

Tretinoin

Moderate evidence

Sheds pigmented surface cells faster and treats the acne writing new marks, which is why it does two jobs on this page. It is stronger than an over-the-counter retinol and correspondingly more irritating at first. Build up slowly, because the peeling, stinging phase is inflammation and can darken the marks before it lightens them.

An illustrative cream tube labeled Tri-Luma beside a cream swatch; packaging is conceptual.

Triple combination cream

Moderate evidence

Hydroquinone, a retinoid and a mild steroid in one cream, used in short supervised courses for marks that have not moved on simpler treatment. The three parts block pigment, speed up shedding and calm the irritation the other two cause. It is not a long-term product: months of continuous use thins the skin and can cause its own discoloration.

Finacea — Header Image

Finacea

Moderate evidence

The prescription strength of the same ingredient, worth asking about when the over-the-counter version has helped but not enough. It remains one of the few options that is both effective and gentle enough for continuous use on skin that marks easily. It is often the choice when hydroquinone is not wanted or the course has ended.

Tazarotene — Header Image

Tazarotene

Moderate evidence

The strongest of the topical retinoids, and it has been studied specifically in dark marks from acne on deeper skin tones. It works the same way as tretinoin but irritates more, so it is usually a second choice rather than a first. Ask your doctor before using any retinoid if you are pregnant or trying to be.

Hydroquinone 4% — Header Image

Hydroquinone 4%

Moderate evidence

The strongest cream for lightening a sun spot, applied thinly to the spot itself rather than the skin around it. It is used in a defined course of about three to four months with a break afterwards, not indefinitely, and it works best combined with a retinoid. It is slower than a single session of freezing or laser, and it is the option to prefer when treatment risk on deeper skin tones is the concern.

Tretinoin — Header Image

Tretinoin

Moderate evidence

The prescription retinoid, and the one with real trial evidence in sun spots specifically. It lightens spots over about six to ten months and improves the sun-damaged skin around them at the same time. Expect dryness and flaking early on, and use it at night with daily sunscreen, since it leaves skin more sun-sensitive. Ask your doctor about it if you are pregnant or trying to become pregnant.

Tazarotene — Header Image

Tazarotene

Moderate evidence

A stronger retinoid with good trial results in sun spots, used when tretinoin has not done enough. It works the same way, a little faster, and irritates more, so it is often started a few nights a week. Ask your doctor about it if you are pregnant or trying to become pregnant.

Procedures
Editorial illustration for Chemical Peel, based on the entry’s treatment or equipment reference.

Chemical Peel

Moderate evidence

A series of light peels speeds up the shedding of surface pigment, so it helps brown marks far more than gray ones. Done gently and spaced out, it adds to a good home routine rather than replacing it. Done too strongly, especially on deeper skin tones, the peel itself inflames the skin and creates a fresh round of marks.

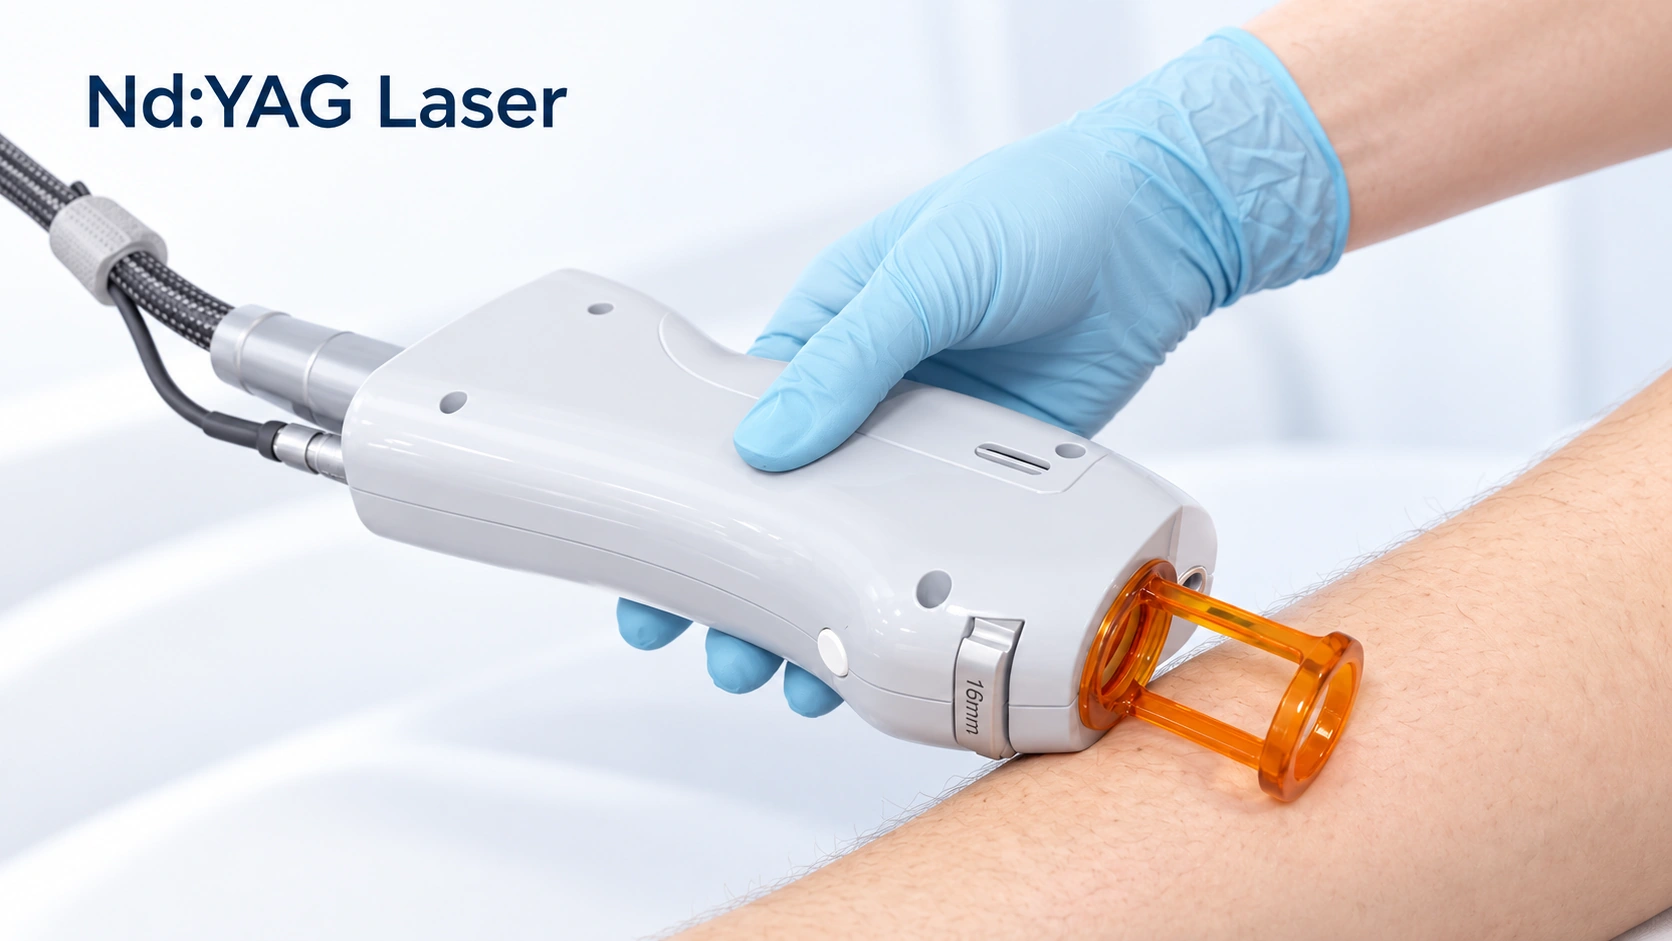
Editorial illustration for Nd:YAG Laser, based on the entry’s treatment or equipment reference.

Nd:YAG Laser

Limited evidence

Low-energy 1064 nm treatment is the laser most often chosen for pigment in deeper skin tones, because that wavelength passes through the surface and reaches the deeper, gray-toned pigment. Several sessions are needed and results are modest. Settings matter more than the machine, and this should be done by someone who treats your skin tone regularly.

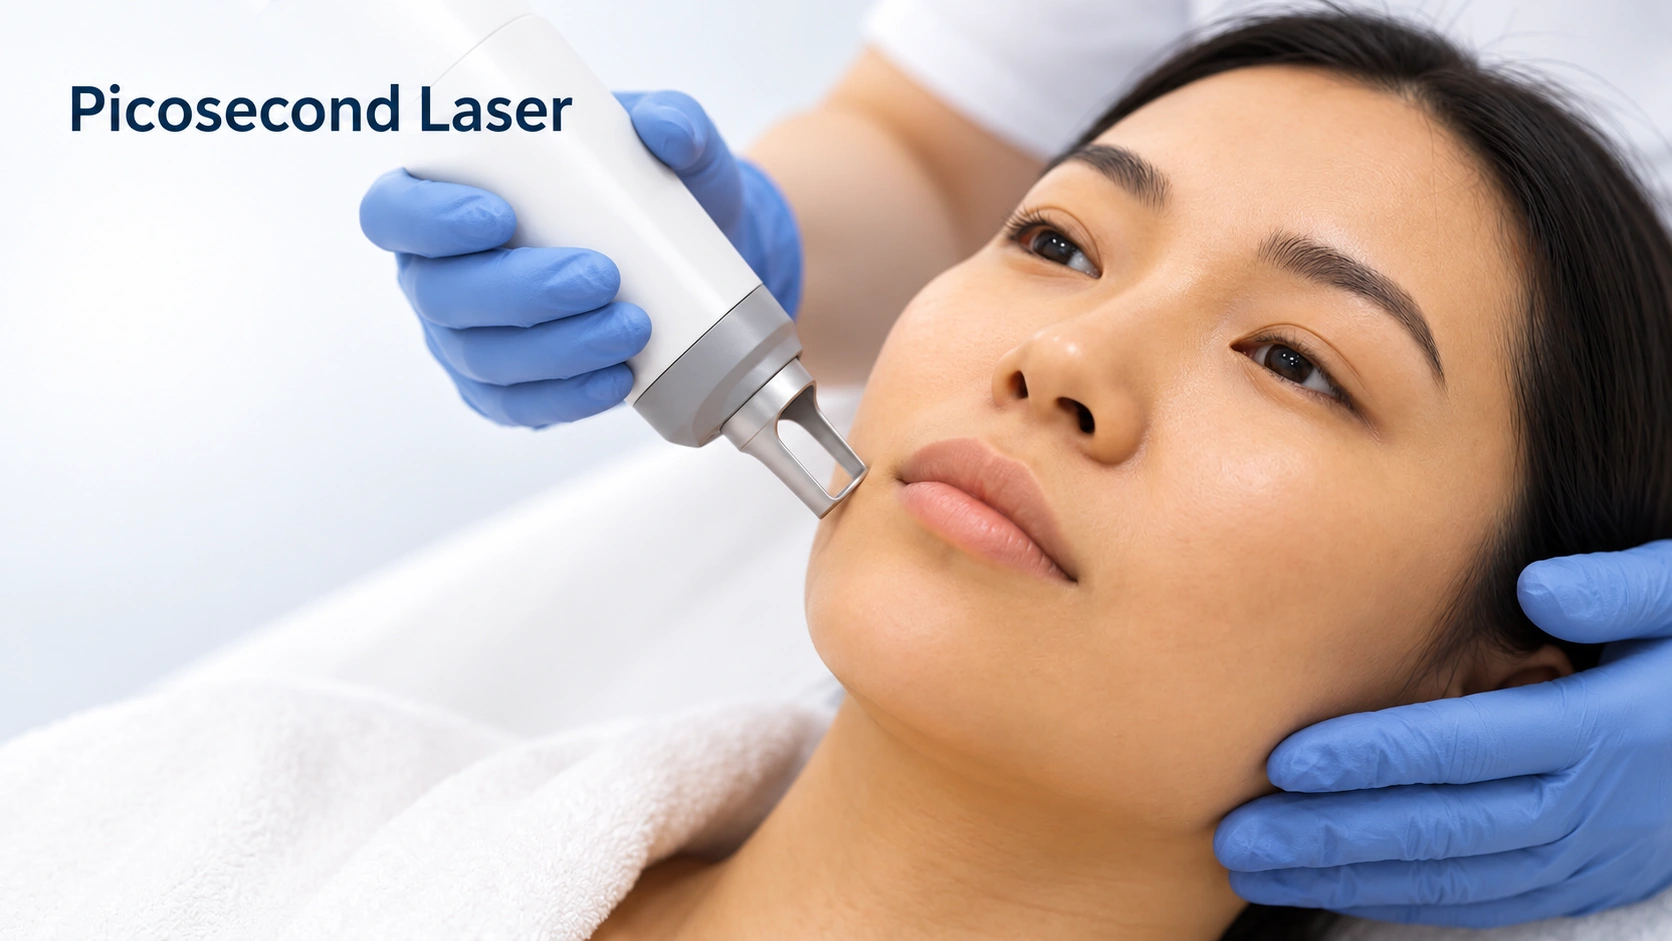
Editorial illustration for Picosecond Laser, based on the entry’s treatment or equipment reference.

Picosecond Laser

Limited evidence

Breaks pigment into fragments small enough for the body to carry away, using very short pulses that put less heat into the skin than older lasers. It is one of the safer device options for stubborn deep marks, but the evidence in dark marks after inflammation is still thin. Test patch first, and expect a course rather than one session.

Editorial illustration for Microneedling, based on the entry’s treatment or equipment reference.

Microneedling

Limited evidence

Fine needles make controlled channels that help topical treatments penetrate and encourage the skin to remodel. It is mainly a scarring treatment, and its effect on pigment alone is small. It is a reasonable choice when true scars and dark marks sit together, but it can inflame reactive skin, so conservative depths are used on deeper skin tones.

IPL

Limited evidence

IPL. Broad-spectrum light aimed at surface pigment, and it is a poor fit for these marks. It is absorbed strongly by pigment throughout the skin, so on medium and deep skin tones it can burn and leave a darker or patchier result than it started with. It is used far more for sun spots on fair skin than for anything on this page.

Editorial illustration for Microdermabrasion, based on the entry’s treatment or equipment reference.

Microdermabrasion

Limited evidence

Sands off the very top of the skin, which is above where the pigment actually sits, so it does little for brown marks and nothing for gray ones. Repeated sessions add friction and inflammation to skin that marks easily. Money spent here is better spent on daily sunscreen and a treatment that reaches the pigment cells.

Editorial illustration for Chemical Peel, based on the entry’s treatment or equipment reference.

Chemical Peel

Limited evidence

Lightens spots across a whole area rather than one at a time, which suits the backs of the hands, the forearms and the chest where spots are scattered widely. Usually a course rather than a single treatment, and the result is a general evening out rather than each spot disappearing. Depth matters: a peel strong enough to leave the skin raw can leave a darker mark instead.

Editorial illustration for Picosecond Laser, based on the entry’s treatment or equipment reference.

Picosecond Laser

Moderate evidence

Delivers its energy in much shorter pulses, which breaks up pigment with less heat spilling into the skin around it. That lower heat is the reason it is often chosen for medium and deeper skin tones, where a darker mark afterwards is the main worry. It costs more than the older lasers and the results in sun spots are broadly similar.

IPL

Moderate evidence

IPL. The best option when there are many spots across a whole area such as the face, chest or the backs of the hands. Usually one to three sessions, with the spots darkening and flaking off over one to two weeks after each. It is aimed at contrast between spot and skin, so it works best on lighter tones and is used cautiously or not at all on deep skin.

Editorial illustration for Microdermabrasion, based on the entry’s treatment or equipment reference.

Microdermabrasion

Limited evidence

Polishes off the very top layer of skin, which makes it briefly smoother and brighter. The pigment in a sun spot is held in ridges below that layer, so it is not reached. It is often sold as a treatment for spots and it is not one, and repeated sessions can irritate skin enough to leave marks of their own.

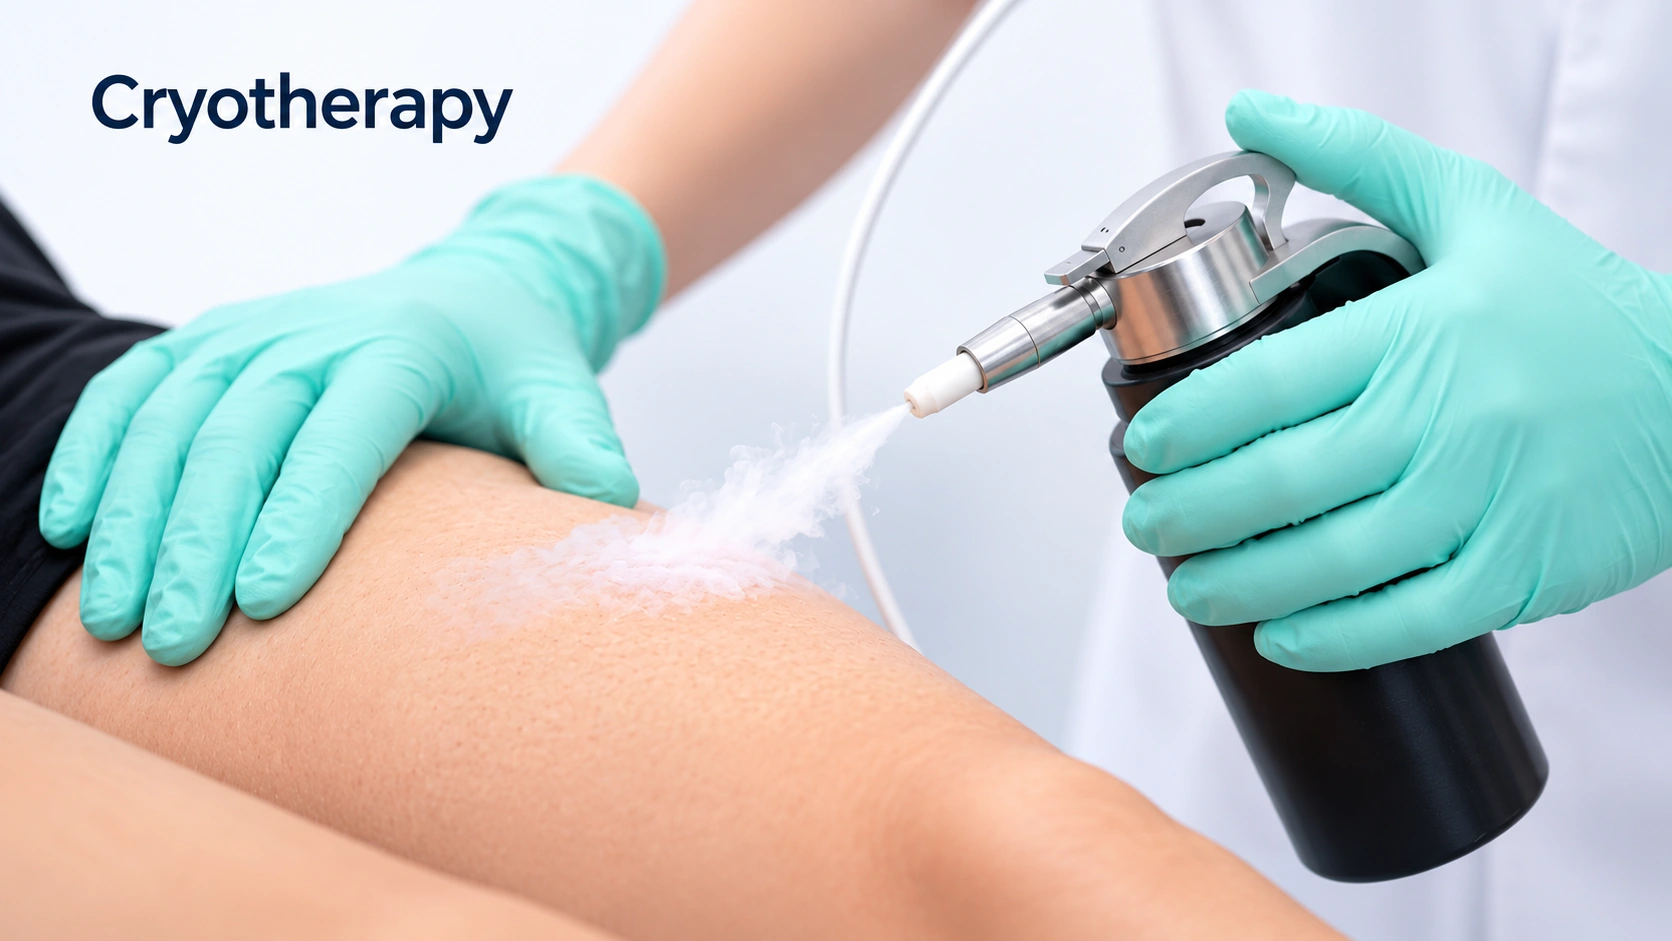
Editorial illustration for Cryotherapy, based on the entry’s treatment or equipment reference.

Cryotherapy

Moderate evidence

A few seconds of liquid nitrogen on each spot, done in the room, no anesthetic needed. The spot darkens, crusts and lifts off over one to two weeks. It suits a small number of spots rather than a whole hand, and its known cost is a permanent pale mark where too many pigment cells were destroyed, which is a bigger risk on medium and deeper skin tones.

Editorial illustration for Q-Switched Laser Tattoo Removal, based on the entry’s treatment or equipment reference.

Q-Switched Laser Tattoo Removal

Moderate evidence

The same pigment-shattering laser used for tattoo ink is used at low energy on individual sun spots, and it clears them reliably in one or two sessions. It is more precise than intense pulsed light and better for a few stubborn spots rather than a whole area. Settings have to be matched to the skin tone, since too much energy leaves a pale or a dark mark behind.

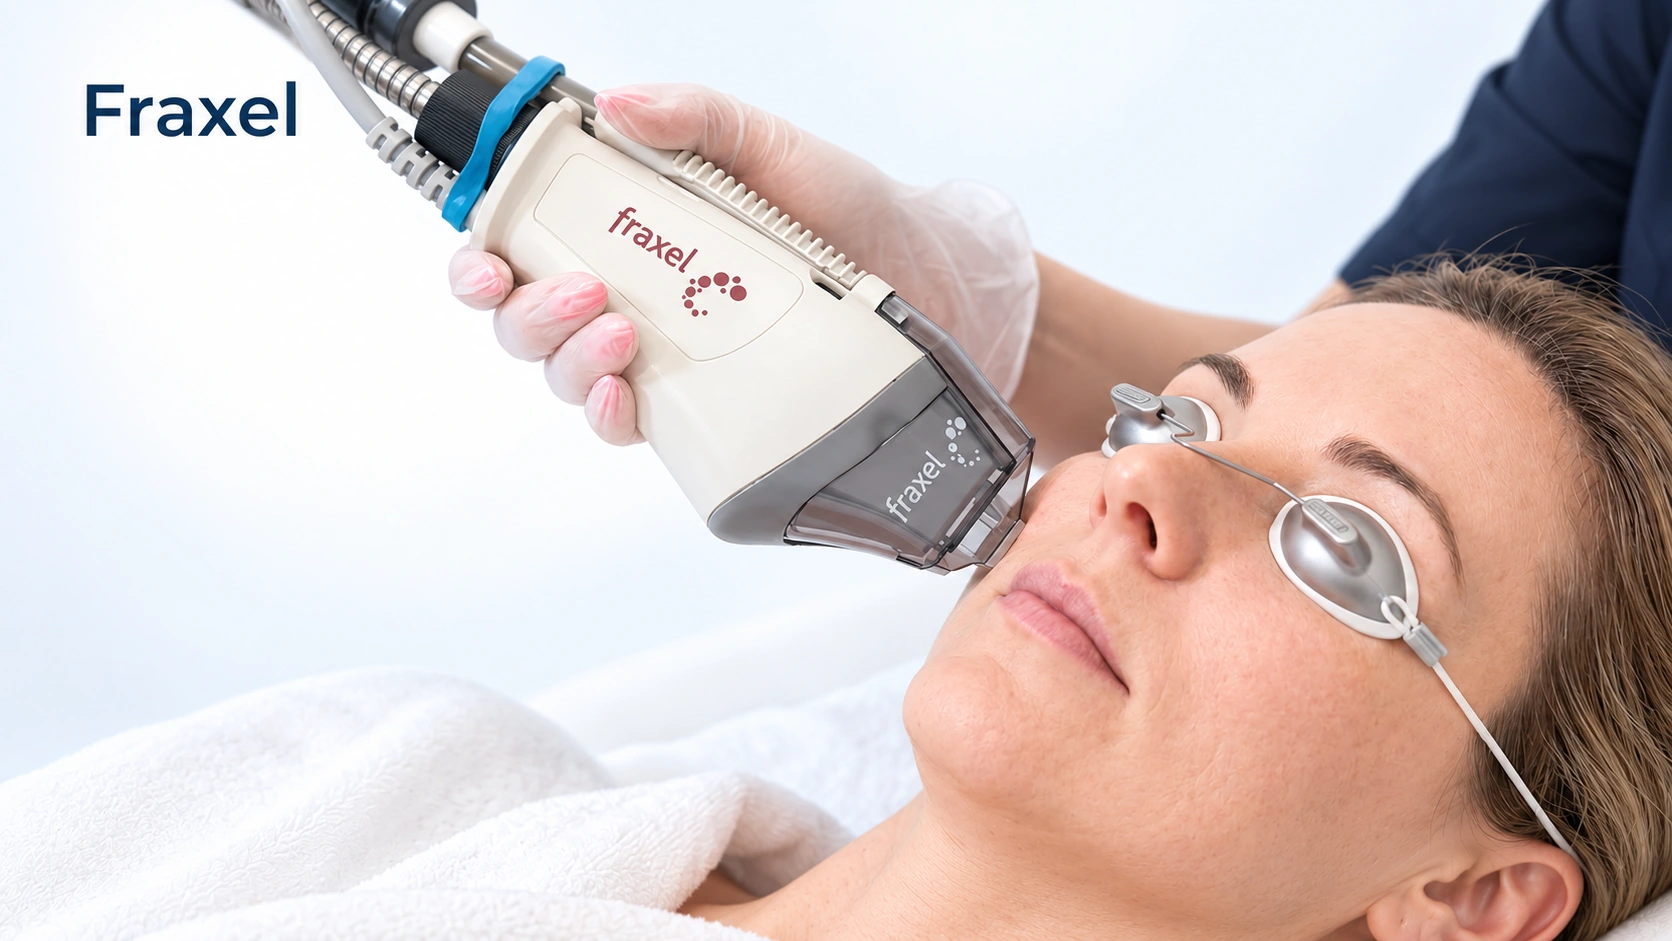
Editorial illustration for Fraxel, based on the entry’s treatment or equipment reference.

Fraxel

Limited evidence

Fraxel. Treats the sun-damaged skin as a whole rather than targeting individual spots, so it improves texture and fine lines alongside the pigment. That makes it a reasonable choice when the spots are only part of what is bothering you. For clearing spots alone it is slower, dearer and less precise than freezing or a pigment laser.

Outlook

Long term

Fading is not a straight line. Marks lighten over winter and stall over summer if sun protection slips, and a photograph in the same light shows progress a mirror does not. What decides the course is whether new inflammation keeps happening — while acne or a rash is active, marks accumulate faster than they clear.

Sun spots usually persist and can increase with further ultraviolet exposure. They do not themselves become skin cancer, but sun-damaged skin can develop other lesions. A changing, rough or otherwise unusual spot needs assessment before cosmetic treatment.

Complications

Possible complications

The underlying trigger may be acne, eczema, infection or injury. Dark marks can persist after that problem settles, especially on deeper skin tones; treating active inflammation helps prevent additional marks.

Solar lentigines are benign, but they mark ultraviolet exposure and may coexist with other sun-damaged lesions. A changing or irregular spot needs assessment rather than an assumed age-spot diagnosis.

When to get help

When to get help

Seek assessment of uncertain or changing pigmentation. Treat active inflammation first and review stronger fading treatments with a clinician, especially during pregnancy.

Have a new, changing, unevenly colored or bleeding spot checked before using a fading treatment.

Common questions

Post-Inflammatory Hyperpigmentation:How long will these take to fade?

Brown, surface-level marks lighten noticeably over three to six months and are often gone within a year. Gray or slate marks sit deeper and take a year or longer. Sun protection stops those timelines stretching.

Post-Inflammatory Hyperpigmentation:Is this a scar?

Only if you can feel it. Scars are raised or indented and never resolve. Flat brown or gray marks are pigment, and they fade. Calling both scars sends people after the wrong treatment.

Post-Inflammatory Hyperpigmentation:What is the single most useful thing I can do?

Stop the next mark forming. Treat the acne, eczema or ingrown hairs properly, do not pick, and wear tinted sunscreen daily. Those three beat any brightening product.

Post-Inflammatory Hyperpigmentation:Why do my marks look red instead of brown?

That is post-inflammatory erythema — a blood vessel change, not pigment. Commoner on lighter skin tones, usually fades on its own, and pigment-lightening products do not help. Different problem, different plan.

Post-Inflammatory Hyperpigmentation:Will a laser or a peel clear them faster?

Sometimes, and sometimes they make it worse. Gentle, well-chosen treatments speed up surface pigment. Aggressive ones inflame the skin and cause fresh marks, a real risk on deeper skin tones. Keep any device treatment conservative, with someone who treats your skin tone regularly.

Post-Inflammatory Hyperpigmentation:Should I stop my acne treatment now that the spots are gone and only marks are left?

No. Stopping usually brings the acne back within months, and every new spot adds a mark. Most acne treatments also fade the marks, so continuing does both jobs.

Sun Spots:Are sun spots dangerous?

The spots are harmless and do not turn into cancer. What they indicate matters - that much sun exposure makes other changes more likely, so watch and protect those areas.

Sun Spots:How do I tell a sun spot from something serious?

The reassuring pattern is flat, one even color, a clear edge, stable over time, similar to its neighbors. The pattern that needs a check is changing, growing, more than one color, a ragged or blurred edge, itching, bleeding, or a spot unlike the rest. Being unsure is a reason to have it looked at, not to worry.

Sun Spots:What is the fastest way to get rid of them?

In-office treatment. Freezing works for a few spots; laser or intense pulsed light for many, usually over one to three sessions. Expect them to darken and flake off over one to two weeks. Creams work far more slowly.

Sun Spots:Will they come back after treatment?

The individual spot usually does not return. New ones keep appearing on sun-exposed skin unless the sun protection changes, which is why people who treat spots and change nothing else are back within a few years.

Sun Spots:Do sunscreen and creams help spots I already have?

Sunscreen does not remove them, but it stops them darkening and slows new ones. Retinoids, vitamin C, niacinamide and short courses of hydroquinone lighten existing spots over three to six months, more gently than a procedure.

Sun Spots:I have deeper skin - is freezing a good option for me?

The one to be most cautious about. Freezing can destroy the pigment cells and leave a permanent pale mark, more noticeable on deeper skin tones and harder to correct than the original spot. Topical treatment first, conservative settings, a test spot, and a provider who treats deeper skin tones regularly is the safer path.

Sources

Sources and further reading

  1. DermNet

  2. DermNet
Dermapedia on YouTube