Acne
Reduces inflamed breakouts.
Minocycline: An oral antibiotic for moderate to severe inflamed acne. It works about as well as doxycycline, but carries a few rarer risks, so it is usually the second choice. Winlevi: The first cream that blocks hormones in the skin itself. It is the only topical treatment that works on the hormonal driver of acne, and it can be used by men and women.


Choose as a second-choice acne antibiotic when doxycycline doesn't suit — it works about as well, with a few rarer risks.
Choose for acne with a hormonal driver when you want a cream rather than a pill — the only topical that targets it.
Can you take them together?
They work on different causes of acne and can be used together. Winlevi can continue after minocycline stops.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.


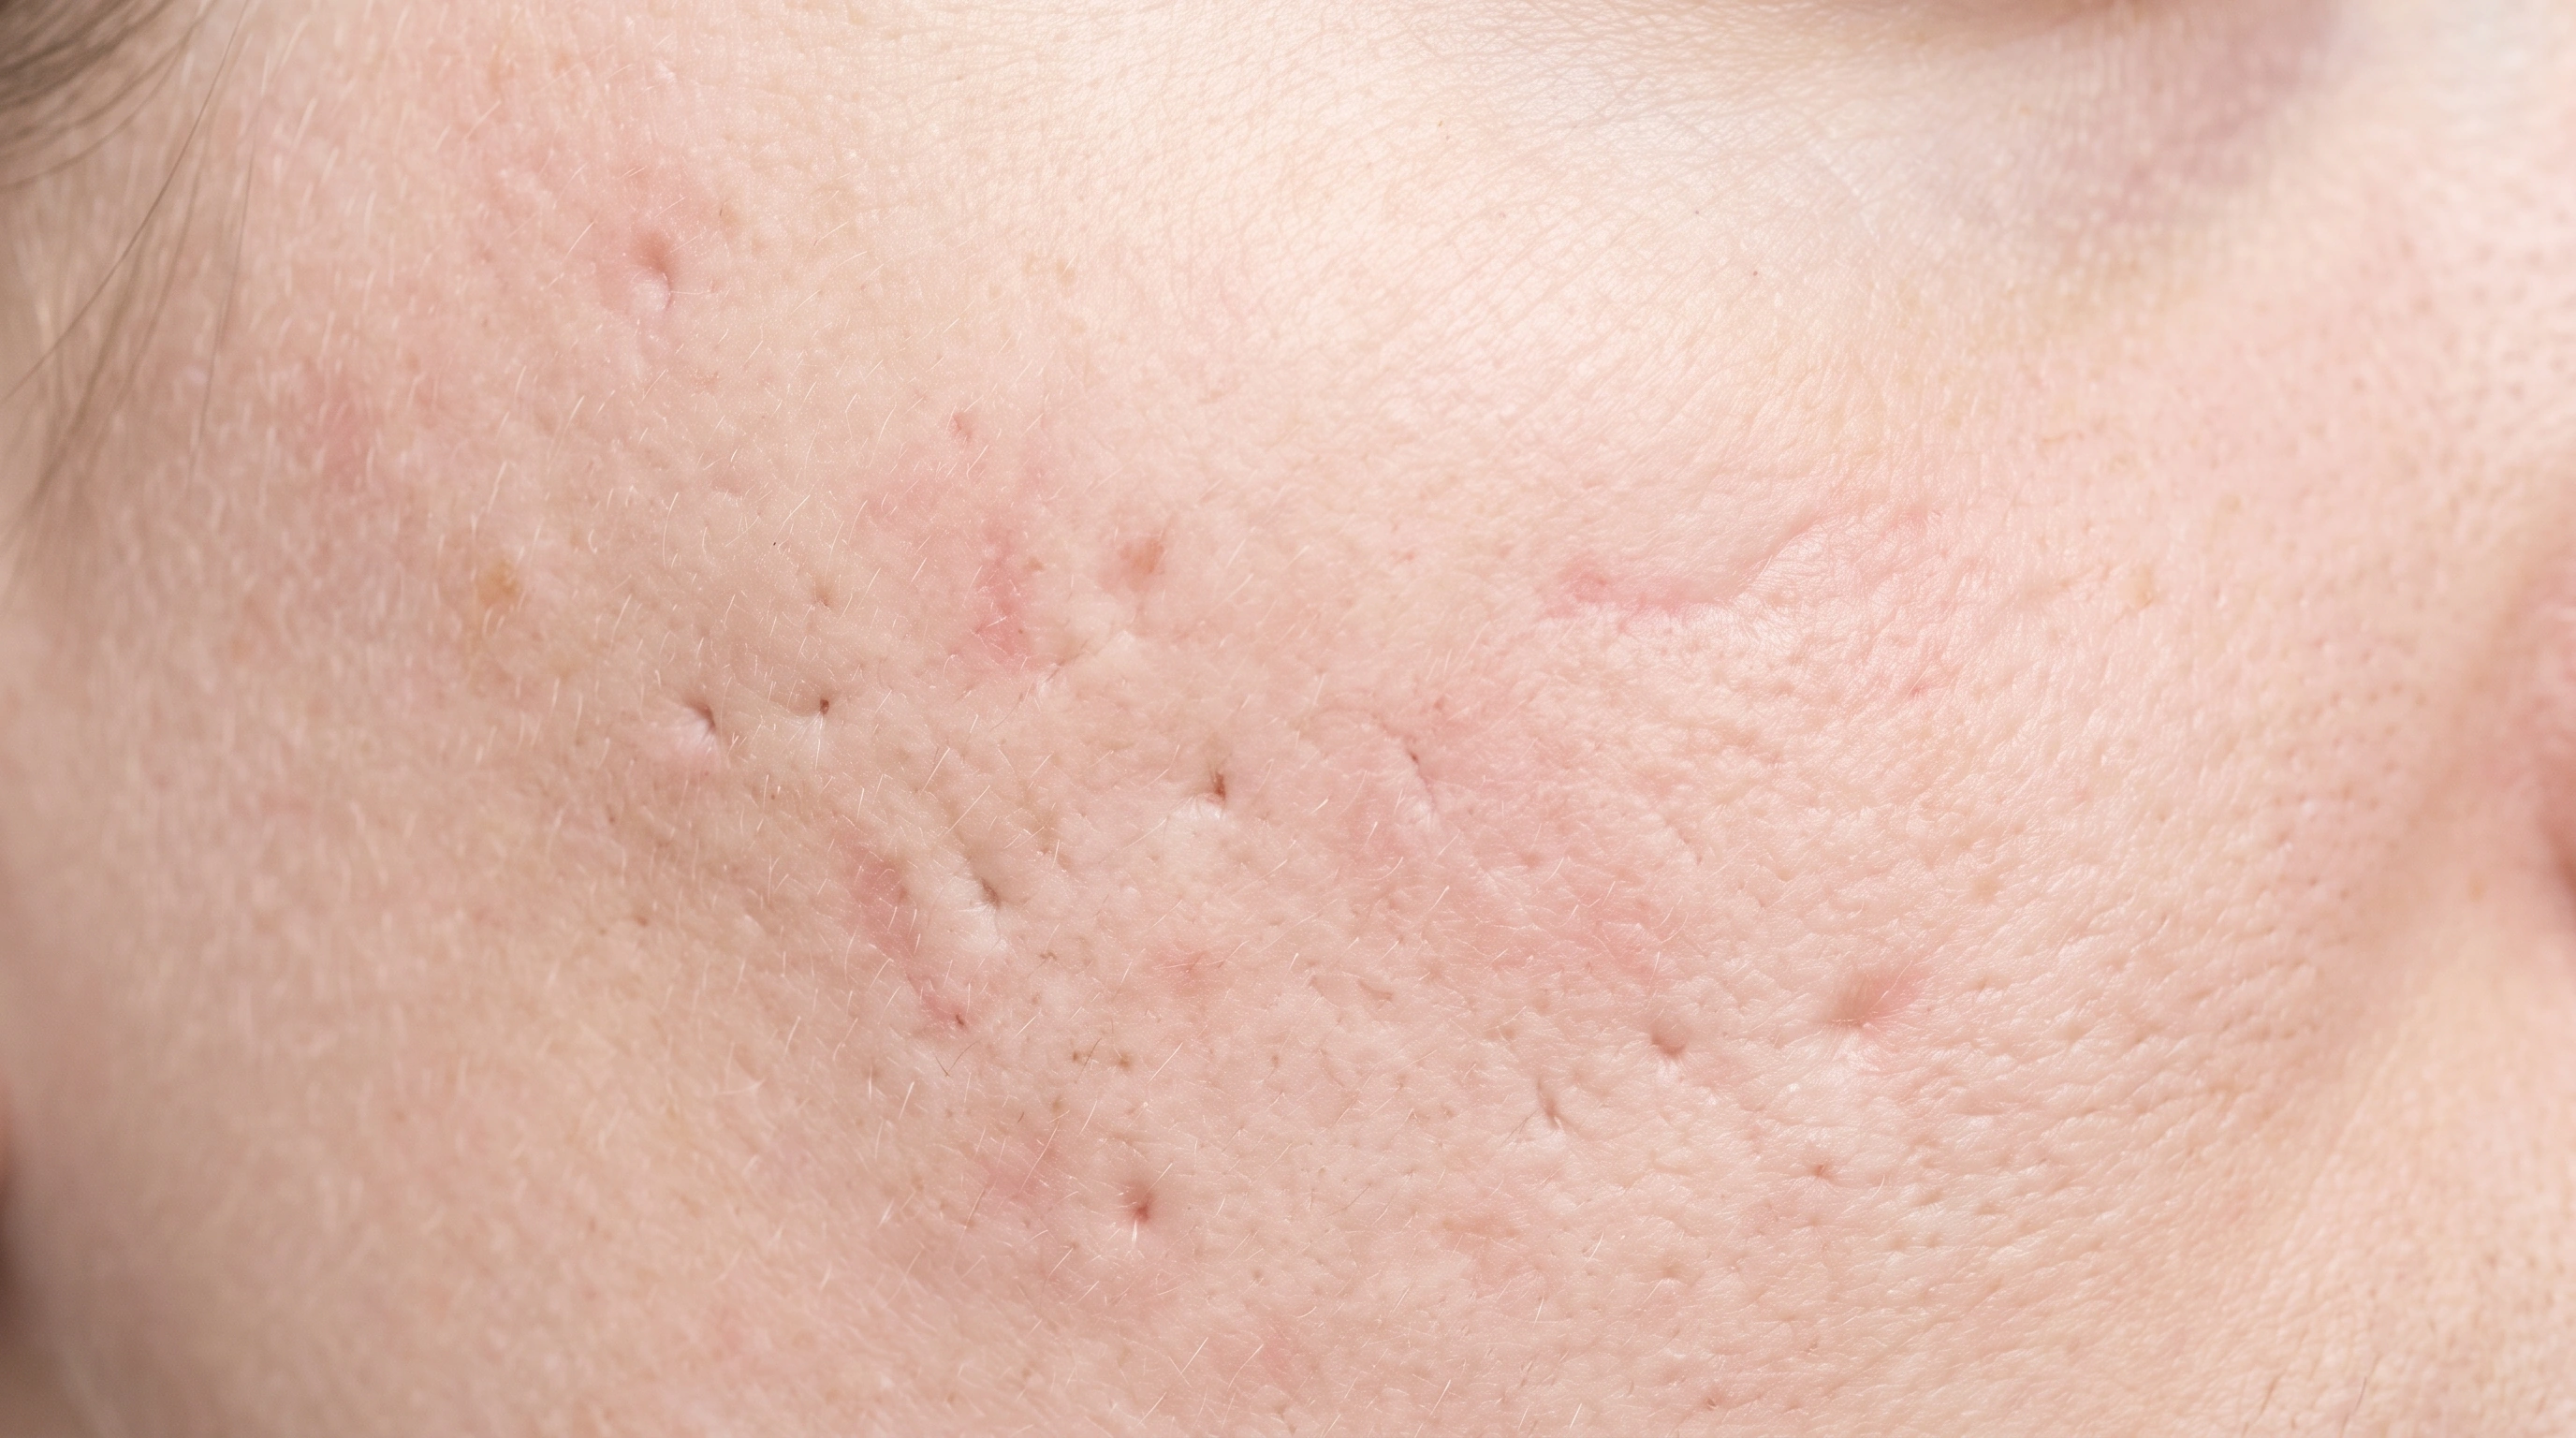

Slows acne bacteria: Blocks the 30S ribosome that bacteria use to make proteins. Calms inflammatory responses: Can also reduce some inflammation-related activity. Reduces inflamed spots: Red bumps and pimples can gradually improve.
Bacterial protein-synthesis inhibition is established. The complete acne mechanism and the contribution of individual antibacterial and anti-inflammatory effects are not fully defined. This does not imply direct exfoliation, oil-gland shrinkage, or treatment of resistant bacteria.

Blocks androgen receptors: Limits hormone signaling inside skin cells. May reduce oil and inflammatory signals: These effects have been seen in laboratory sebocytes. Helps reduce acne lesions: Both clogged and inflamed spots can improve.
Androgen receptor inhibition is established. Reduced lipid and cytokine production were demonstrated in human sebocytes in vitro; their clinical contribution is not fully established. The label states the complete acne mechanism is unknown.
Dose is set by what you tolerate more than body weight. Dizziness is the usual limit, not the stomach. Liver problems can lower it.
Starting dose: Commonly 50 mg to 100 mg once or twice a day. Some doctors start low for a week to see how you feel.
Going up: After a week or two if it is tolerated and acne has not begun to respond.
Usual dose: Around 100 mg once or twice daily. The extended-release form is about 1 mg per kilogram of body weight, once daily.
Total course: About three to four months. Guidelines advise reassessing at three months and stopping once the topical can hold the result. Long uninterrupted use is what raises the pigment risk.
When to Apply: Twice a day, morning and night, on clean dry skin. A fingertip of cream over the whole area. Sunscreen or moisturizer goes on top once it dries.
How to Start: Twice daily from day one — and twice daily is the part people quietly drop.
If It Irritates: Mild dryness or redness early on is usually the base, not the drug, and moisturizer underneath settles it.
If It’s Not Working: One strength, so nothing to increase. Give it twelve weeks, then ask about adding another treatment.
With a full glass of water. Food is fine and usually reduces nausea. Stay upright for at least 30 minutes afterwards, and not right before bed — a tablet that lodges in the food pipe can burn the lining.
If it makes you unsteady, taking it at night helps, since you sleep through the peak. Ask your doctor before changing the timing.
Space antacids, iron and calcium supplements by about two hours. They bind the drug and less gets in.
Take it when you remember, unless the next dose is close. Never take two at once — a doubled dose mostly produces nausea and dizziness.
No routine blood tests for a standard three to four month course in a healthy person. Monitoring is clinical: a review at about three months, and a look at skin, gums and old scars for a gray or blue tinge.
Blood tests are ordered if something appears. Joint pain, fever or unusual tiredness prompts testing for a lupus-like reaction; a rash with fever and swollen glands, for a hypersensitivity reaction that can involve the liver. Both are rare, likelier with long use, and usually settle once the drug stops.
This is not a drug to stay on for years. Two things build up: antibiotic resistance, and pigment that is dose and duration related and can be slow to fade or permanent. Guidelines say oral antibiotic courses for acne should be as short as possible, with a topical retinoid alongside to take over.
No routine blood tests in a healthy person. Monitoring is a review at about twelve weeks.
The exception is kidney or adrenal problems, or drugs that raise potassium — then a doctor may check it. People can stay on it long term; nothing accumulates, because it breaks down quickly after absorption. The recurring issue is cost and coverage, not safety.
Approximate windows, not promises.
First doseTaking it: One tablet with plenty of water, sitting upright. Nausea or dizziness show up in the first few days if they happen.
Weeks 1 to 2Settling in: Little change in the skin yet.
Weeks 2 to 6Working: Red, sore papules and pustules become fewer and less painful. This is what minocycline is aimed at.
Weeks 8 to 12Judge it here: Most of what an antibiotic will give has arrived. Dark marks fade as fewer new spots form, over months, faster with sun protection.
Weeks 1 to 4Little visible change, maybe mild dryness.
Weeks 4 to 8Oiliness often drops before spot counts.
After 12 weeksJudge it here. Trials measured their main result here, and many kept improving past it.
Sorted by what to do about them.
Generic immediate-release minocycline is inexpensive and widely stocked, usually in the same price range as generic doxycycline, and both are covered by most plans.
The extended-release brands cost far more, and prior authorization is common. You would be paying for comfort rather than clearing: the slower release was meant to reduce dizziness, not clear acne better.
If cost is the problem, say so before you leave. Doxycycline, minocycline and plain tetracycline are all generic, so the choice can follow what your plan covers.
Brand only, no generic. Among the most expensive topical acne treatments, with inconsistent coverage. Prior authorization is common, and plans usually want a retinoid and benzoyl peroxide first. Savings cards exist and change often.
Usually three to four months. If a year has passed and you are still refilling, the plan needs revisiting.
No. Comparisons have not shown it clears acne better. An alternative, not an upgrade, with a few risks doxycycline does not have.
Minocycline can leave a slate or blue-gray color in skin, old scars, gums, nails and sometimes the whites of the eyes. It is uncommon, linked to long use and high total doses, and can be slow to fade or permanent.
More of the drug reaches the inner ear and brain than with doxycycline. It appears in the first few days, is dose-related, and settles after stopping.
Occasional drinking is fine. Heavy drinking clears the drug faster, which can make it work less well.
Yes. The antibiotic lowers inflammation while you take it but does nothing about the clog that starts a spot. The retinoid, usually with benzoyl peroxide, holds the result afterwards and limits resistance.
Yes. It is inactivated quickly after absorption, so it skips the breast tenderness and libido changes of oral anti-androgens.
Usually not. It is milder, for people who cannot take spironolactone or want to avoid a tablet and blood tests.
Not for routine use. Potassium may be checked with kidney disease or drugs that raise it.
Yes, a common combination. Clascoterone in the morning, retinoid at night.