Male Pattern Hair Loss vs Alopecia Areata

Male pattern hair loss is a slow thinning at the temples and crown, caused by normal hormones acting on follicles that inherited a sensitivity to them. It is common and it is not dangerous. Treatment holds on to the hair you still have far better than it brings back hair that is already gone. Alopecia areata is an autoimmune condition that makes hair fall out in smooth, round patches. The immune system switches the follicle off rather than destroying it, so hair can come back - but it is unpredictable, and no one can tell in advance who will regrow and who will not.

Reviewed by Dr. Schwarz, Board-Certified Dermatologist · Research updated 2026-10-23
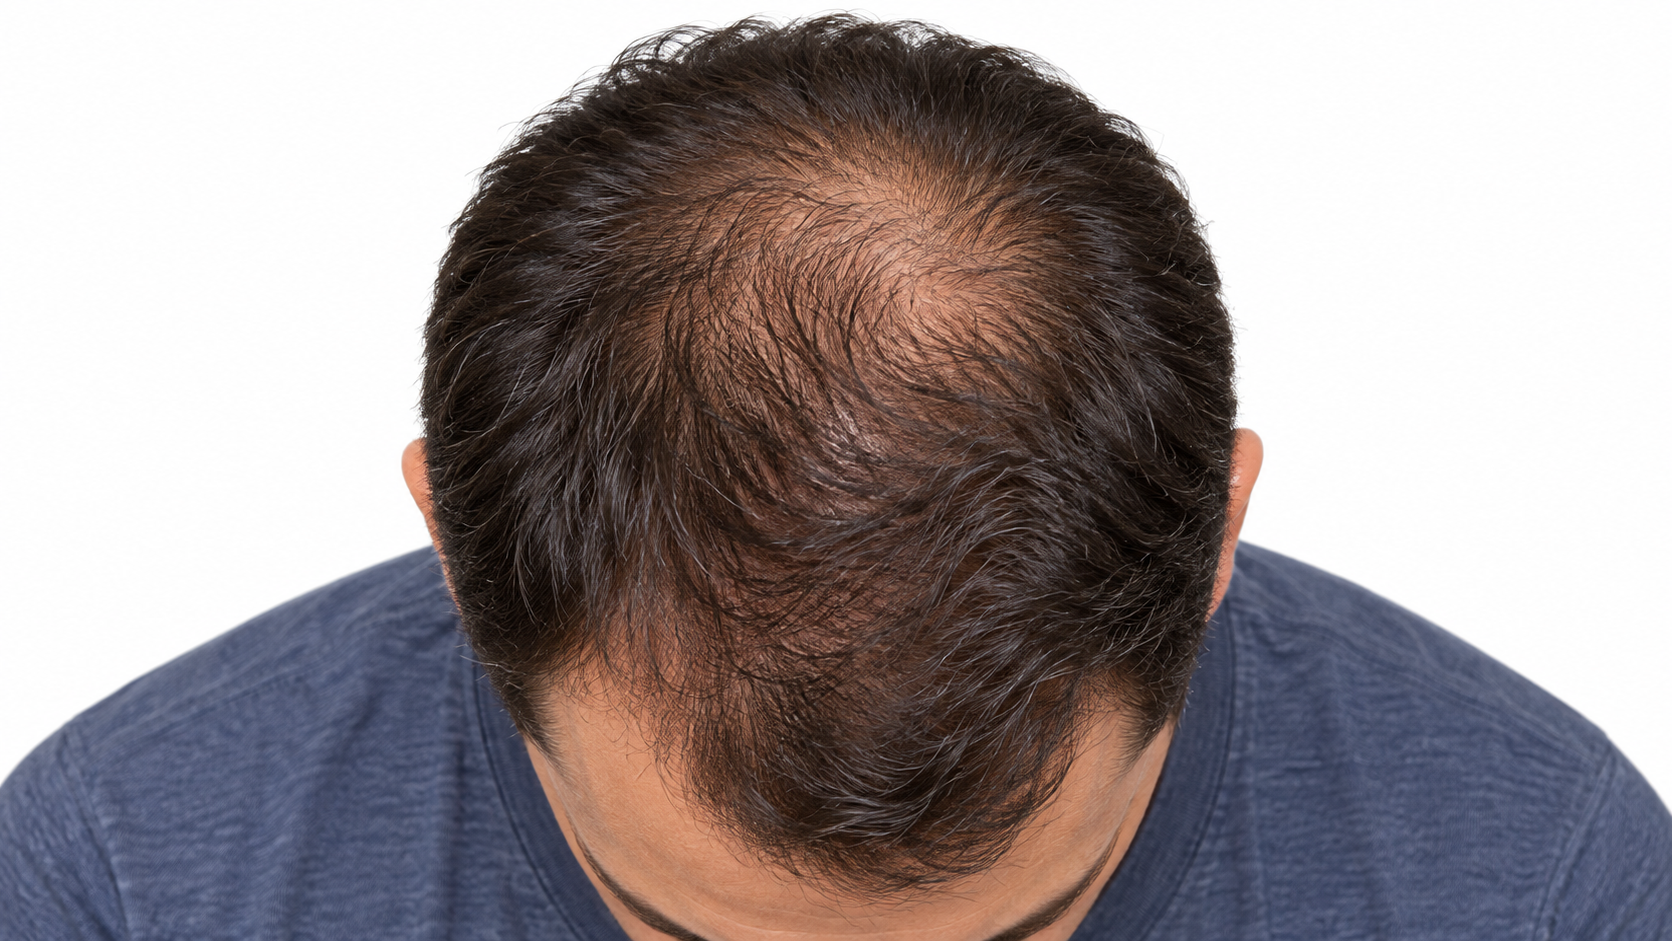
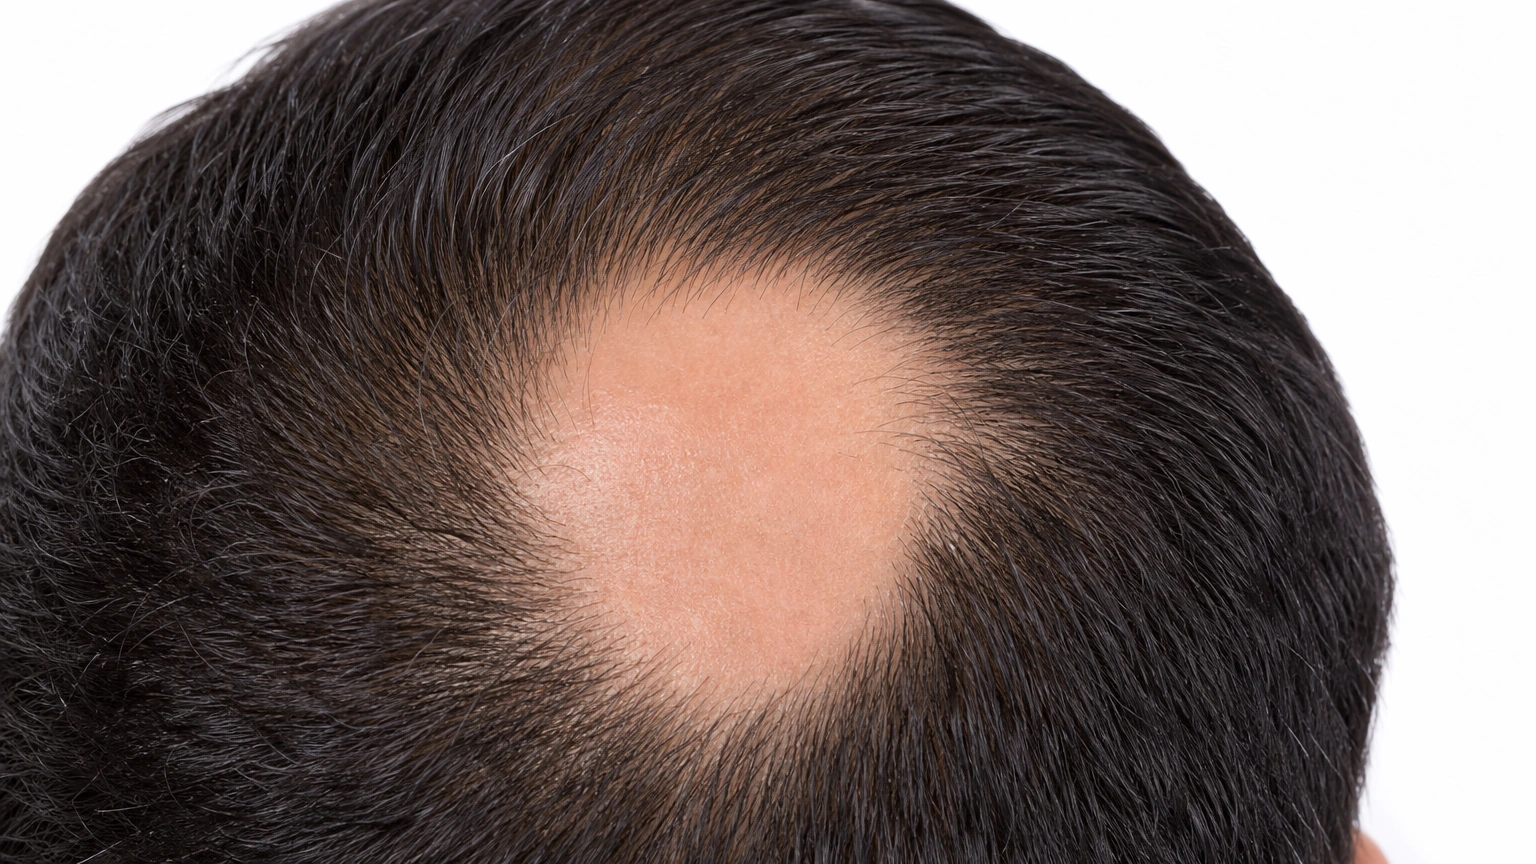
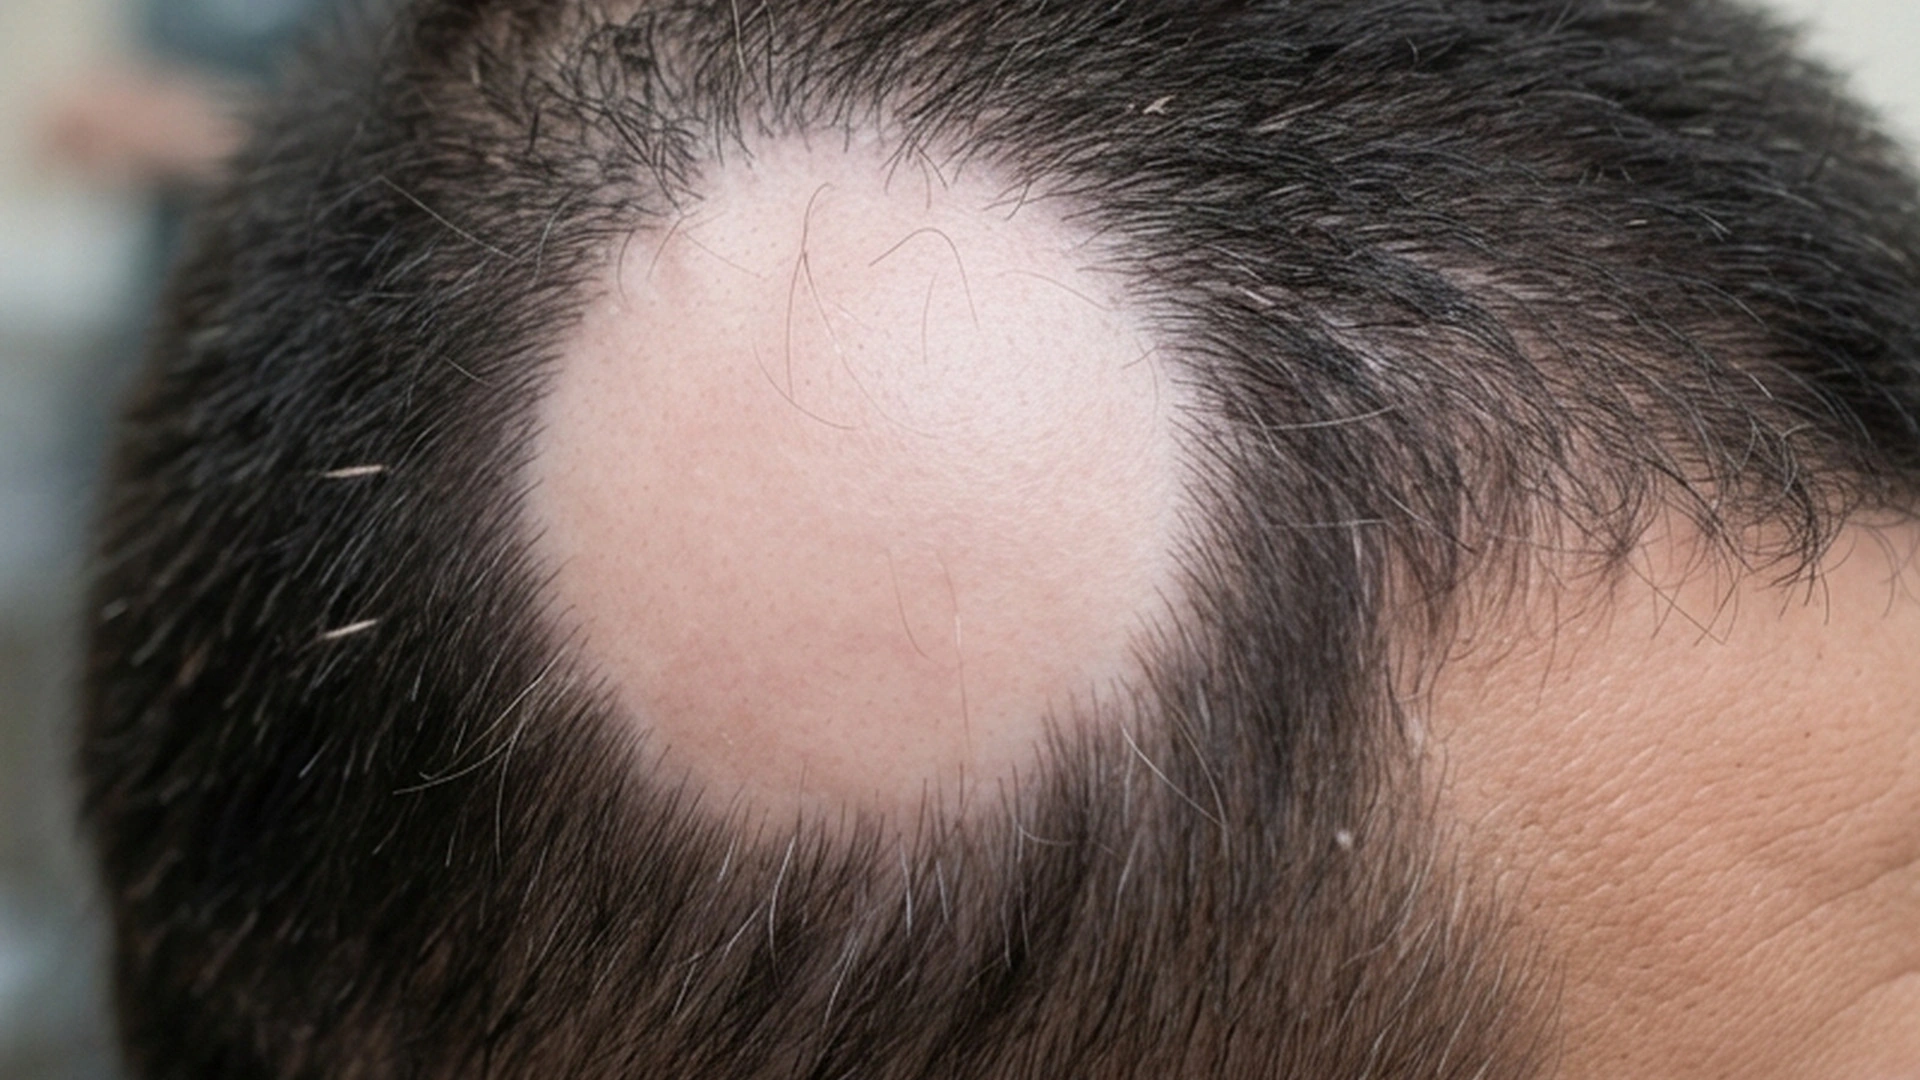
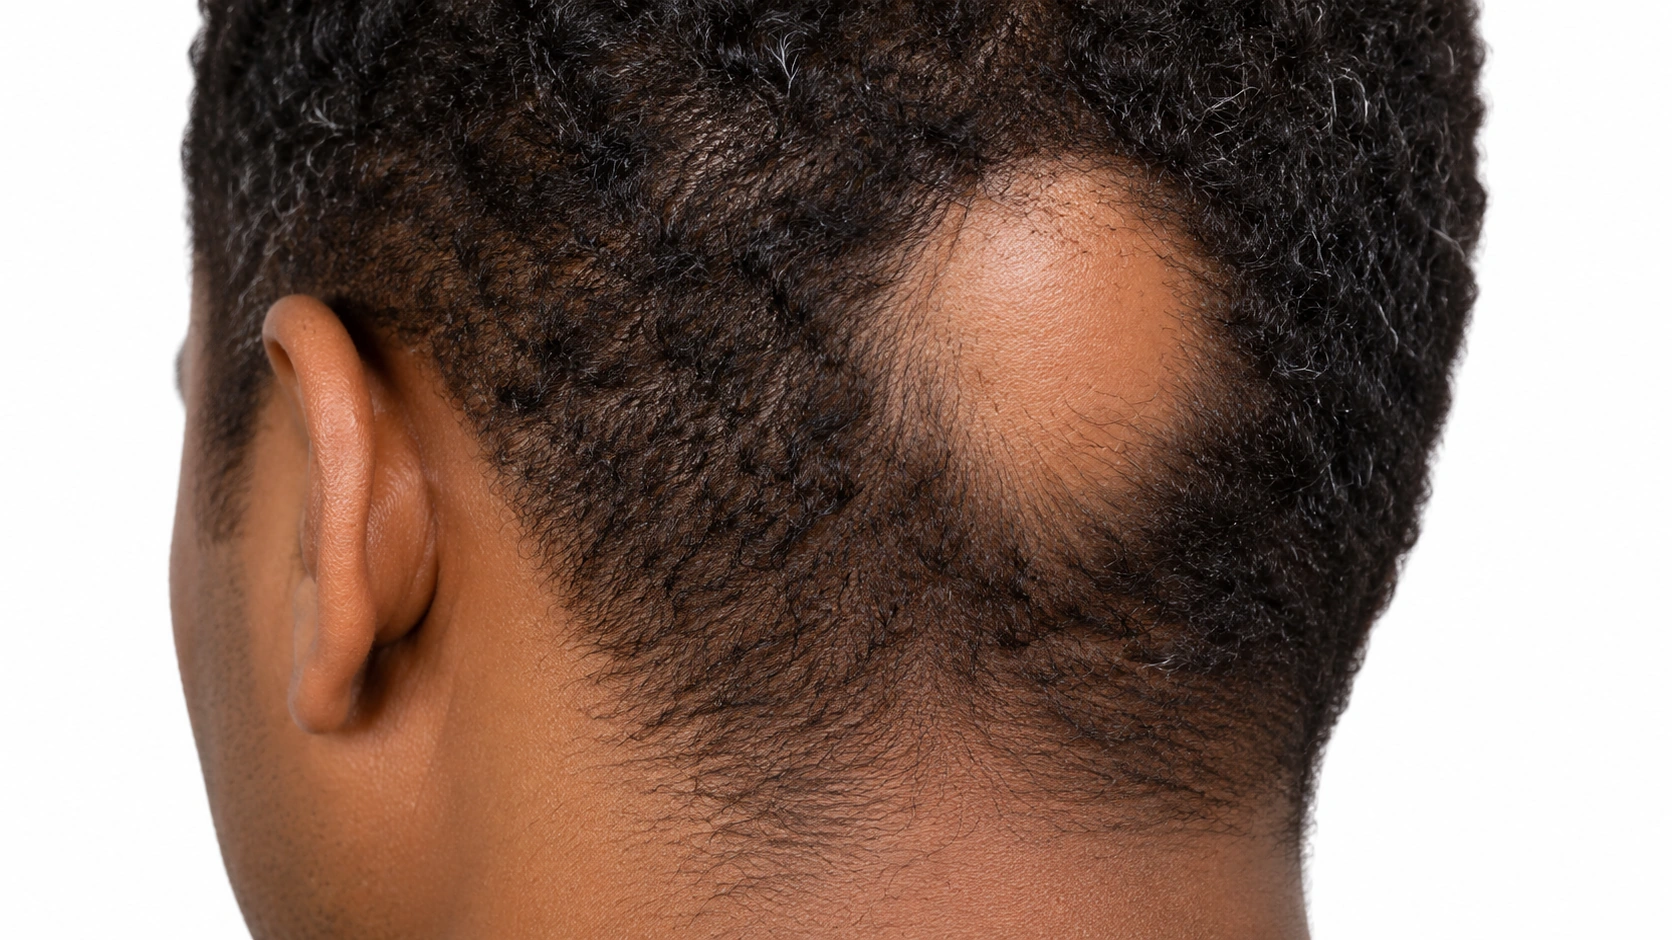
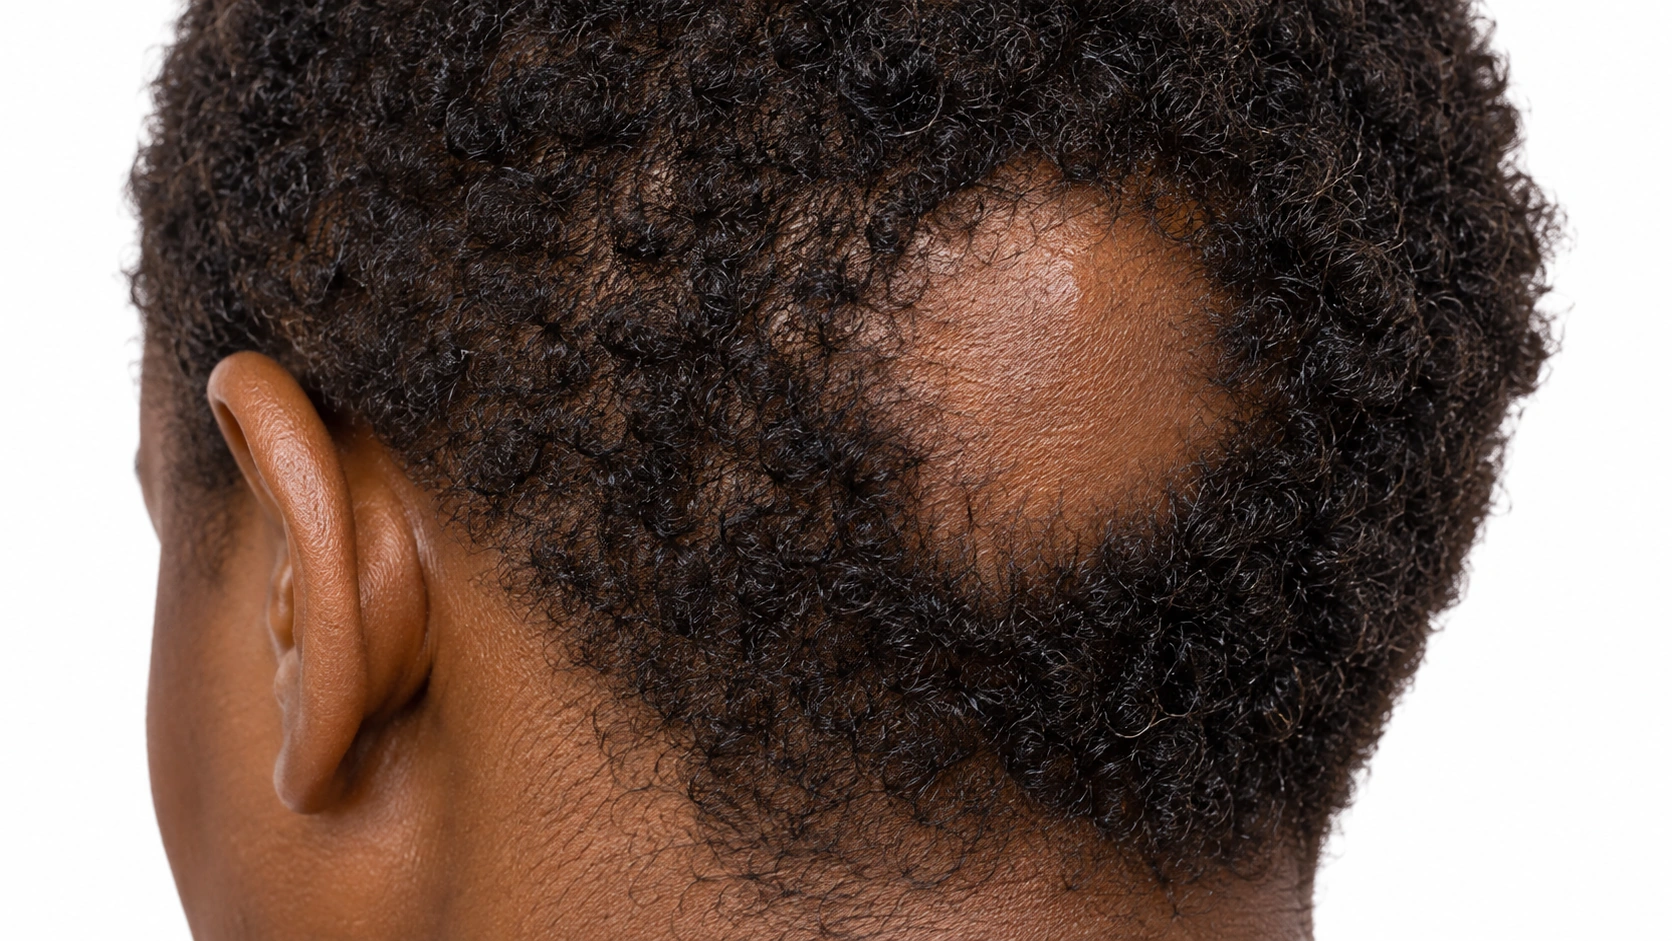
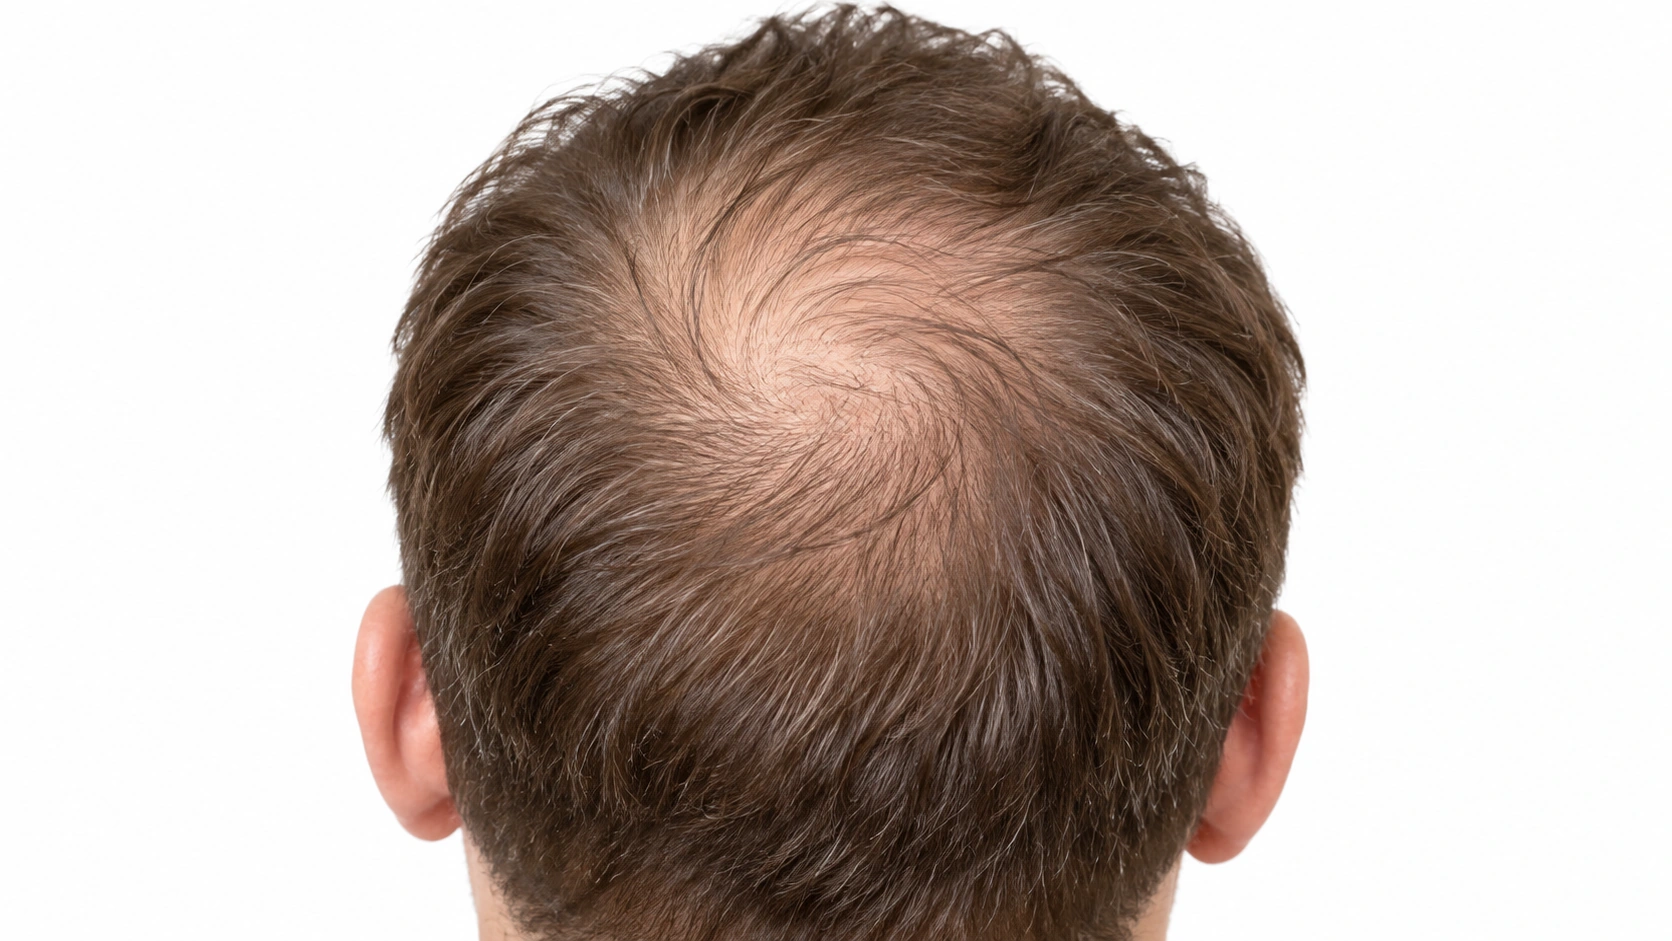
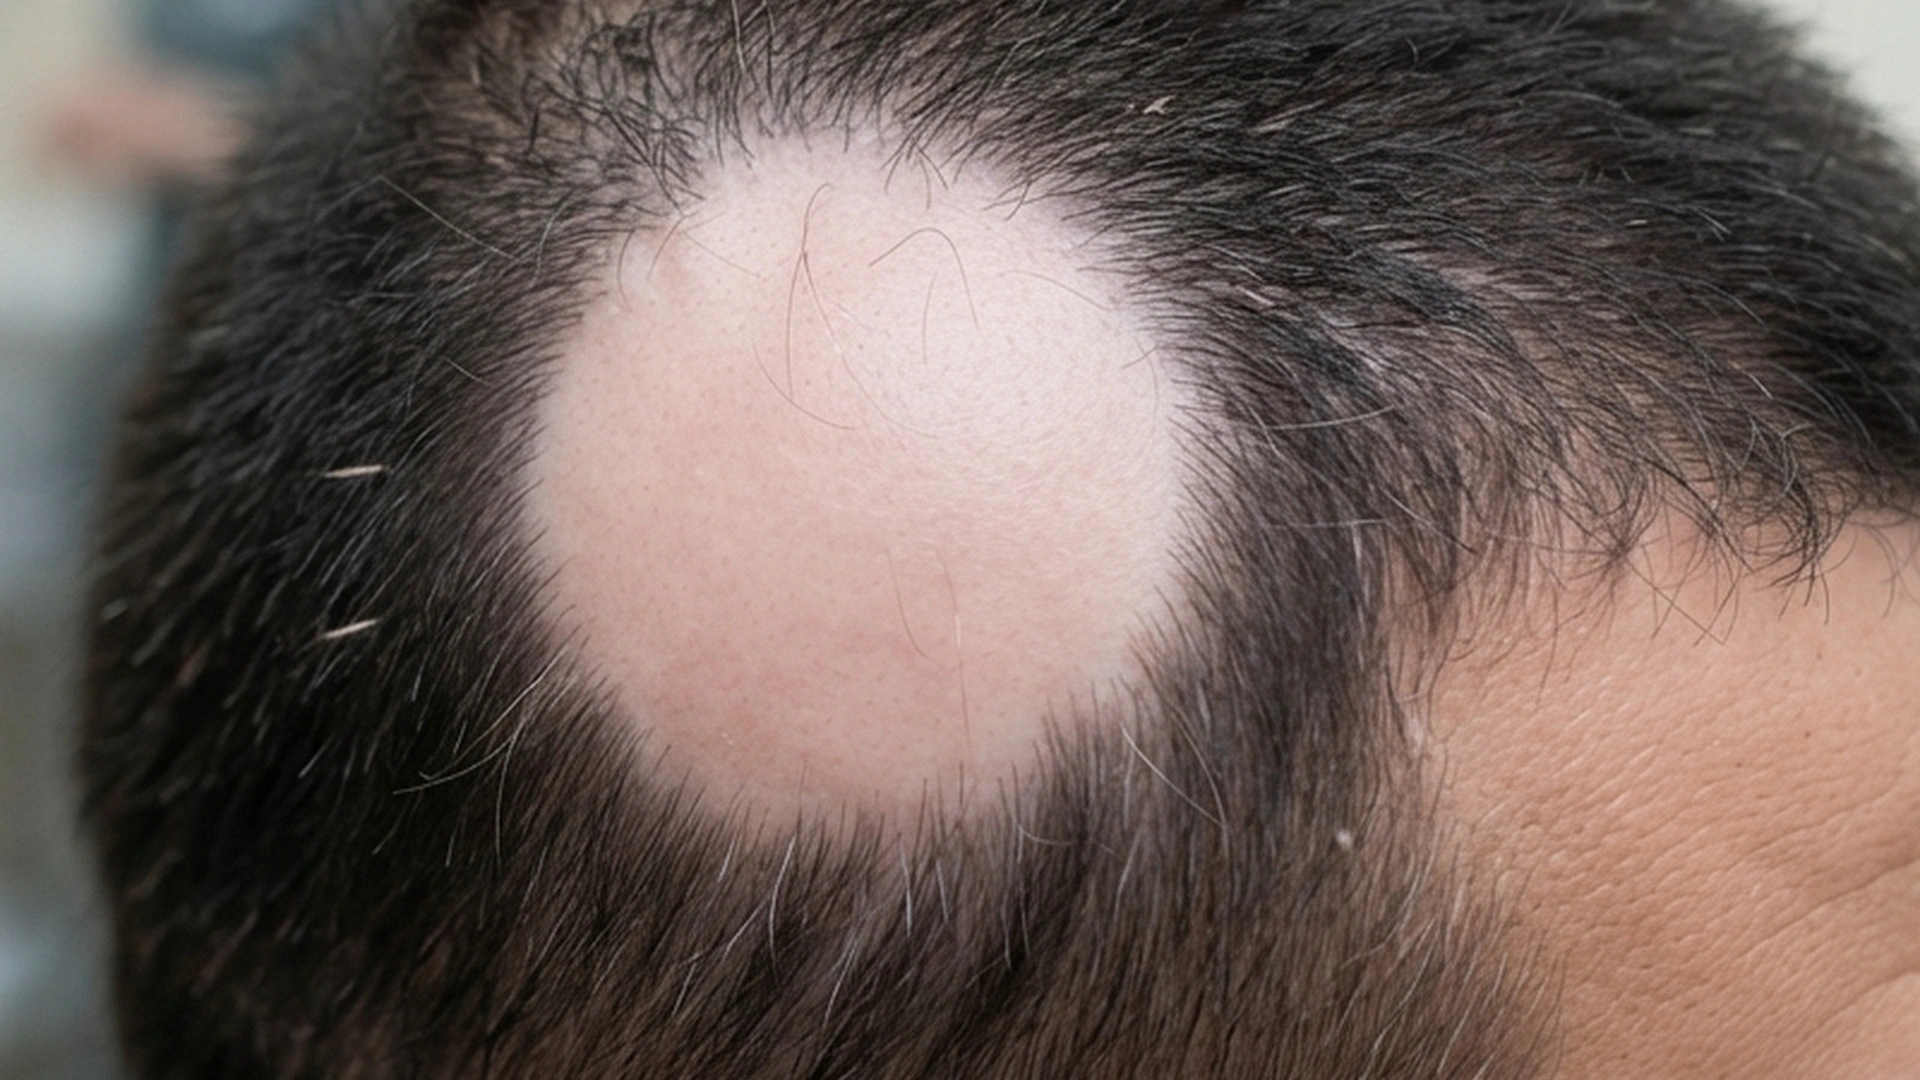
Crown hair thinning with hair retained around the sides on a light scalp.A round smooth bald patch on the scalp.

Key differences

The same eight facts on every condition comparison.

Usual age
After puberty; more with age
Any age; often young
Where
Temples and crown
Scalp, beard, brows
Main sign
Receding hairline, thinning crown
Smooth, round bald patches
Itch or pain
No
Usually none
Contagious
No
No
Long term
Gradual; treatment slows it
Unpredictable; hair can regrow
Scars
No
No
Who gets it
Men with family history
Anyone; runs in families

What is it?

Male Pattern Hair Loss
Alopecia Areata
What is it?

It is progressive follicle shrinkage.
Also called androgenetic alopecia, it follows a recognizable pattern.

Hairs become finer.
The growing phase shortens and coverage decreases.

It is not about hygiene.
It does not reflect poor scalp care.

Other patterns need review.
Sudden shedding, smooth patches, scale or pain may suggest another cause.

It is immune-driven hair loss.
The immune response disrupts active hair follicles.

It does not usually scar.
It differs from infection, pattern thinning and scarring alopecia.

It can start suddenly.
A smooth patch can appear quickly.

Regrowth may look different.
Early regrowth is often fine or pale at first.

What it looks like

Male Pattern Hair Loss

Male Pattern Hair Loss: Receding temples; Early (Norwood 2–3).

Early pattern: Norwood II–III Recession at the temples.

Male Pattern Hair Loss: Crown thinning.

Middle pattern: Norwood IV–V Crown and front thinning.

Male Pattern Hair Loss: Advanced; Advanced (Norwood 6–7).

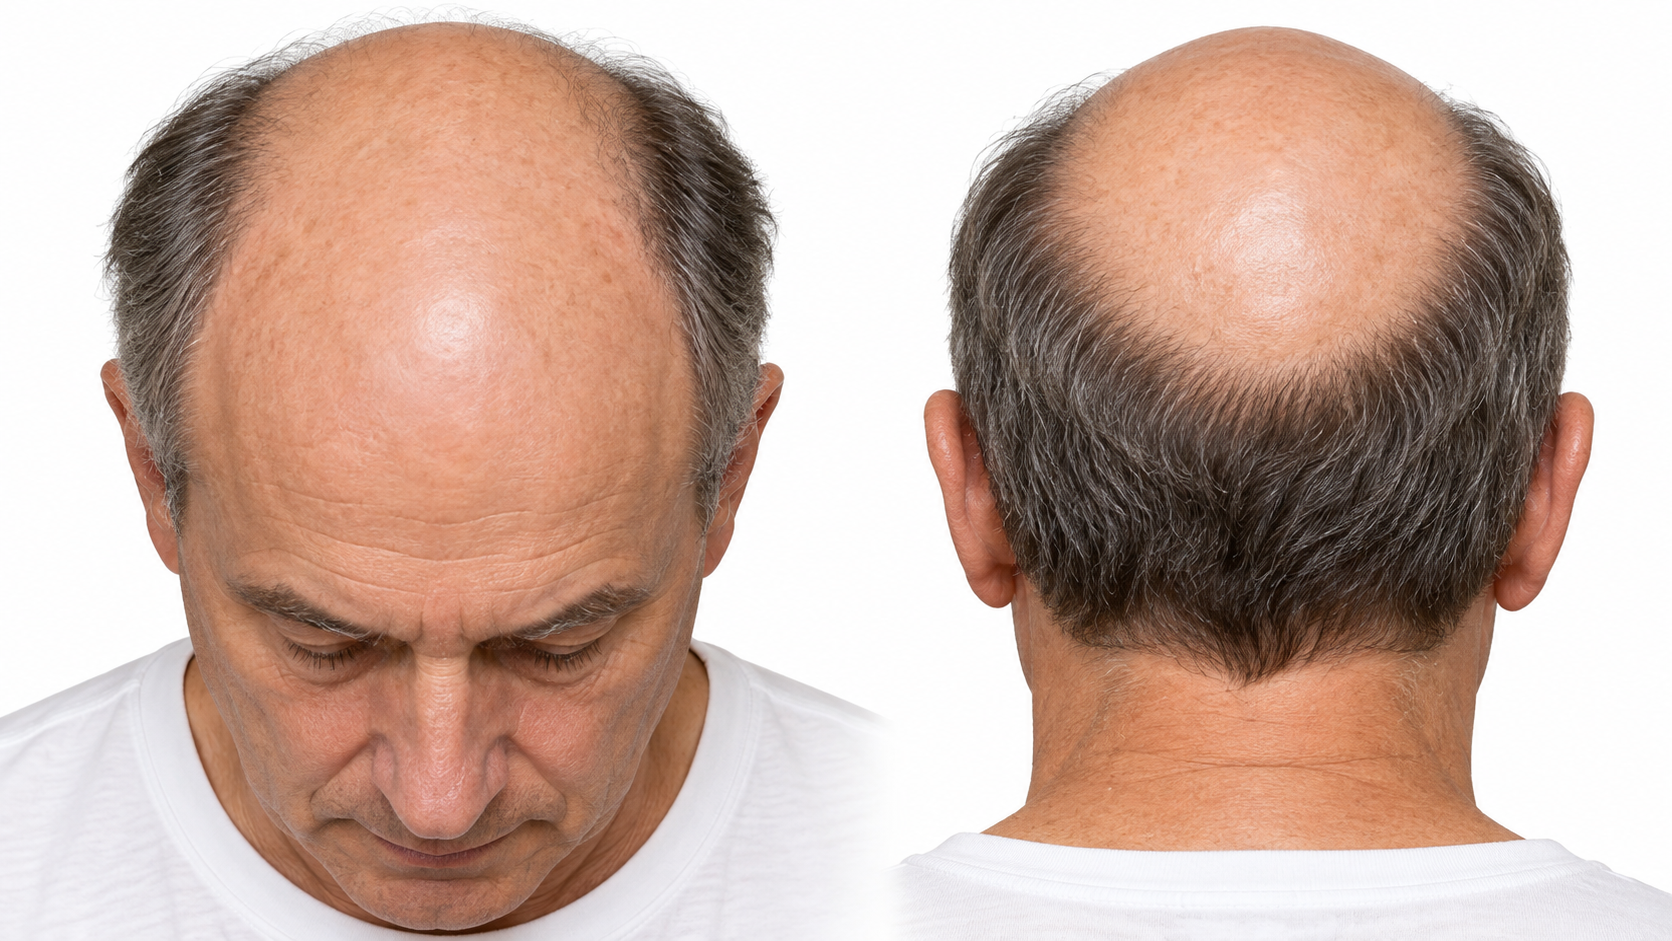
Advanced pattern: Norwood VI–VII Horseshoe pattern.

Alopecia Areata

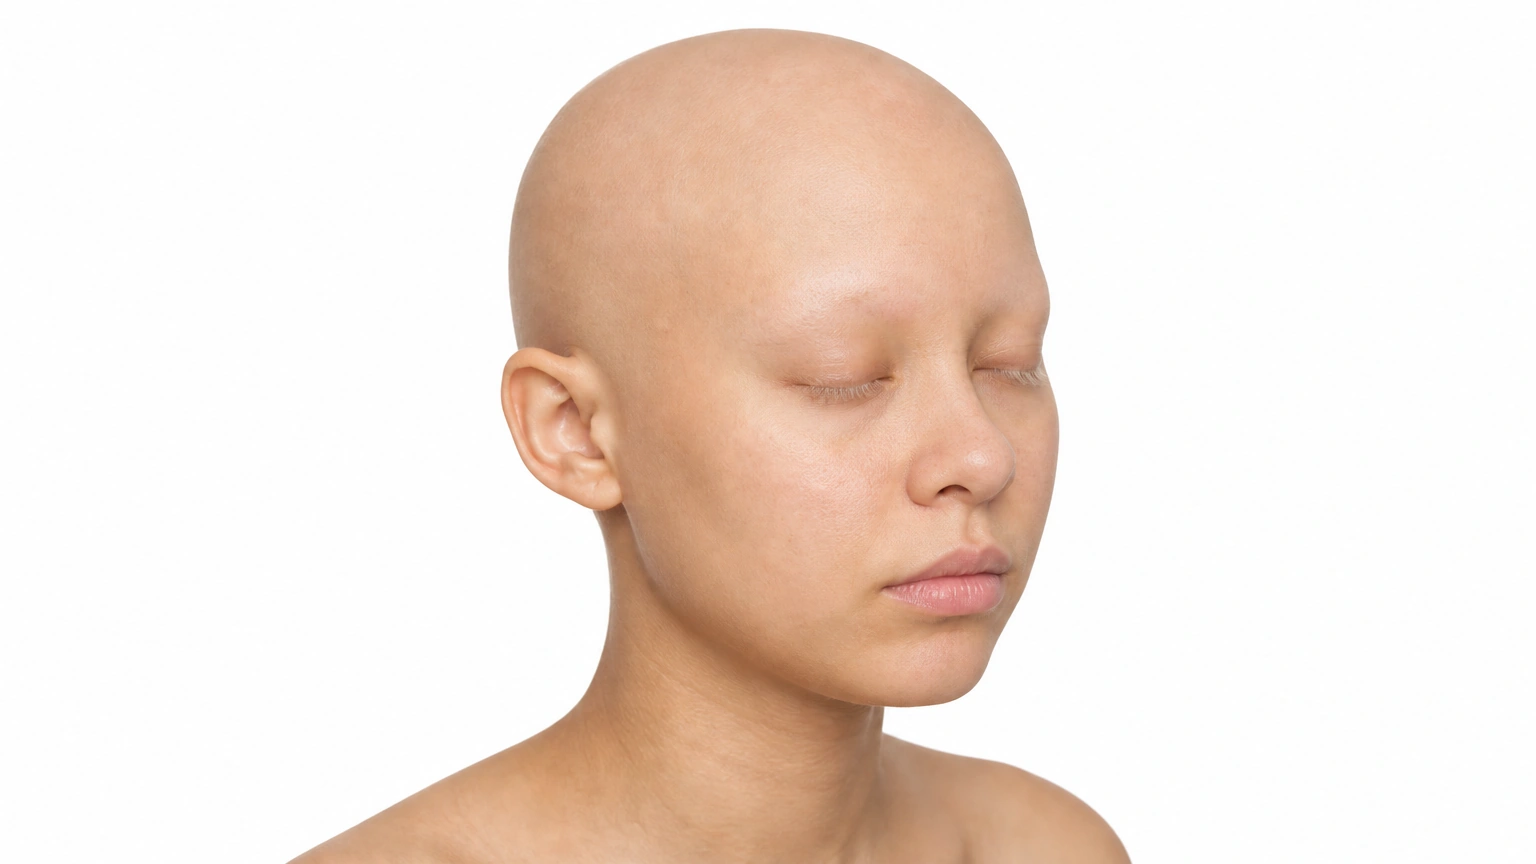
A smooth round bald patch on the scalp, representing alopecia areata.

Patchy alopecia areata One or more round patches; most common.

A smooth hairless patch interrupts the beard.

Beard involvement A smooth hairless patch interrupts the beard.

A broad smooth band of hair loss along the back and sides of the scalp, representing ophiasis-pattern alopecia areata.

Ophiasis pattern A band along the sides and back.

Complete smooth scalp hair loss with eyelashes retained, representing alopecia totalis.

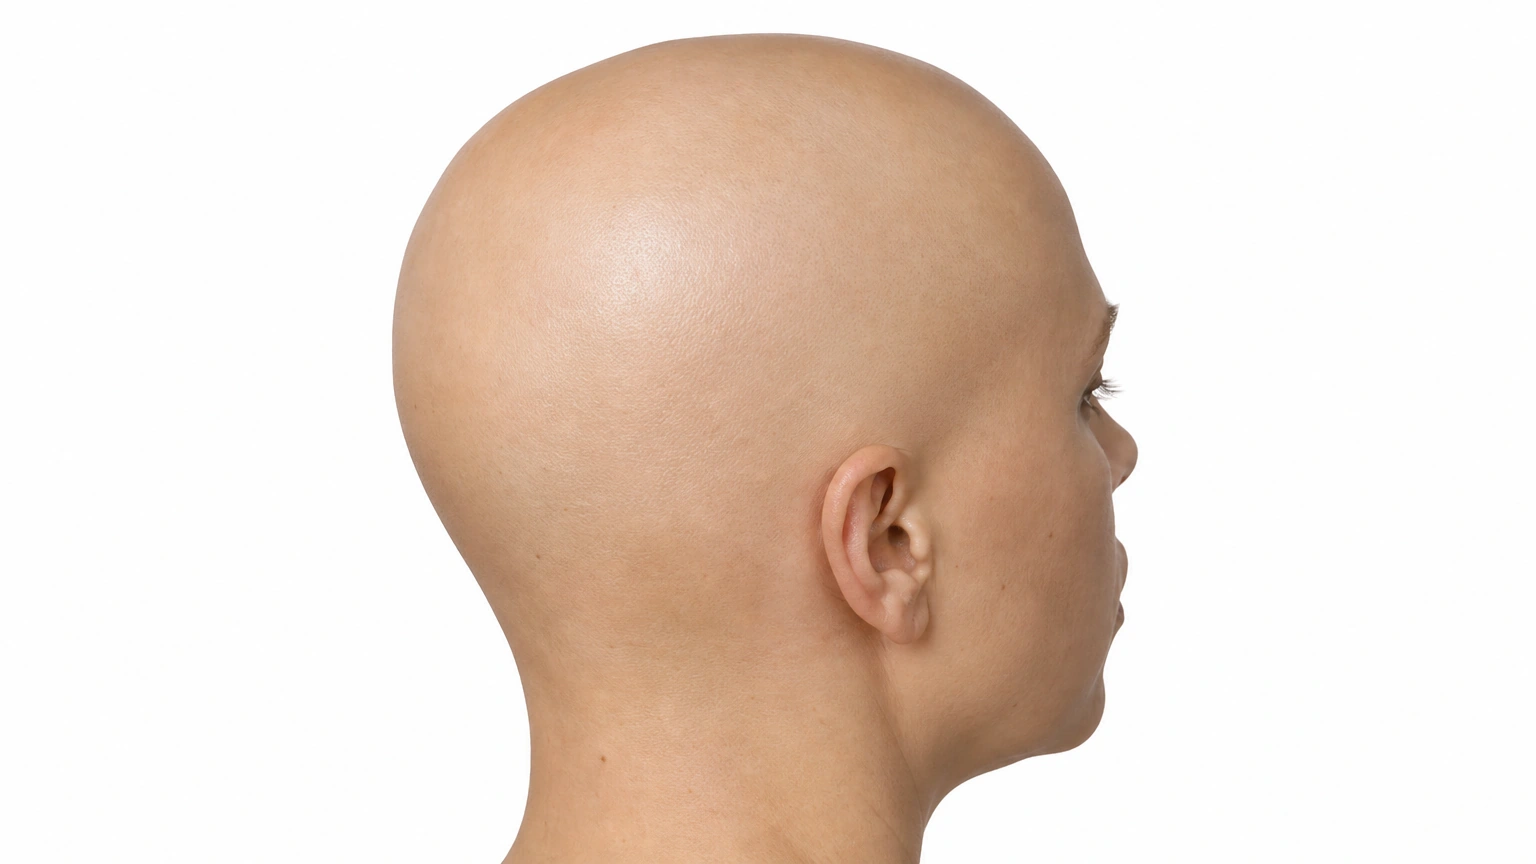
Alopecia totalis Loss of all scalp hair.

Complete scalp, eyebrow and eyelash hair loss, representing alopecia universalis.

Alopecia universalis Loss of all body hair.

Skin tones
Crown hair thinning with hair retained around the sides on a light scalp.
Receding hairline on medium skin.
a receding frontal hairline and thinning crown on brown skin.
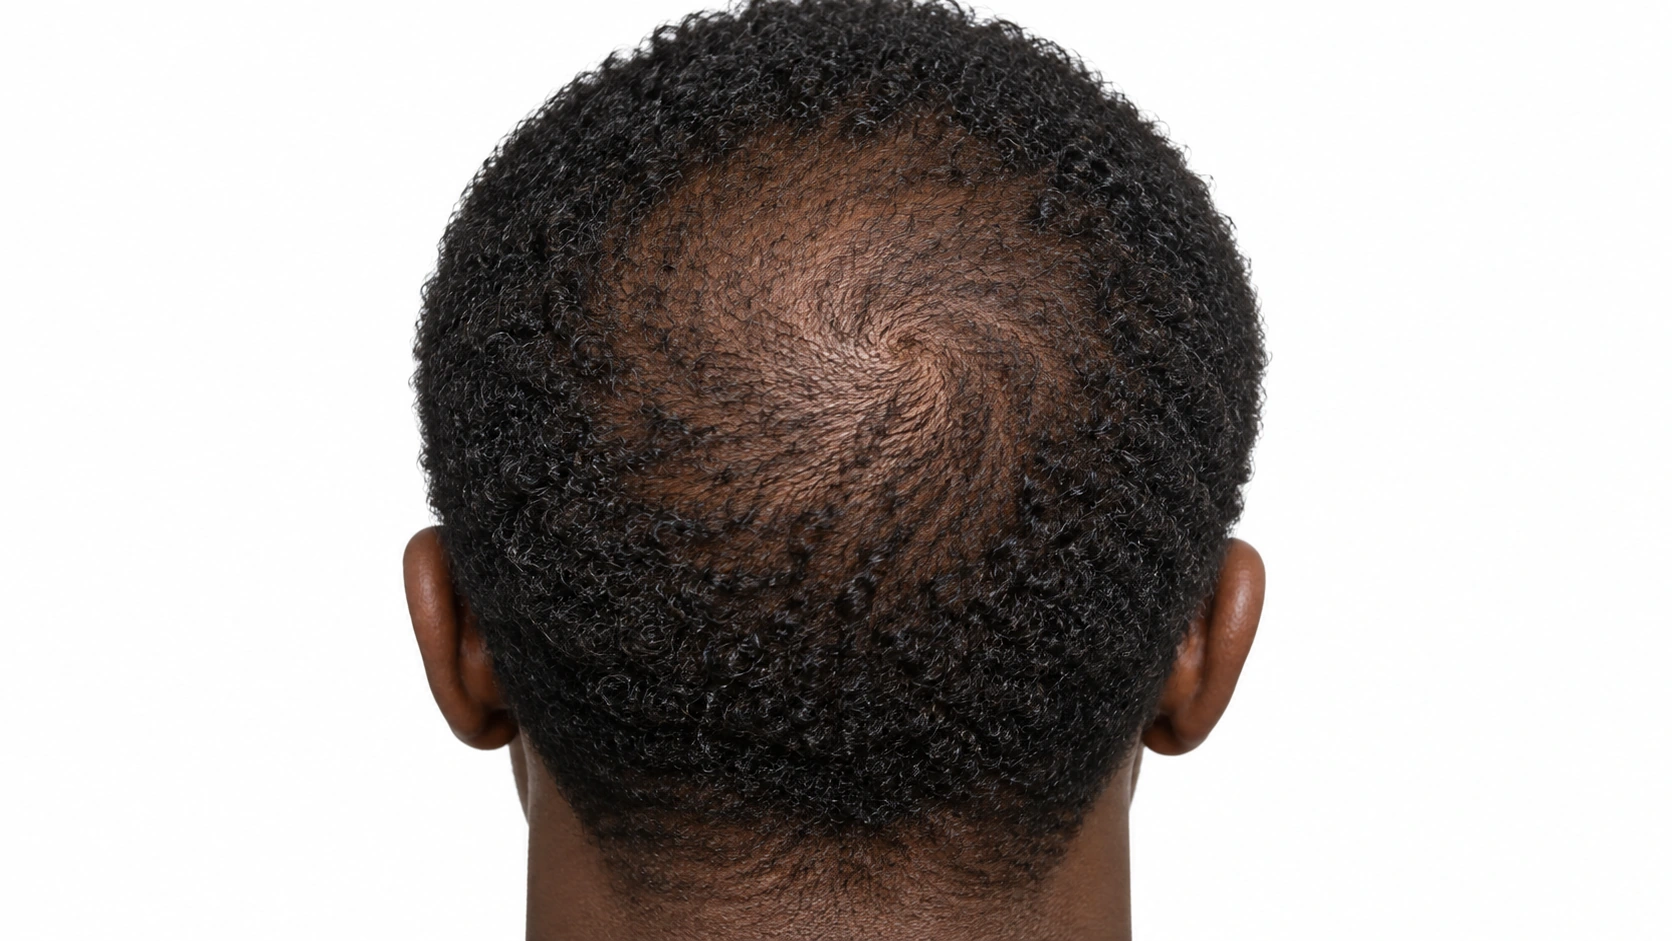
crown hair thinning with the surrounding hair retained on deep brown skin.
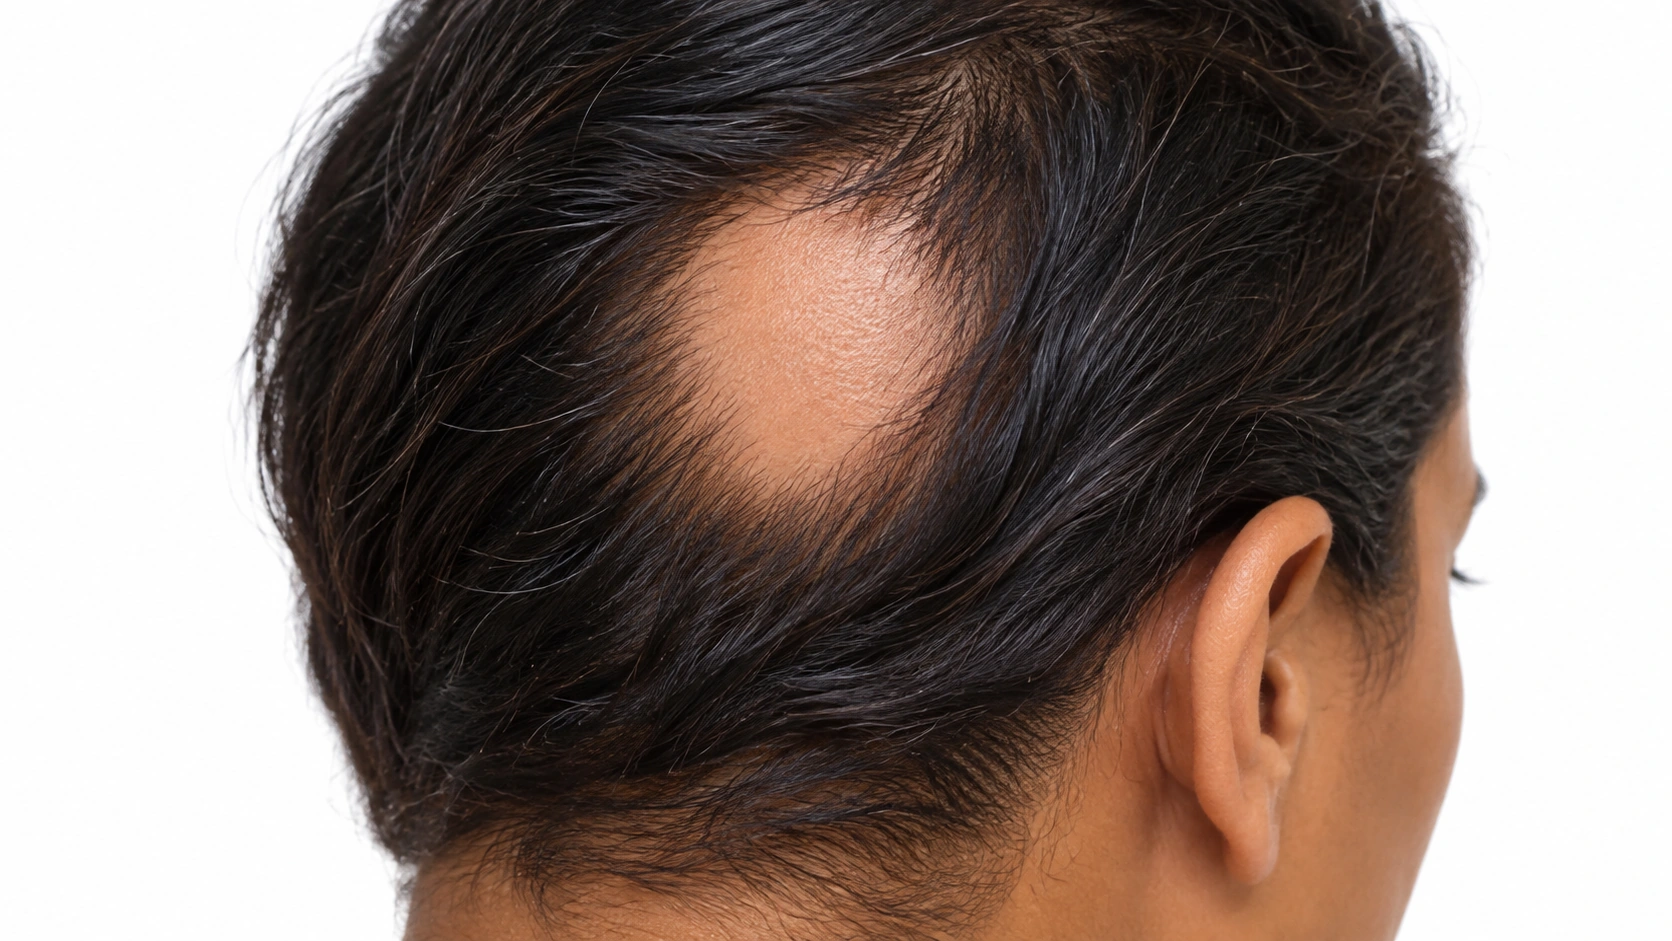
A round smooth bald patch on the scalp.
Smooth round bald patch on a medium-toned scalp.
a smooth, round bald patch at the back of a scalp with brown skin.
a smooth round bald patch in tightly coiled hair on deep brown skin.
Diagram
Male Pattern Hair Loss mechanism diagram. Follicles become smaller: Successive hairs can grow finer and shorter. Growth phases become shorter: Affected hairs spend less time growing. Follicles respond to androgens: DHT acts on genetically susceptible scalp follicles.
Alopecia Areata mechanism diagram. Immune cells target the follicle: The response gathers around growing hair roots. Hair growth is disrupted: Affected hairs can become weak or shed. The follicle usually remains: Regrowth is possible, but the course varies.
In the skin

In genetically susceptible scalp follicles, the hormone DHT contributes to gradual miniaturization. Shorter growth phases produce finer, shorter hairs and reduce visible scalp coverage.

Immune activity around growing hair follicles disrupts hair production and can cause affected hairs to shed. The follicles usually remain present, so regrowth is possible, although the course varies.

Where it shows up

Receding temples and crown
Variable patches on the scalp or body

When it usually starts

010203040506070+

Male Pattern Hair Loss. May begin after puberty and becomes more common with age.

Alopecia Areata. Can start at any age, often in childhood or younger adult life.

Causes and triggers

Causes

Male pattern hair loss happens when DHT, a hormone made from testosterone, shrinks sensitive hair follicles over years.

Alopecia areata is an autoimmune condition. The immune system attacks hair follicles, causing round patches of hair loss.

Family tendency

Genes from both parents matter. The androgen receptor gene on the X chromosome, inherited from the mother, plays a key role.

About 1 in 5 people with it have a relative with it.

Risk factors
Age, Family history, Smoking
Family history, Eczema or asthma, Thyroid disease, Other autoimmune conditions
Trigger
● Male Pattern Hair Loss
● Alopecia Areata
Anabolic steroids and testosterone
Strong link
Not listed
Severe illness or stress
Possible
Not listed
Severe stress
Not listed
Possible
Illness
Not listed
Possible

Daily Care

Male Pattern Hair Loss
Alopecia Areata
Daily care

Habits that help

  • Photographs and patience
    Same light, same angle, every six months.
  • Sun protection on a thinning scalp
    It burns easily and is a common site for skin cancer.
  • Hair transplant surgery
    The only way to put hair where the follicle has closed.
  • Treating anything else going on
    Correcting low iron or thyroid gives back that density.
  • Seek assessment for progressive hair thinning rather than waiting indefinitely
    Every untreated year closes more follicles.

Avoid

  • Avoid: Crash dieting
    Fast weight loss triggers a shed months later.
  • Avoid: Smoking
    Linked to earlier and more severe pattern loss.
  • Avoid: Tight hairstyles
    Cause traction alopecia, which eventually scars.
  • Avoid: Cycling through products
    Nothing here shows its hand in under six months.
  • Avoid: Stopping treatment once it works
    The gains fade over six to twelve months.
  • Avoid: Untreated iron or thyroid problems
    Neither causes pattern loss, but either adds a heavy shed.

Habits that help

  • Sun protection on bare scalp
    Sunscreen, a hat or a scarf.
  • Wigs, toppers, brows and lashes
    Use cosmetic options if they help you feel comfortable with visible hair loss.
  • Talking to someone about it
    Anxiety and low mood are well documented, and support groups exist.
  • Oral JAK inhibitors
    Can regrow hair in very extensive loss, with monitoring and real risks.
  • Follow treatment for a confirmed thyroid problem
    Treating it does not regrow hair, but it is worth finding.

Avoid

  • Avoid: Assuming a patch will sort itself out
    Waiting costs most when loss is spreading.
  • Avoid: Chasing unproven cures
    Months lost while a spreading case goes untreated.
  • Avoid: Severe or prolonged stress
    Often reported before flares, hard to prove.
  • Avoid: Sunburn on bare scalp
    Skin never exposed burns fast and marks for months.
  • Avoid: Stopping treatment at first regrowth
    Regrowth means the attack is suppressed, not over.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Male Pattern Hair Loss
● Alopecia Areata
Filter by type
Hair loss stage

Select one or more.

Alopecia areata pattern

Select one or more.

Over-the-counter
Topical Minoxidil — Header Image

Topical Minoxidil

Strong evidence

The one over-the-counter treatment that genuinely works for pattern hair loss. Applied to the scalp once or twice a day, it lengthens the growing phase and thickens hairs that have already gone fine, so it does most for a crown that is thinning and least where the scalp has been bare for years. Expect more shedding in the first month or two, and expect to keep using it — stopping gives the ground back within six to twelve months.

Educational still life: hair laser cap.

Low-level laser caps and combs

Moderate evidence

Home laser devices have trials behind them showing a modest increase in hair count, and they are safe. The devices are expensive, the sessions have to be kept up several times a week for years, and the effect is smaller than minoxidil or finasteride. Reasonable as an addition to those, weak as a plan on its own.

Ketoconazole shampoo.

Ketoconazole shampoo

Limited evidence

An antifungal shampoo, used two or three times a week, with some small-study evidence for slightly better hair density in pattern loss alongside its usual job on flaking. It is a helper rather than a treatment. Worth having in the routine if your scalp flakes anyway, and not worth relying on by itself while the loss carries on.

Rosemary oil.

Rosemary oil

Limited evidence

One small trial found rosemary oil performed similarly to 2 percent minoxidil over six months, and that single study is doing a great deal of work in how it gets talked about online. It is cheap and low-risk, and it can irritate the scalp if it is not diluted. If you are choosing between this and minoxidil for a hairline you want to keep, minoxidil has far more behind it.

Biotin and hair supplements.

Biotin and hair supplements

Limited evidence

Biotin only helps hair if you are genuinely deficient in it, which is rare. In pattern hair loss it does nothing measurable. High doses can also throw off thyroid and heart blood tests, which occasionally causes real trouble in an emergency room. If you think something else is going on as well, ask for iron and thyroid tests rather than a supplement.

Topical Minoxidil — Header Image

Topical Minoxidil

Limited evidence

Minoxidil does not switch off the immune attack, so it will not clear a patch on its own here. What it does is support hair that is already coming back, which is why it is usually added to injections or a steroid rather than used by itself. It has to be kept up to keep any benefit.

Biotin and hair supplements.

Biotin and hair supplements

Limited evidence

Biotin, collagen and hair-and-nail supplements are the first thing most people try. They do nothing for alopecia areata, because the problem is an immune attack rather than a shortage of a nutrient. Iron, vitamin D or thyroid problems are worth checking and correcting if a blood test shows one, but supplements taken on spec are not a treatment.

Serum dropper bottle lying on its side, labelled Rosemary Oil, with a product-texture swatch behind it on a white background.

Rosemary oil and onion juice

Limited evidence

These circulate constantly online, and neither has evidence worth acting on in alopecia areata. Because many single patches fill in on their own within a year, whatever someone was using at the time gets the credit. They are mostly harmless in themselves — the real cost is the months that pass while a spreading case goes untreated.

Existing illustration of Hair fibers and root powders.

Wigs, toppers, brows and lashes

Listed

Not a lesser option, and not giving up. Wigs, toppers, scalp micropigmentation, brow pencils and false lashes let people carry on while treatment is tried, and many people use them for years alongside everything else. In the US many insurers cover a wig with a prescription, so it is worth asking your dermatologist to write one.

Prescription topicals
Educational still life: topical solution.

Topical finasteride

Moderate evidence

A solution or spray put on the scalp instead of swallowing a tablet. Trials show it works close to as well as the tablet with lower drug levels in the blood, which is why it appeals to men worried about side effects. Some of it is still absorbed, so the same conversation applies. It is usually made up by a compounding pharmacy, and consistency between them varies.

Clobetasol — Header Image

Clobetasol

Limited evidence

Clobetasol Propionate. A strong topical steroid used on the patch, often under a cover overnight to push it in. It is slower and less reliable than injections, and it is the usual choice for children and for anyone who does not want needles. Used for months on the same area it can thin the skin, so it is worked in cycles with breaks rather than applied indefinitely.

Anthralin

Limited evidence

Anthralin cream. An old treatment applied for a short time each day and then washed off, deliberately causing a mild irritation that seems to distract the immune system from the follicle. It is used mainly in children and when steroids have not worked. It stains skin, hair and towels a brown-orange, and it needs patience over months.

Prescription pills
Finasteride — Header Image

Finasteride

Strong evidence

The most effective single treatment for male pattern hair loss. One tablet a day blocks the enzyme that makes DHT, and in trials it holds the line in the large majority of men and thickens some of the hair that has gone fine. Judge it at a year, not at three months. The commonly reported side effects are sexual, affect a small percentage of men, and are worth weighing with a doctor rather than with a forum.

An amber pill bottle labeled Dutasteride tipped over with white tablets spilling out

Dutasteride

Moderate evidence

A stronger relative of finasteride that blocks both forms of the enzyme, and head-to-head studies favor it on hair count. In most countries it is not licensed for hair loss and is prescribed off-label, usually when finasteride has not held the line. It stays in the body far longer than finasteride, which matters if you might want to stop.

Oral Minoxidil — Header Image

Oral Minoxidil

Moderate evidence

Low-dose minoxidil tablets, prescribed off-label when the topical is impractical, irritating or not doing enough. It suits men who will not keep up a twice-daily liquid on the scalp. Because it works throughout the body it can cause unwanted hair on the face and body, ankle swelling and, less often, a fast heartbeat, so it needs a doctor who is monitoring it.

Olumiant

Strong evidence

A JAK inhibitor tablet, approved for severe alopecia areata in adults, that blocks the immune signals attacking the follicle. In trials a substantial share of people with extensive loss regrew most of their scalp hair over several months to a year. It is not a cure — the loss usually returns after stopping — and it needs blood tests before and during treatment, with real risks around infection, blood clots and cholesterol to weigh up first.

Litfulo

Strong evidence

A second JAK inhibitor tablet for severe alopecia areata, approved from age 12, which makes it the option for teenagers as well as adults. The results, the monitoring and the trade-offs are broadly similar to baricitinib, and which one is chosen often comes down to age, other health conditions and what your insurance covers. A third, deuruxolitinib, is also available for adults.

Prednisone — Header Image

Prednisone

Limited evidence

A short course of steroid tablets is sometimes used to slow loss that is spreading quickly. It can work while it is being taken, and hair frequently falls out again once it stops. Because the side effects of long-term steroids are serious, it is a bridge to another treatment rather than a plan on its own.

16:9 hero for Methotrexate. Never cropped: the tone strip and the corner logo depend on the full frame.

Methotrexate

Limited evidence

An older immune-suppressing tablet used for extensive alopecia areata, sometimes with a low dose of steroid alongside. It has been overtaken by the JAK inhibitors for most people, and it stays useful where those are not available, not affordable or not suitable. It takes months to judge, needs regular blood tests, and must not be taken in pregnancy.

Injections
None listed
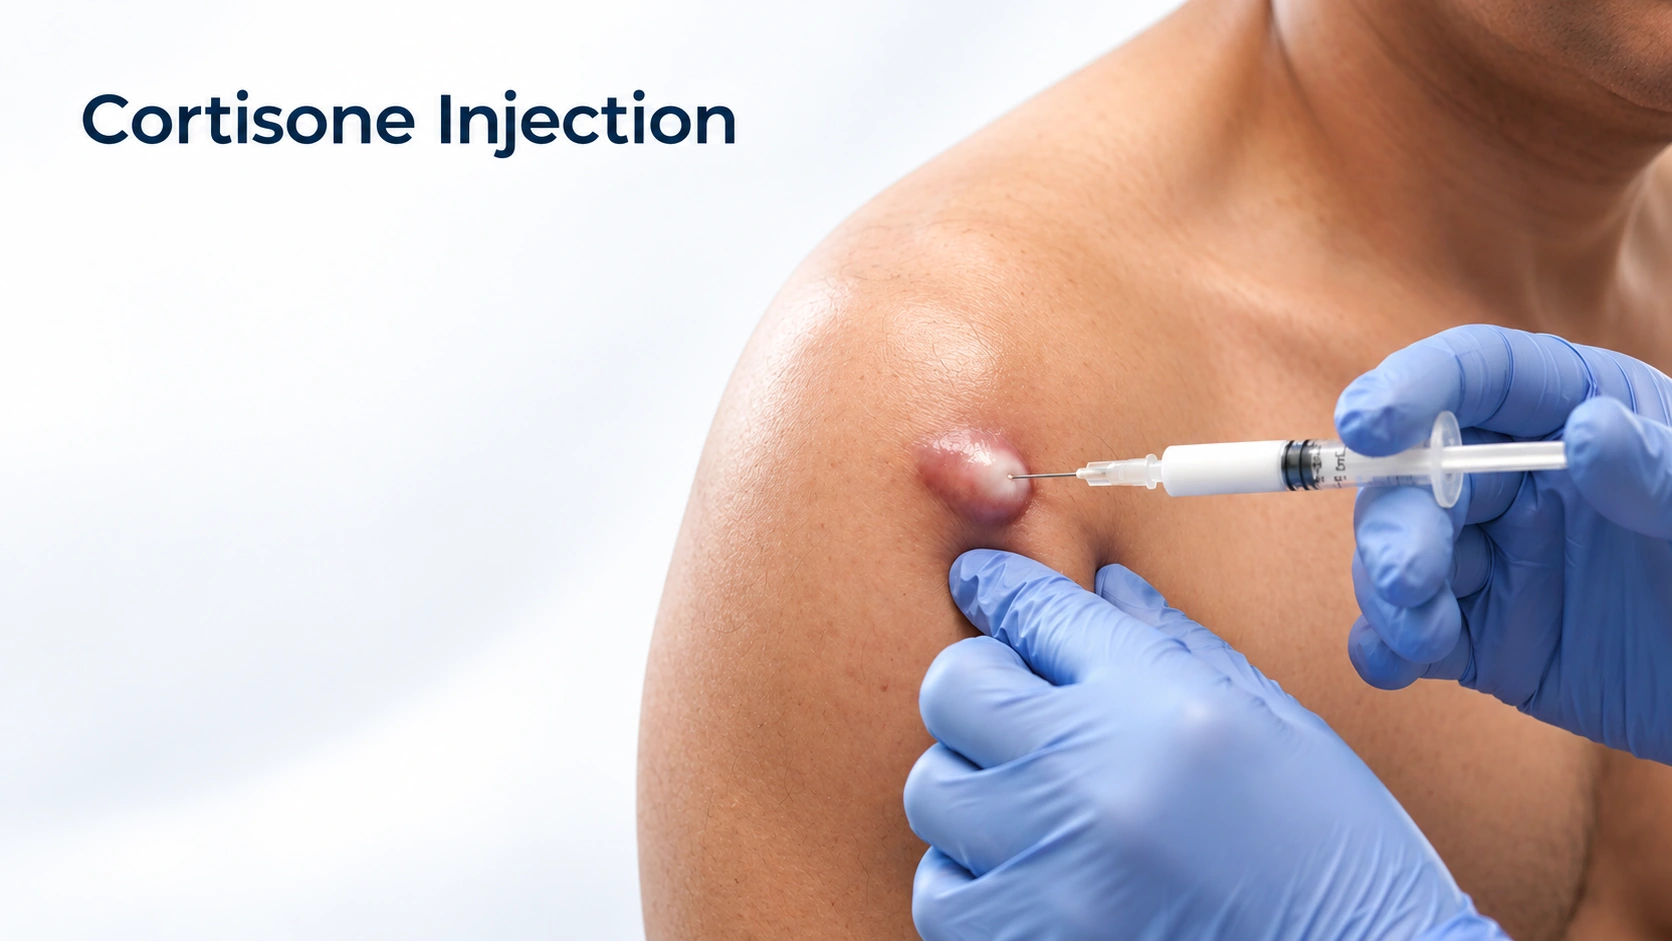
Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Moderate evidence

Steroid Injections. The fastest reliable option for a limited number of patches, and the usual first treatment in adults. Several small injections are placed across a patch, repeated every four to six weeks, with regrowth often visible in one to two months. They sting for a few seconds each, and numbing cream beforehand is fine to ask for. They can leave a lighter patch of skin or a small dent where the fat has thinned, which usually recovers over months and shows more on deeper skin tones. They treat the patches injected, not the tendency.

Procedures
Editorial illustration for Hair Transplant, based on the entry’s treatment or equipment reference.

Hair Transplant

Moderate evidence

The only treatment that puts hair back where the follicle has already closed. Follicles are moved from the permanent band at the back of the head to the front and crown, and they keep growing there because they never carried the sensitivity in the first place. It works best once the pattern has settled, and nearly everyone is advised to stay on medical treatment afterwards, because a transplant does nothing for the untreated hair around the grafts.

Editorial illustration for PRP for Hair Loss, based on the entry’s treatment or equipment reference.

PRP for Hair Loss

Moderate evidence

Your own platelets, concentrated and injected into the scalp, usually three or four sessions and then top-ups. Studies suggest a modest improvement in density, but they are small and use different protocols, so it is hard to say who benefits and by how much. It is an add-on to minoxidil and finasteride, priced like a main treatment.

Editorial illustration for Microneedling, based on the entry’s treatment or equipment reference.

Microneedling

Moderate evidence

Fine needles rolled or stamped into the scalp, used alongside minoxidil rather than instead of it. The small trials that exist favor the combination over minoxidil alone. Sessions are spaced weeks apart, and doing it too often or too deeply irritates the scalp without adding anything.

Editorial illustration for Hair Transplant, based on the entry’s treatment or equipment reference.

Hair Transplant

Limited evidence

This is the wrong operation for alopecia areata, and it is worth knowing why before anyone offers it. The follicles here are alive and switched off rather than gone, so there is nothing to replace, and moved hairs land in skin where the same immune attack is still running and can be lost too. Transplants are for scarring hair loss and for pattern hair loss, where the follicle really has been destroyed.

Editorial illustration for PRP for Hair Loss, based on the entry’s treatment or equipment reference.

PRP for Hair Loss

Limited evidence

Your own blood is spun down and the platelet-rich part injected into the patch. Small studies in alopecia areata have shown some regrowth, but they are few and short, and there is no agreed recipe or schedule. It is not covered by insurance and courses are expensive, so it is a reasonable thing to try after the better-tested options rather than instead of them.

Editorial illustration for Contact Immunotherapy, based on the entry’s treatment or equipment reference.

Contact Immunotherapy

Moderate evidence

A chemical is painted on the scalp to set off a deliberate mild allergic reaction, which appears to pull the immune system's attention away from the follicles. It is one of the better options for widespread loss where injections are not practical, and it is done in specialist centers. It means a mildly itchy, red, flaky scalp every week for months, and results take that long to appear.

Editorial illustration for Excimer Laser, based on the entry’s treatment or equipment reference.

Excimer Laser

Limited evidence

Targeted ultraviolet light delivered to individual patches, usually twice a week for a few months. It is painless and can be useful for a small number of stubborn patches, including in children who cannot manage injections. The evidence is thin, regrowth often fades after treatment stops, and it asks for a lot of clinic visits.

Outlook

Long term

This is a decades-long process, not an event. It moves in steps rather than at a steady rate, so a quiet stretch is normal and does not mean it has finished.

Alopecia areata is unpredictable. The follicle survives throughout, however long the hair has been gone, which is why treatment stays worth trying after a long gap.

Complications

Possible complications
  • Sun damage on an exposed scalp
  • The effect on mood and confidence
More details

Sun damage on an exposed scalp
A scalp that has lost its cover burns easily, and years of that exposure make the top of the head a common place for rough scaly patches called actinic keratoses, and for skin cancer. It is the one complication of pattern hair loss that affects health rather than appearance. Sunscreen on the part line and the crown, or a hat, is the whole of the prevention, and it matters after a transplant too while the new hairline is still thin.

The effect on mood and confidence
For some men this is a cosmetic change they stop noticing within a year. For others it affects mood, confidence and how they behave around other people, and that is a real reason to treat rather than a vain one. It is worth saying at the appointment, because it changes what is worth offering and how soon. It is also the reason to judge treatment on photographs rather than on how you feel in the shower.

  • Sunburn on an unprotected scalp
  • Losing Eyebrows and Eyelashes
  • Anxiety and low mood
More details

Sunburn on an unprotected scalp
Scalp skin that has been covered by hair all its life has no tan and no toughening, so it burns very fast — sometimes within twenty minutes. A burn there is painful, it can blister, and on deeper skin tones it often leaves a dark mark that outlasts the burn by months. Sunscreen, a hat or a scarf on any bare area prevents it entirely, and it is the easiest thing on this page to avoid.

Losing Eyebrows and Eyelashes
In some people the immune attack takes the brows and lashes as well as the scalp. Lashes keep dust, sweat and grit out of the eye, so losing them can leave the eyes gritty, watery and easily irritated, and wind and bright light feel worse. Sunglasses help day to day. This is also the loss people find hardest to cover, and it is a reasonable thing to bring up at the appointment rather than manage alone.

Anxiety and low mood
The weight of this is not a side issue. People field questions from strangers, cover up in photographs, and wake up not knowing what they will find on the pillow, and anxiety and low mood are well documented in alopecia areata. It is worth saying out loud at the appointment if it is affecting your sleep, your work or your mood. Support groups exist, and many insurers in the US cover a wig with a prescription.

When to get help

When to get help

Seek assessment if loss is sudden, patchy, painful or associated with scalp inflammation, or if you want help choosing an ongoing treatment.

Arrange assessment for new patchy hair loss, eyebrow or eyelash loss, or rapid progression. Scalp scale or pain may indicate a different cause.

Common questions

Male Pattern Hair Loss:Will my hair grow back?

Some of it, in the right places. Thinning areas still have follicles that can thicken again with treatment. Areas bare for years have no working follicle to respond, and only a transplant puts hair there. That is the whole argument for starting early.

Male Pattern Hair Loss:How long before I know if a treatment is working?

Six months at a minimum, a year for a fair verdict. Hair grows about a centimeter a month and each follicle has to finish its current cycle before you see the new one, so anything judged at eight weeks tells you almost nothing. Expect a temporary increase in shedding in the first month or two of minoxidil.

Male Pattern Hair Loss:Do I have to take it forever?

For as long as you want the effect. These treatments suppress an ongoing process rather than cure it, so stopping lets it resume, and the hair you gained is usually lost within six to twelve months. That is a real cost, and a fair reason some men decide not to start.

Male Pattern Hair Loss:Are the side effects of finasteride as bad as I have read online?

The commonly reported ones are sexual, and in trials they affect a small percentage of men and generally settle when the drug is stopped. Whether a small number have symptoms that persist afterwards is genuinely debated among specialists and not settled. Weigh that with a doctor rather than a forum.

Male Pattern Hair Loss:Is my hair loss caused by stress?

Stress does not cause pattern hair loss. It can cause a separate heavy all-over shed called telogen effluvium, which shows up two to three months after the stressful period and recovers on its own. That shed often thins the hair enough to reveal pattern loss that had been building quietly for years, so stress takes the blame for both.

Male Pattern Hair Loss:Should I get a hair transplant?

It is reasonable for the right person — loss settled into a stable pattern, good donor hair at the back, and willingness to stay on medical treatment afterwards. Transplanting into a scalp that is still actively thinning looks worse a few years later, as the untreated hair around the grafts keeps going.

Alopecia Areata:Will my hair grow back?

Often, but nobody can promise it. A single small patch fills in within a year in a large share of people, with or without treatment. Widespread loss is much less predictable. There is always a chance, because the follicle is switched off rather than destroyed, even after years.

Alopecia Areata:Is this caused by stress?

Stress may trigger it in someone already predisposed. It is not the underlying cause, and calming your life down is not a treatment. Manage stress for its own sake, and do not blame yourself for the hair.

Alopecia Areata:Is it contagious? Can my children catch it?

No. It cannot be passed by contact of any kind. There is an inherited tendency, so your children have a somewhat higher chance of developing it, but that is genetics rather than transmission.

Alopecia Areata:Does this mean I will get other autoimmune diseases?

Not necessarily. Thyroid disease, vitiligo and a few others are more common, which is why thyroid function is checked once. Most people never develop another.

Alopecia Areata:Do the steroid injections hurt, and how often do I need them?

They sting for a few seconds each, and there are usually several across a patch, so the appointment is uncomfortable rather than painful. They are typically repeated every four to six weeks while there is reason to continue. Numbing cream helps, and it is fine to ask for it.

Alopecia Areata:Why did my hair come back white?

That is normal here. The pigment cells take longer to restart than the hair-making cells, so new growth comes through fine and pale before it thickens and regains color over the following months. It is a sign of recovery, not failure.
Sources

Sources and further reading

  1. DermNet
  2. DermNet
Dermapedia on YouTube