Melasma
Clinical trials support improvement with monitored topical treatment.
Hydroquinone: Treats selected hyperpigmentation, including melasma, under an appropriate treatment plan. Tranexamic Acid: Topical formulas are studied for melasma, with mixed results.


Choose for diagnosed stubborn pigment with professional guidance and a defined review point.
Consider a topical pigment option; the evidence is mixed and formula-specific.
Can you use both?
A common melasma pairing; tranexamic acid is gentle and can continue after hydroquinone stops.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

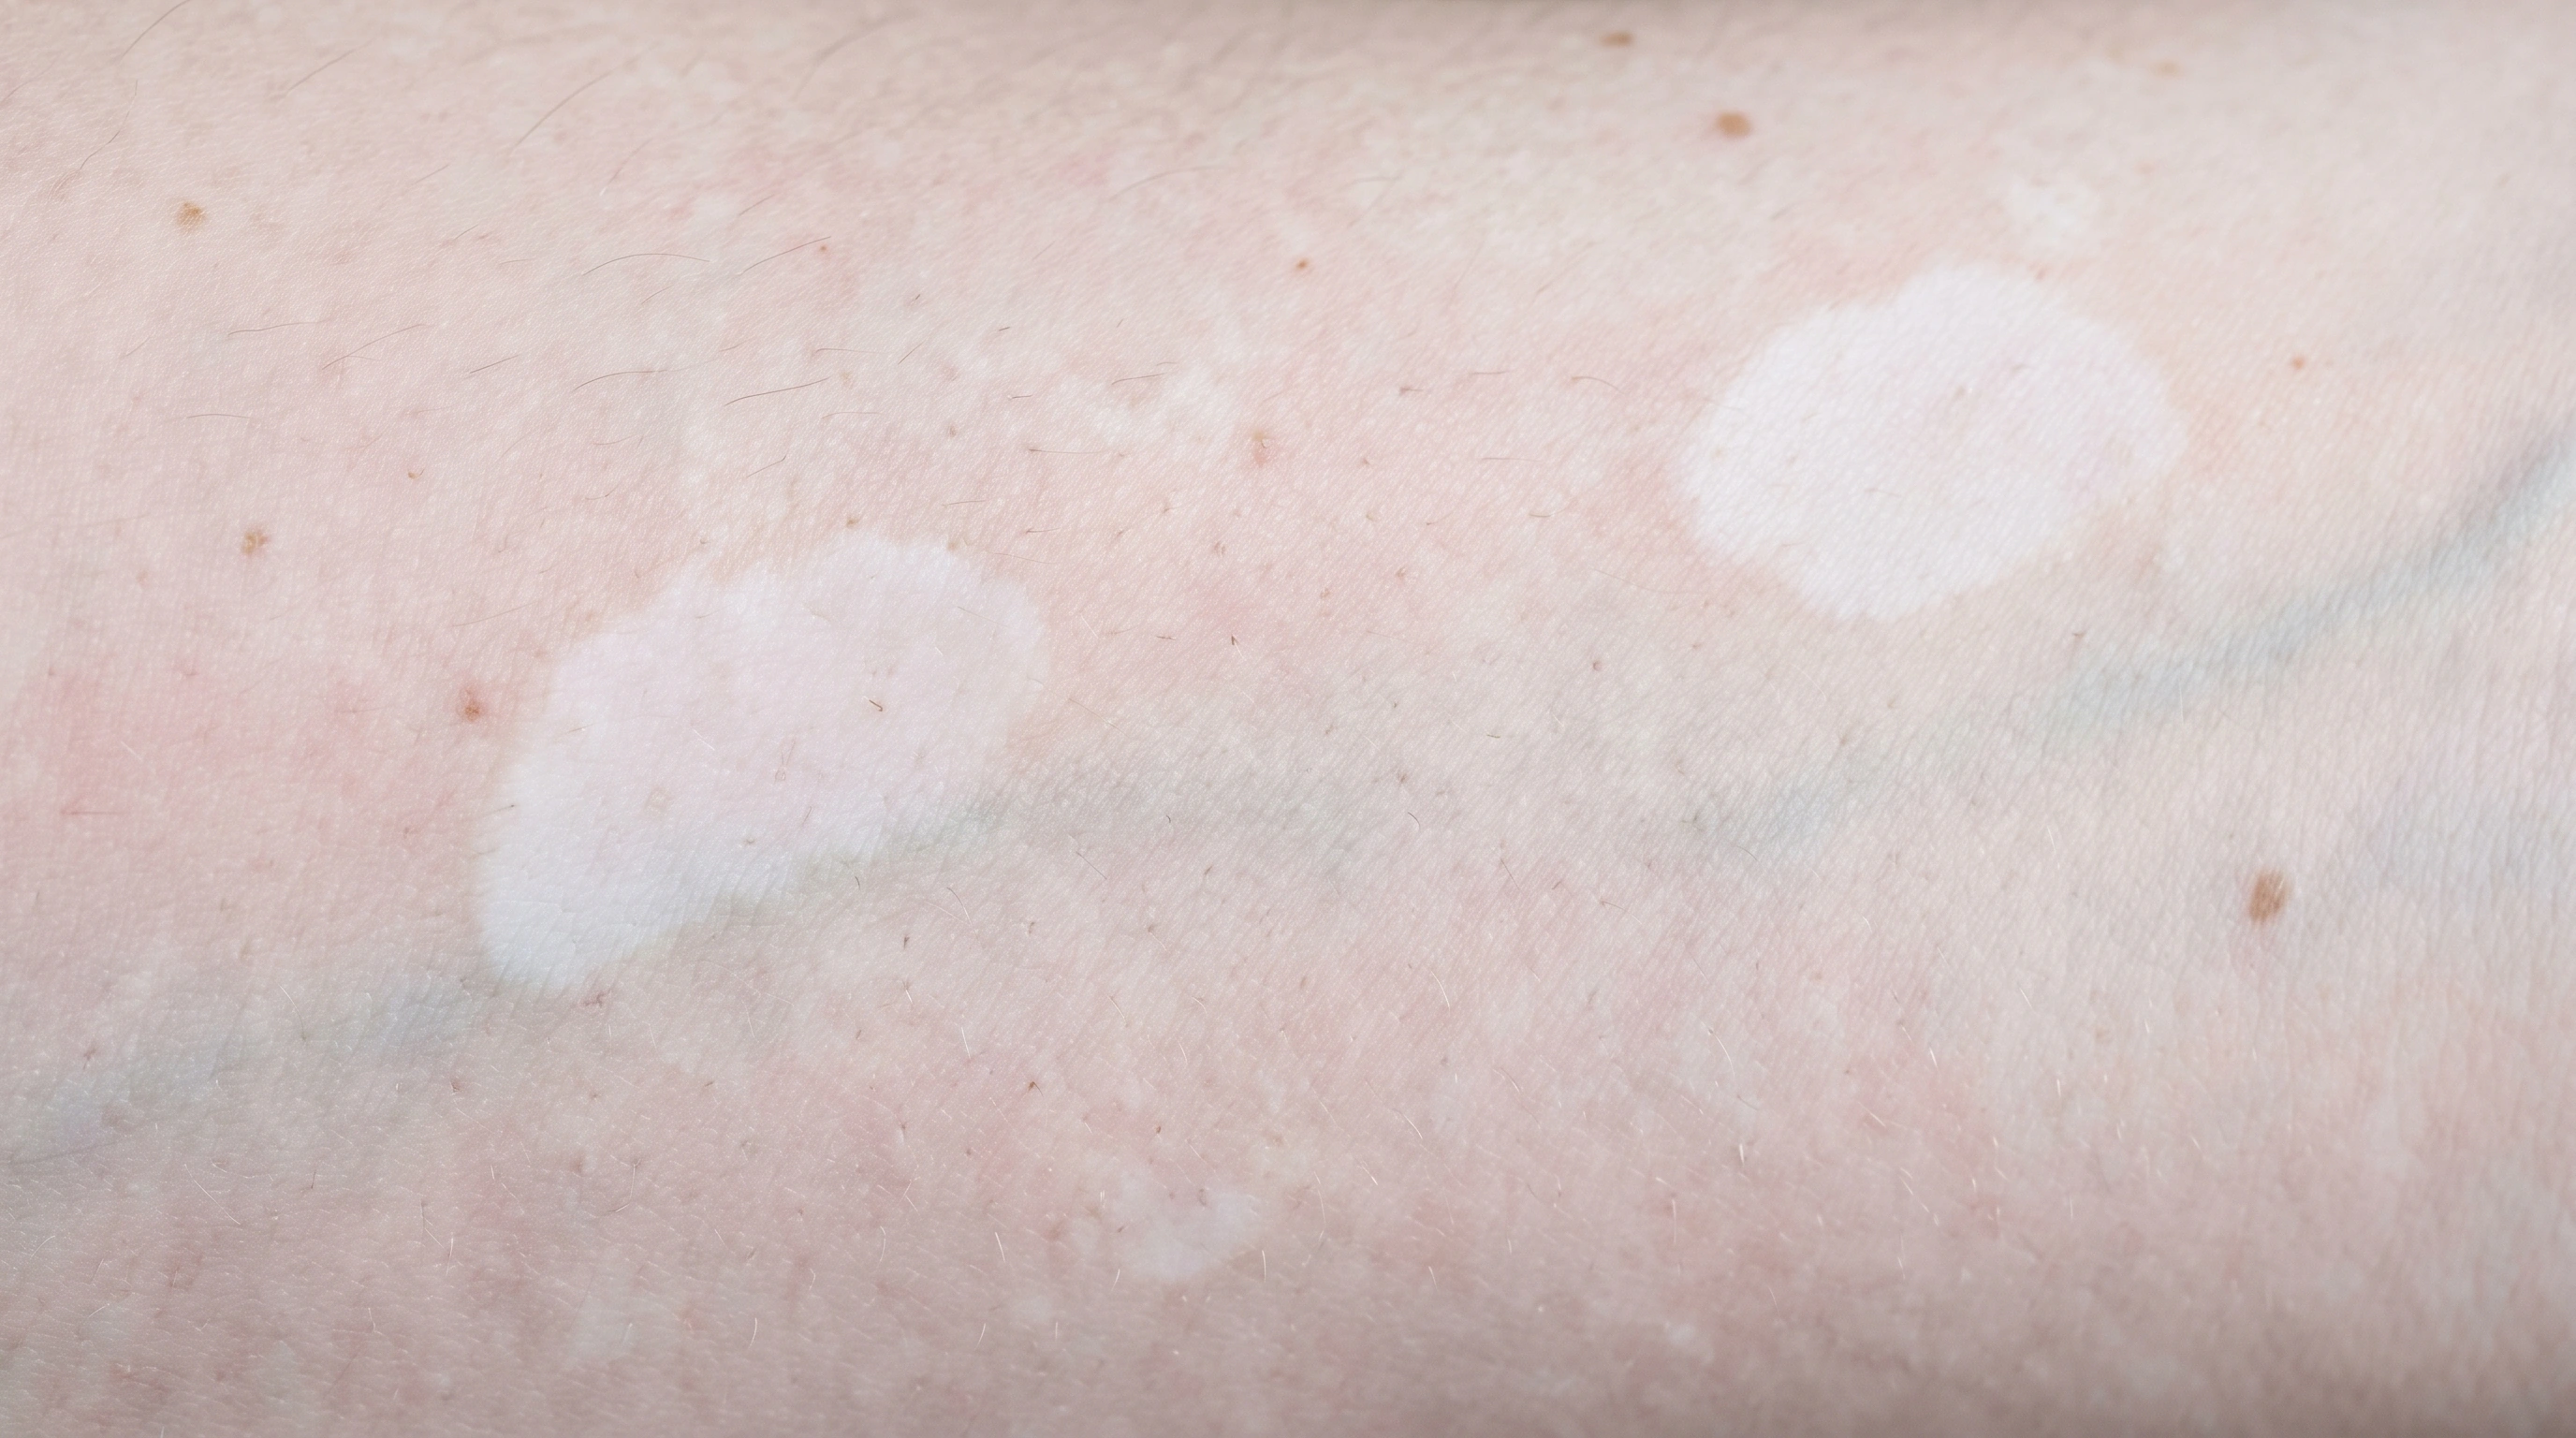

Acts on tyrosinase pathways: Hydroquinone suppresses melanin synthesis. Targets excess pigmentation: Appropriate use and monitoring matter.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.

Affects plasmin-related signaling: May reduce signals that stimulate pigment production. May help uneven pigmentation: Delivery and the formula influence topical results.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.
Built from where each one usually sits in a routine. Introduce one at a time.
4% is a common clinician-directed hydroquinone strength. In the U.S., hydroquinone skin-lightening products are not legally marketed over the counter; higher compounded strengths are not routine starting points.
4%
Clinician-directed strength
Used in melasma treatment and in the approved combination TRI-LUMA. Treatment length and the complete formula require medical guidance.
Choosing a strength: Get a diagnosis and a treatment plan for the pigmented area rather than choosing solely by concentration.
Higher strengths: More is not automatically better. Irritation and blue-black discoloration called ochronosis are important risks, especially with inappropriate or prolonged use.
Formula matters: Single-ingredient creams, compounded blends and TRI-LUMA are different products. A combination containing a steroid or retinoid needs its own instructions.
Topical tranexamic acid studies have used different delivery systems, including 1.8% liposomal lotion and 5% creams or solutions. Oral treatment and procedure-assisted delivery are separate medical decisions.
1.8%
5%
Studied liposomal lotion
One melasma trial tested this delivery system. Its percentage cannot be directly compared with an ordinary serum.
Studied topical formulas
Several melasma studies used topical formulas at this strength. Evidence does not establish one best concentration for all pigment concerns.
Choosing a strength: Look for evidence on the finished topical product. Do not use injectable or oral products as DIY skincare.
Higher strengths: A stronger topical percentage has not been shown to guarantee better results. Oral use requires separate evaluation of risks, including clotting risk.
Formula matters: Liposomal delivery, other brightening ingredients and procedures can change the treatment. A microneedling study is not evidence for the same result from a home serum.
Approximate windows, not promises.
First few weeksAssess tolerance first; pigment change is usually slower.
First few weeksAssess tolerance first; pigment change is usually slower.
4–8 weeksSome studied regimens begin showing pigment improvement.
4–8 weeksSome studied regimens begin showing pigment improvement.
8–12 weeksA useful review point for benefit and irritation.
8–12 weeksA useful review point for benefit and irritation.
3–6 monthsMany melasma trials assess results over three to four months; recurrence is common.
3–6 monthsMany melasma trials assess results over three to four months; recurrence is common.
6–12 monthsLong-term use depends on the active; follow a monitored plan rather than extending treatment automatically.
6–12 monthsLong-term use depends on the active; follow a monitored plan rather than extending treatment automatically.
Can irritate; prolonged inappropriate use can cause paradoxical darkening (ochronosis).
Can sting or cause redness; do not substitute tablets or injections for a cosmetic product.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.
Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.
Do not use to lighten normal skin broadly or continue through worsening pigmentation. US nonprescription hydroquinone skin-lightening products are not legally marketed.
Do not use a cosmetic product as a substitute for diagnosis of an unexplained, changing or persistent skin problem.
More of it is absorbed through the skin than with most topicals, so it is usually stopped. Azelaic acid is the common substitute. Ask the doctor managing your pregnancy.
Melasma is common in pregnancy, so this comes up constantly. Oral tranexamic acid is not a casual pregnancy decision, and the topical version has little pregnancy-specific data. Ask the doctor managing your pregnancy, since they know your full picture.
On the skin. The finished product delivers hydroquinone in a particular vehicle.
Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Conversion. No activation step is established as necessary for its intended topical role.
Skin response. Suppresses melanin synthesis through tyrosinase-related activity; targeted use and monitoring matter.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
On the skin. The finished product delivers tranexamic acid in a particular vehicle.
Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Conversion. No activation step is established as necessary for its intended topical role.
Skin response. May affect plasmin-related signalling involved in pigmentation; a small molecular size does not guarantee delivery.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
Choose for diagnosed stubborn pigment with professional guidance and a defined review point.
The reviewed active-comparator melasma study was small with substantial attrition. Hydroquinone has broader clinical use, but this comparison does not support indefinite treatment or unsupervised high strengths.
Consider a topical pigment option; the evidence is mixed and formula-specific.
A small vehicle-controlled 5% trial did not show superiority over vehicle. A larger active-comparator study found improvement in both groups but did not prove equivalence to hydroquinone.
Sources