Epidermal Inclusion Cyst vs Pilar Cyst

An epidermoid cyst is a firm lump under the skin, lined with the same cells as the skin surface and slowly filling with keratin. It is harmless and often sits quietly for years. The trouble starts when the wall ruptures, which is why squeezing one is the worst thing you can do to it. A keratin-filled cyst arising from the hair root sheath, usually on the scalp.

Research updated 2026-10-23
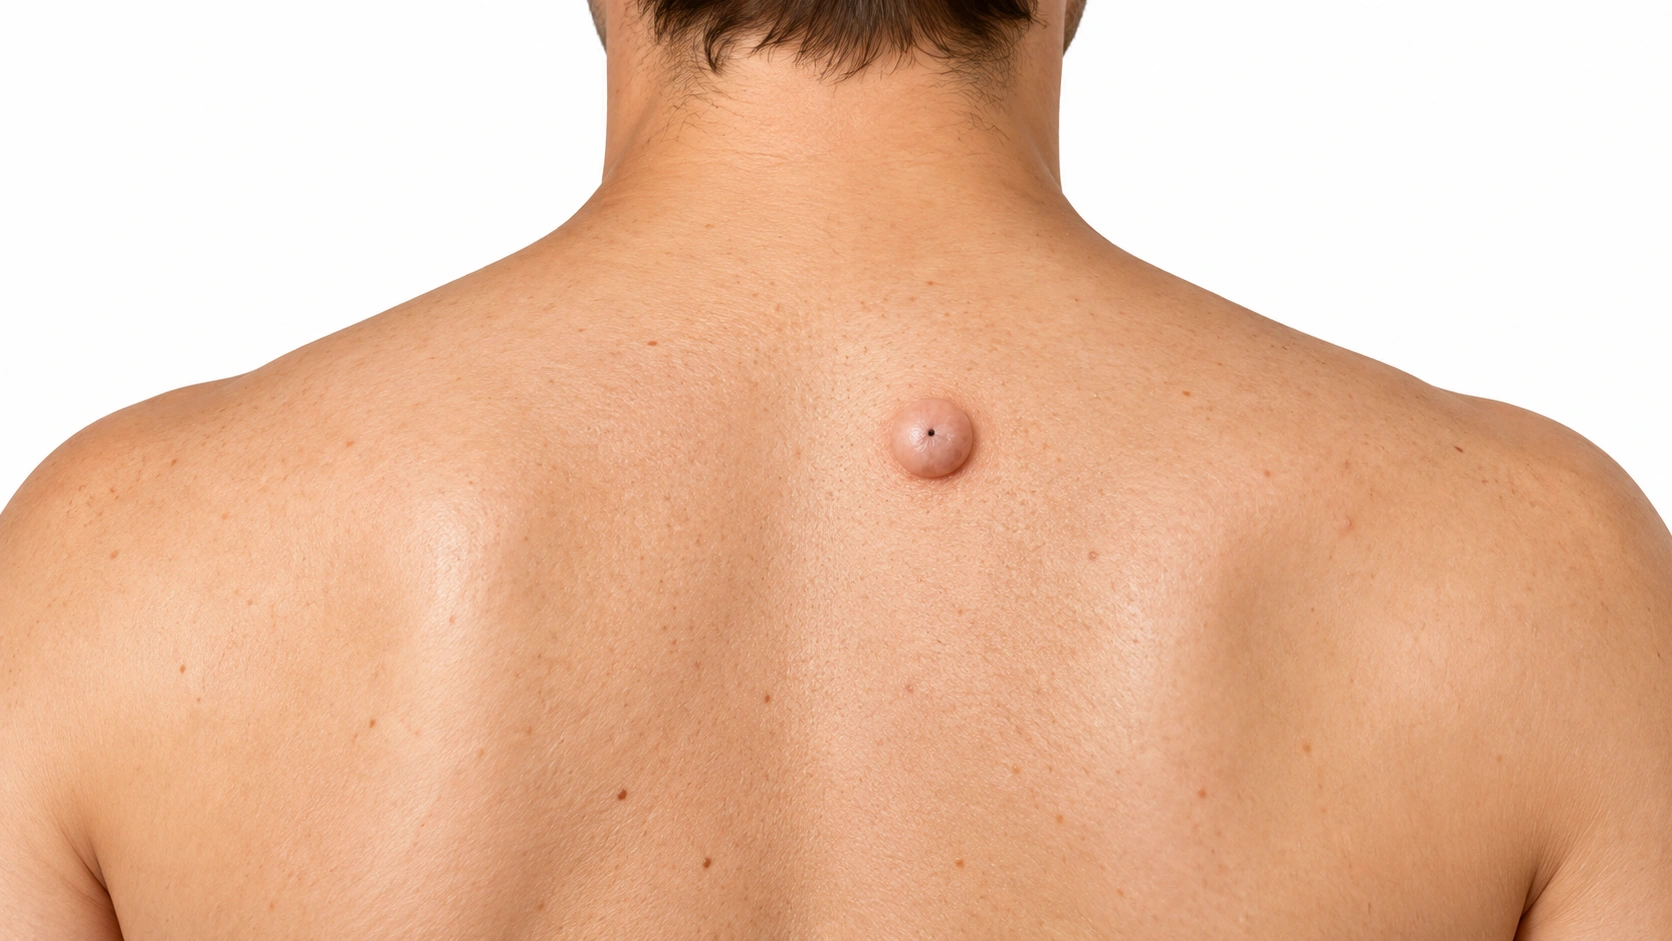
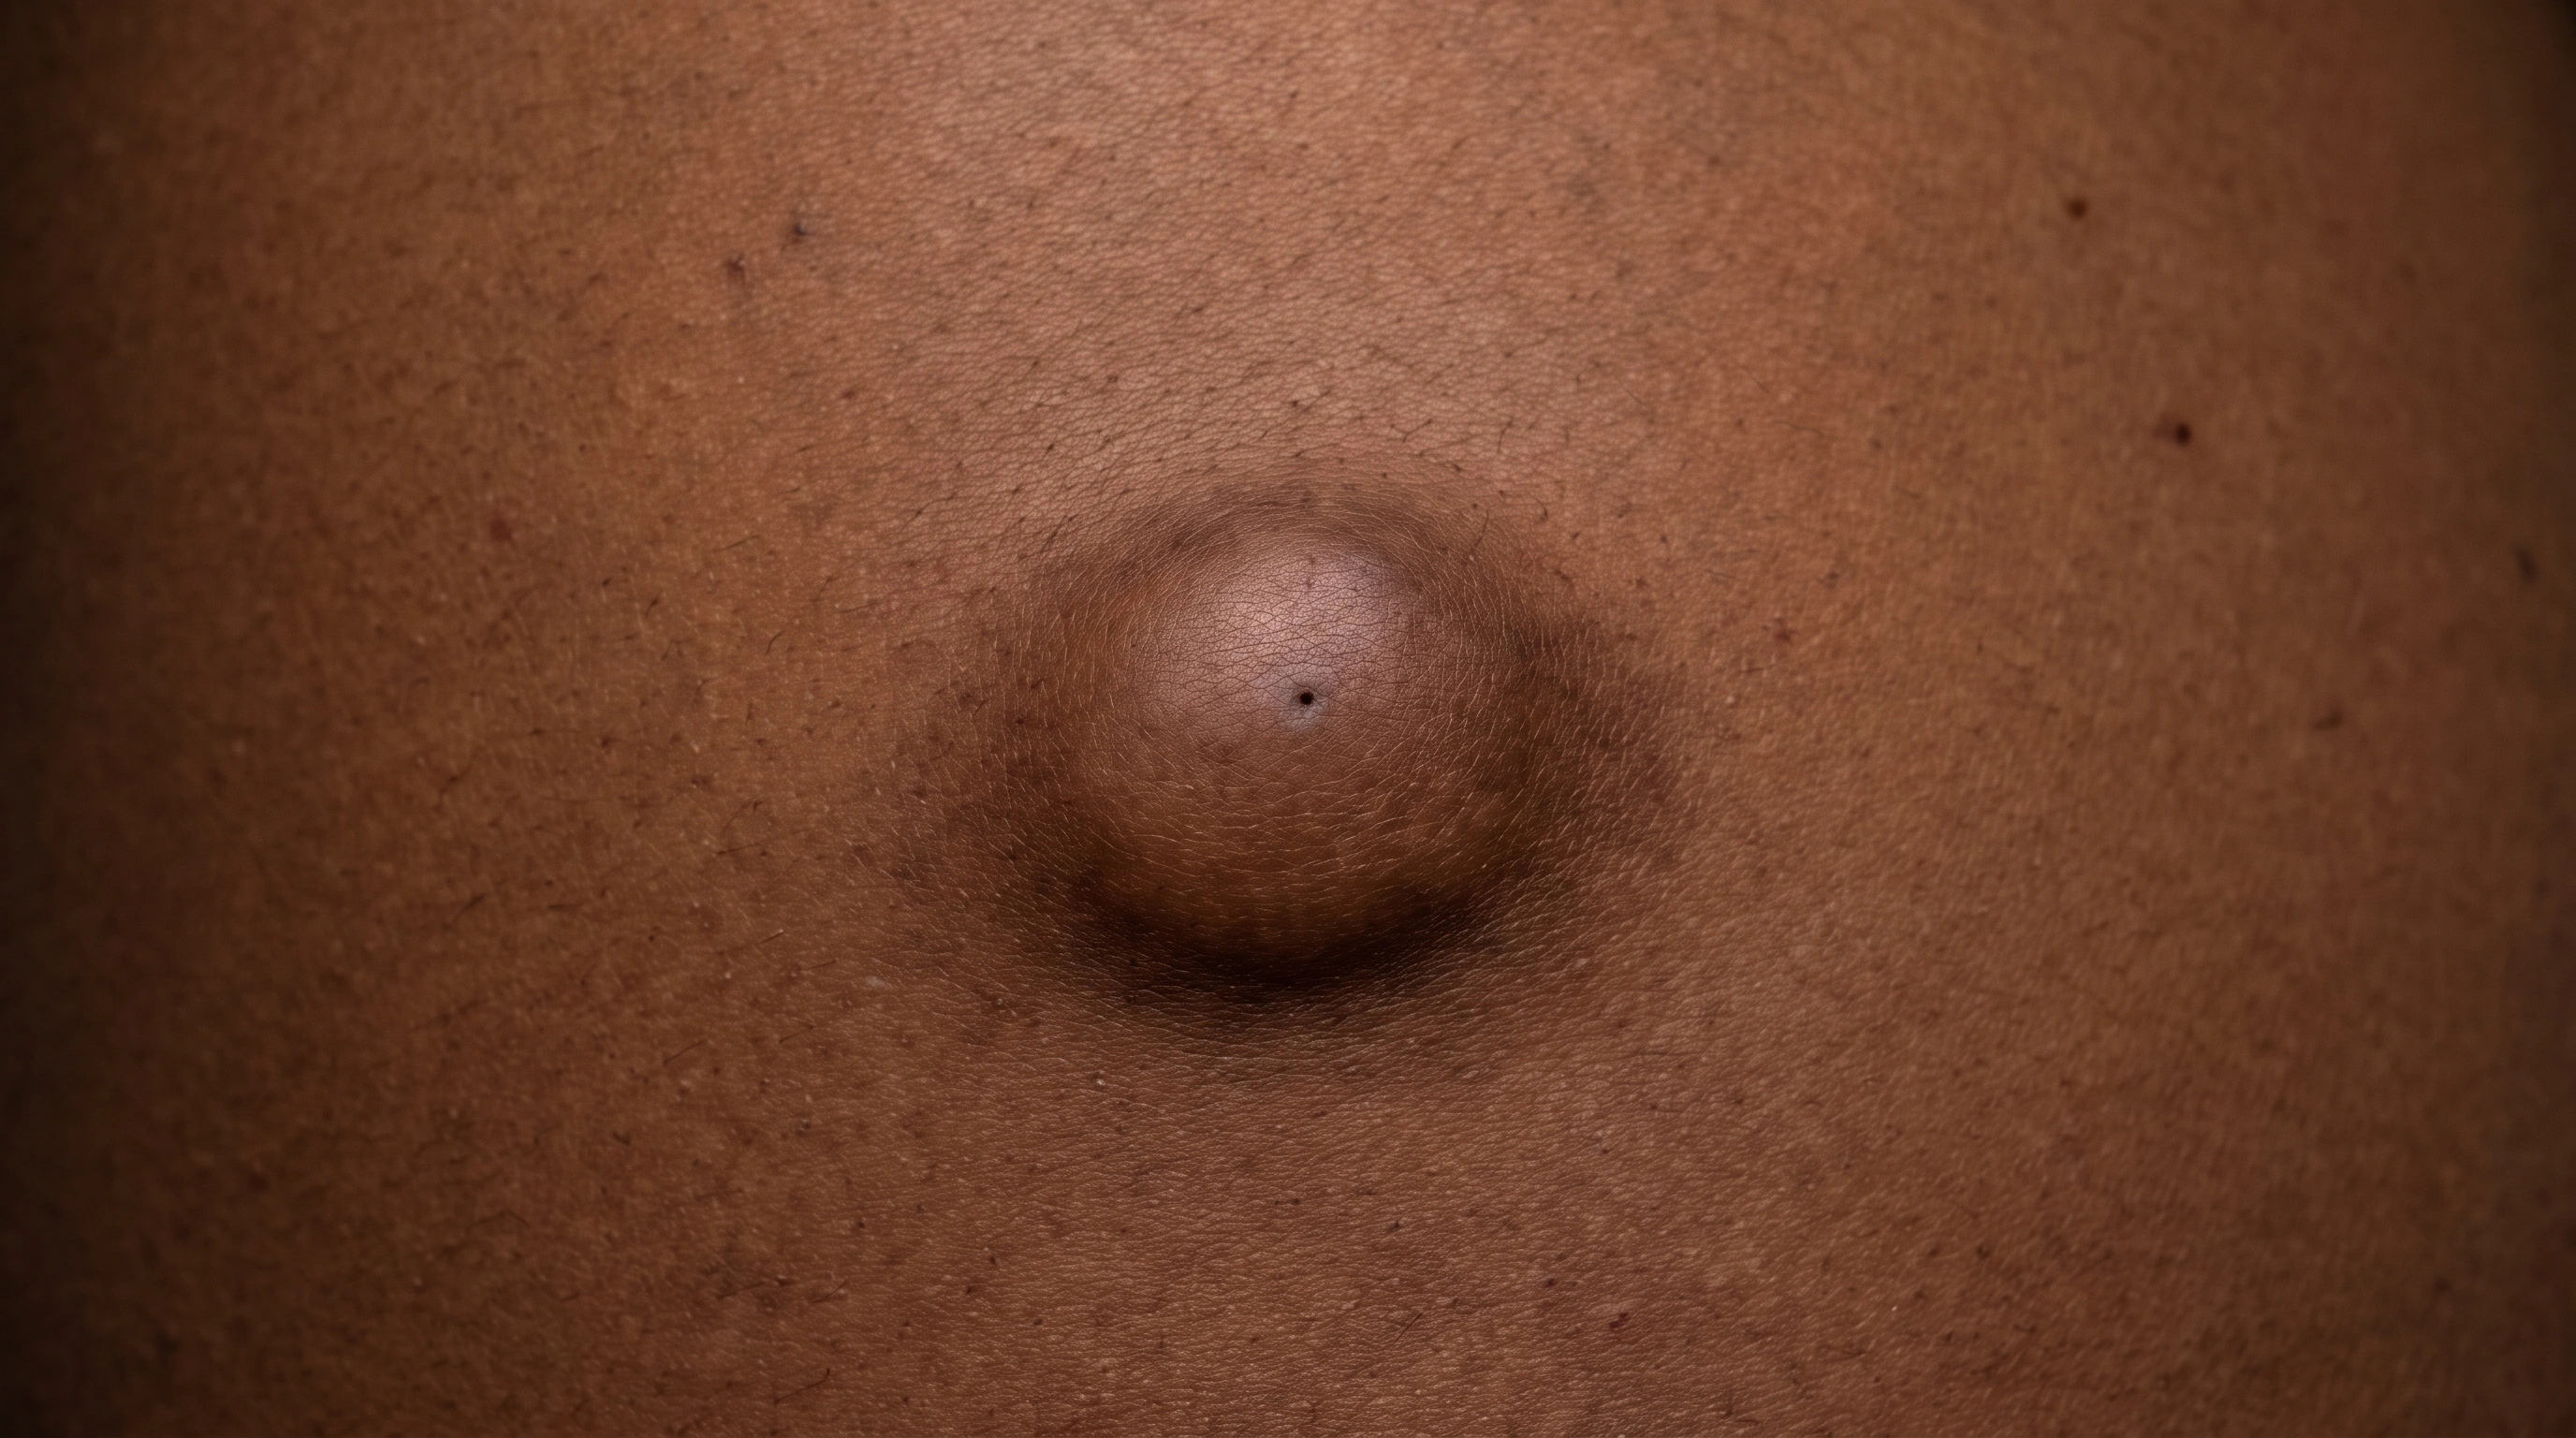
A smooth, dome-shaped lump about two centimetres across on the upper back on pale skin, with a tiny dark pore at its center and faintly pink skin over it.Pilar Cyst

Key differences

The same eight facts on every condition comparison.

Usual age
Adults
Adults
Where
Face, neck, trunk
Scalp
Main sign
Firm, movable lump with a pore
Smooth firm lump
Itch or pain
Painless unless inflamed
Contagious
No
No
Long term
Stays until the sac is removed
Stays until removed
Scars
Removal leaves a scar
No
Who gets it
Adults; more in men
Adults; often runs in families

What is it?

Epidermal Inclusion Cyst
Pilar Cyst
What is it?
  • It is a keratin-filled sac.
    The cyst is a usually benign sac lined by skin-like cells and filled with keratin.
  • It grows slowly.
    It often appears as a slowly growing lump with a central opening.
  • "Sebaceous cyst" is a misnomer.
    It is commonly called a sebaceous cyst, but its contents are not simply trapped oil.
  • Unusual lumps need examining.
    A new, changing, hard, fixed or uncertain lump should be checked rather than assumed to be a cyst.
  • What it is
    A keratin-filled cyst arising from the hair root sheath, usually on the scalp.

What it looks like

Epidermal Inclusion Cyst

Representative image of quiet cyst. It illustrates a visible feature or experience and is not a diagnostic reference.

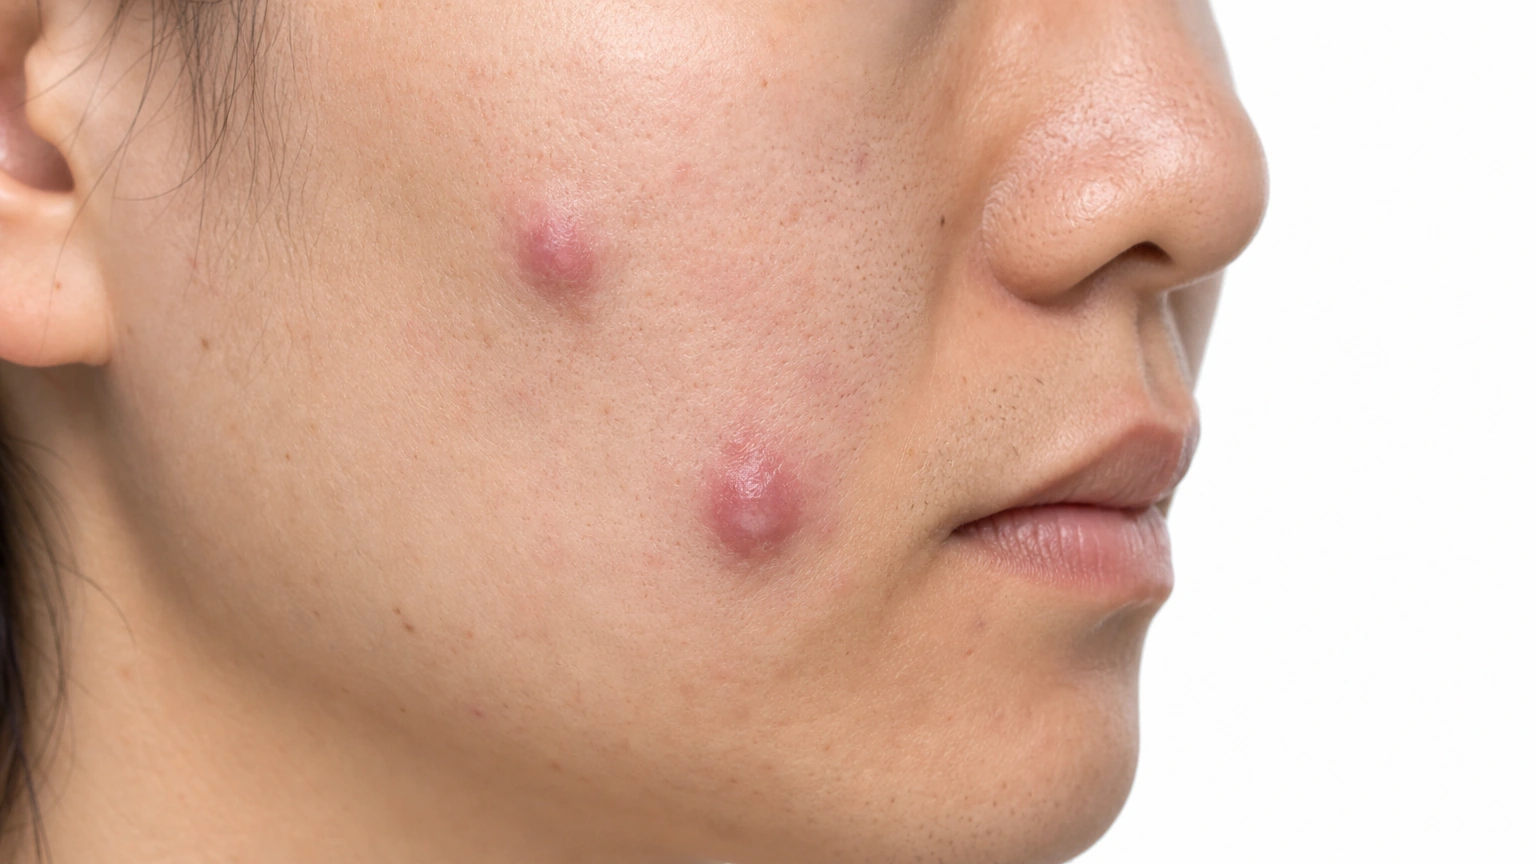
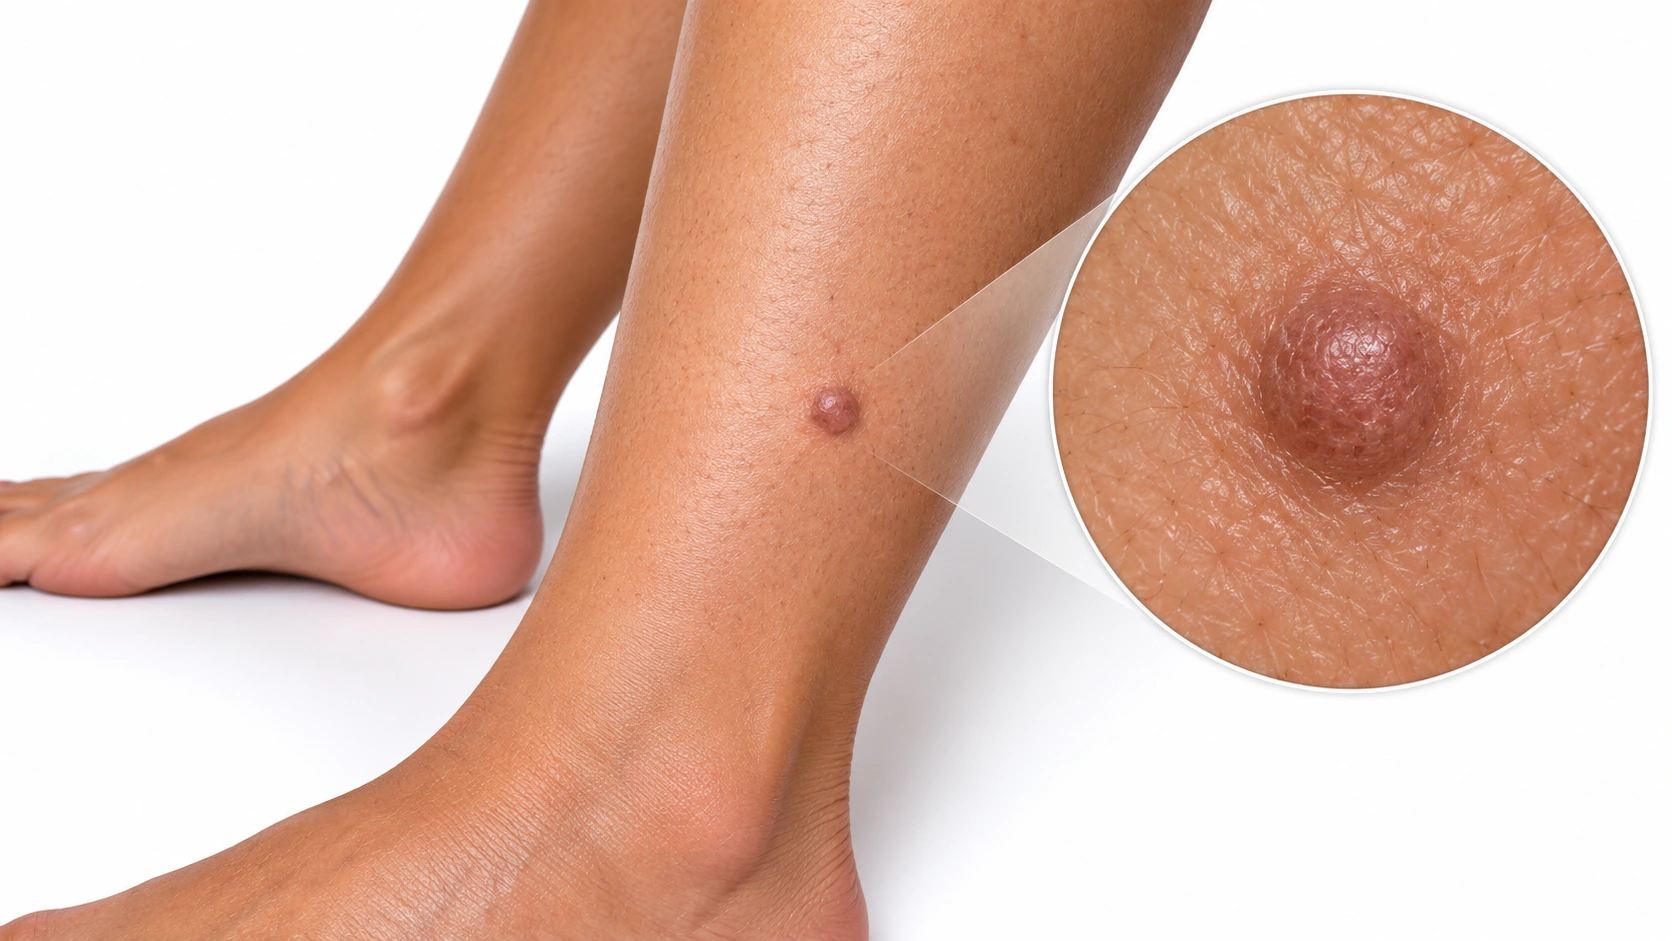
Round lump Smooth and movable under skin.

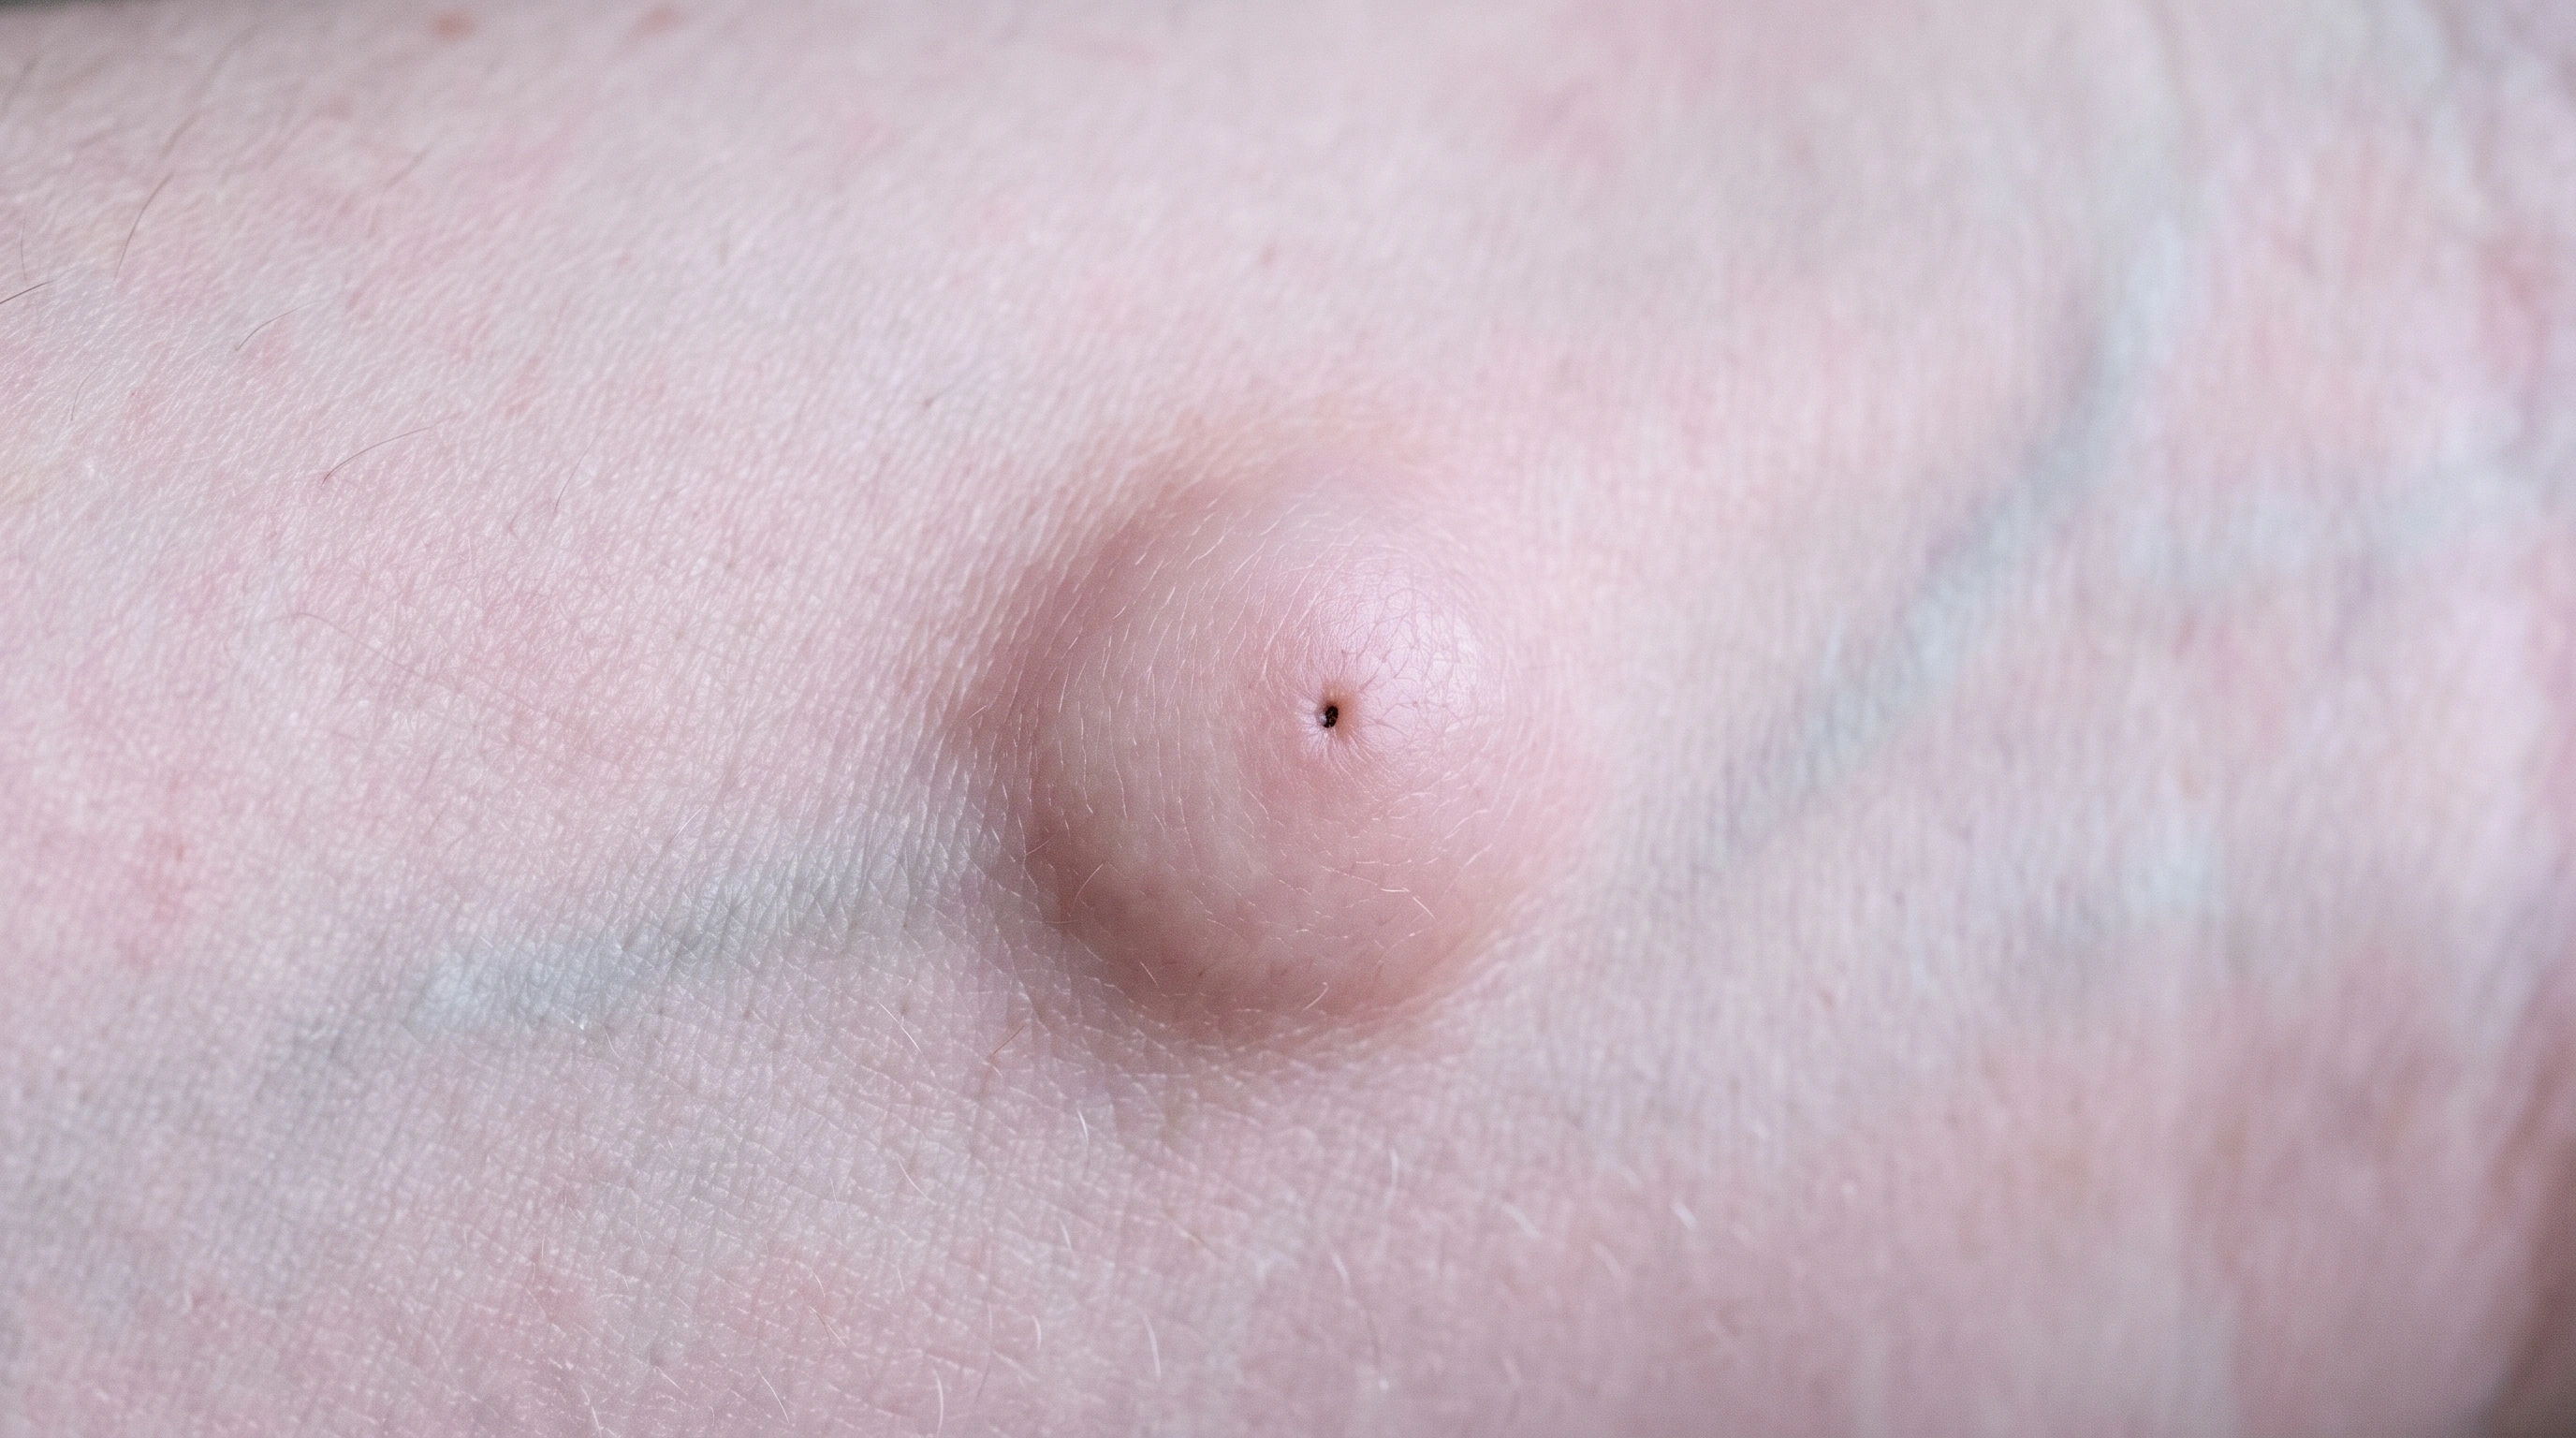
Representative image of cyst punctum. It is not a diagnostic reference or an exact depiction of every subtype, stage or location.

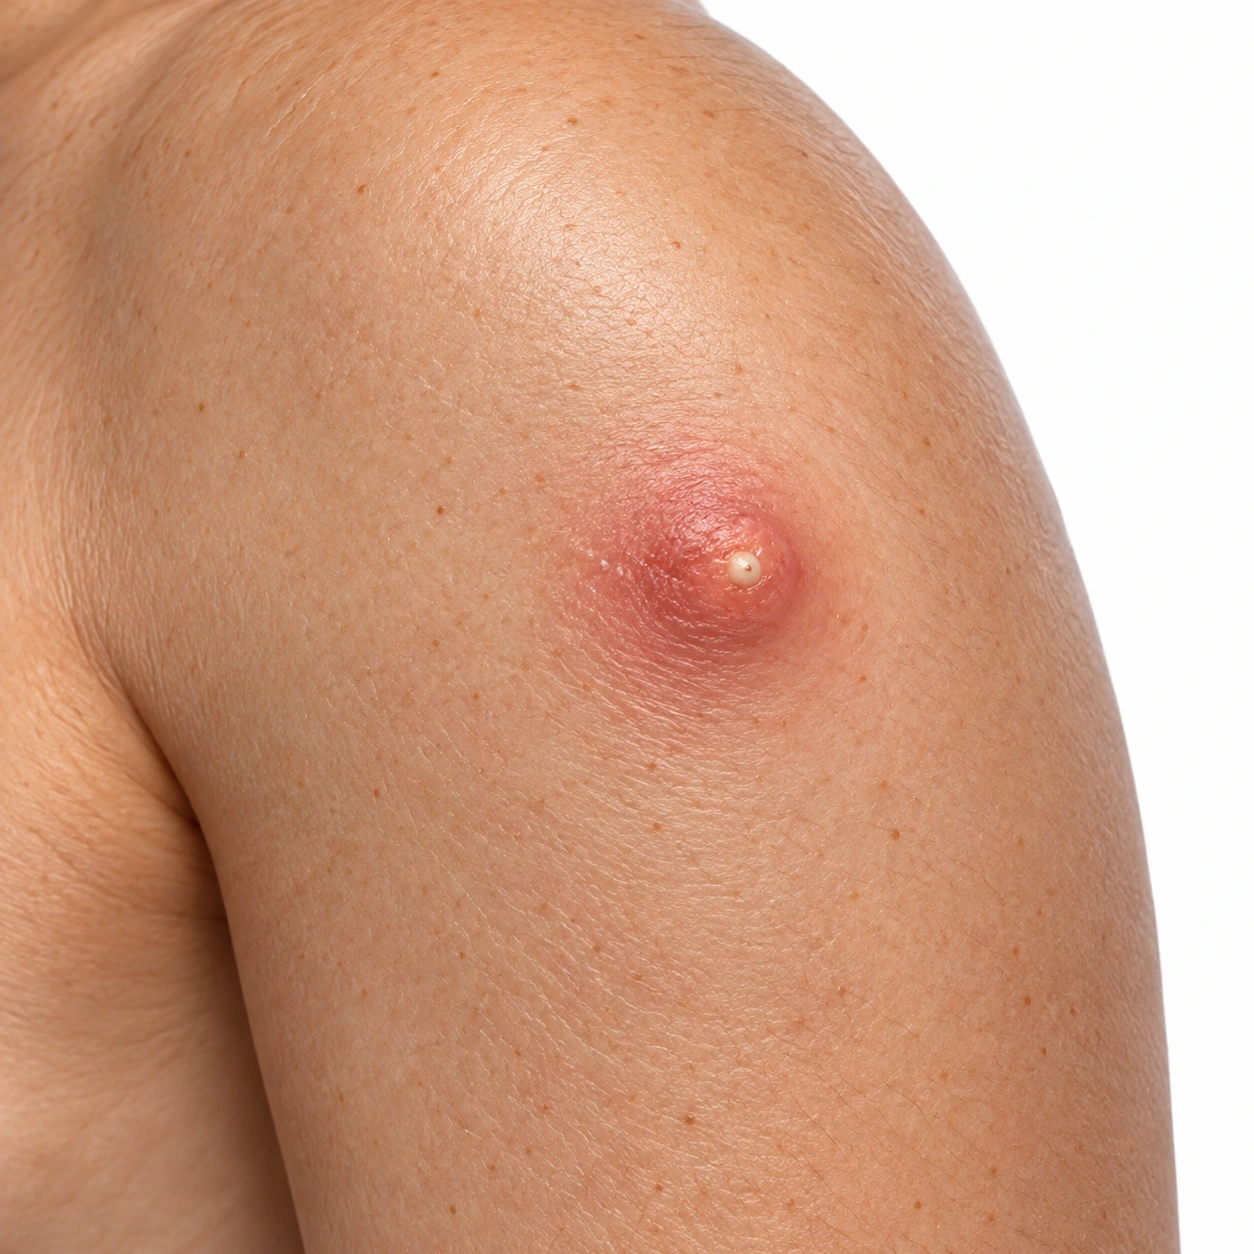
Central opening A small dark pore on top.

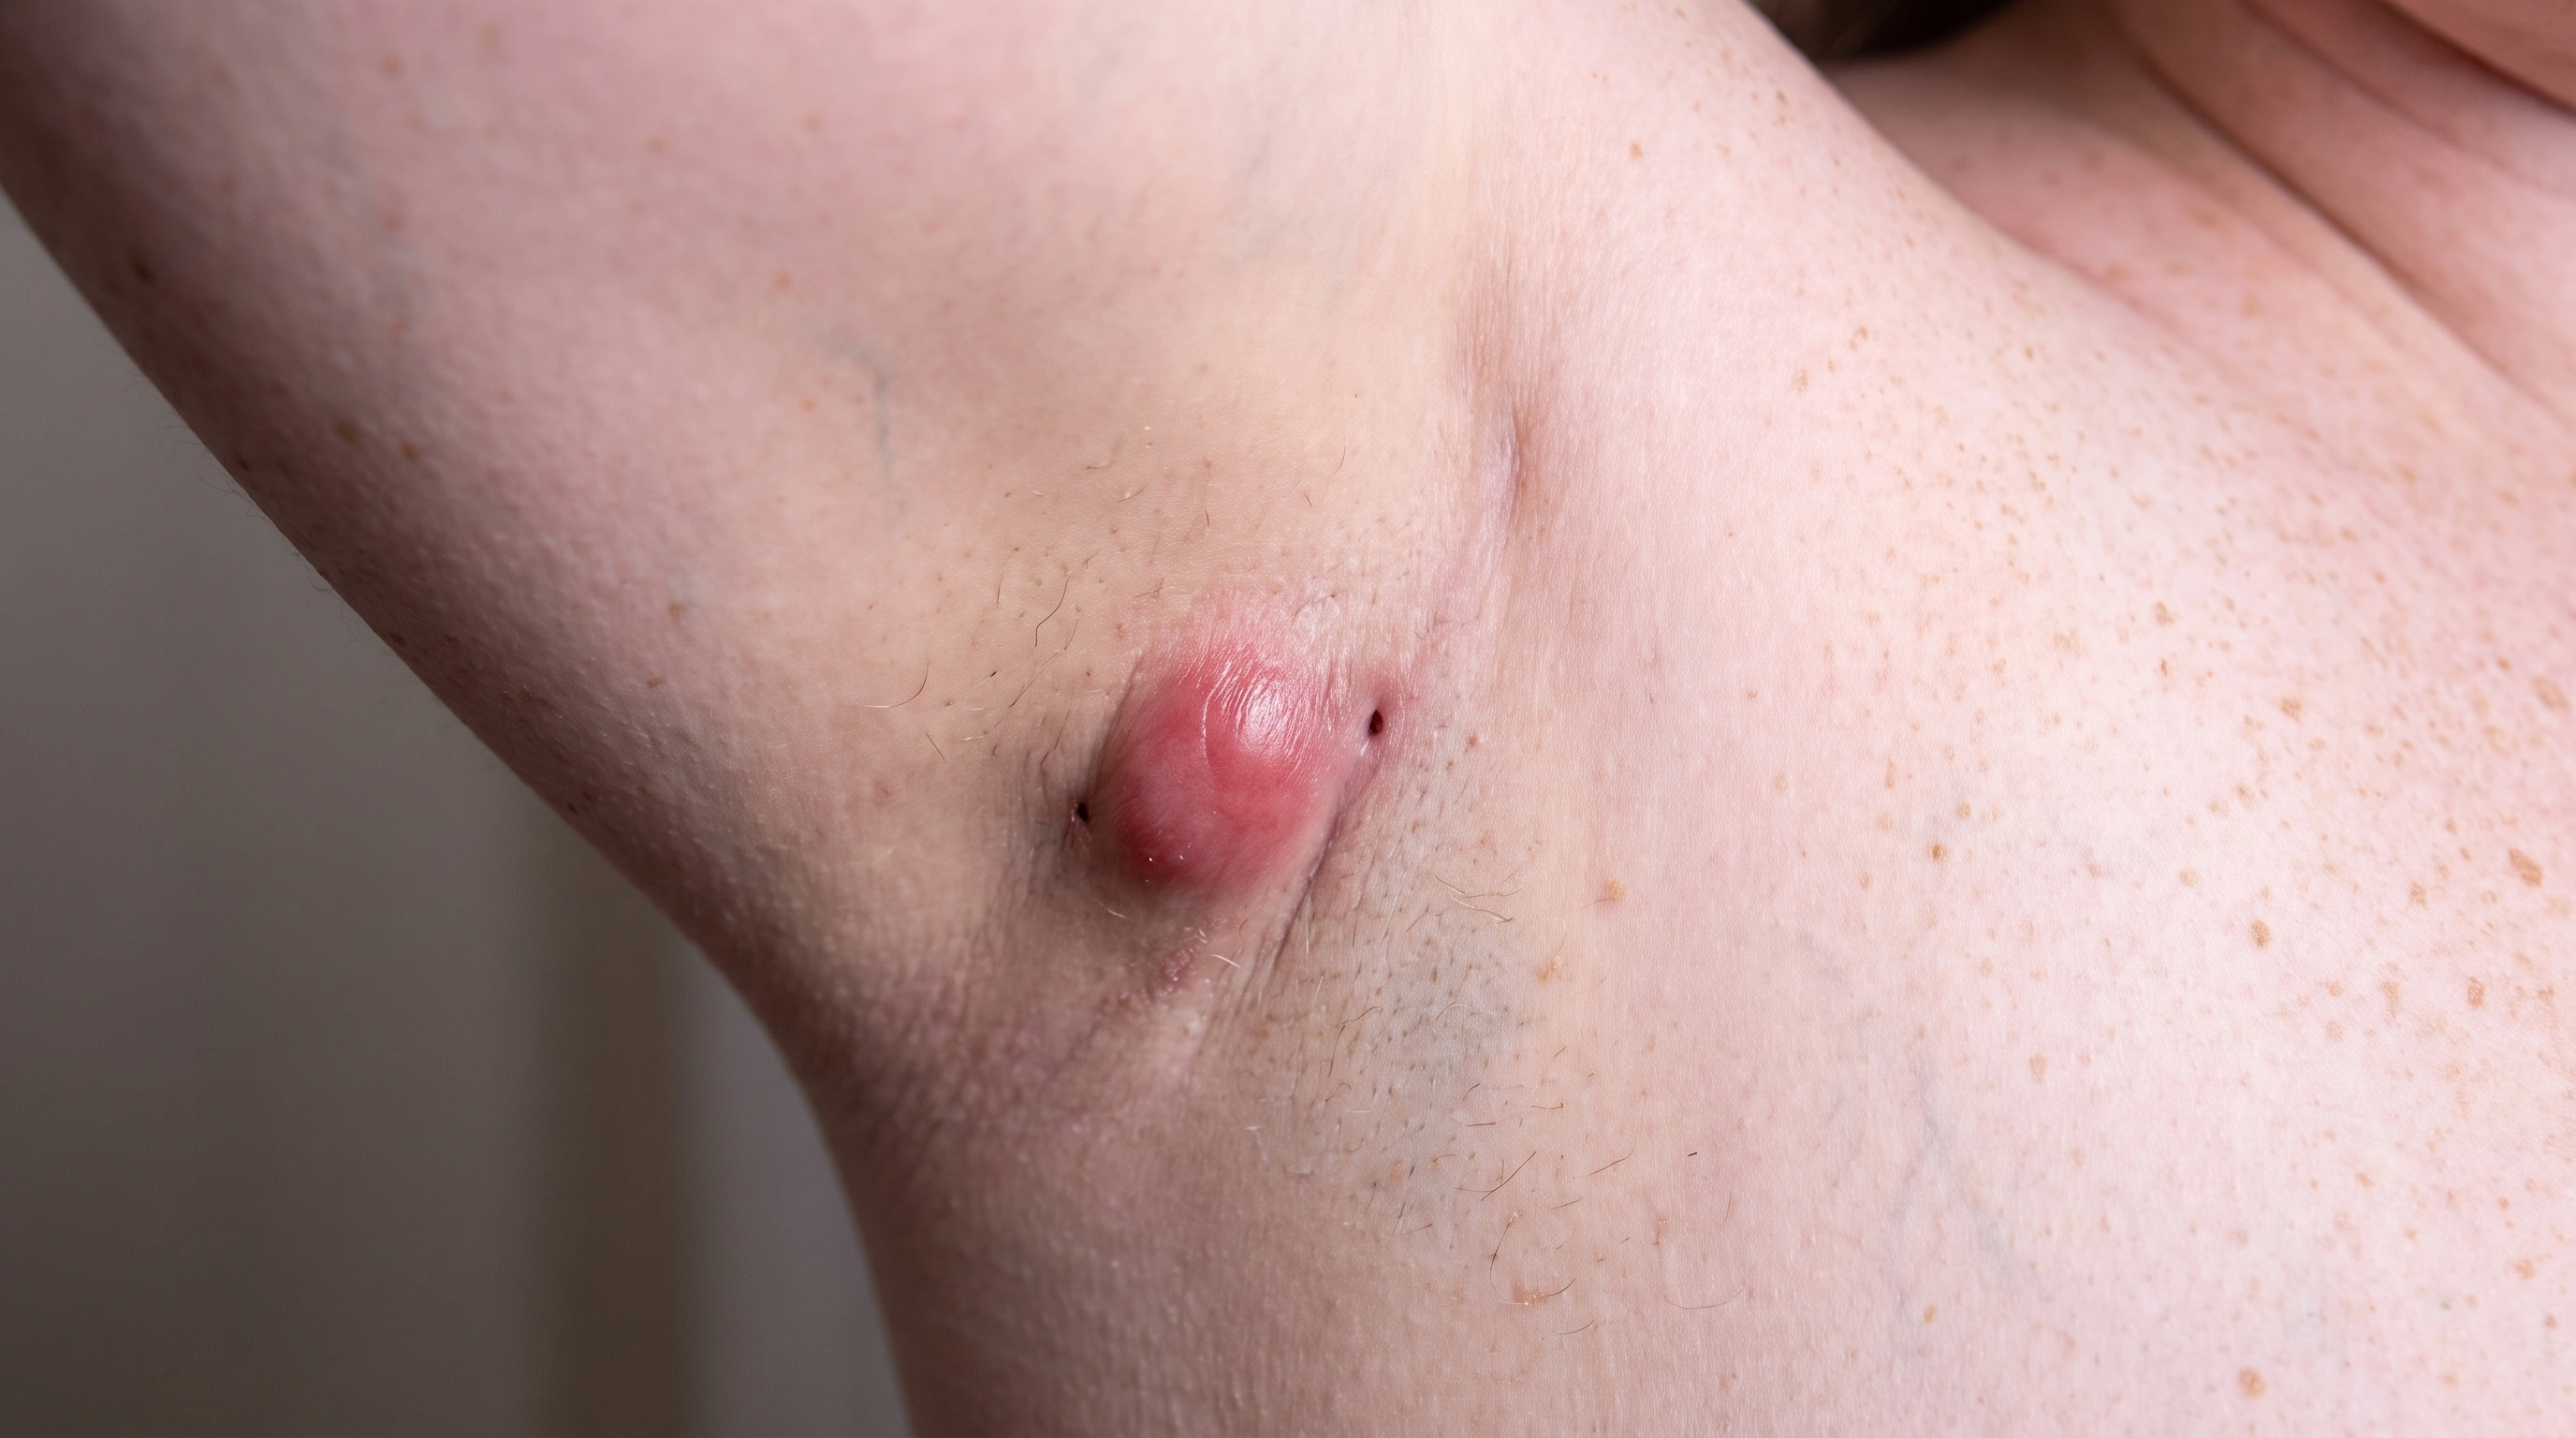
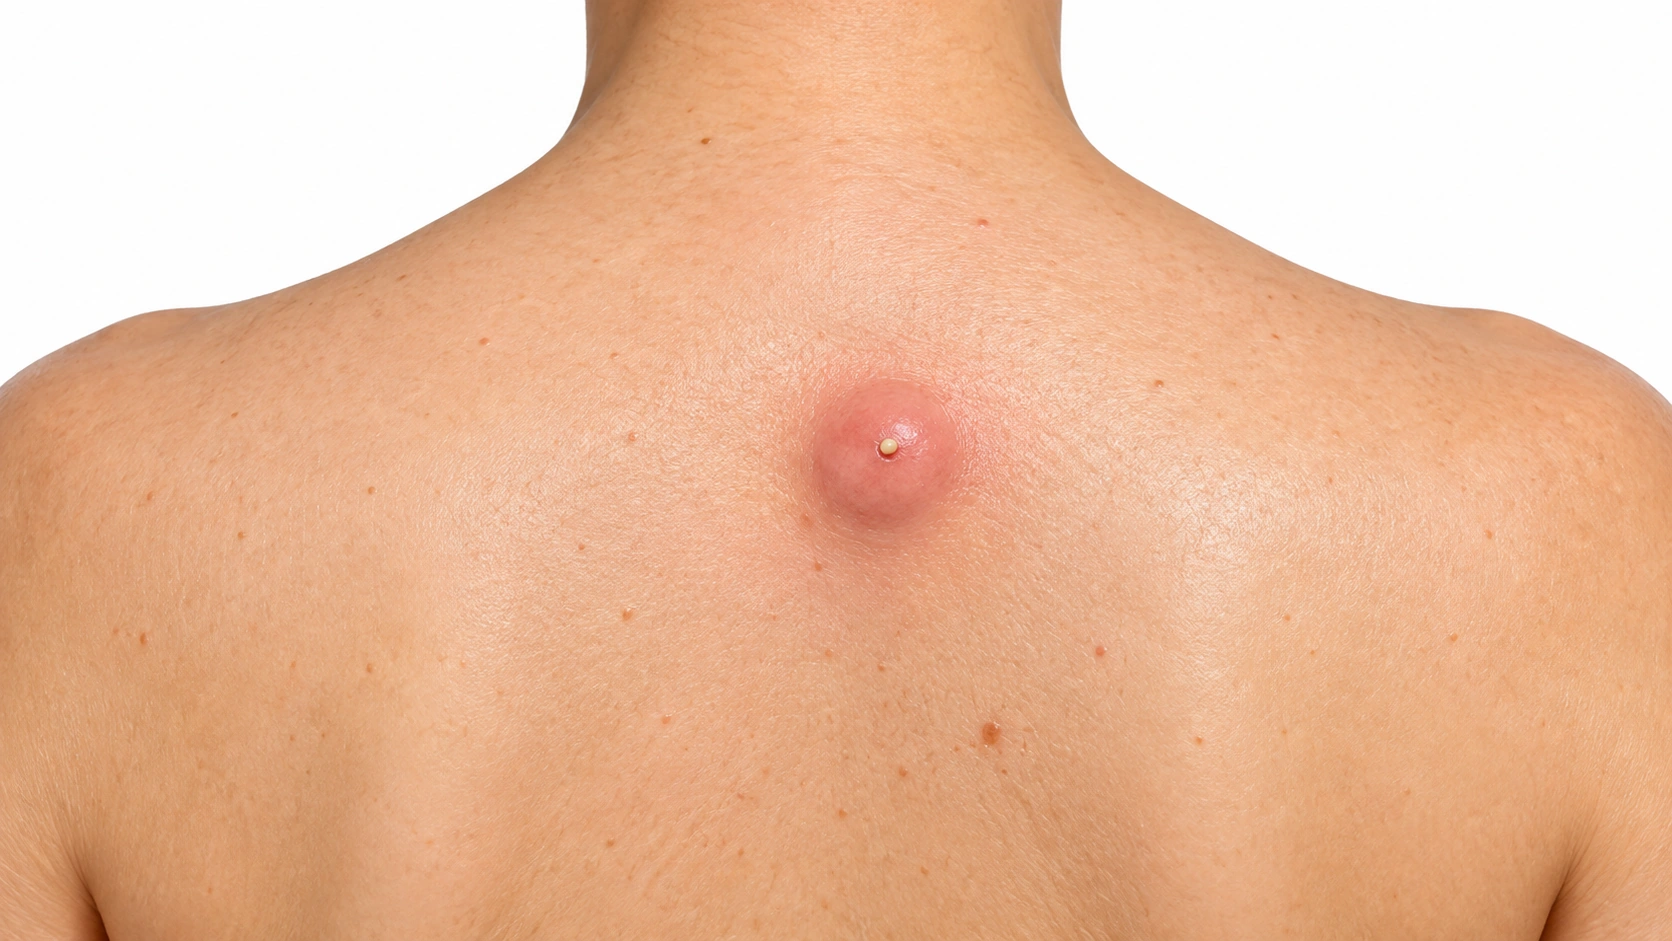
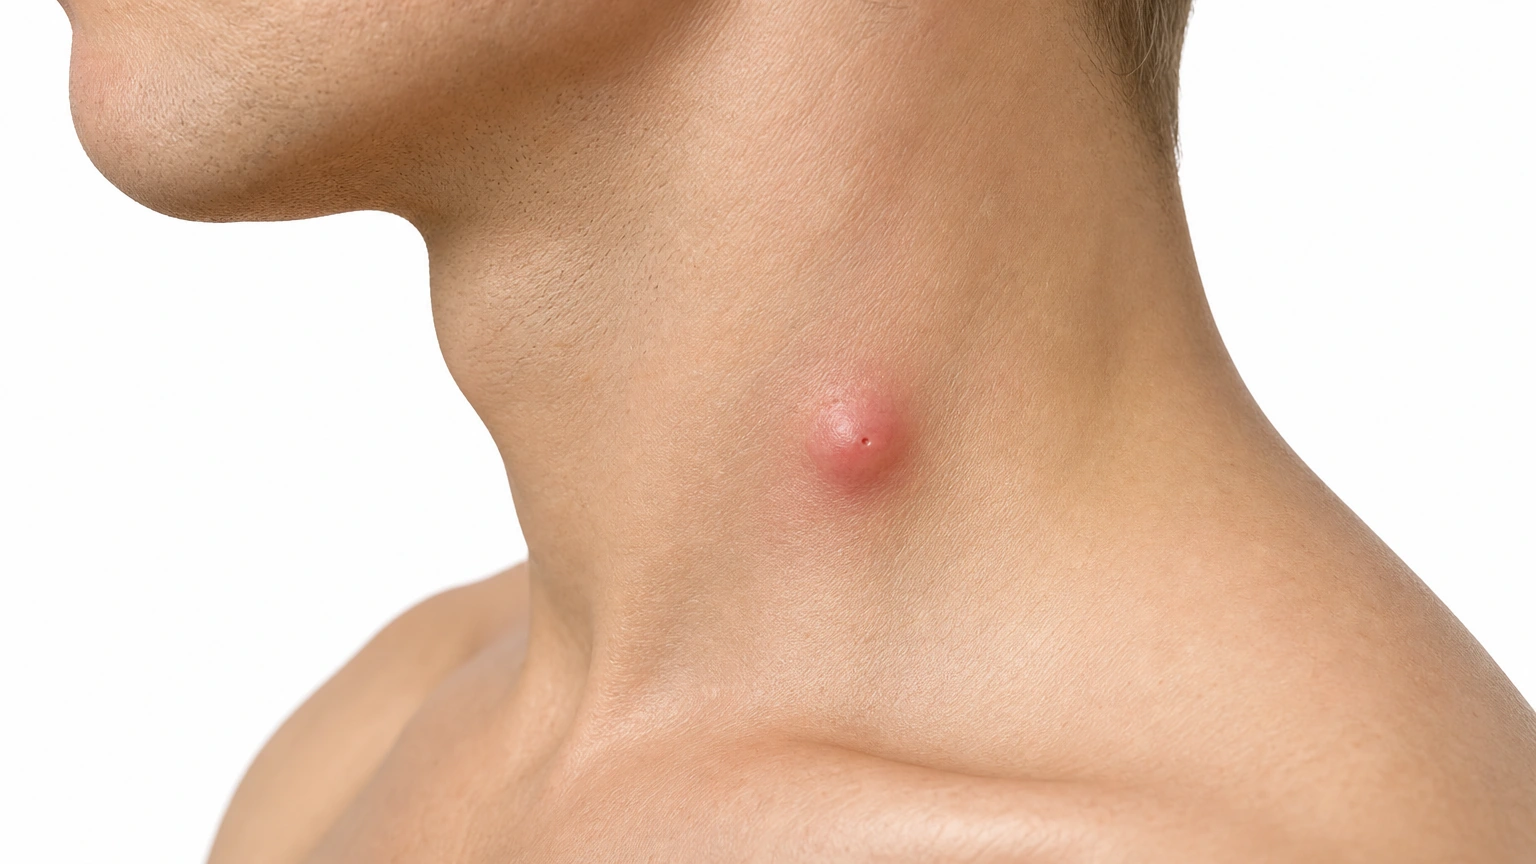
A small red swollen dome-shaped cyst with a tiny central punctum on the side of the neck.

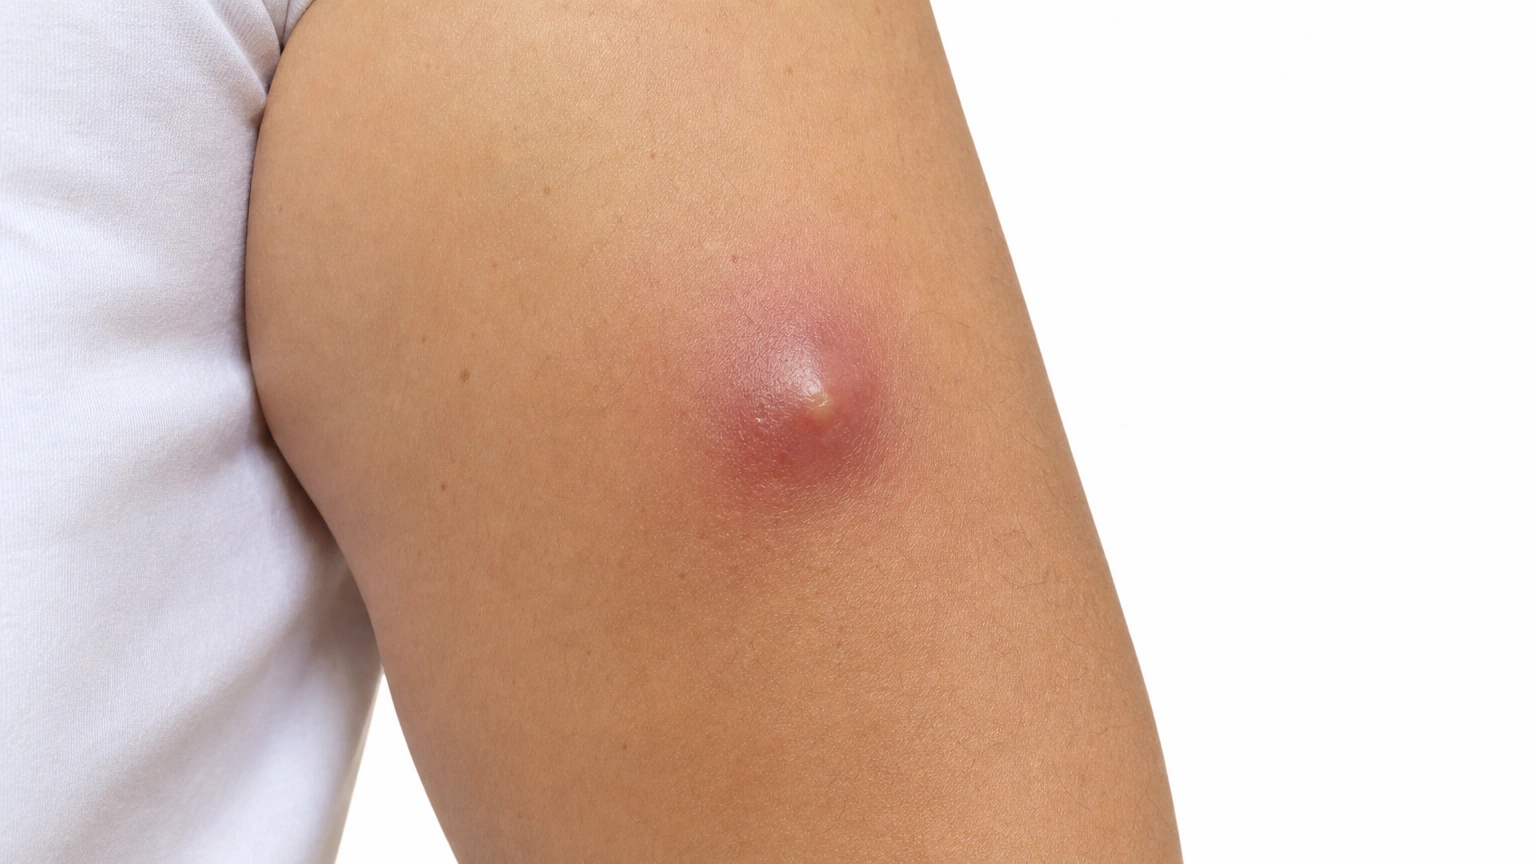
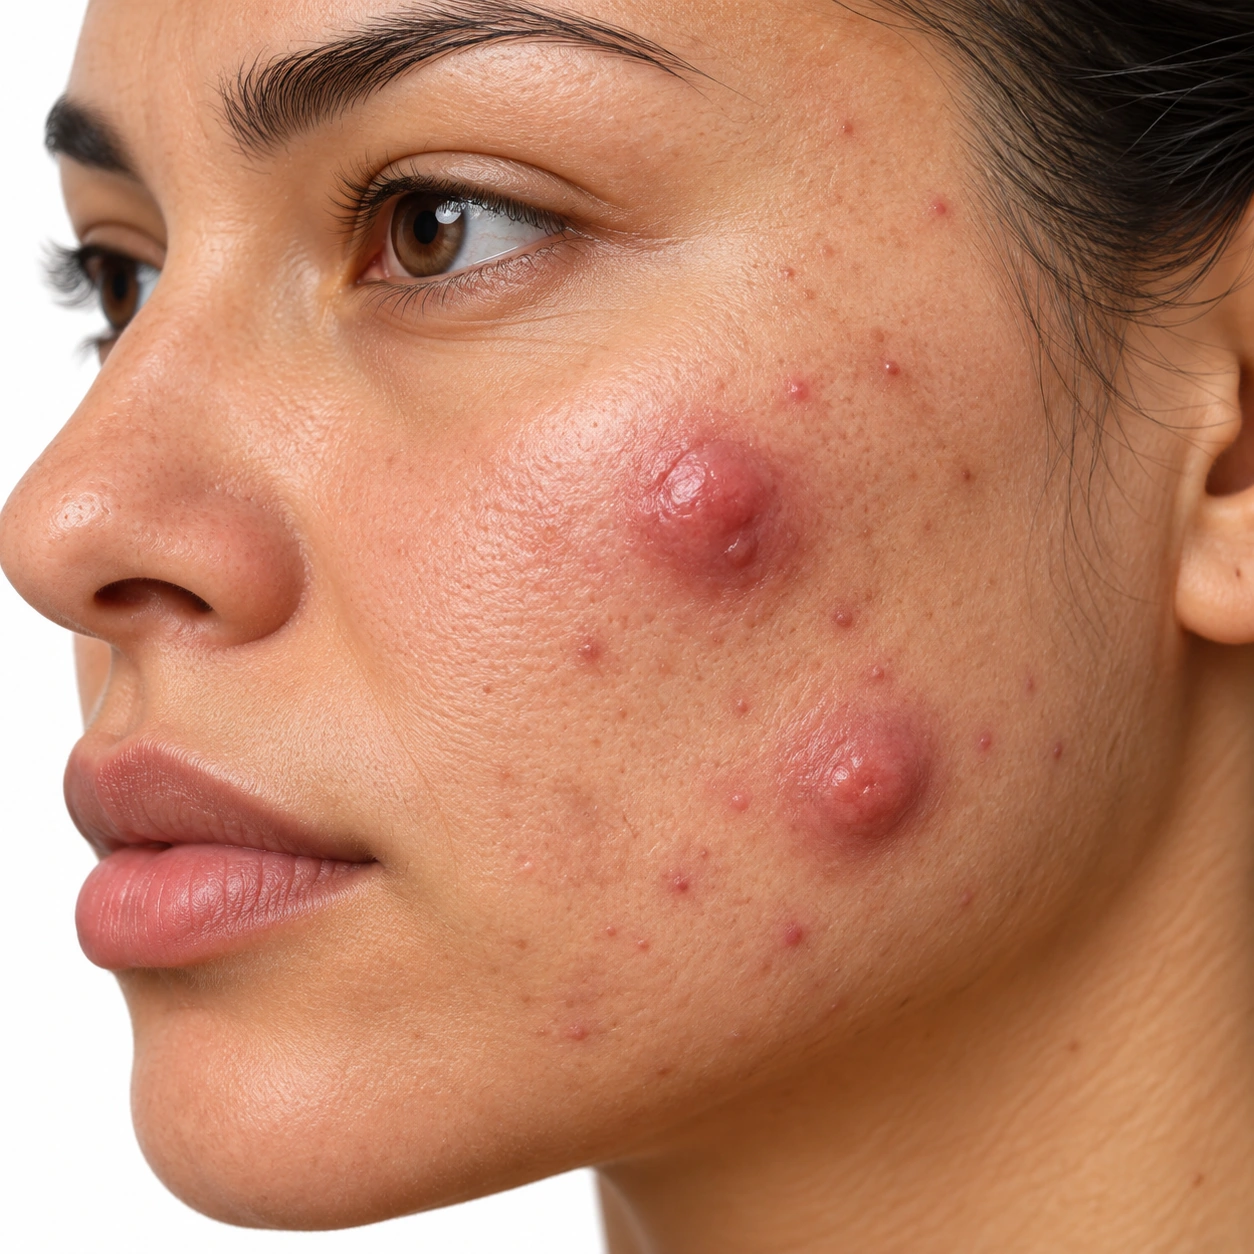
Inflamed cyst Red, swollen and tender.

Pilar Cyst

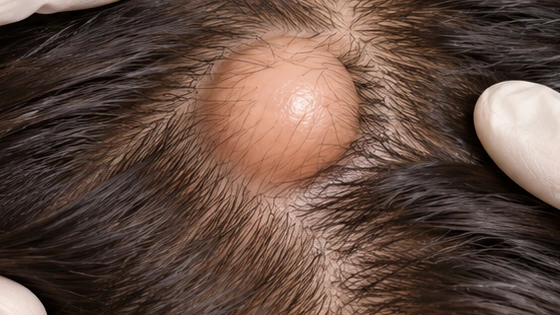
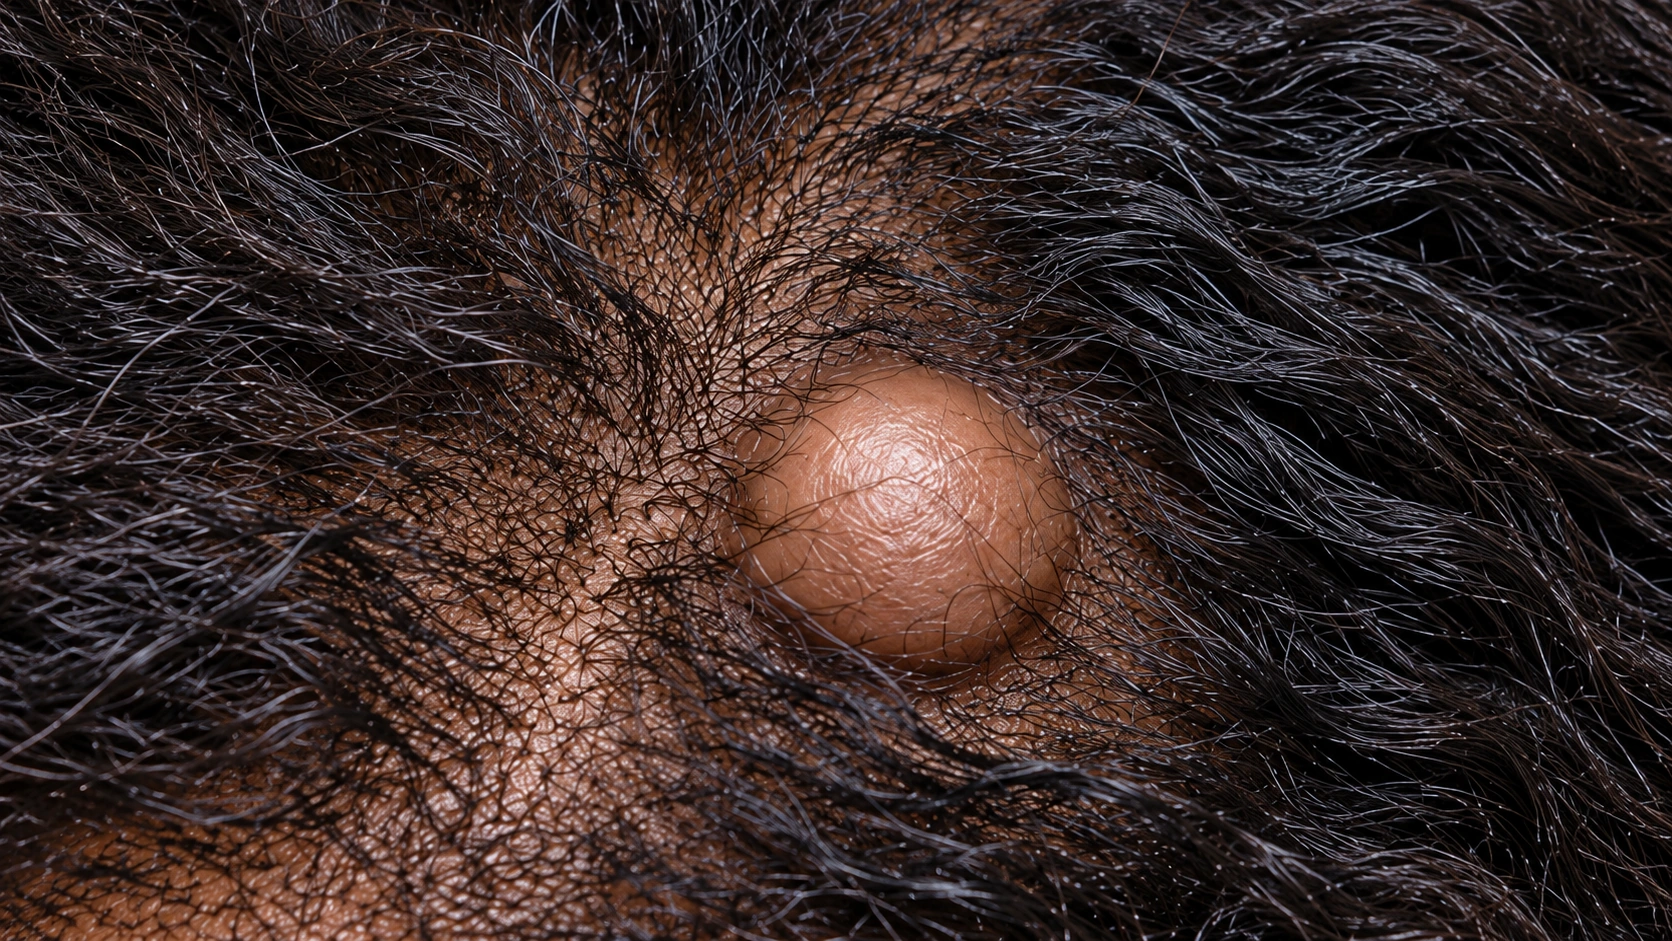
Gloved hands parting hair around a rounded skin-colored scalp lump.

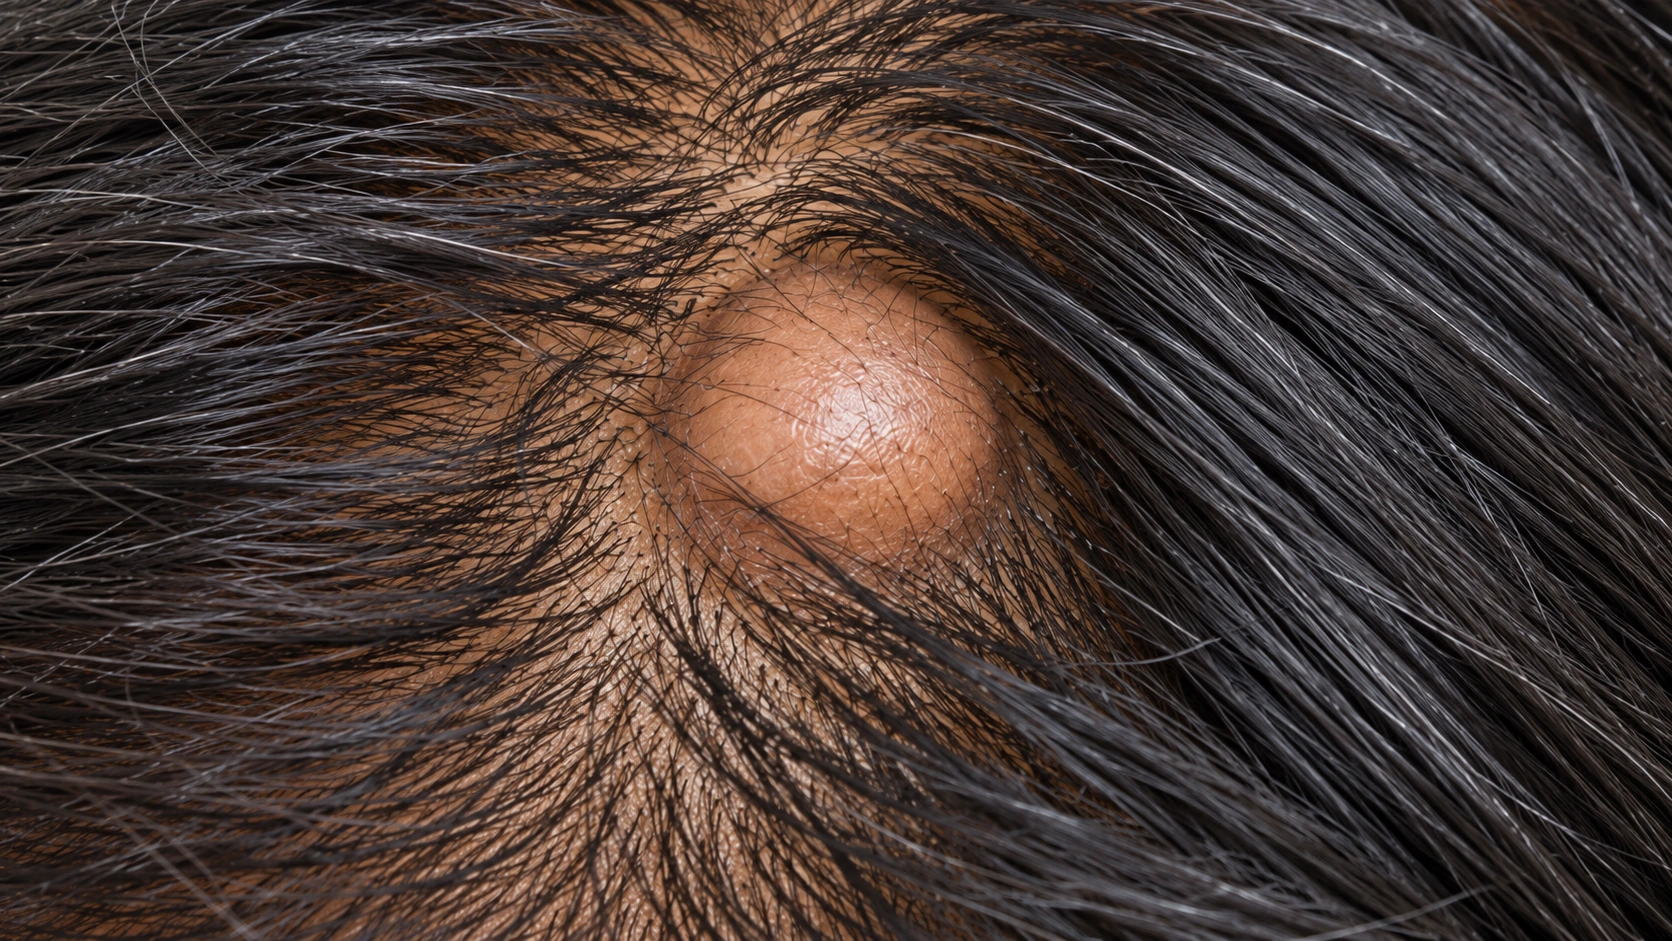
Pilar Cyst Parted hair reveals a smooth raised bump beneath the skin.

Skin tones
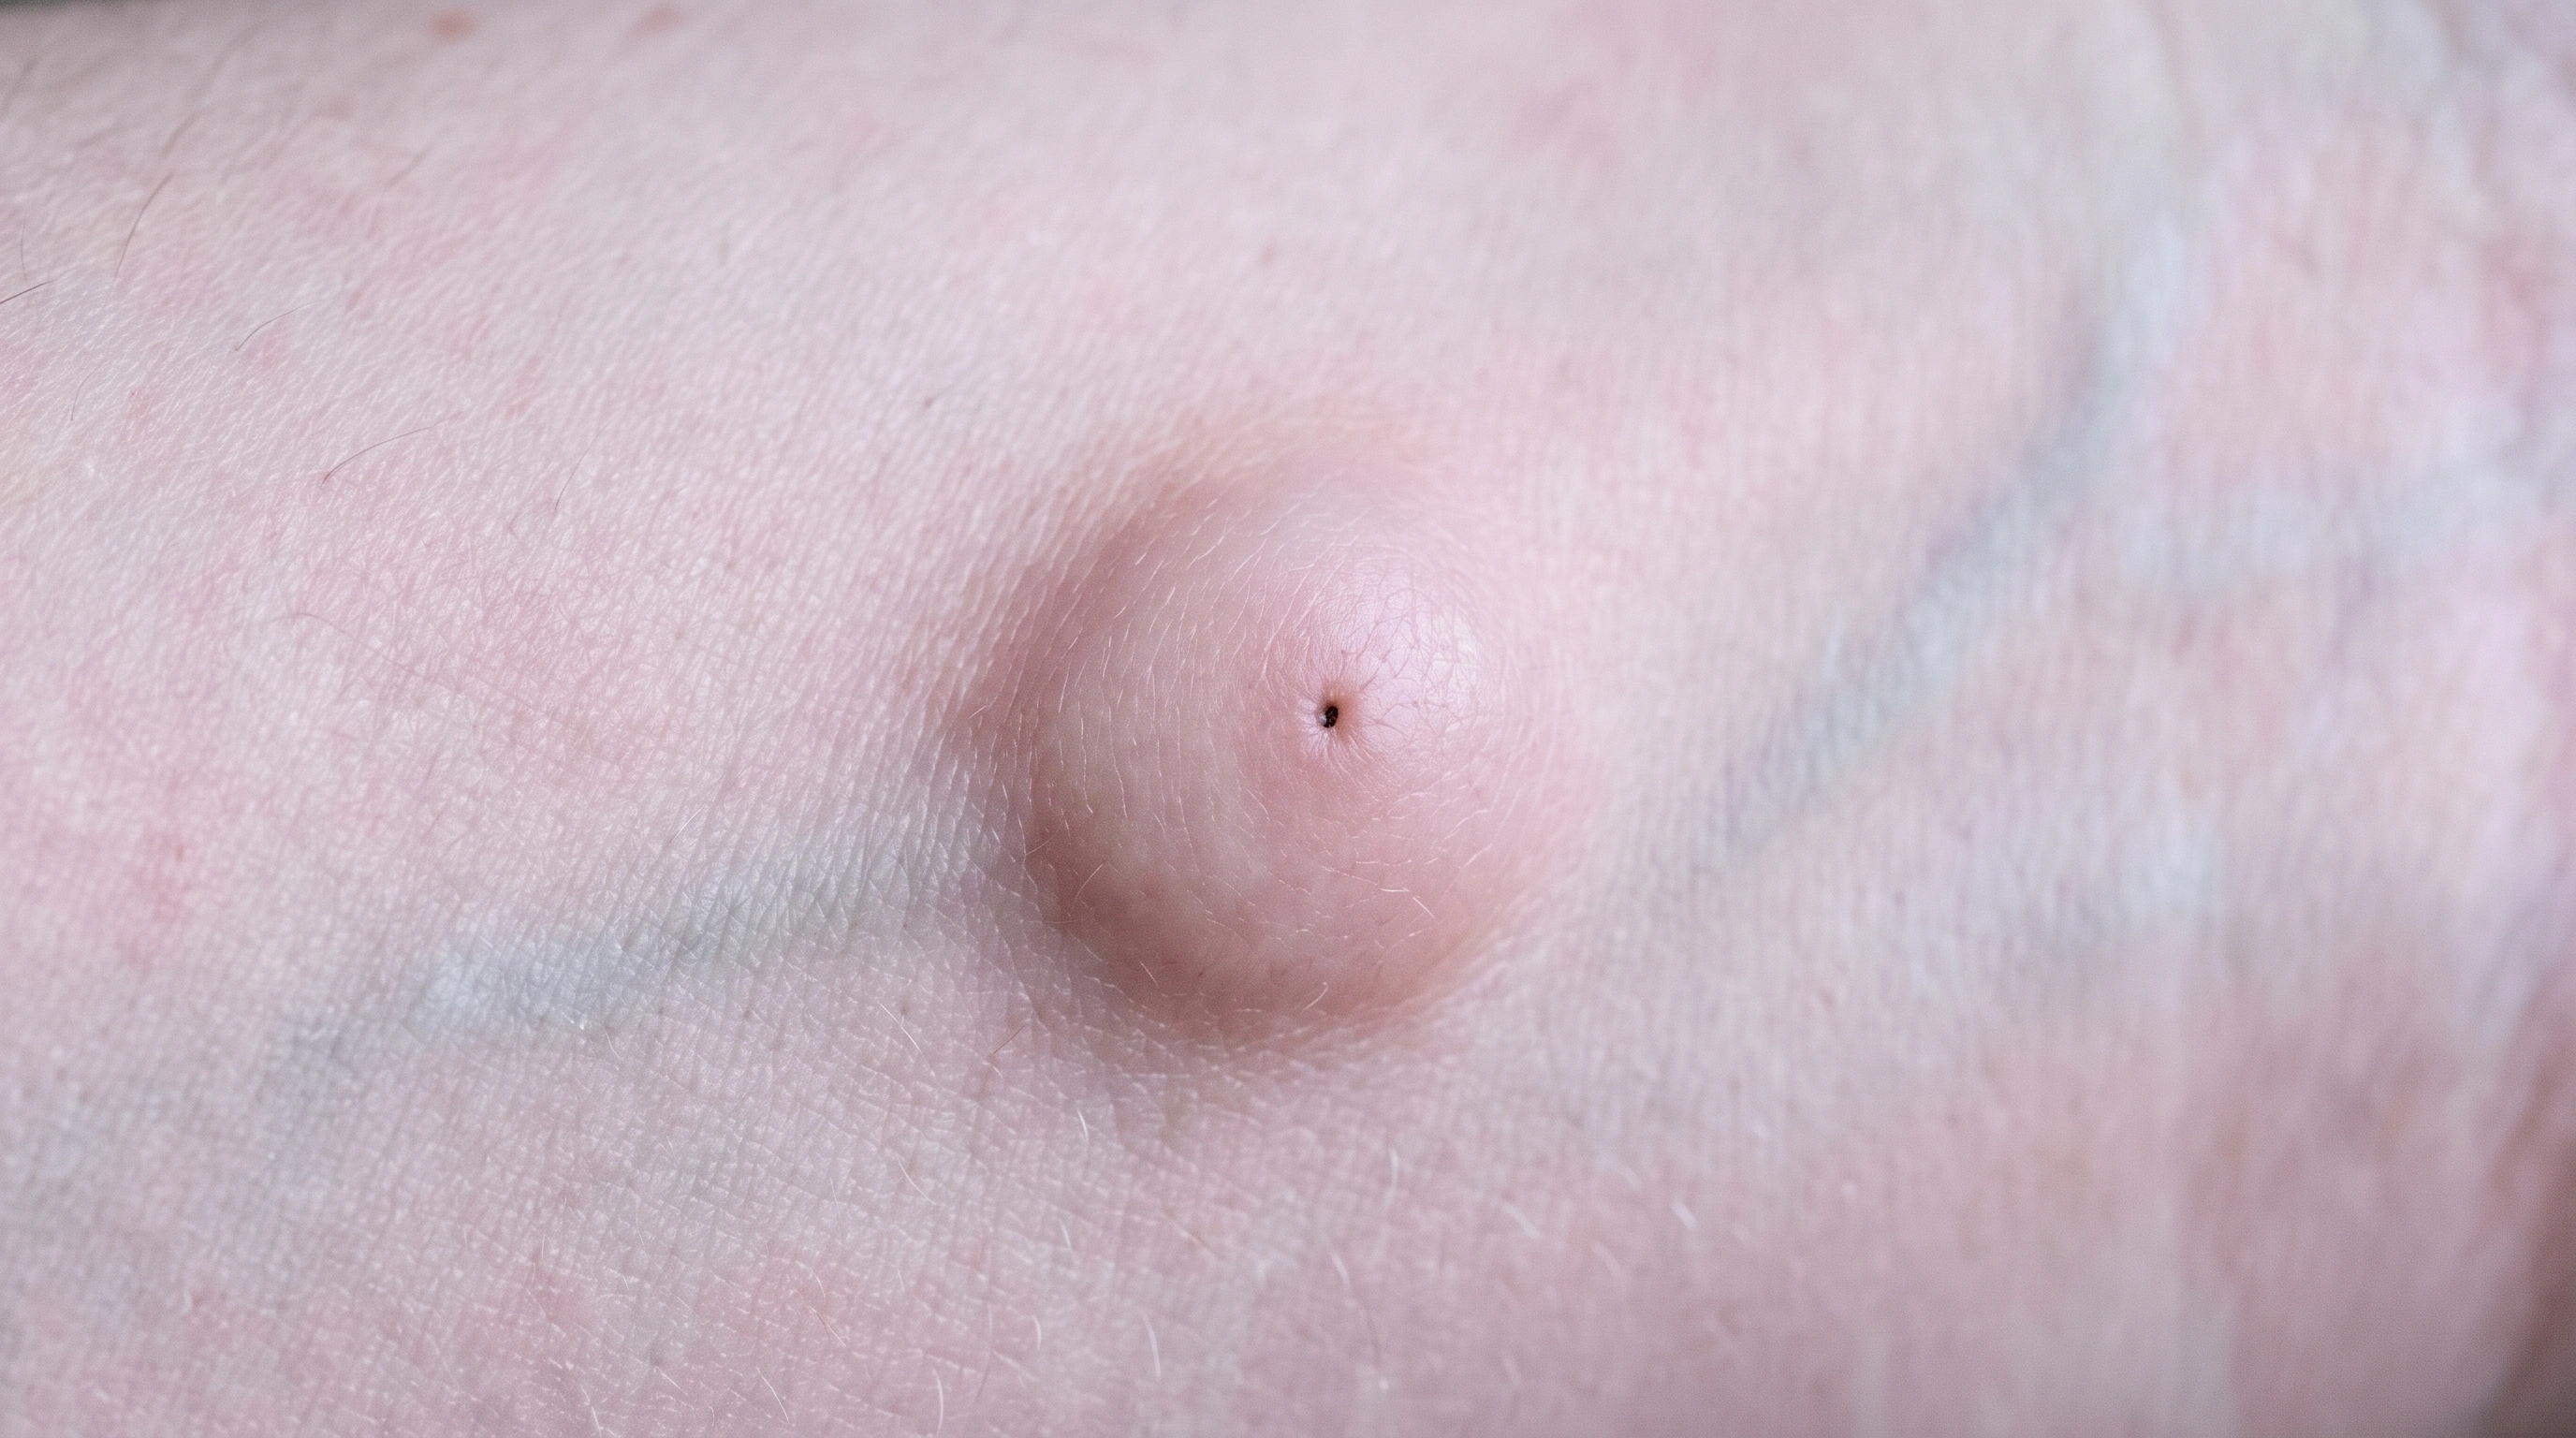
A smooth, dome-shaped lump about two centimetres across on the upper back on pale skin, with a tiny dark pore at its center and faintly pink skin over it.
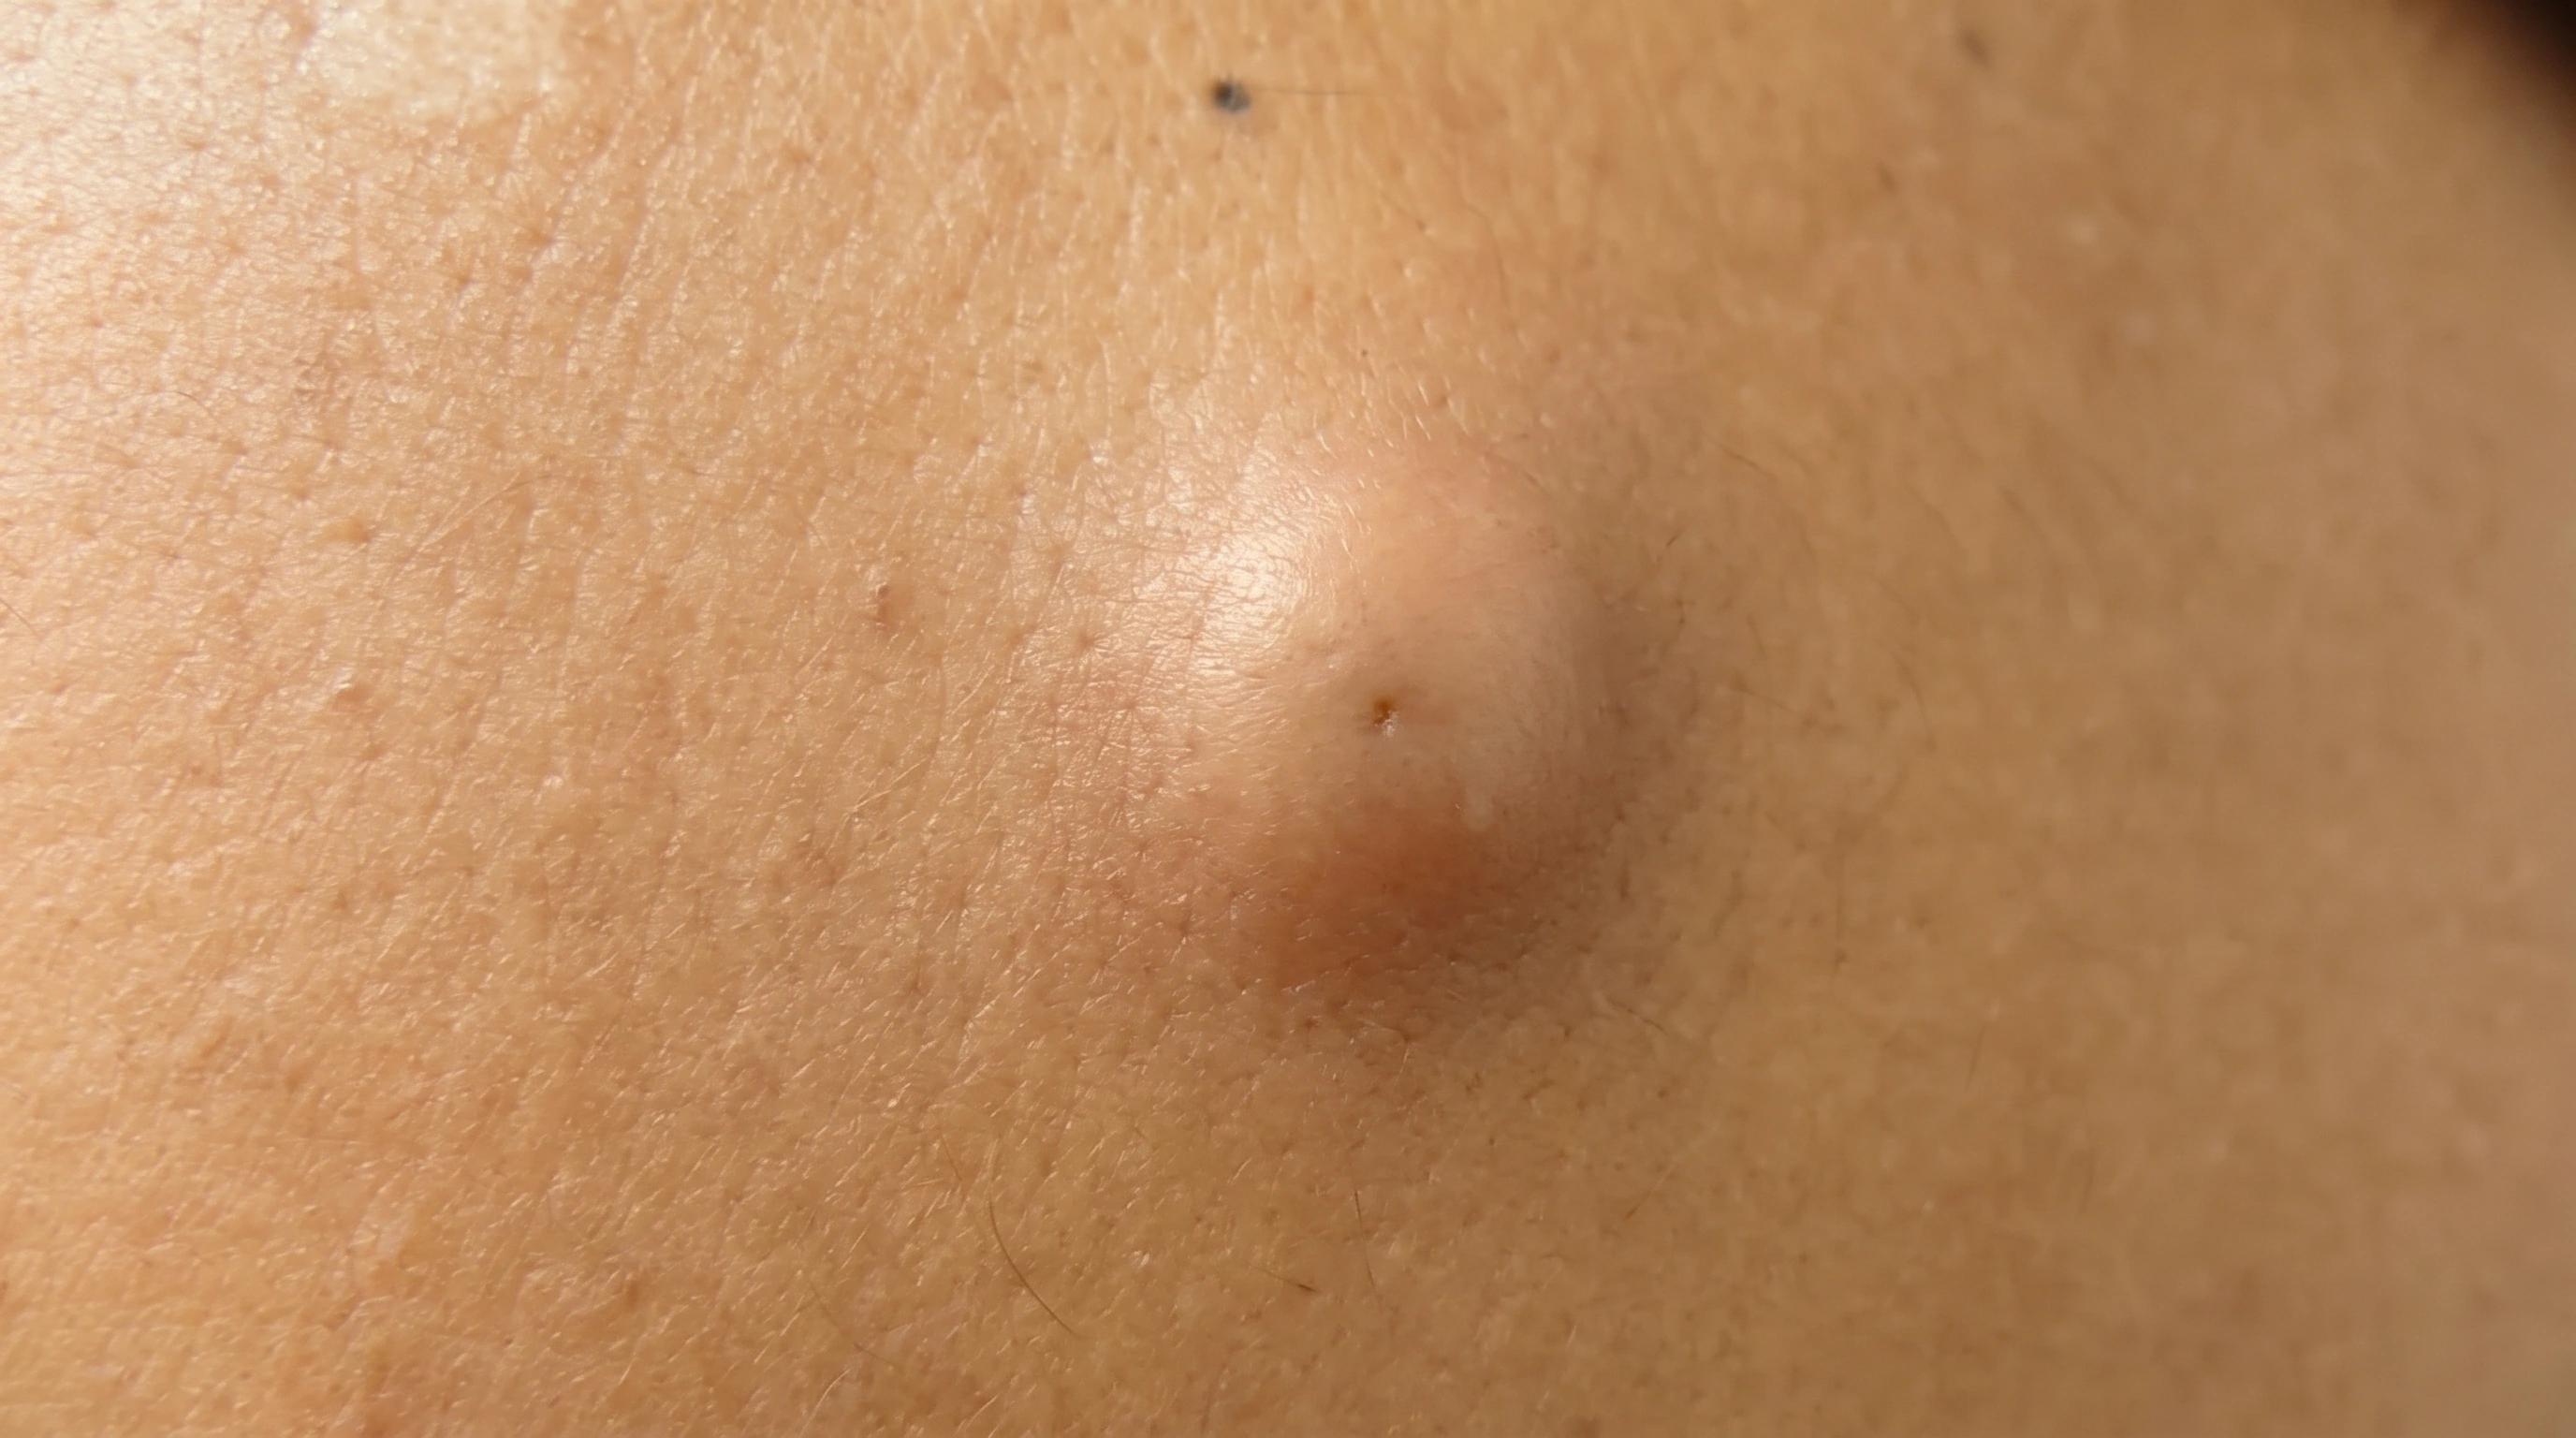
A smooth, dome-shaped lump on the upper back on medium olive skin, with only a faint central pore and skin over it the same color as the skin around it.
A smooth, dome-shaped lump on the upper back on mid-brown skin, with a small central pore and skin over it very slightly darker than the skin around it.
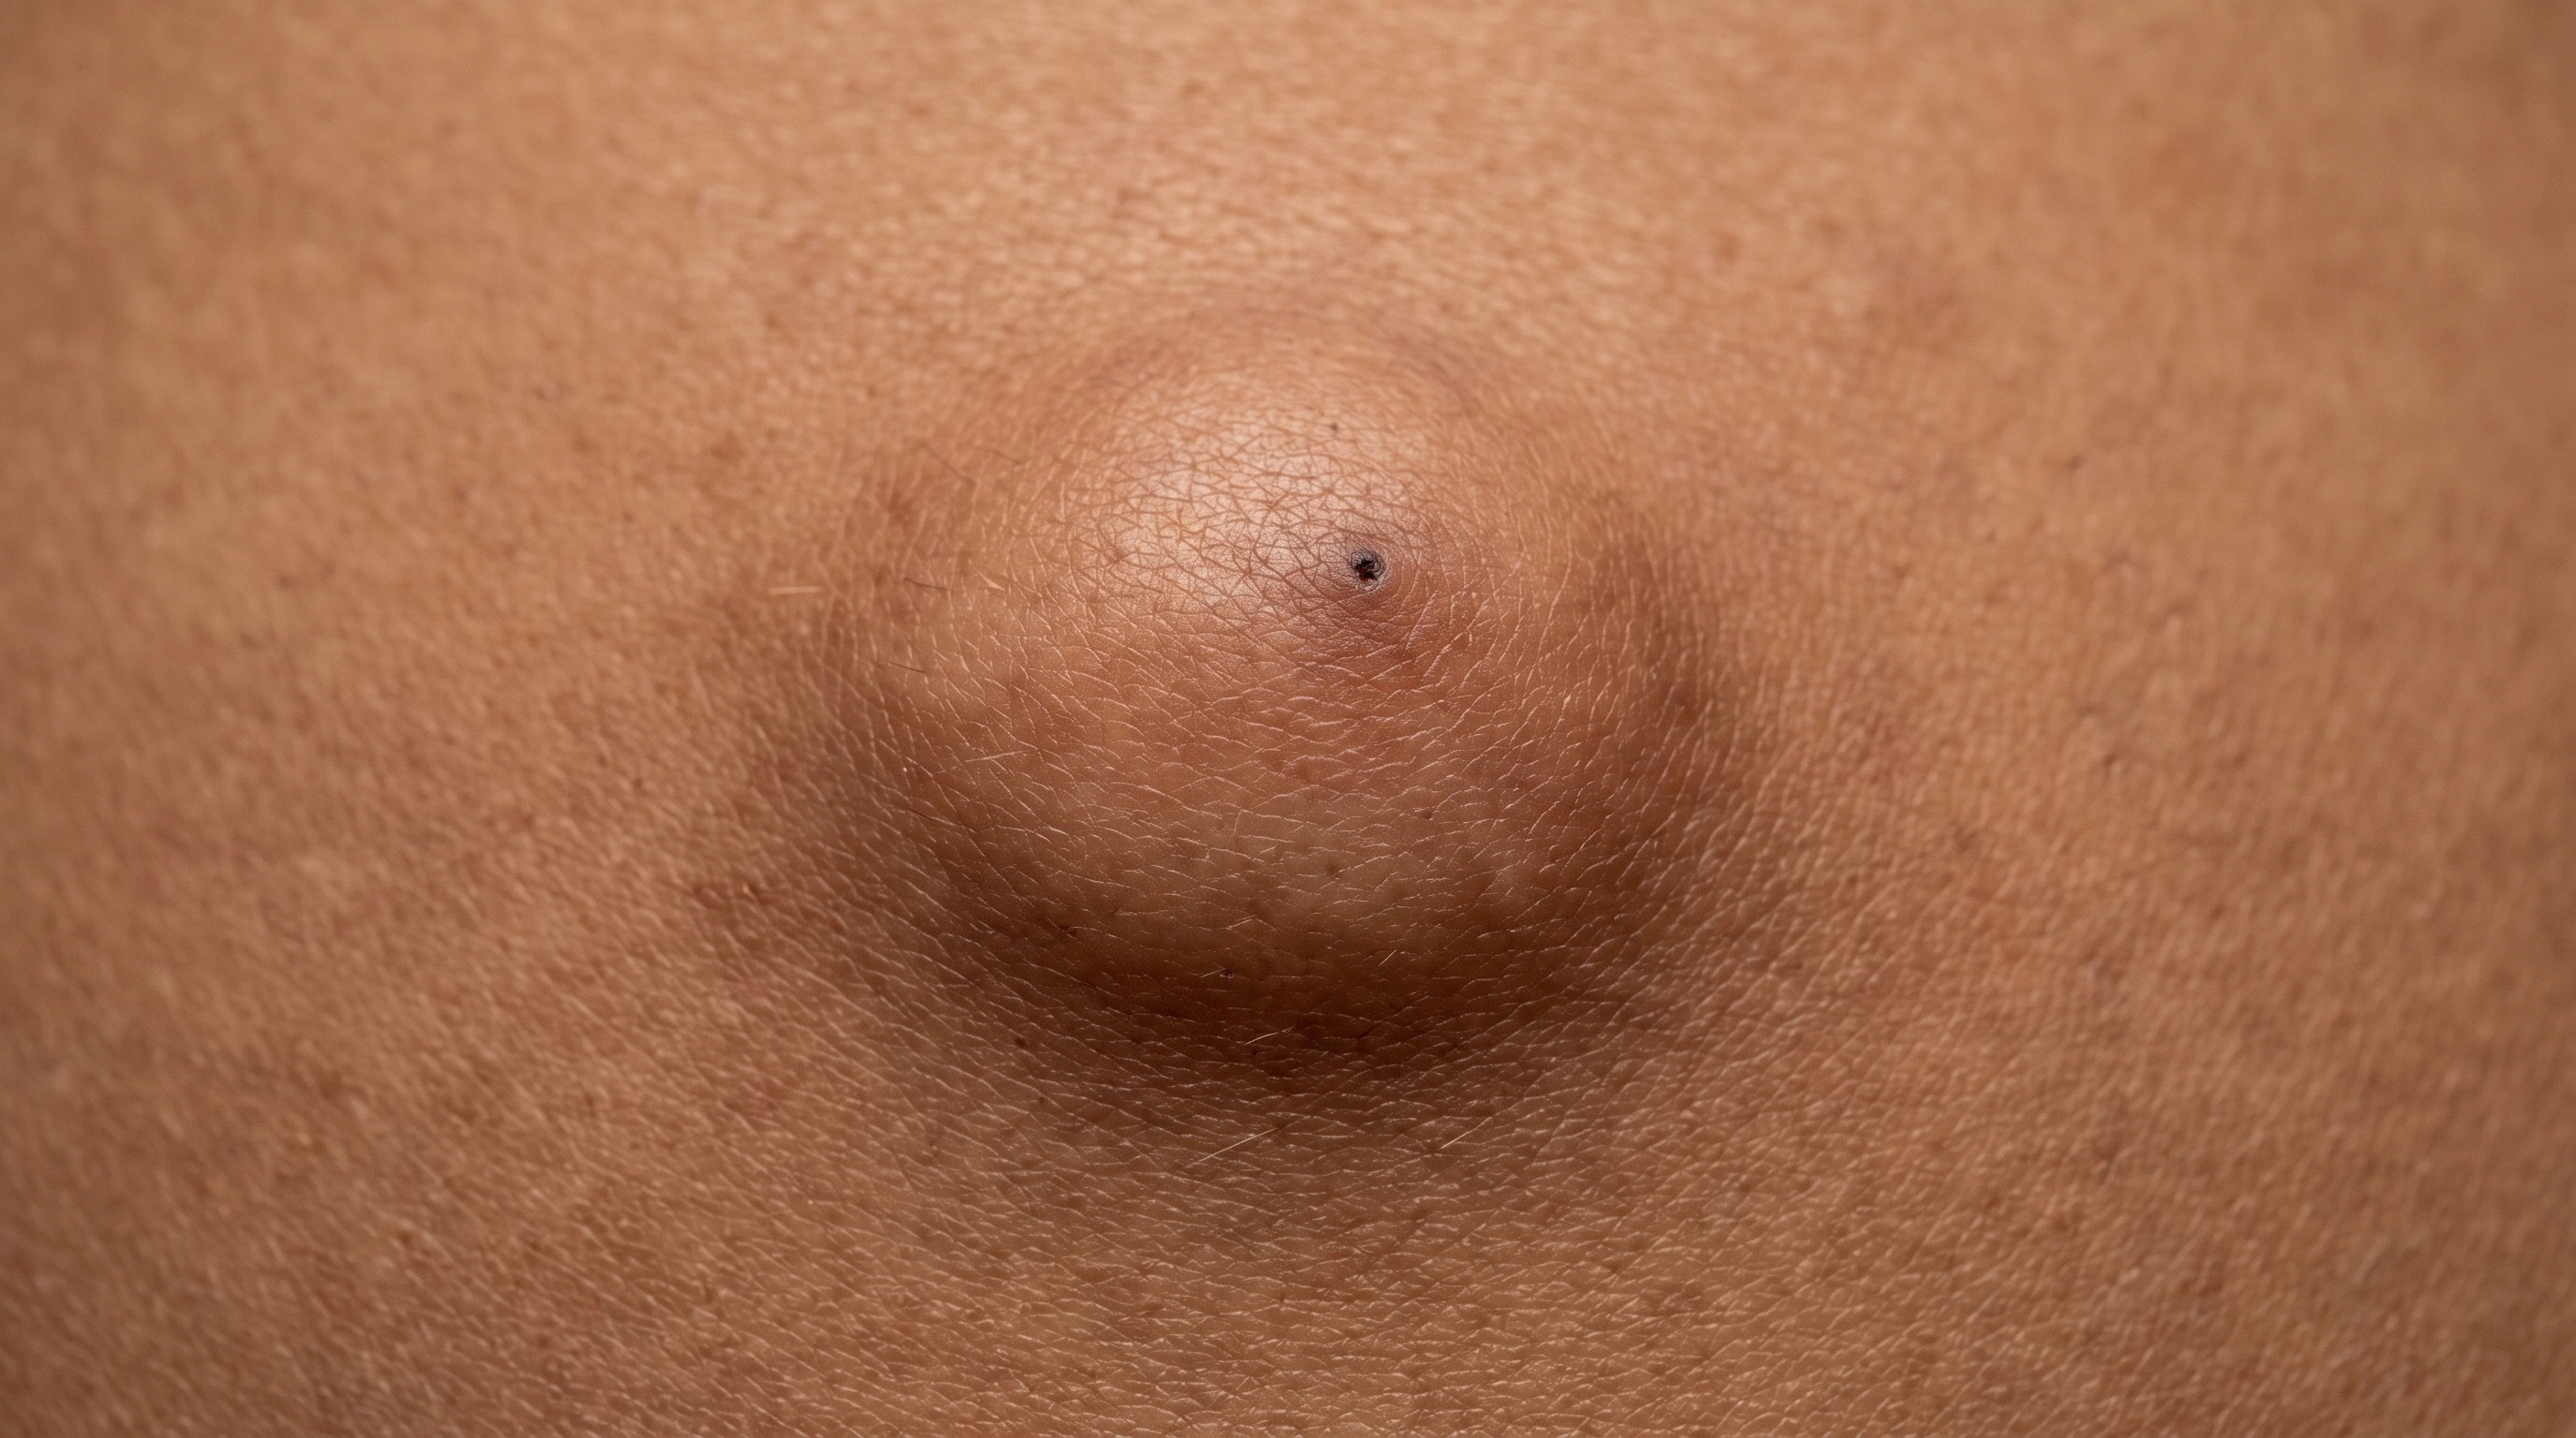
A smooth, dome-shaped lump on the upper back on deep brown skin, with a small dark central pore and even-toned skin over it.
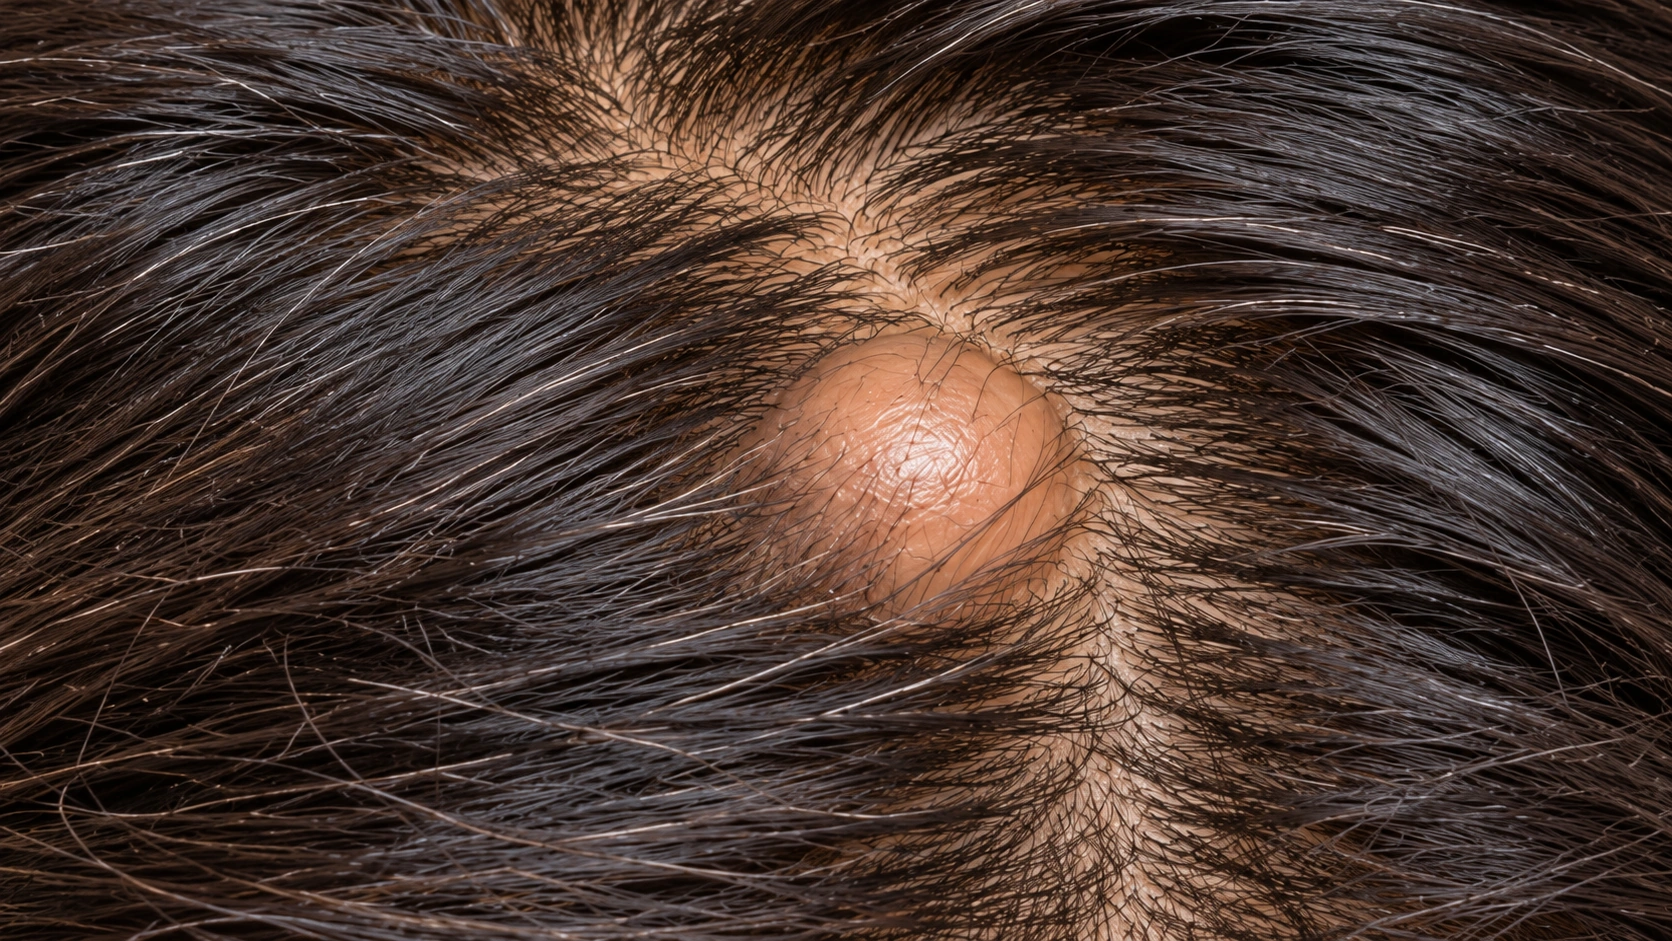
Pilar Cyst on light skin.
A smooth rounded pilar cyst beneath intact scalp skin.
Diagram
Epidermal Inclusion Cyst mechanism diagram. A lining forms: Skin-like cells line a sac beneath the surface. Keratin collects: The lining sheds skin protein into the sac. Rupture can inflame it: Escaped keratin irritates surrounding tissue.
In the skin

A sac lined by skin-like cells forms beneath the surface and fills with shed keratin. If the lining ruptures, escaped keratin can provoke inflammation in the surrounding tissue.

Cells from the hair root sheath form a cyst lining beneath the skin. Keratin produced by this lining accumulates inside the cyst.

When it usually starts

010203040506070+

Epidermal Inclusion Cyst. Most often develops in adults, though it can occur at other ages.

Pilar Cyst. Most often recognised in adults.

Causes and triggers

Causes

An epidermal inclusion cyst forms when surface skin cells get trapped under the skin and keep making keratin.

Keratin accumulates within a cyst lined by cells from the hair root sheath.

Risk factors
Acne, Skin injury, Adults aged 20 to 40
Family tendency
Trigger
● Epidermal Inclusion Cyst
● Pilar Cyst
Blocked hair follicles
Strong link
Not listed
Skin injury or surgery
Strong link
Not listed
Squeezing the cyst
Well established
Not listed
Local trauma can inflame an existing cyst
Not listed
Can contribute

Daily Care

Epidermal Inclusion Cyst
Pilar Cyst
Daily care

Habits that help

  • Warm compresses
    Ease discomfort and help it come to a head.
  • Reduce friction over it
    Adjust a strap, move a backpack.
  • Treat underlying acne
    Fewer new cysts where heavy acne is controlled.

Avoid

  • Avoid: Squeezing it
    Pressure tears the sac from inside.
  • Avoid: Picking at the central dot
    Widens the opening, invites bacteria.
  • Avoid: Lancing it at home
    Infection risk, a scar, and the lining stays.
  • Avoid: Friction and pressure over it
    Straps and waistbands set a stable cyst flaring.
  • Avoid: Shaving over it
    A nick is a straight route to inflammation.
  • Avoid: Drawing salves and home remedies
    Nothing surface-applied dissolves a sac.
  • Avoid: Waiting for a flare to remove it
    The sac tears instead of lifting out.
  • Avoid: Having only the contents drained
    The lining stays, so it refills.
  • Avoid: Repeated flares over years
    Each lays down scar tissue that tethers the sac.
  • Avoid: A midline lump on a baby
    Identify it first - a few connect to deeper structures.

Habits that help

  • Leave a stable, clinician-confirmed benign lesion alone
    It may not need treatment if it is comfortable and not changing.
  • Reduce rubbing from clothing, shaving or hair tools
    Repeated injury can make a harmless lesion sore or cause bleeding.
  • Notice meaningful changes without repeatedly squeezing it
    Arrange examination for rapid growth, persistent bleeding or a change in appearance.
  • Comb and wash around the lump gently
    Do not puncture a scalp cyst; inflammation or drainage needs assessment.

Avoid

  • Avoid: Cutting, burning, freezing or acid removal at home
    Home removal can cause infection, scarring and delay the correct diagnosis.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Epidermal Inclusion Cyst
● Pilar Cyst
Injections
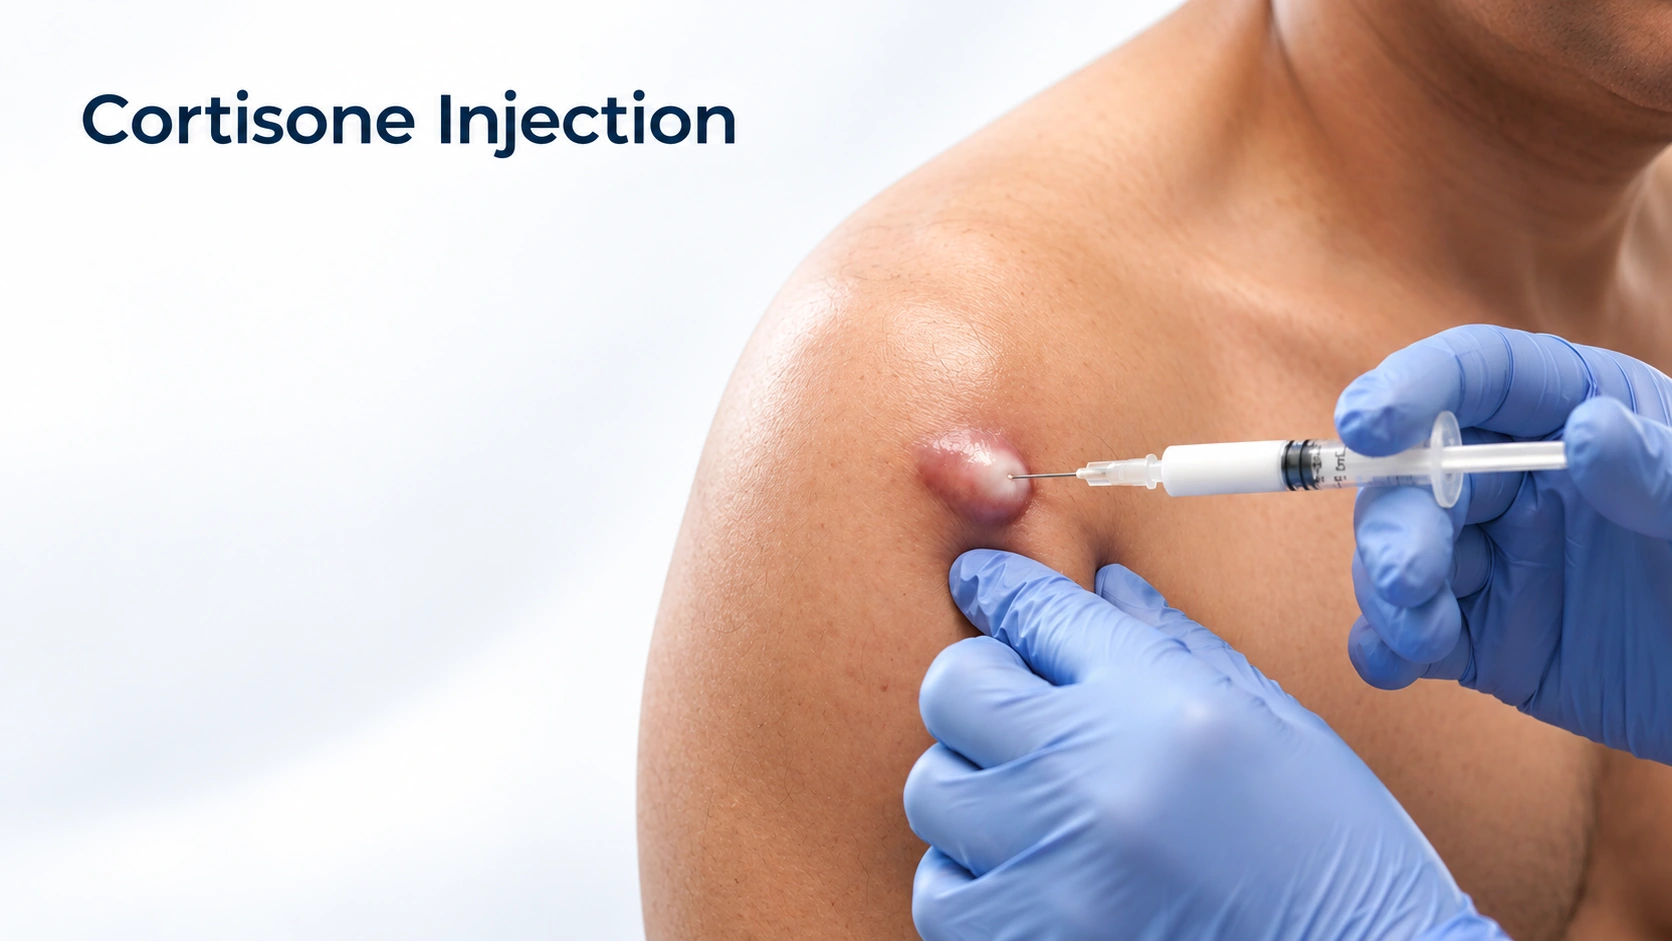
Editorial illustration for Cortisone Injection, based on the entry’s treatment or equipment reference.

Cortisone Injection

Limited evidence

A small injection of steroid into an inflamed cyst early in a flare, which settles the swelling and pain over a few days. It is for the flare, not the cyst — the sac and its lining are still there afterwards. It works best in the first day or two, before the lump has come to a head.

None listed
Procedures
Editorial illustration for Cyst Removal, based on the entry’s treatment or equipment reference.

Cyst Removal

Strong evidence

The only thing that ends a cyst, because it takes out the sac wall as well as the contents. It is a single minor procedure under local anesthetic, done through a small cut that is usually placed along a natural skin crease. Done on a quiet cyst it lifts out whole and leaves a thin line; done on an inflamed one it tears, fragments get left behind, and it is more likely to come back.

Editorial illustration for Incision and Drainage, based on the entry’s treatment or equipment reference.

Incision and Drainage

Moderate evidence

Incision and drainage. A small cut to let out the contents of a large, painful, inflamed cyst. The relief is immediate and it is exactly the right thing to do for an abscess. It is not a cure: the lining stays behind and keeps making keratin, so it usually refills over weeks to months. The usual plan is to settle things this way, then remove the sac properly a month or two later.

Cyst excision

Listed

Can remove a symptomatic or troublesome cyst and its wall; the specimen may be examined.

Outlook

Long term

Left alone, a cyst sits quietly for years, punctuated by flares. The pattern matters more than any single episode - a cyst that has never flared can come out whenever it suits you, while one that has flared twice is on a trajectory. Plan removal during a quiet spell.

Pilar cysts are usually benign and often remain unless removed. A painful or inflamed cyst needs assessment; recurrence is possible if the cyst wall is not completely removed.

Complications

Possible complications
  • Rupture and a painful flare
  • Infection or an abscess
  • Scars and keloids from repeat flares
More details

Rupture and a painful flare
The wall tears and keratin spills into the tissue around it, and the immune system attacks it. The lump becomes hot, swollen and painful over a day or two, and feels bigger and firmer than it did. Most of these are not infections. Squeezing is the single most common reason it happens, so leaving a quiet cyst alone is the best prevention there is.

Infection or an abscess
Sometimes bacteria do get in, and the cyst becomes a genuine abscess. It looks much like an ordinary flare, so the things that point to infection are spreading discoloration, pus, fever and feeling unwell. This is the version where antibiotics belong, and a large abscess usually needs draining as well. A hot, inflamed cyst around the nose, eyes or upper lip is treated more cautiously than one anywhere else.

Scars and keloids from repeat flares
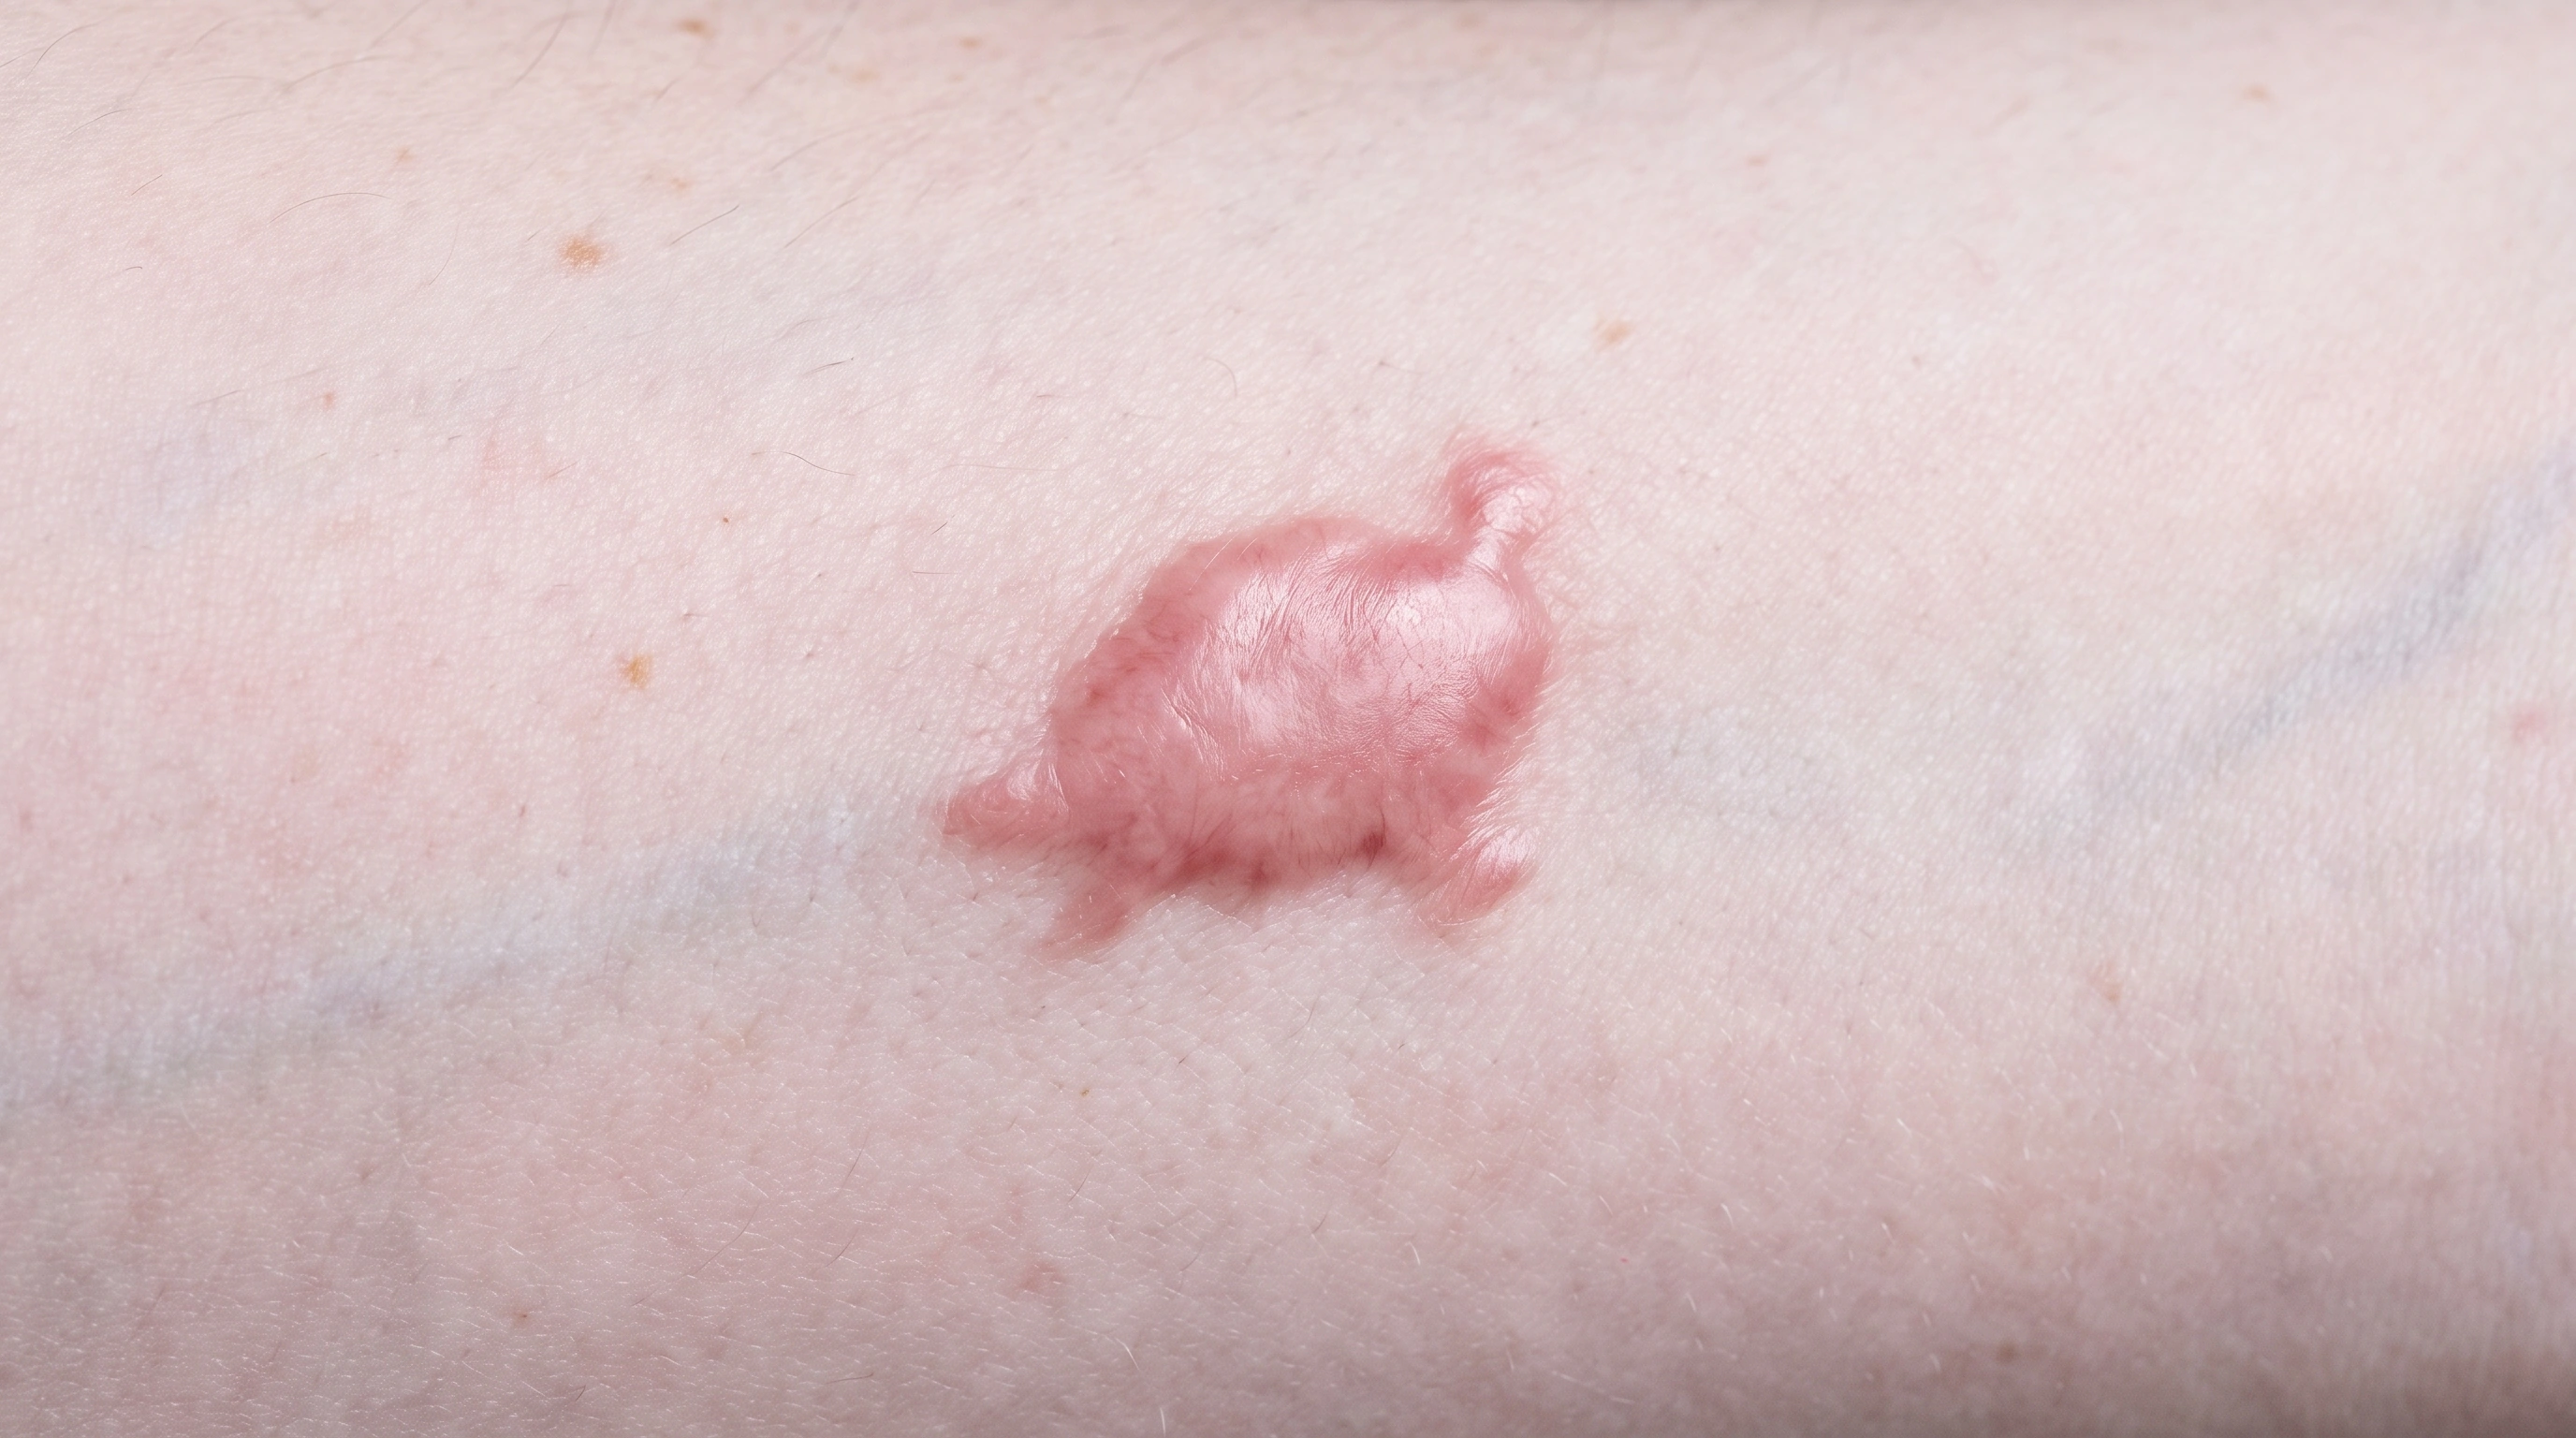
Every rupture and every emergency drainage lays down its own scar, and after a few episodes the area is tethered and marked before anyone has operated. Raised, thickened scars and keloids are more likely on the chest, shoulders, upper back and jawline, and more likely on deeper skin tones. A planned removal on a quiet cyst usually leaves a thin line along a natural skin crease, which is the argument for doing it sooner.

Most are benign; a rapidly growing, ulcerated or recurrent lump needs assessment.

When to get help

When to get help

Seek assessment if a lump is growing, recurrently inflamed or uncertain. Rapidly increasing pain, redness, drainage or fever may require prompt treatment.

Have painful, growing, bleeding or uncertain lumps examined.

Common questions

Epidermal Inclusion Cyst:Is it dangerous?

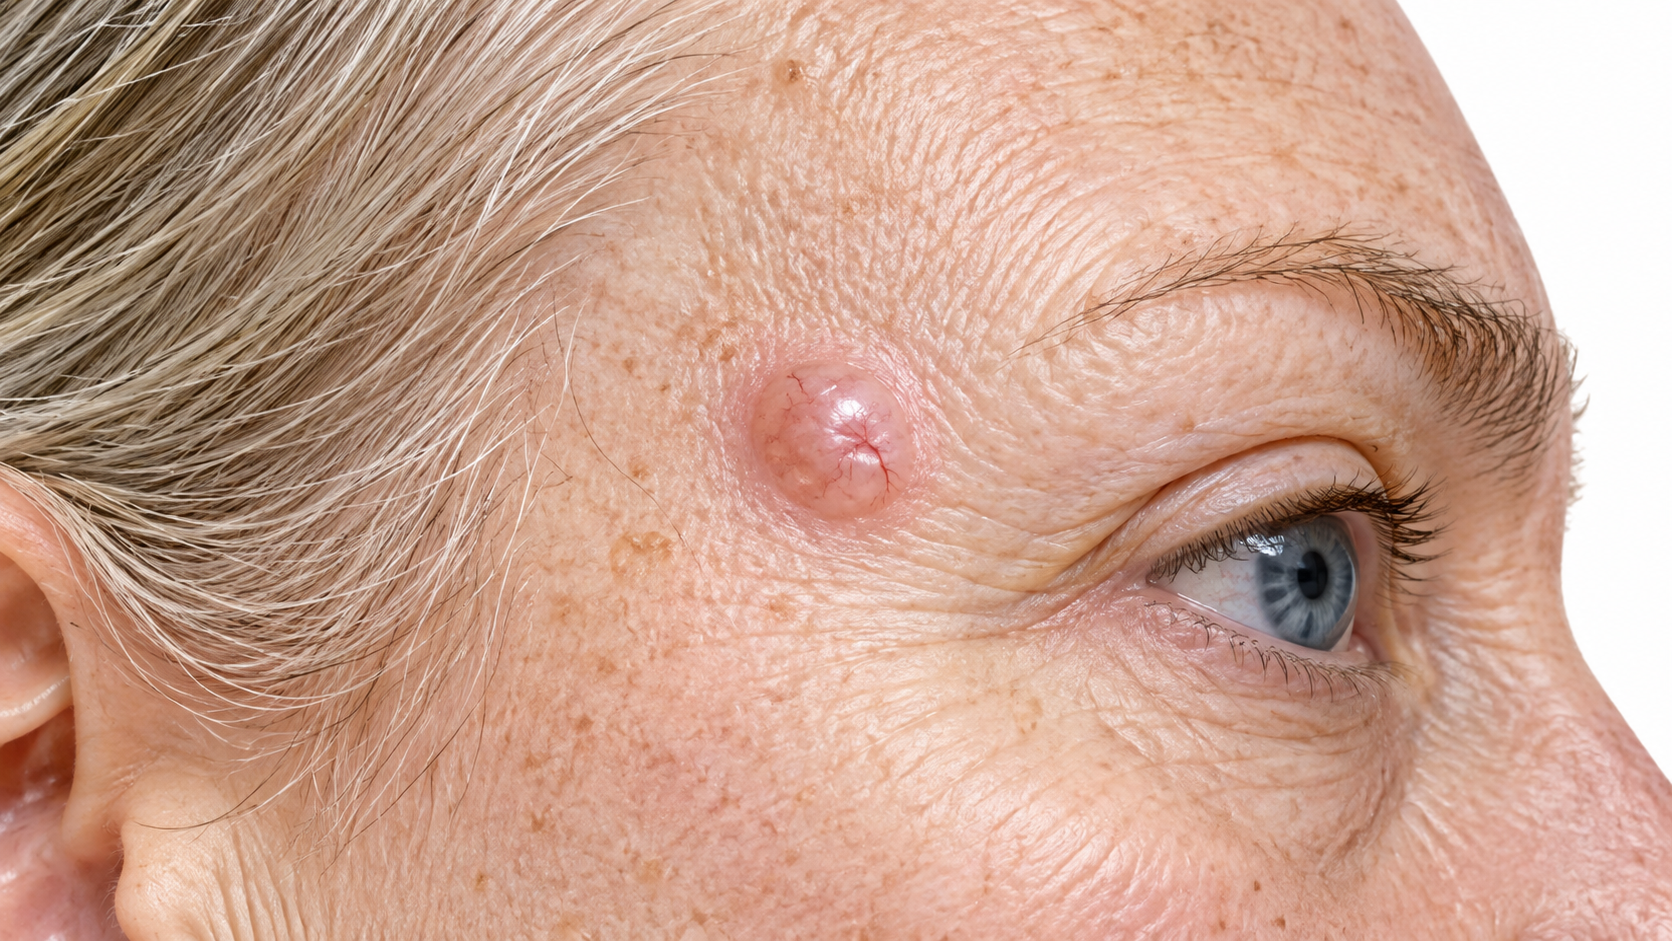
Epidermoid cysts are benign. They do not spread and do not turn into cancer. Cancers arising inside a cyst are described but genuinely rare. Have it examined if it grows rapidly, feels hard and fixed rather than mobile, bleeds, or has a sore over it that will not heal - those suggest the lump may not be a cyst.

Epidermal Inclusion Cyst:Why does it smell?

The contents are keratin and broken-down skin cells, sealed in for a long time, and skin bacteria break that material down. The smell comes from the contents, not from infection.

Epidermal Inclusion Cyst:Can I just have it drained?

You can, and for a large, painful, inflamed cyst that is the right thing for relief. But draining empties the contents and leaves the lining, and the lining makes keratin, so it refills over weeks to months. Removing the whole sac is what ends it.

Epidermal Inclusion Cyst:Why will my doctor not remove it while it is inflamed?

Because the result is worse. Inflamed tissue is swollen and fragile, so the sac tears instead of lifting out whole, fragments get left behind, the cyst is more likely to come back, and the scar is wider. Settle the flare first, then remove it a month or two later.

Epidermal Inclusion Cyst:Will it come back after surgery?

Not if the whole lining comes out, which is the goal. Recurrence happens when a fragment is left behind, more likely if the cyst was inflamed or heavily scarred from previous flares. New cysts can form elsewhere - that is a new cyst, not the old one.

Epidermal Inclusion Cyst:Can I stop getting them?

Not reliably, because most people who get one have no identifiable cause. You can reduce flares - do not squeeze them, take pressure and friction off them, and treat significant acne if cysts keep appearing where it was. If you are getting a lot from a young age, mention it, because a few people have an inherited reason.

Pilar Cyst:What is Pilar Cyst?

A keratin-filled cyst arising from the hair root sheath, usually on the scalp.

Pilar Cyst:What can I do day to day?

Avoid picking or squeezing and protect it from comb trauma.

Pilar Cyst:When should I get medical advice?

Have painful, growing, bleeding or uncertain lumps examined.

Sources

Sources and further reading

  1. DermNet
  2. Trichilemmal cyst
Dermapedia on YouTube