Eczema
Treats mild to moderate flares.
Elidel: A steroid-free anti-inflammatory cream for eczema. It calms the immune reaction in the skin without thinning it, which is why it is used on the face, eyelids and skin folds. Protopic: A non-steroid ointment for eczema, used where steroids are hardest to keep using: the face, the eyelids, and skin folds. It carries a boxed warning that twenty years of follow-up have not supported.

Choose for eczema on delicate skin — face, eyelids, folds — when you want to avoid steroid thinning.
Choose for eczema where steroids are hardest to keep using — face, eyelids, folds — or to prevent flares twice a week.
Can you take them together?
These are the same type of medicine. Elidel is milder; Protopic is stronger. Use one, not both.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.
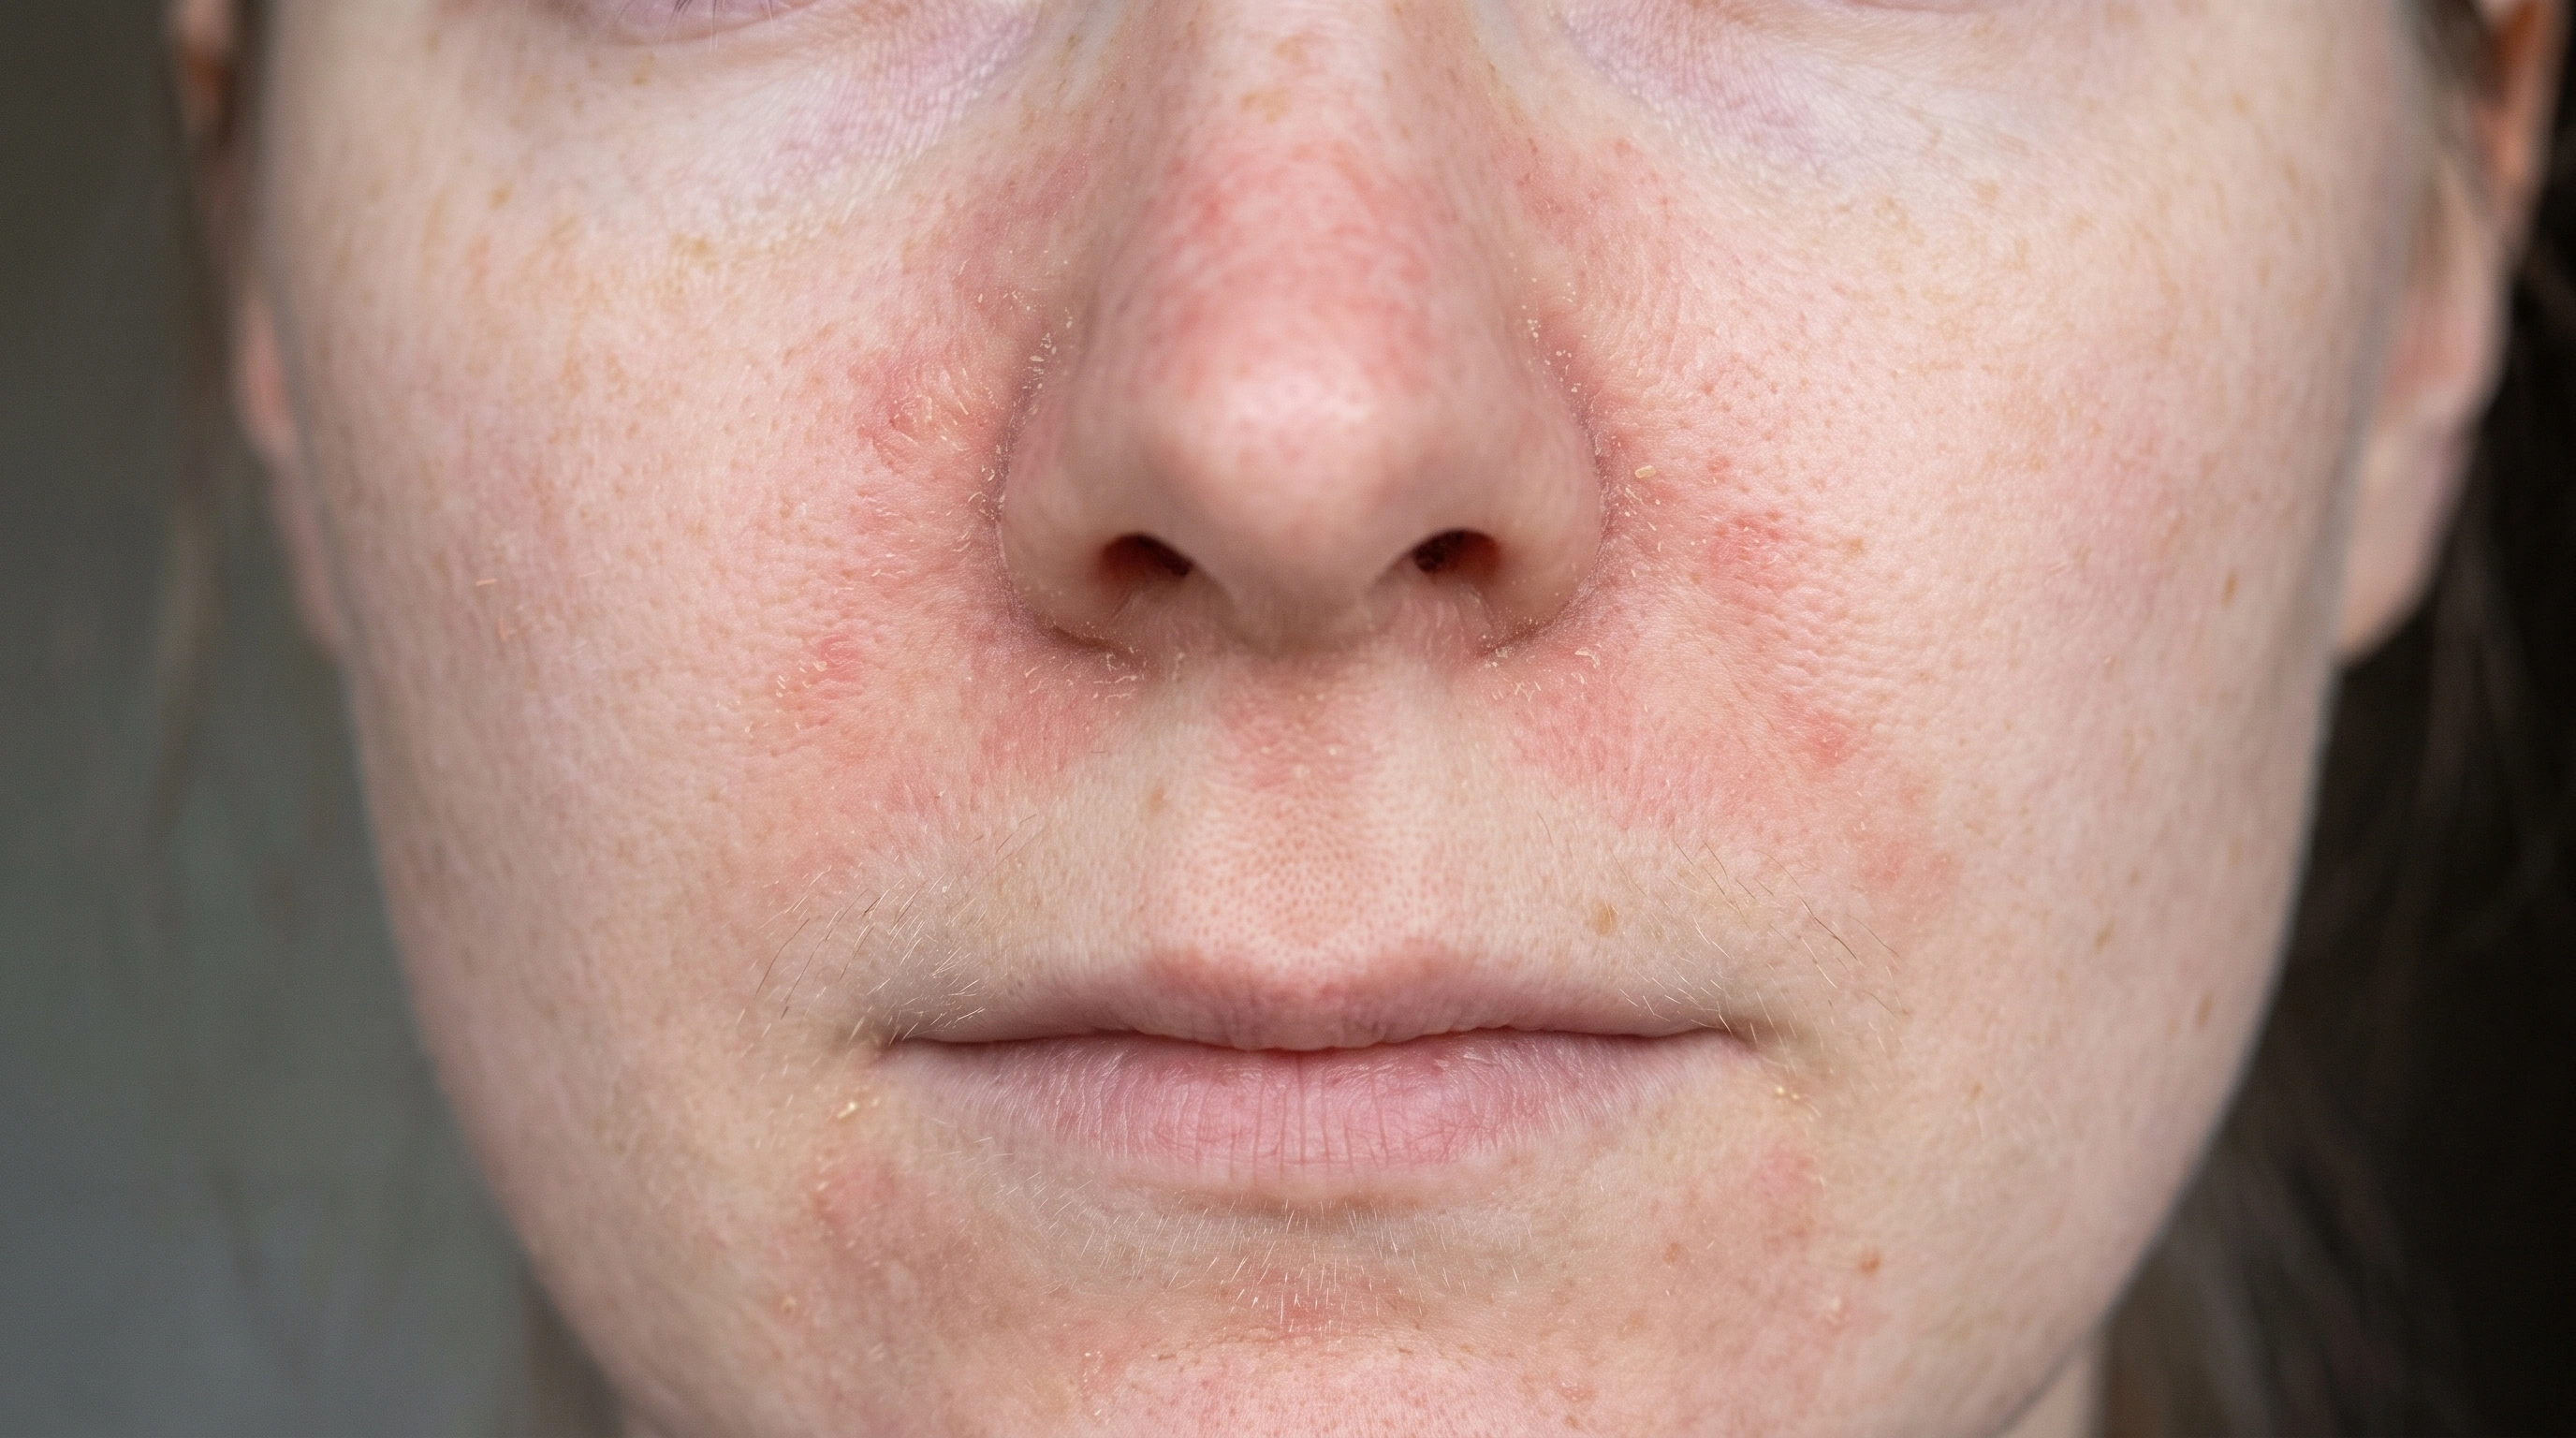



Inhibits calcineurin: Blocks a switch that helps activate T cells. Reduces immune messengers: T cells release fewer inflammation-driving signals. Calms eczema and itch: Redness and irritation ease as inflammation settles.
The drug binds FKBP-12 and inhibits calcineurin, reducing T-cell cytokine transcription; the complete atopic-dermatitis mechanism is not known. It also has other cellular effects.
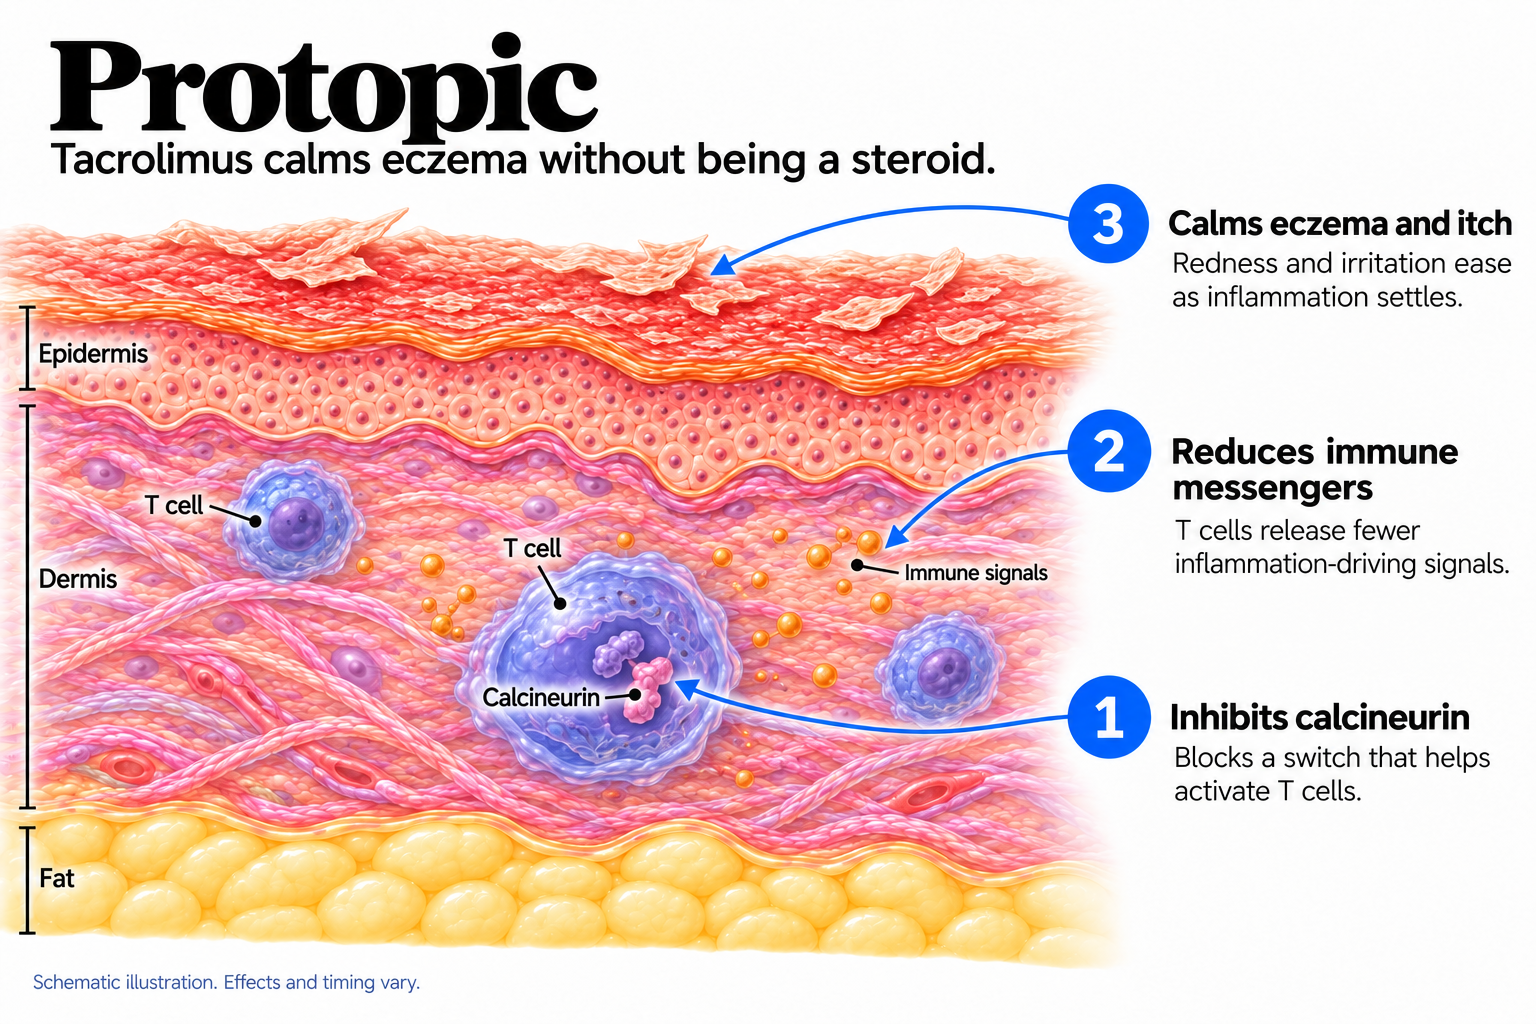
Inhibits calcineurin: Blocks a switch that helps activate T cells. Reduces immune messengers: T cells release fewer inflammation-driving signals. Calms eczema and itch: Redness and irritation ease as inflammation settles.
The drug binds FKBP-12 and inhibits calcineurin, reducing T-cell cytokine transcription; the complete atopic-dermatitis mechanism is not known. It also has other cellular effects.
When to Apply: A thin layer twice a day on the affected skin. Rub it in until it disappears. Moisturizer can go on top or underneath.
How to Start: Twice daily as soon as a flare starts, and keep going until the skin is clear rather than merely better. Many people then move to two or three days a week on the spots that always come back, to head off the next flare. Discuss that with your doctor.
If It Irritates: Warmth, stinging or burning for the first few days is the commonest complaint. It happens because the skin is inflamed, not because you are allergic, and it usually stops within a week as the eczema settles. Keeping the cream in the fridge, moisturizing first, or starting once a day for a few days makes it easier.
If It's Not Working: Nothing to increase — there is one strength. Give it six weeks of consistent twice-daily use. If the skin is no better, the usual next steps are a short steroid course to reset it, a switch to tacrolimus ointment, or a newer non-steroid cream.
When to Apply: A thin layer twice a day to the affected skin, rubbed in gently. It goes on the rash, not over clear skin. Keep moisturizer a couple of hours apart — layering one straight onto the other has not been studied.
How to Start: Twice a day until the patch clears, usually one to three weeks, then stop. Many people then move to maintenance — twice a week on the places that always flare, even when they look normal. That is well supported and makes flares less frequent.
If It Irritates: Burning or stinging for fifteen to thirty minutes after applying is very common in the first days and is not an allergy. It settles within about a week. Keeping the tube in the fridge, applying to dry rather than damp skin, and skipping alcohol early on all help.
If It's Not Working: Check it is going on twice a day — two to three weeks is a fair trial. Then the options are the higher strength if you are an adult on 0.03%, a short steroid course to break the flare, or a look at whether infection or a contact allergy is driving the rash.
No routine blood tests. Blood levels are very low or undetectable, and it does not affect the adrenal glands the way strong steroids do.
Monitoring is a conversation at six weeks, then longer intervals if you stay on it. Your doctor is checking whether the eczema is actually controlled, whether steroid rescue courses have been needed often enough to suggest a change of plan, and whether any patch of skin is behaving oddly rather than simply eczema.
Because of the boxed warning, most dermatologists look harder at any new or changing spot in long-term users rather than assuming it is part of the rash. Registry follow-up has not found the increase in skin cancer or lymphoma the warning anticipated, so this is ordinary caution, not surveillance for a known risk.
No blood tests are needed. Blood levels are usually undetectable with the ointment and fall further as the barrier repairs — the opposite of the oral form used after transplants. Monitoring is a check at two to three weeks on whether the rash responded, then a plan for maintenance.
The boxed warning is the part to understand. It says long-term safety is not established, that rare cases of lymphoma and skin cancer were reported in people who used these drugs, and that continuous long-term use should be avoided. It was added in 2006, based mainly on animal studies using very high doses by mouth or injection, plus scattered case reports.
What has happened since matters. Large cohort studies, and a registry that followed treated children for a decade, have not found the rise in lymphoma the warning describes. Guidelines in the United States and Europe still recommend these drugs, including on the face and eyelids and as twice-weekly maintenance. The concern was theoretical, more than twenty years of use has not borne it out, and how long to continue is still a decision to make with a doctor.
Day-to-day monitoring is simple: keep skin checks routine, use sun protection on treated areas, and pause during a skin infection.
Approximate windows, not promises.
First few minutesApplying it: A thin layer twice a day. Warmth or stinging for a few minutes, strongest on the rawest skin.
First few minutesApplying it: A thin layer twice a day. Burning or stinging for a short while afterward is common and worst in the first week.
Days 1 to 5Adjusting: The stinging is at its worst now and fades as the skin heals. Itch often eases while the rash looks the same.
Weeks 1 to 2Working: Redness fades, skin feels less tight. Night scratching drops off first.
Weeks 2 to 6Judge it here: The rash flattens and clears. The fair point to decide whether it is doing enough.
Face, eyelids and foldsIts strongest use: Thin skin is where steroids cause the most trouble, so a non-thinning option is worth losing some strength. Armpits, groin and under the breasts thin quickly too.
OngoingHolding: Once clear, many drop to two or three applications a week on the areas that always flare. No thinning means no time limit.
Days 1 to 7Adjusting: Burning is at its worst now. Itch often improves in the same week, which is what gets most people through.
Weeks 1 to 3Working: Redness and thickening settle and the burning has usually stopped. Most people reach their best result here.
MaintenanceKeeping flares apart: Once clear, twice-weekly use on the trouble spots lengthens the gaps between flares. Licensed, not an improvisation.
Sorted by what to do about them.
Cost has improved. Generic pimecrolimus cream brought the price down from one of the more expensive eczema treatments to something ordinary. Brand-name Elidel is still costly.
The usual obstacle is not price but step therapy. Because the label calls it second-line, many plans want to see that a topical steroid was tried and failed, or a reason a steroid should not be used, before covering it. A note from your doctor saying the eczema is on the eyelids or in the folds usually settles that.
Cash prices for the generic vary between pharmacies more than most drugs, so check a discount card price before assuming you cannot afford it. Tube size matters too — a large tube is often better value per gram, and eczema treatment runs longer than people expect.
Both strengths come as generics, which brought the price down a long way, though it still costs more than a generic steroid ointment. Prices vary widely between pharmacies and discount cards sometimes beat insurance, so check more than one.
Prior authorization is still common, usually asking that a topical steroid was tried first. Tube size is the practical variable: twice-daily use means a small tube treating a child's face lasts far longer than the same tube on two hands.
No. Different pathway, and it does not thin the skin — the whole reason it is used on eyelids, the face and skin folds.
Because at approval regulators noted that related medicines suppress immunity body-wide in transplant patients, that very high oral doses caused tumors in animals, and that a small number of cancer reports existed in users. The warning states that long-term safety is not established — a precaution, not a finding. Follow-up since has not shown an increased rate of skin cancer or lymphoma.
Because the skin underneath is inflamed. It is the commonest side effect, strongest in the first few days, and it settles as the eczema heals. Moisturizing first or chilling the tube helps.
No fixed limit. It does not thin skin, so it can run in repeated courses, or two or three times a week, for years with review.
Yes — eyelids are one of its main uses, one of the few anti-inflammatory options that can go there repeatedly without thinning skin or raising eye pressure.
No. Tacrolimus 0.1% ointment is more powerful for moderate eczema. Pimecrolimus is better tolerated and cosmetically easier, so it is often the one people keep using.
Yes, and it is printed on the label — long-term safety is not established, and rare cases were reported. Studies following large groups for years have not found the increased risk. A caution, not a demonstrated harm.
It acts on nerve endings in inflamed skin as well as on immune cells. Burning is worst in the first few days and gone within a week as the rash heals.
Yes — eyelid eczema is one of the main reasons it gets prescribed. Keep it off the eye itself and the lid margin.
Alcohol flushing is a known effect while using it. Harmless, and it stops when the treatment does.
The label asks for the shortest suitable use and for breaks. Twice-weekly maintenance on trouble spots is licensed and widely used. Make that decision with a doctor rather than leaving a prescription running.
No. Blood levels are usually undetectable with the ointment. The tablets are a different treatment entirely.