Eczema
Treats mild to moderate flares.
Elidel: A steroid-free anti-inflammatory cream for eczema. It calms the immune reaction in the skin without thinning it, which is why it is used on the face, eyelids and skin folds. Opzelura: The first cream approved to bring color back to vitiligo, and a fast non-steroid option for eczema. It carries a boxed warning borrowed from the tablet versions of the same drug class, and a limit on how much skin you can treat.

Choose for eczema on delicate skin — face, eyelids, folds — when you want to avoid steroid thinning.
Choose to bring color back to vitiligo, especially on the face, or for a fast non-steroid eczema option — if cost can be managed.
Can you take them together?
Both are steroid-free creams for eczema on sensitive skin. Use one or the other rather than layering them.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.
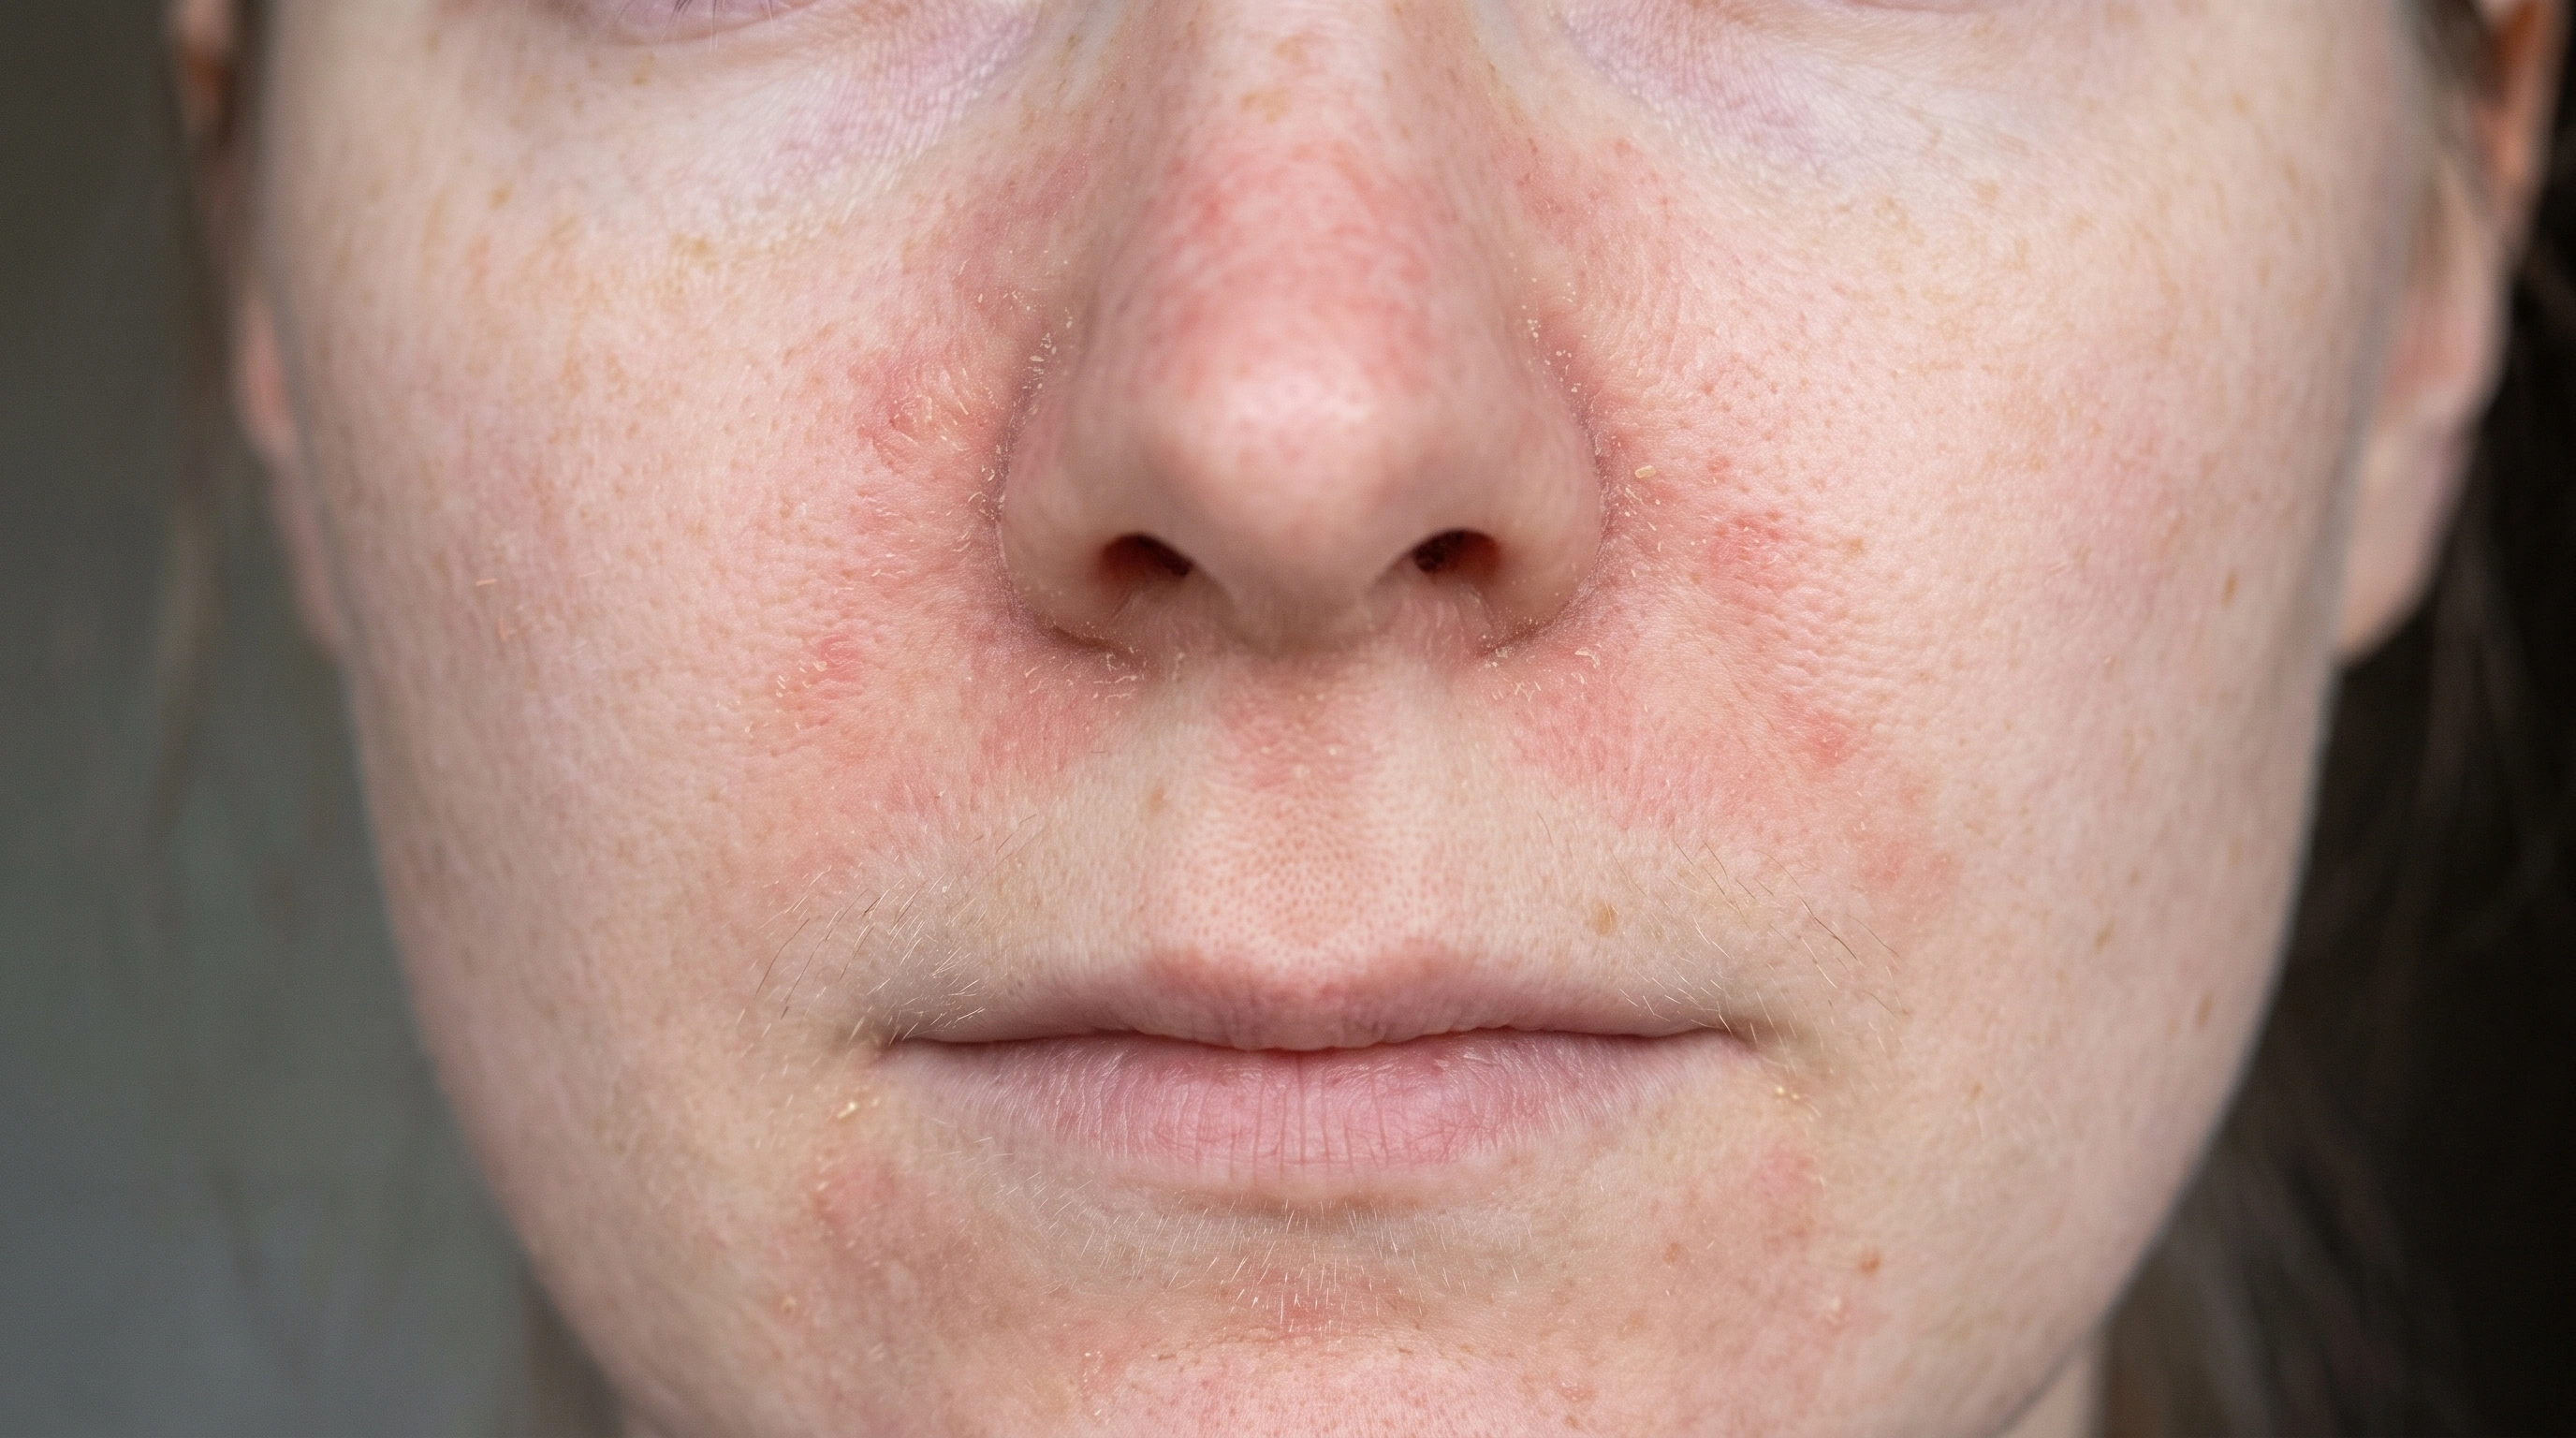



Inhibits calcineurin: Blocks a switch that helps activate T cells. Reduces immune messengers: T cells release fewer inflammation-driving signals. Calms eczema and itch: Redness and irritation ease as inflammation settles.
The drug binds FKBP-12 and inhibits calcineurin, reducing T-cell cytokine transcription; the complete atopic-dermatitis mechanism is not known. It also has other cellular effects.

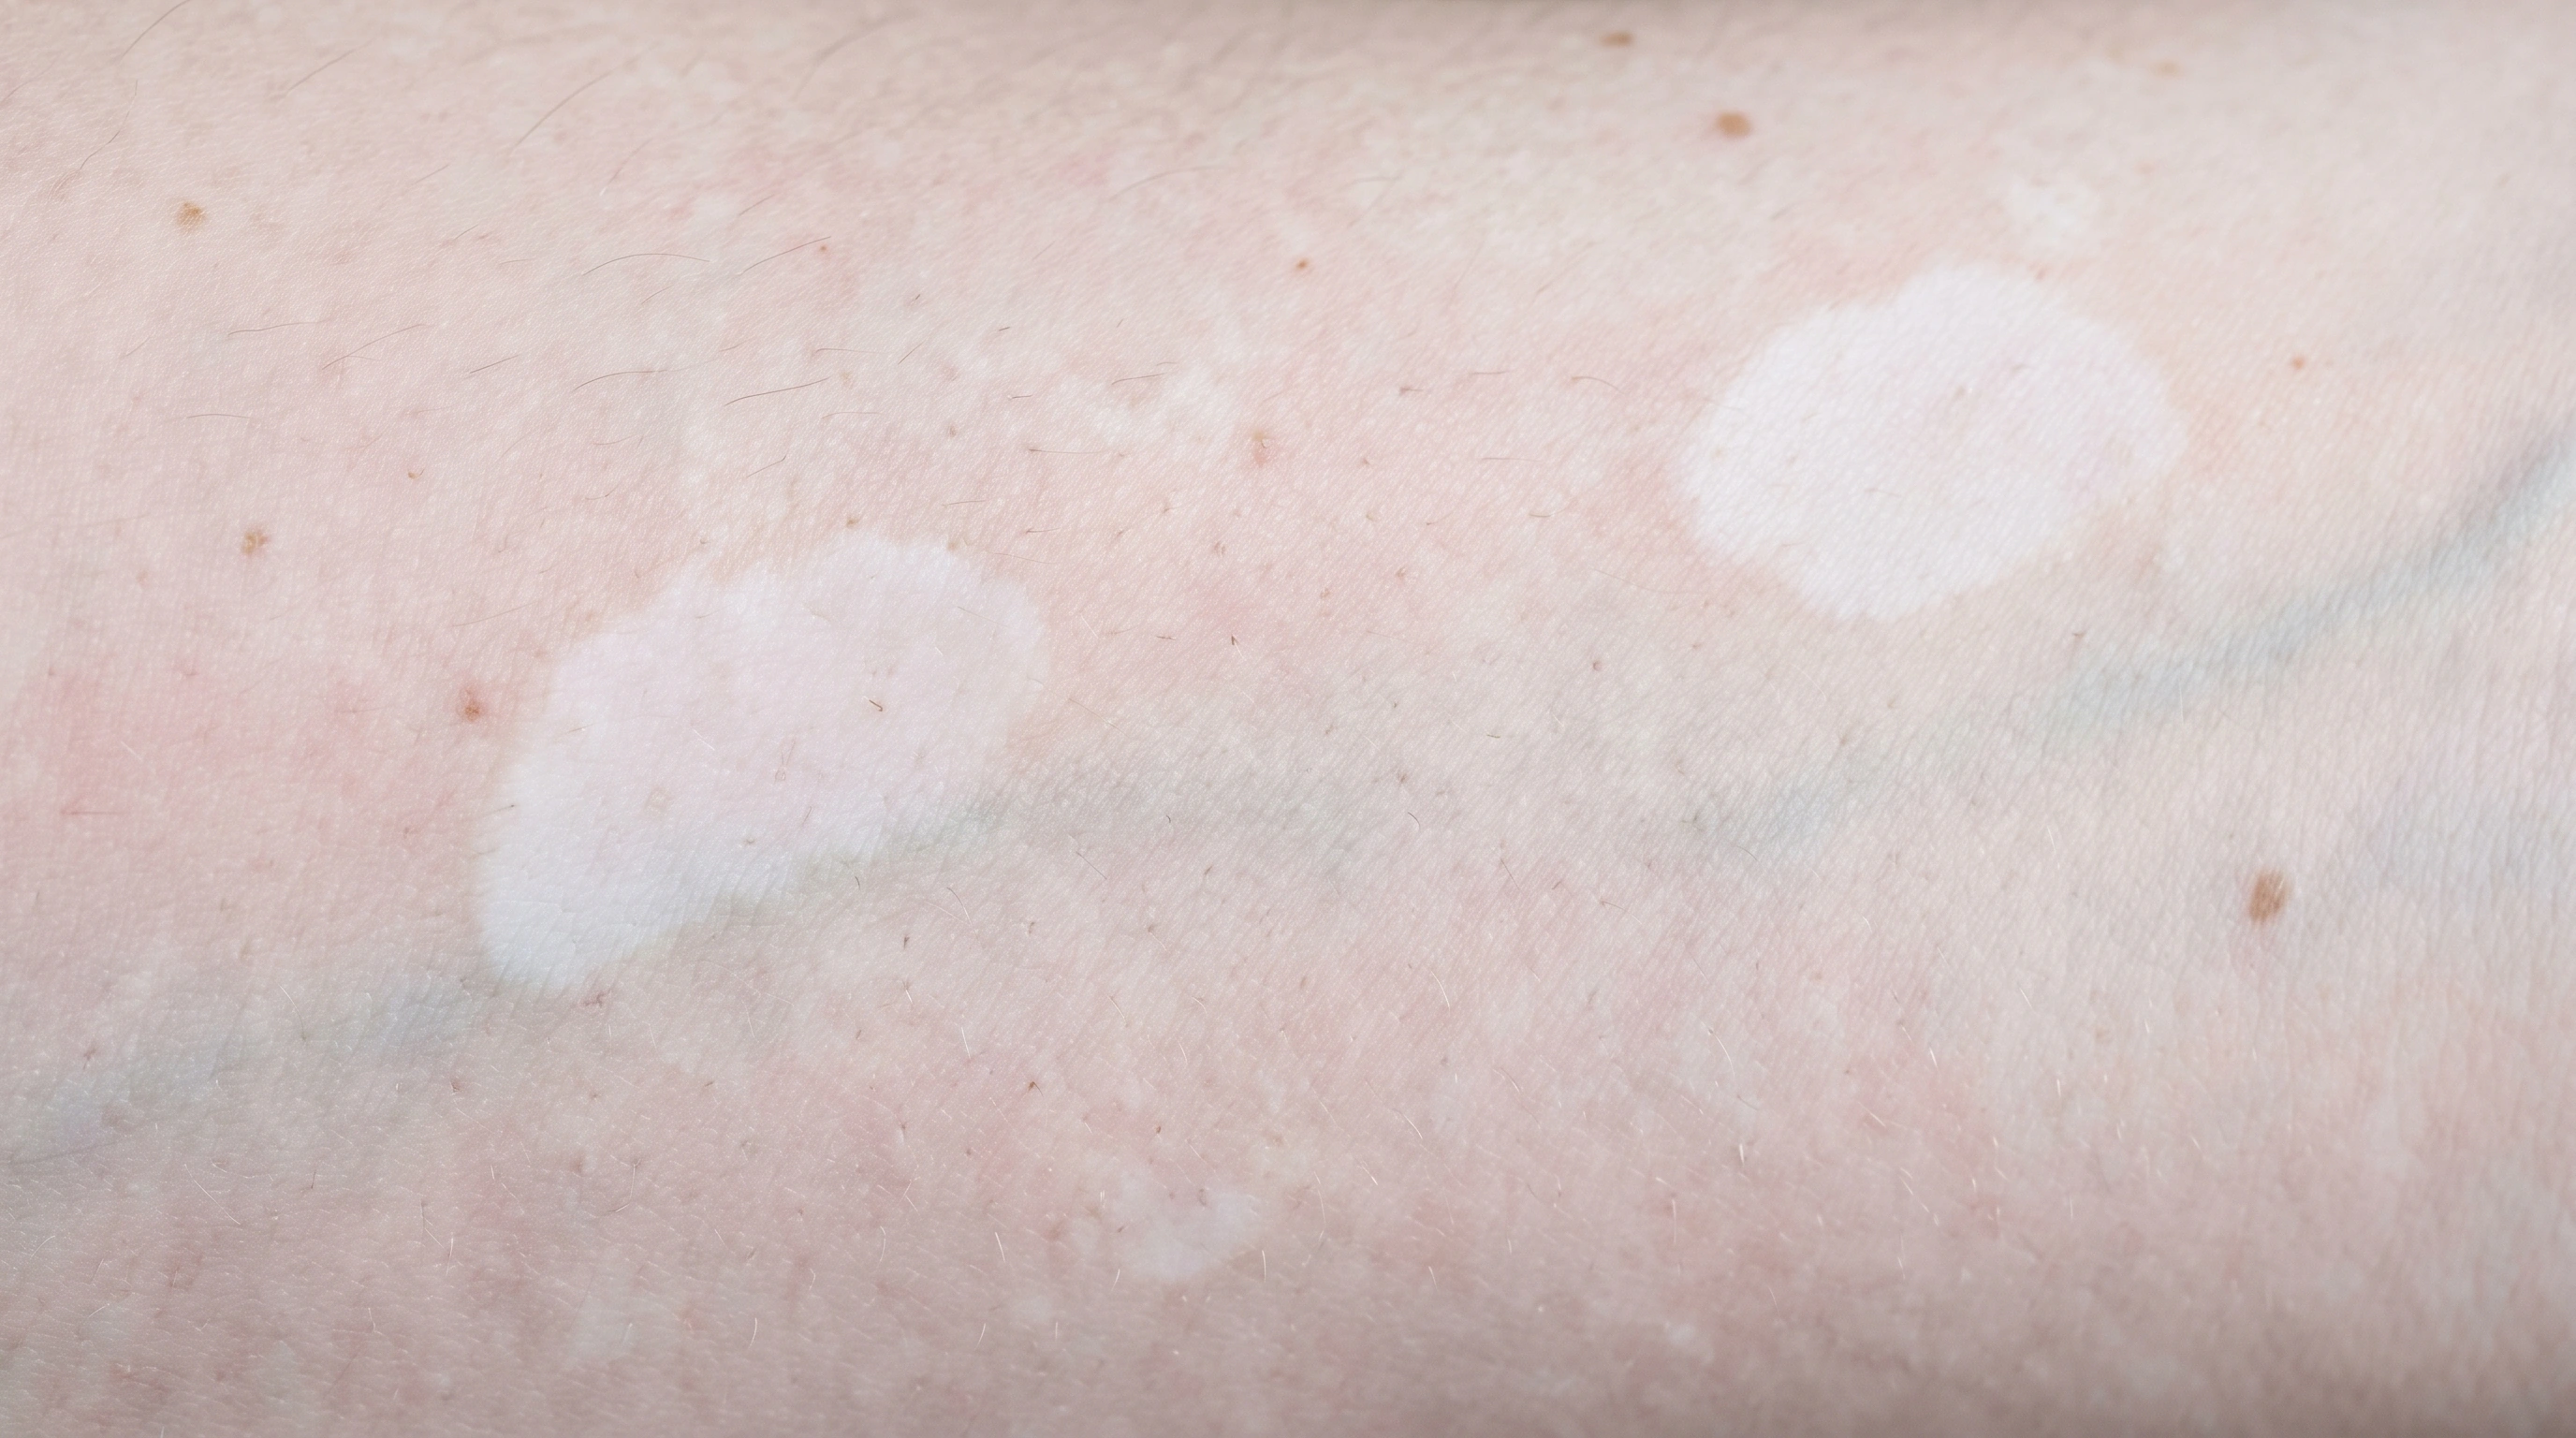
Blocks JAK1 and JAK2: Interrupts enzymes that relay inflammatory messages. Calms eczema and itch: Less inflammatory signaling helps irritated skin settle. Helps pigment return: In vitiligo, skin color can recover gradually.
JAK1/JAK2 inhibition is established; the relevance of individual JAK enzymes to therapeutic effectiveness is not fully known. Eczema improvement and vitiligo repigmentation are distinct outcomes, not guaranteed or immediate.
When to Apply: A thin layer twice a day on the affected skin. Rub it in until it disappears. Moisturizer can go on top or underneath.
How to Start: Twice daily as soon as a flare starts, and keep going until the skin is clear rather than merely better. Many people then move to two or three days a week on the spots that always come back, to head off the next flare. Discuss that with your doctor.
If It Irritates: Warmth, stinging or burning for the first few days is the commonest complaint. It happens because the skin is inflamed, not because you are allergic, and it usually stops within a week as the eczema settles. Keeping the cream in the fridge, moisturizing first, or starting once a day for a few days makes it easier.
If It's Not Working: Nothing to increase — there is one strength. Give it six weeks of consistent twice-daily use. If the skin is no better, the usual next steps are a short steroid course to reset it, a switch to tacrolimus ointment, or a newer non-steroid cream.
When to Apply: A thin layer twice a day, roughly twelve hours apart, on affected skin only. Wash your hands afterwards unless your hands are being treated. Two limits are on the label, not suggestions: no more than 20% of your body surface at a time, and no more than 60 grams a week, or 100 grams over two weeks. One palm is about 1% of your body surface.
How to Start: Twice daily from day one. For eczema, keep going until the skin is clear, then stop — the label calls it short-term, on-and-off treatment. For vitiligo it is the opposite: use it steadily. Stopping early is the usual reason it appears not to work.
If It Irritates: Redness, itch or a mild sting where you apply it is the usual early complaint and it settles. Acne or small bumps at the site is the other common one, most often on the face in vitiligo treatment, and it is treatable rather than a reason to stop. Moisturizing afterwards helps both.
If It's Not Working: For eczema, reassess at 8 weeks; if the skin is not clear, the label says stop and reconsider. For vitiligo, do not judge before 24 weeks. Repigmentation is slow, it starts on the face, and hands and feet may show very little for a long time. No change by about six months is when your doctor will usually add narrowband UVB light treatment.
No routine blood tests. Blood levels are very low or undetectable, and it does not affect the adrenal glands the way strong steroids do.
Monitoring is a conversation at six weeks, then longer intervals if you stay on it. Your doctor is checking whether the eczema is actually controlled, whether steroid rescue courses have been needed often enough to suggest a change of plan, and whether any patch of skin is behaving oddly rather than simply eczema.
Because of the boxed warning, most dermatologists look harder at any new or changing spot in long-term users rather than assuming it is part of the rash. Registry follow-up has not found the increase in skin cancer or lymphoma the warning anticipated, so this is ordinary caution, not surveillance for a known risk.
For most healthy people using it within the label limits, no routine blood tests are needed. Blood levels from the cream are very low, and the trials did not find the blood count or cholesterol changes the tablet causes.
Your doctor monitors the label's safety concerns by asking rather than testing. Expect questions about blood clots, heart attack or stroke, smoking, cancer, tuberculosis exposure, hepatitis, and whether anything else you take suppresses your immune system. This cream is not meant to be combined with other JAK inhibitors, biologics or strong immunosuppressants.
They will check the response on schedule — 8 weeks for eczema, 24 weeks and then longer for vitiligo — and ask about infections, unexplained fever, night sweats, weight loss, chest pain, breathlessness and leg swelling. Some doctors check blood counts and cholesterol at baseline in people with other risk factors.
Skin checks matter for a different reason — unpigmented skin burns easily, so an annual look at the skin is sensible regardless.
Approximate windows, not promises.
First few minutesApplying it: A thin layer twice a day. Warmth or stinging for a few minutes, strongest on the rawest skin.
First few minutesApplying it: A thin layer twice a day. Mild stinging or redness where you apply it is the usual side effect.
Days 1 to 5Adjusting: The stinging is at its worst now and fades as the skin heals. Itch often eases while the rash looks the same.
Weeks 1 to 2Working: Redness fades, skin feels less tight. Night scratching drops off first.
Weeks 2 to 6Judge it here: The rash flattens and clears. The fair point to decide whether it is doing enough.
Face, eyelids and foldsIts strongest use: Thin skin is where steroids cause the most trouble, so a non-thinning option is worth losing some strength. Armpits, groin and under the breasts thin quickly too.
OngoingHolding: Once clear, many drop to two or three applications a week on the areas that always flare. No thinning means no time limit.
Days 1 to 7Adjusting: For eczema, itch often improves within the first few days, sometimes the first day — among the quickest of any topical. For vitiligo, nothing visible yet.
Weeks 2 to 4Working, eczema: Redness fades and the rash flattens. Most of the eczema improvement happens here.
Weeks 4 to 8Judge it here, eczema: Week 8 is the fair point. If the skin is not clear, the label says stop and reconsider.
Weeks 8 to 24Working, vitiligo: The first sign is small pigmented dots inside a patch, often around hairs, which spread and join up. The face and neck move first, and around a third of people reach 75 percent repigmentation of the face by about six months.
Months 6 to 12 and beyondContinuing, vitiligo: By about a year roughly half reach that 75 percent mark on the face. The trunk and limbs are slower, and skin with hair does better, because surviving pigment cells live in hair follicles. Where vitiligo is still spreading, the cream helps hold the line.
ThroughoutWatch for: Acne or small bumps at the site. Report any fever, unusual infection, chest pain, breathlessness or swollen painful leg.
Sorted by what to do about them.
Cost has improved. Generic pimecrolimus cream brought the price down from one of the more expensive eczema treatments to something ordinary. Brand-name Elidel is still costly.
The usual obstacle is not price but step therapy. Because the label calls it second-line, many plans want to see that a topical steroid was tried and failed, or a reason a steroid should not be used, before covering it. A note from your doctor saying the eczema is on the eyelids or in the folds usually settles that.
Cash prices for the generic vary between pharmacies more than most drugs, so check a discount card price before assuming you cannot afford it. Tube size matters too — a large tube is often better value per gram, and eczema treatment runs longer than people expect.
Cost is the honest sticking point. Ruxolitinib cream is brand only with no generic, and a 60-gram tube lists at a few thousand dollars. Since a tube is one week's maximum, sustained use is expensive at list price.
Almost nobody pays that, but almost everybody has to work for coverage. A prior authorization is standard. For eczema, plans typically want a topical steroid and often a calcineurin inhibitor tried first. For vitiligo, coverage has been harder because some plans treat it as cosmetic — a letter from your dermatologist explaining that vitiligo is an autoimmune disease with real medical and psychological effects is usually what turns that around. Denials are frequently overturned on appeal.
The manufacturer runs a copay program that can cut the cost a lot with commercial insurance, plus patient assistance for people who qualify. Terms change often. People on government insurance are usually not eligible for copay cards, which is a real gap.
One practical point: the drug is priced by the tube, so treating only the areas that need it is a cost decision as well as a safety rule.
No. Different pathway, and it does not thin the skin — the whole reason it is used on eyelids, the face and skin folds.
Because at approval regulators noted that related medicines suppress immunity body-wide in transplant patients, that very high oral doses caused tumors in animals, and that a small number of cancer reports existed in users. The warning states that long-term safety is not established — a precaution, not a finding. Follow-up since has not shown an increased rate of skin cancer or lymphoma.
Because the skin underneath is inflamed. It is the commonest side effect, strongest in the first few days, and it settles as the eczema heals. Moisturizing first or chilling the tube helps.
No fixed limit. It does not thin skin, so it can run in repeated courses, or two or three times a week, for years with review.
Yes — eyelids are one of its main uses, one of the few anti-inflammatory options that can go there repeatedly without thinning skin or raising eye pressure.
No. Tacrolimus 0.1% ointment is more powerful for moderate eczema. Pimecrolimus is better tolerated and cosmetically easier, so it is often the one people keep using.
Most people see the first small pigmented dots between two and six months, usually on the face and often around hairs. Twenty-four weeks is the earliest fair point to judge, and results keep improving past a year.
Regulators applied it to the whole drug class after a large safety study of a JAK tablet in older people with rheumatoid arthritis and heart risk factors found more heart events, clots, infections and cancers. The cream's own trials did not show those events, and blood levels from a cream within the limits are a small fraction of a tablet dose.
That limit and the 60 grams a week cap keep the amount reaching your bloodstream low. It is why the safety picture for the cream differs from the tablet.
Pigment that has returned usually stays, but the immune attack can restart and patches can begin losing color again. Most people continue treatment or reduce it gradually rather than stopping outright.
Acne at the application site is a recognized side effect, most often on the face during vitiligo treatment. It is treatable and not a reason to stop.
Less well, and more slowly. Areas with few hair follicles have fewer surviving pigment cells to repopulate the skin. The face is where this cream does its best work.
A common combination, often more effective than either alone, but plan it with your dermatologist rather than starting on your own.