Eczema
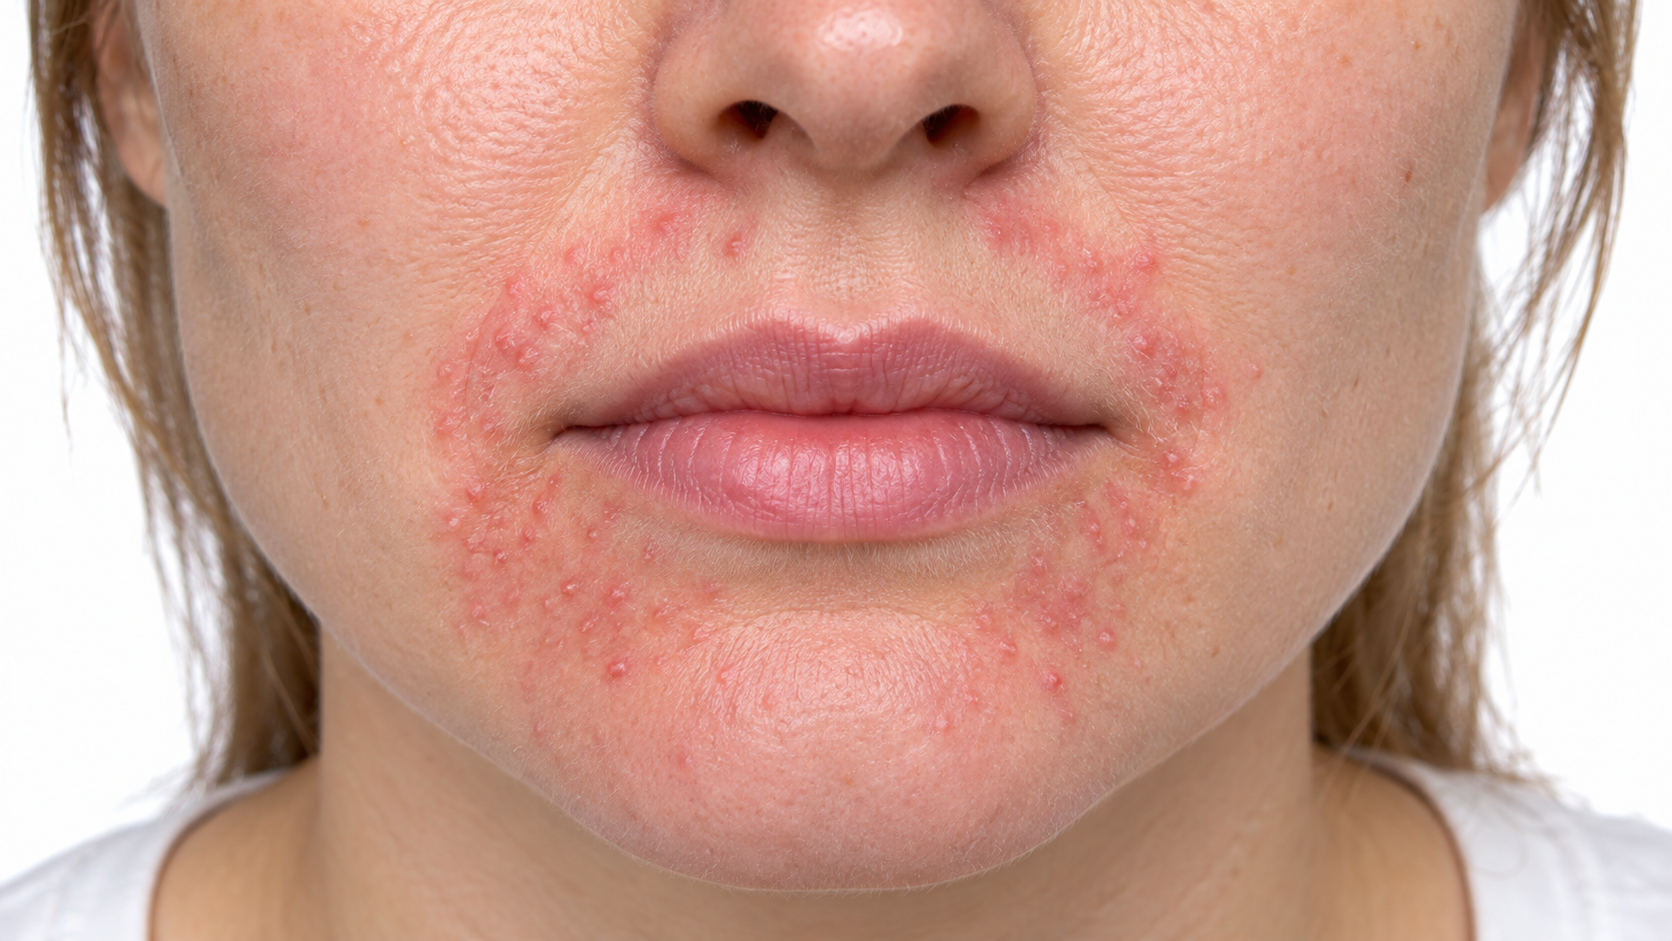
Calms mild flares, including on the face.
Desonide: A low-potency prescription steroid made for delicate skin. It is the usual step up from hydrocortisone for the face, the folds and young children. Elidel: A steroid-free anti-inflammatory cream for eczema. It calms the immune reaction in the skin without thinning it, which is why it is used on the face, eyelids and skin folds.


Choose as the step up from hydrocortisone for delicate skin — face, eyelids, folds and babies.
Choose for eczema on delicate skin — face, eyelids, folds — when you want to avoid steroid thinning.
Can you take them together?
A common pairing for facial eczema: desonide for short flares, Elidel for steroid-free maintenance between them.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.
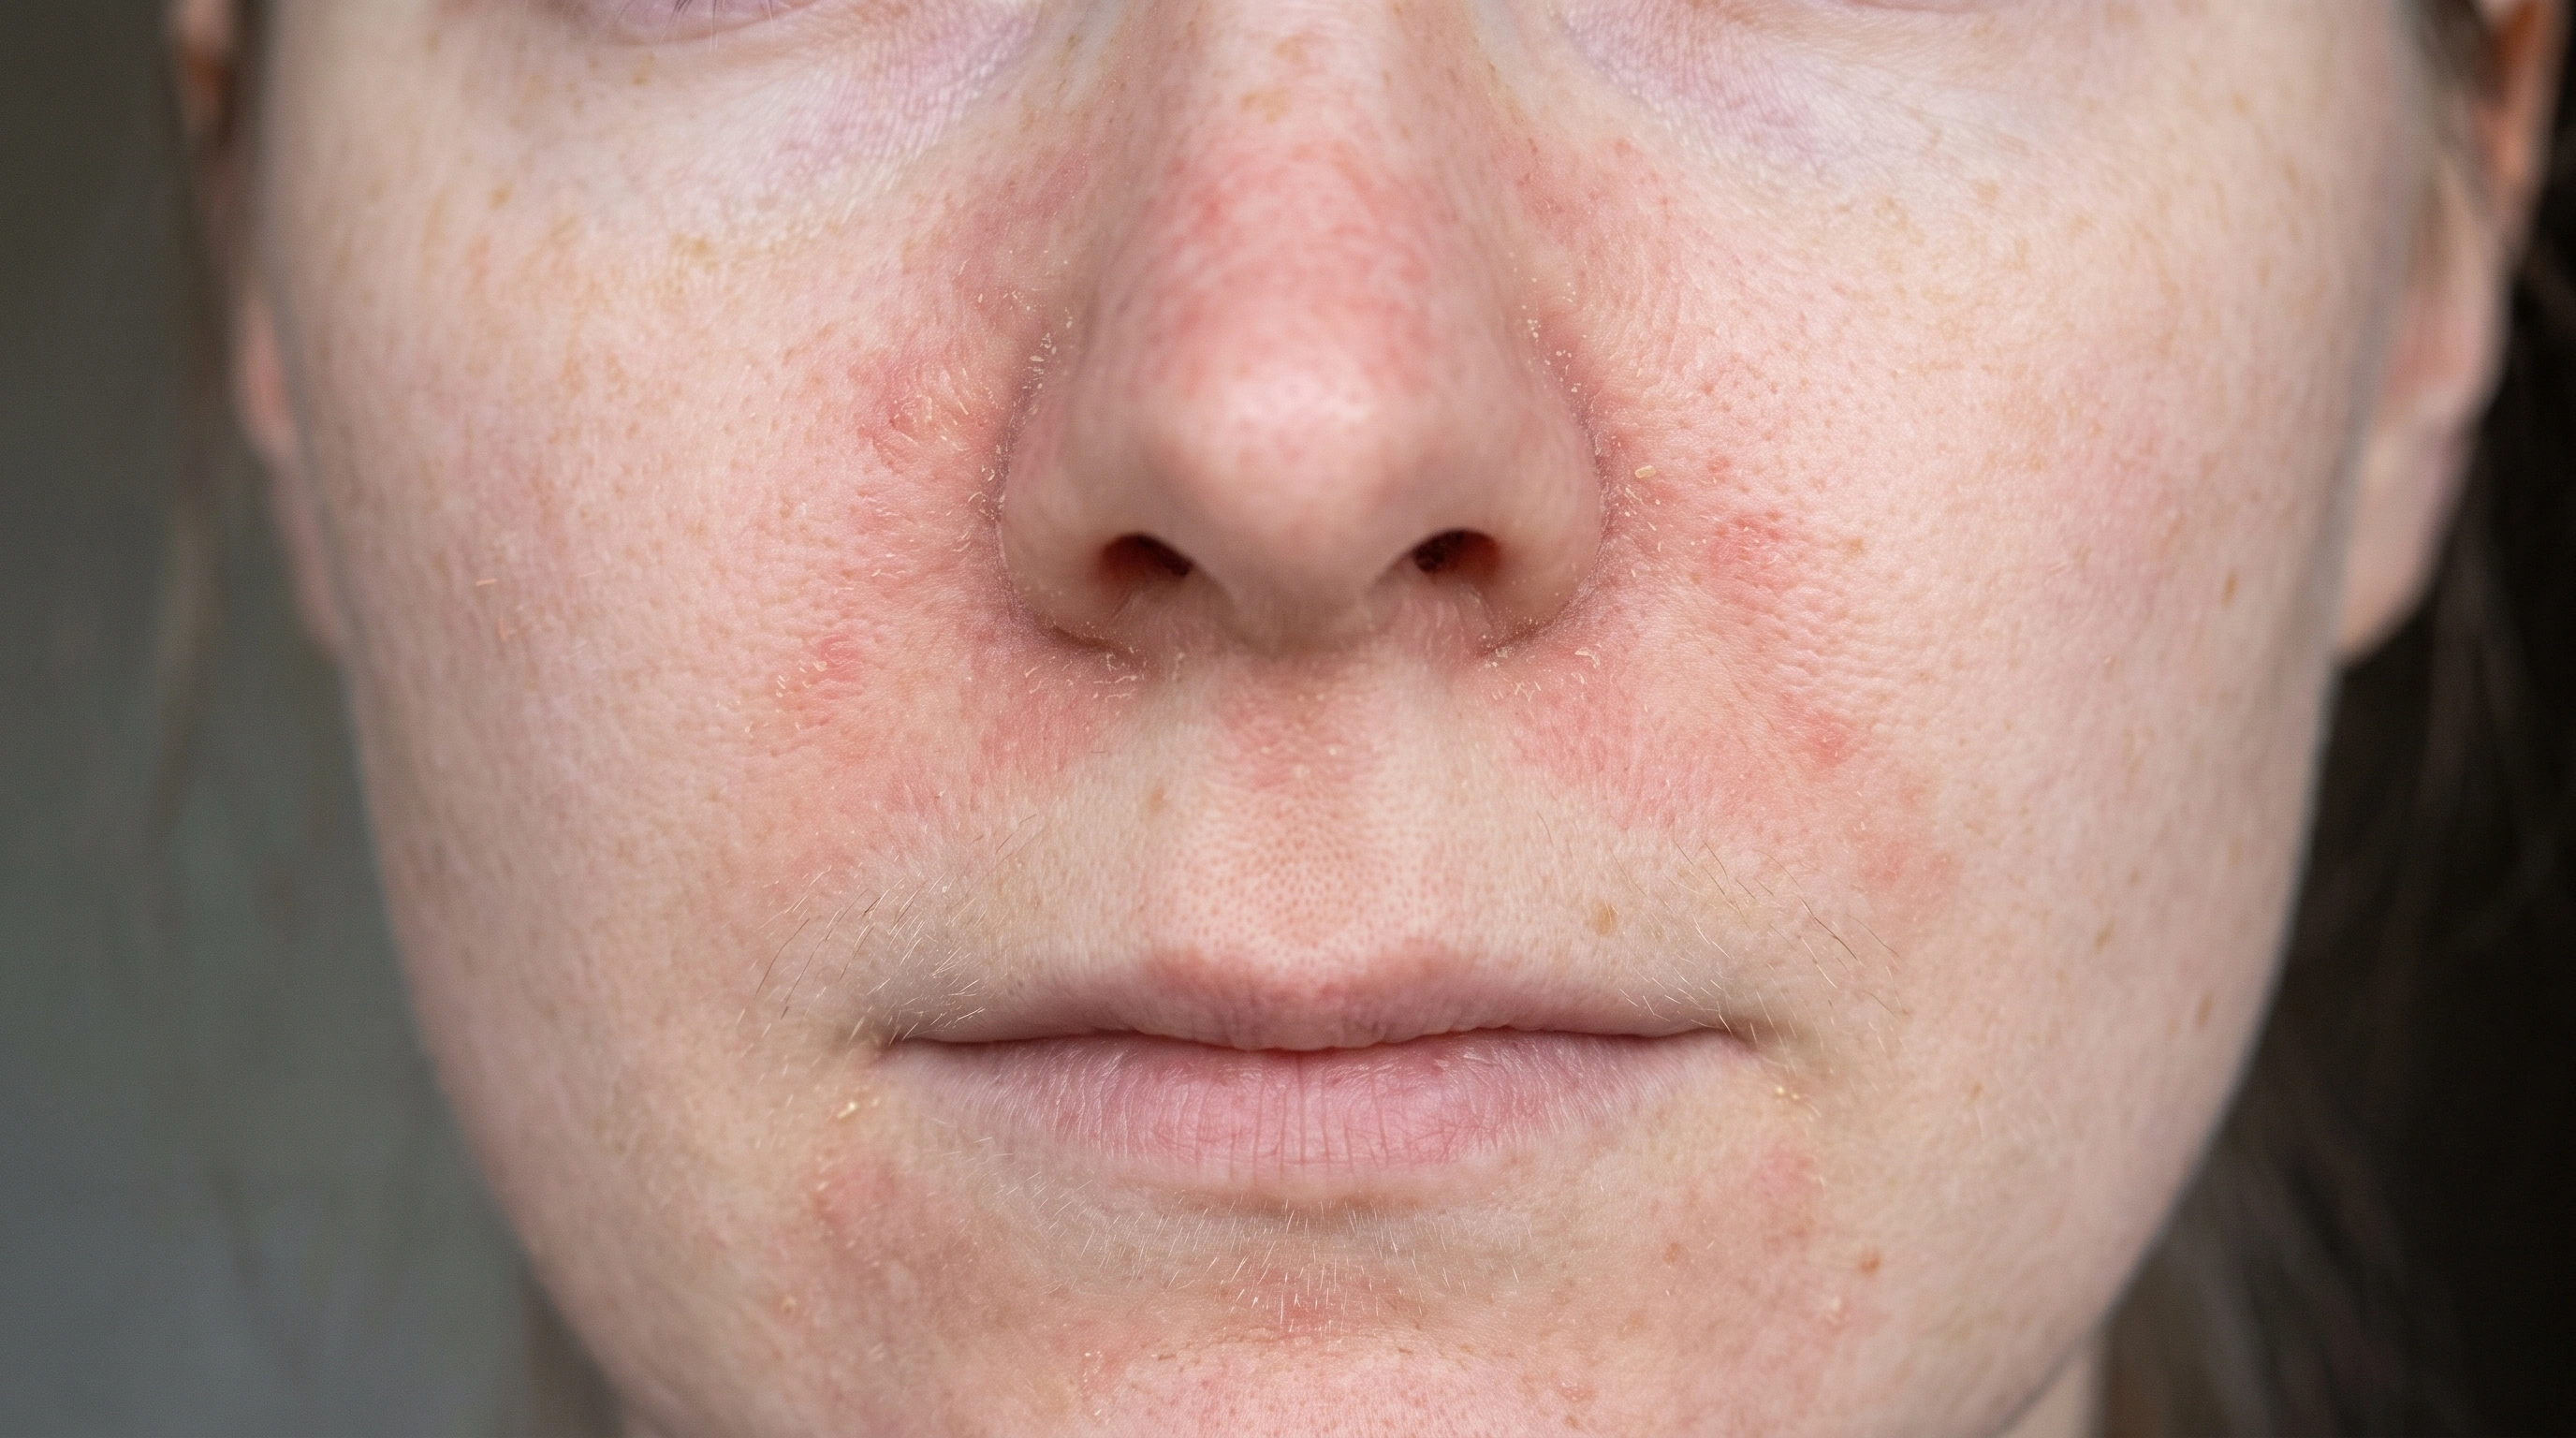
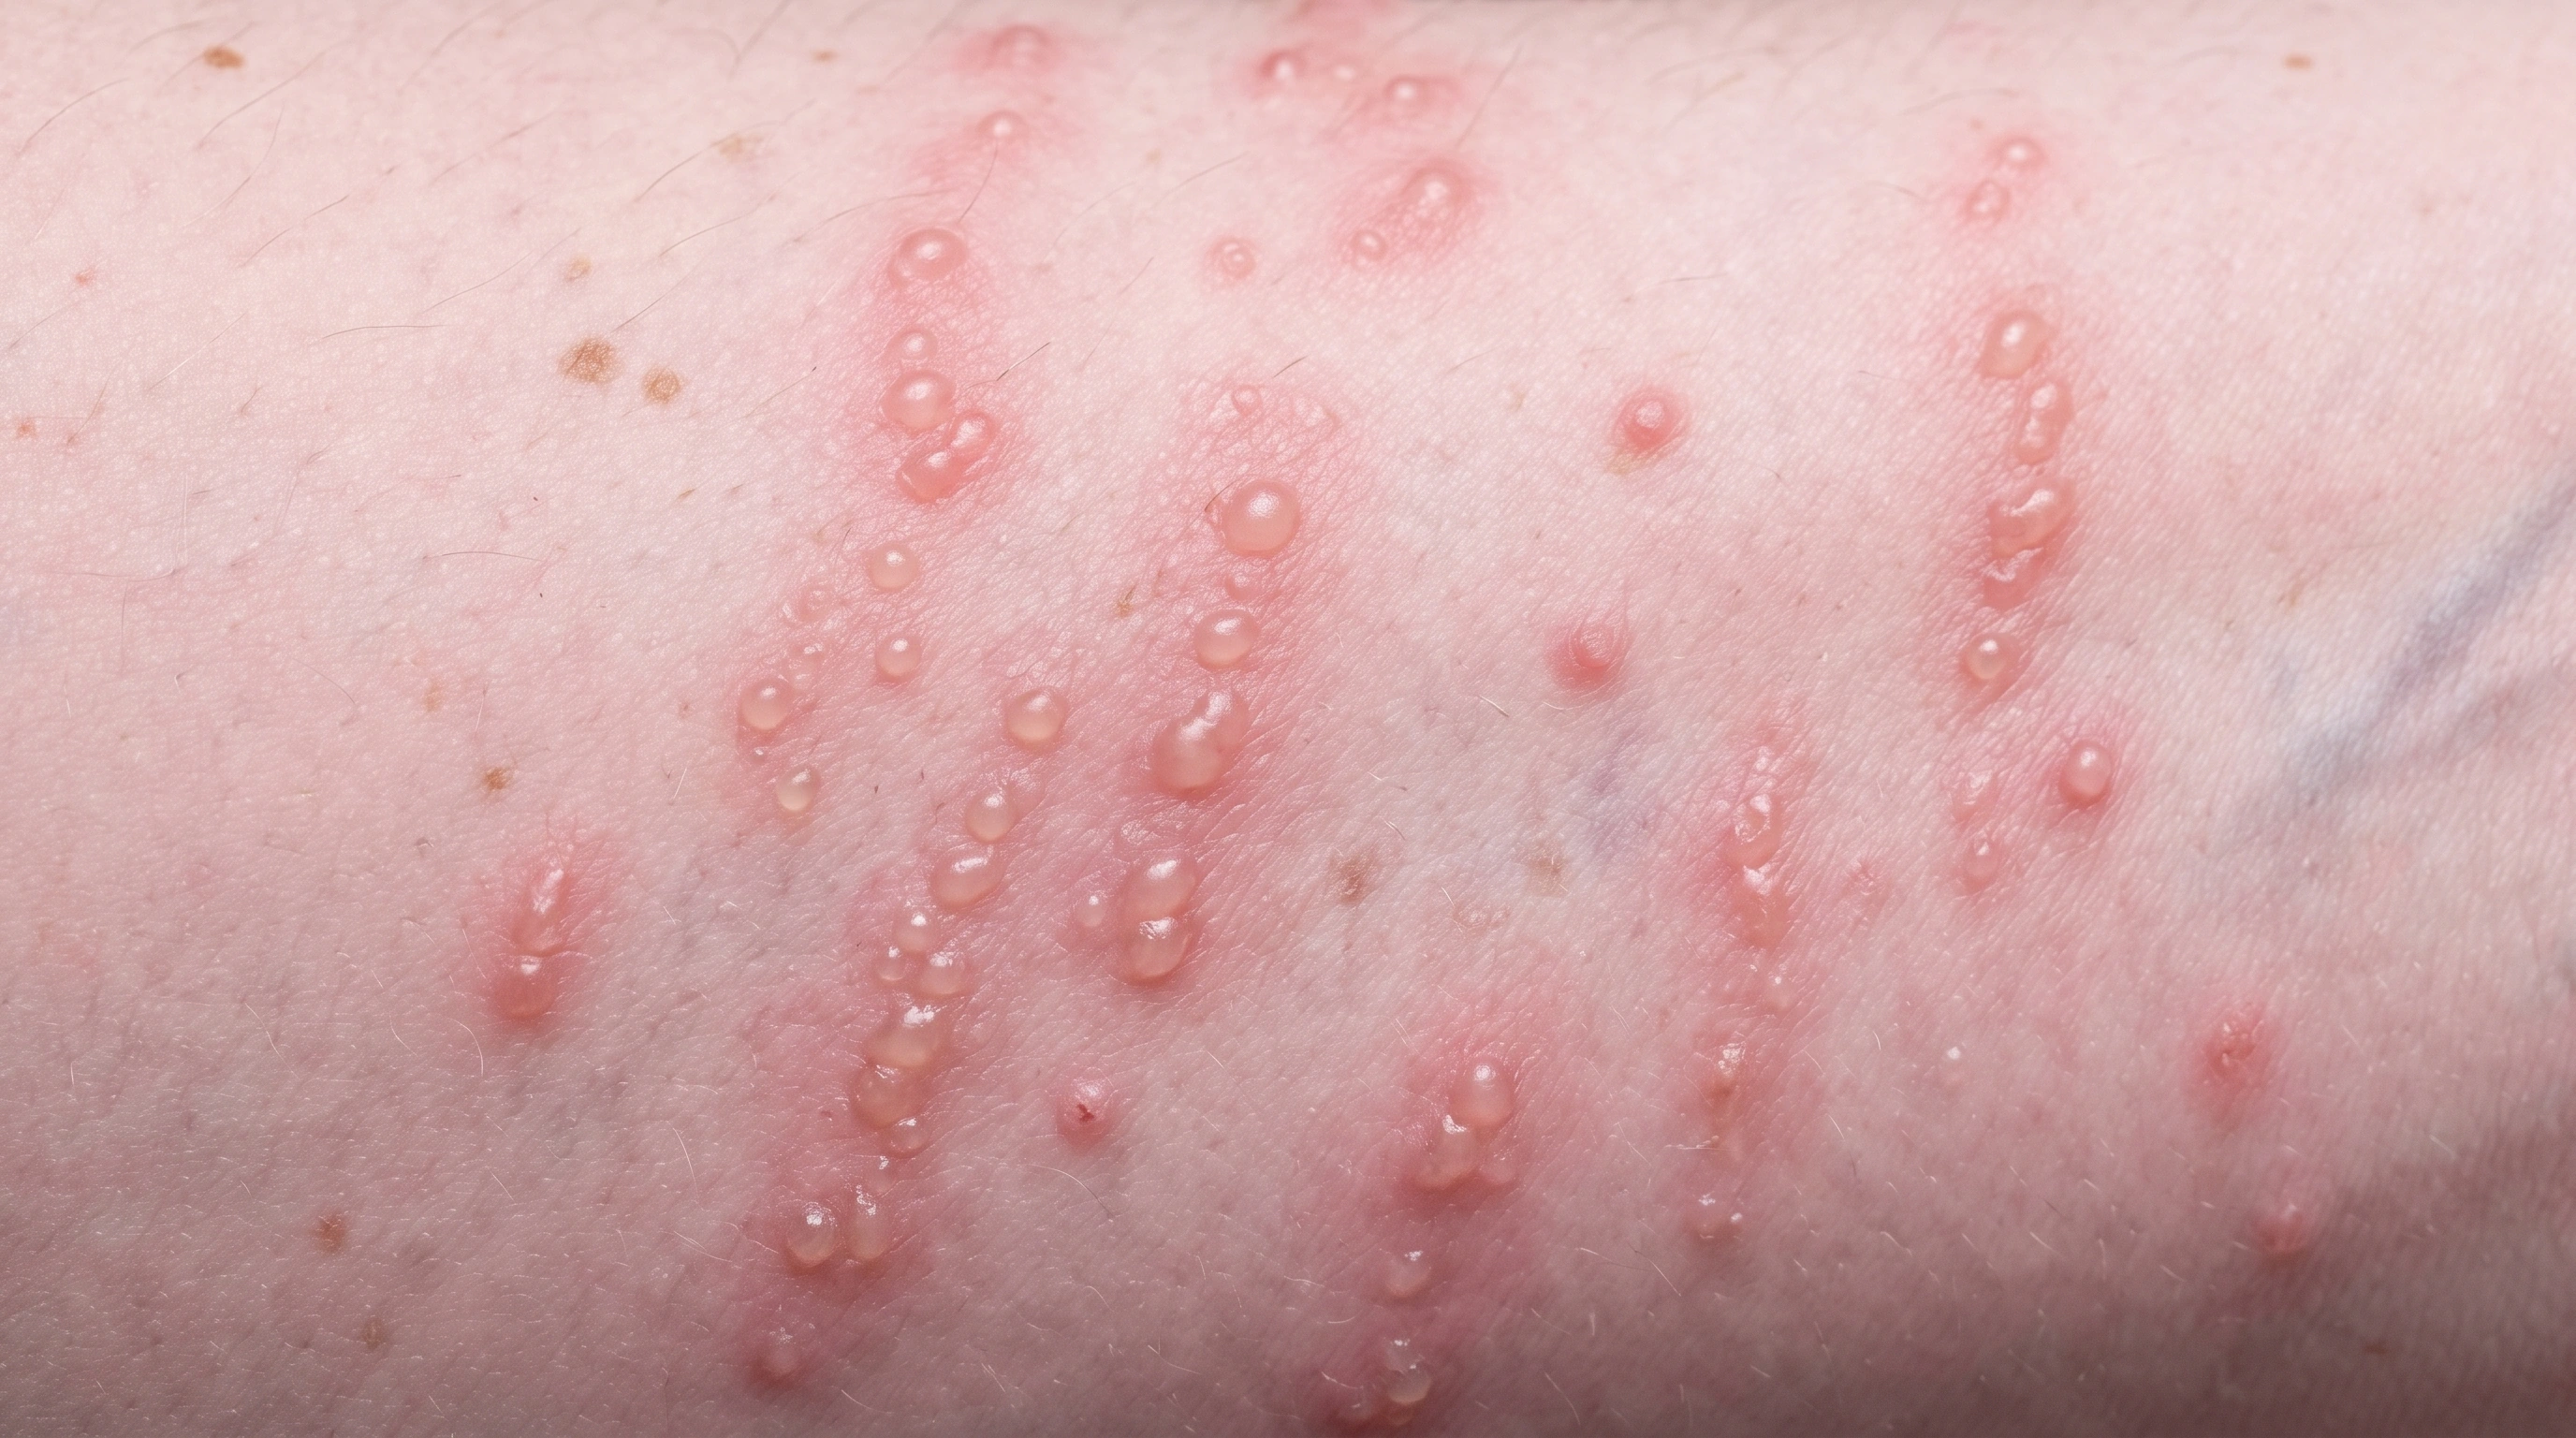
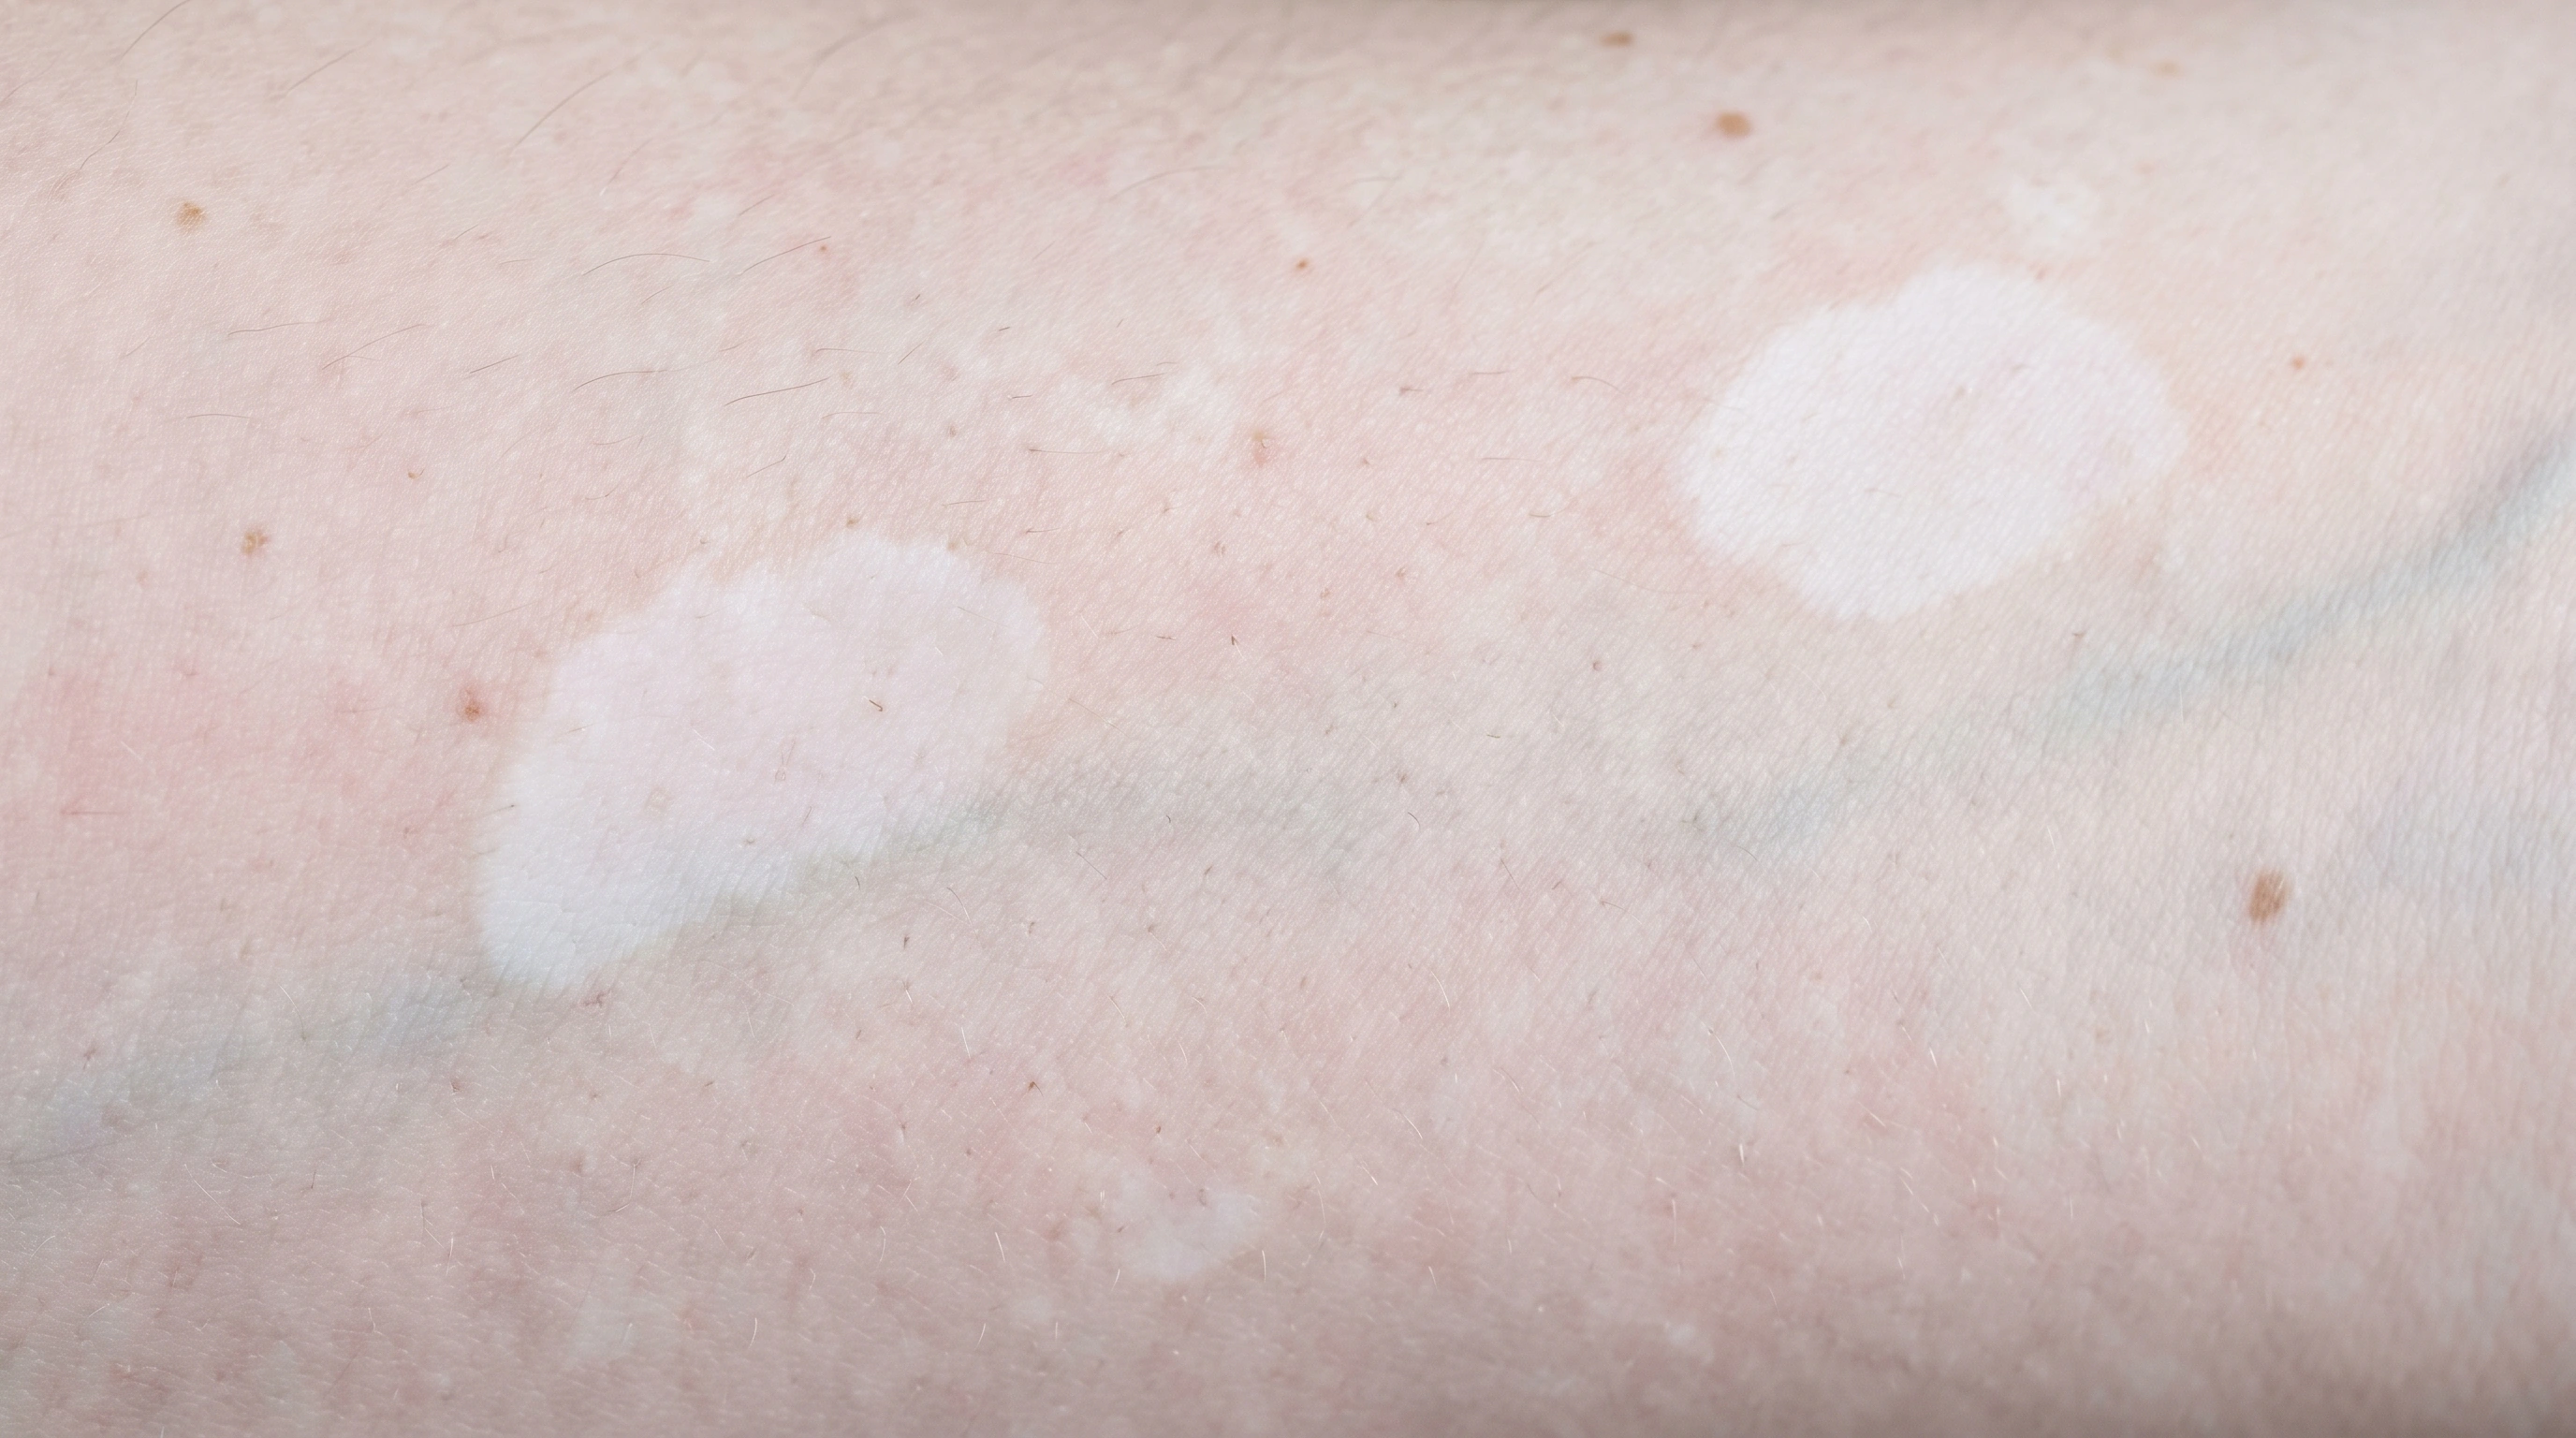



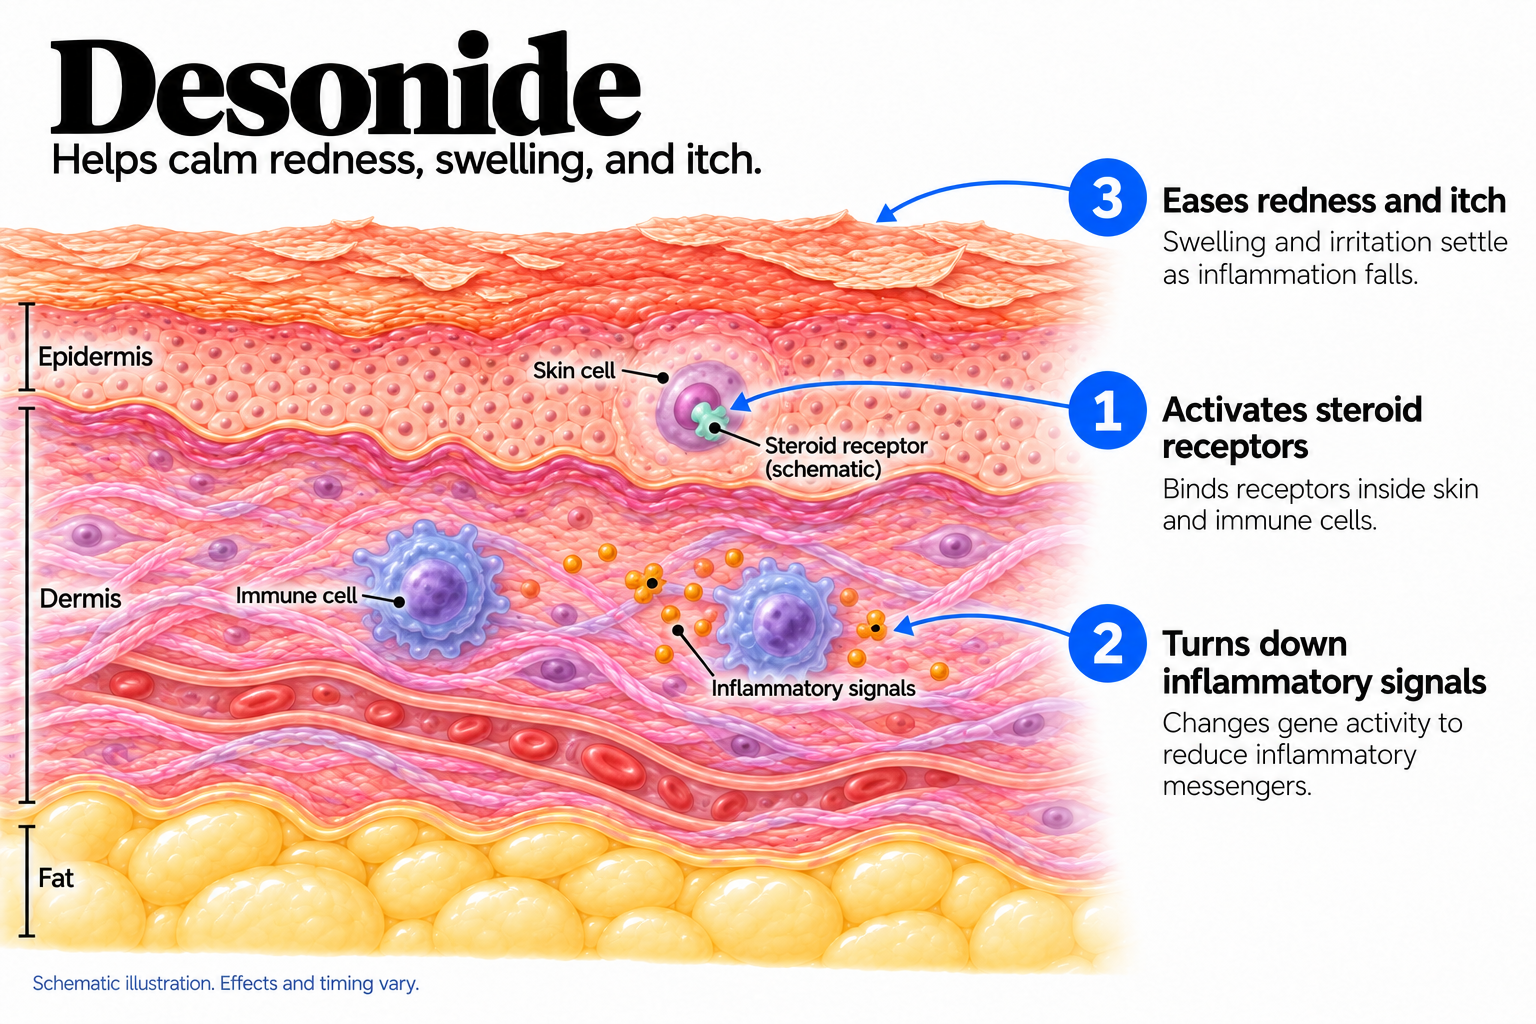
Activates steroid receptors: Binds receptors inside skin and immune cells. Turns down inflammatory signals: Changes gene activity to reduce inflammatory messengers. Eases redness and itch: Swelling and irritation settle as inflammation falls.
Simplified glucocorticoid receptor-mediated effects in steroid-responsive skin inflammation. Full effects also involve other pathways. No claim of antimicrobial action or cure; formulation and potency affect clinical use.

Inhibits calcineurin: Blocks a switch that helps activate T cells. Reduces immune messengers: T cells release fewer inflammation-driving signals. Calms eczema and itch: Redness and irritation ease as inflammation settles.
The drug binds FKBP-12 and inhibits calcineurin, reducing T-cell cytokine transcription; the complete atopic-dermatitis mechanism is not known. It also has other cellular effects.
When to Apply: Twice a day on the affected skin only, in a thin film. One fingertip unit, the amount along the last joint of an adult index finger, covers about two adult palms. Moisturizer goes on separately and continues after the course ends.
How to Start: Twice daily from day one until the rash is flat, not just calmer, usually one to two weeks. Two weeks is the usual limit on a face, up to four weeks on the body before review. In children, follow the prescriber's duration, not the size of the tube.
If It Irritates: Stinging is usually the base, not the drug, and likelier on broken skin or with an alcohol-containing gel or foam. The ointment settles it. Redness or itch that worsens over a week or two can be allergy to the steroid or a preservative, and needs a different product.
If It Is Not Working: Two weeks of proper twice-daily use is a fair test. If nothing changed, question the diagnosis, look for infection, and ask whether the site can take a stronger steroid. On thin skin the better next step is often a non-steroid such as tacrolimus.
When to Apply: A thin layer twice a day on the affected skin. Rub it in until it disappears. Moisturizer can go on top or underneath.
How to Start: Twice daily as soon as a flare starts, and keep going until the skin is clear rather than merely better. Many people then move to two or three days a week on the spots that always come back, to head off the next flare. Discuss that with your doctor.
If It Irritates: Warmth, stinging or burning for the first few days is the commonest complaint. It happens because the skin is inflamed, not because you are allergic, and it usually stops within a week as the eczema settles. Keeping the cream in the fridge, moisturizing first, or starting once a day for a few days makes it easier.
If It's Not Working: Nothing to increase — there is one strength. Give it six weeks of consistent twice-daily use. If the skin is no better, the usual next steps are a short steroid course to reset it, a switch to tacrolimus ointment, or a newer non-steroid cream.
No blood tests for a standard course in a healthy person. Monitoring is looking at the skin: did the rash clear, has the skin become thin or shiny, have small vessels or stretch marks appeared in the folds.
Children are watched more closely, not because desonide is dangerous but because they absorb proportionally more for their size. Prescribers watch how much is used per month, and whether a repeat pattern has quietly become daily use.
Low potency does not mean indefinite. Where a condition keeps flaring, the plan is short courses on flares with emollients doing the daily work, or a switch to a non-steroid such as tacrolimus or pimecrolimus for the face and folds. Around the eyes, prolonged steroid use of any potency raises the risk of glaucoma and cataract.
No routine blood tests. Blood levels are very low or undetectable, and it does not affect the adrenal glands the way strong steroids do.
Monitoring is a conversation at six weeks, then longer intervals if you stay on it. Your doctor is checking whether the eczema is actually controlled, whether steroid rescue courses have been needed often enough to suggest a change of plan, and whether any patch of skin is behaving oddly rather than simply eczema.
Because of the boxed warning, most dermatologists look harder at any new or changing spot in long-term users rather than assuming it is part of the rash. Registry follow-up has not found the increase in skin cancer or lymphoma the warning anticipated, so this is ordinary caution, not surveillance for a known risk.
Approximate windows, not promises.
First few minutesApplying it: A thin layer on the affected skin. Low potency, which suits the face, the eyelids and small children.
First few minutesApplying it: A thin layer twice a day. Warmth or stinging for a few minutes, strongest on the rawest skin.
Days 1 to 3Itch first: Itching and stinging settle before the rash looks different, which is often what lets a child sleep.
Days 3 to 10Clearing: Redness fades and rough or weeping skin settles. Most facial flares are largely better here.
Weeks 1 to 2Judge it here: On the face, stop and reassess here. Facial and eyelid eczema settle without the thinning risk a stronger steroid carries, and seborrheic dermatitis improves in the same window.
Weeks 1 to 2Working: Redness fades, skin feels less tight. Night scratching drops off first.
Weeks 2 to 4Folds and the body: Intertrigo and fold rashes respond, and the mildness suits a site that absorbs heavily; any yeast needs treating too. On the body, about four weeks before review.
After stoppingMarks stay behind: Brown or gray patches where the rash was are pigment change, not scarring, and fade over weeks to months.
Days 1 to 5Adjusting: The stinging is at its worst now and fades as the skin heals. Itch often eases while the rash looks the same.
Weeks 2 to 6Judge it here: The rash flattens and clears. The fair point to decide whether it is doing enough.
Face, eyelids and foldsIts strongest use: Thin skin is where steroids cause the most trouble, so a non-thinning option is worth losing some strength. Armpits, groin and under the breasts thin quickly too.
OngoingHolding: Once clear, many drop to two or three applications a week on the areas that always flare. No thinning means no time limit.
Sorted by what to do about them.
Generic desonide cream, ointment and lotion are cheap and well covered. The branded gel and foam, easier to use on faces and hairy areas, cost considerably more, and plans often ask for a generic first.
It costs more than over-the-counter hydrocortisone, which needs no visit, and less than non-steroids like tacrolimus or crisaborole. If cost is a barrier, start with the cream or ointment.
Cost has improved. Generic pimecrolimus cream brought the price down from one of the more expensive eczema treatments to something ordinary. Brand-name Elidel is still costly.
The usual obstacle is not price but step therapy. Because the label calls it second-line, many plans want to see that a topical steroid was tried and failed, or a reason a steroid should not be used, before covering it. A note from your doctor saying the eczema is on the eyelids or in the folds usually settles that.
Cash prices for the generic vary between pharmacies more than most drugs, so check a discount card price before assuming you cannot afford it. Tube size matters too — a large tube is often better value per gram, and eczema treatment runs longer than people expect.
Yes, by a step or two, and both are low potency. Well below mid-potency steroids like triamcinolone.
That is largely what it is for. Keep courses to about two weeks and stop once the rash is flat. Repeated face use is a reason to ask about a non-steroid.
A common choice in children, and some formulations are approved from a few months of age. Follow the prescriber's duration, and remember a diaper acts as a dressing.
A short course at this potency is unlikely to. Thinning comes from stronger steroids, thin sites and long use. Untreated eczema has its own costs: months of scratching and more pigment change.
It can, less readily than stronger steroids. Pale patches show more on deeper skin tones and recover slowly. Untreated inflammation also leaves light and dark marks.
Several steps of potency. Triamcinolone on a face or in a fold for two weeks can cause thinning and stretch marks desonide would not. Matching steroid to site is why both exist.
No. Different pathway, and it does not thin the skin — the whole reason it is used on eyelids, the face and skin folds.
Because at approval regulators noted that related medicines suppress immunity body-wide in transplant patients, that very high oral doses caused tumors in animals, and that a small number of cancer reports existed in users. The warning states that long-term safety is not established — a precaution, not a finding. Follow-up since has not shown an increased rate of skin cancer or lymphoma.
Because the skin underneath is inflamed. It is the commonest side effect, strongest in the first few days, and it settles as the eczema heals. Moisturizing first or chilling the tube helps.
No fixed limit. It does not thin skin, so it can run in repeated courses, or two or three times a week, for years with review.
Yes — eyelids are one of its main uses, one of the few anti-inflammatory options that can go there repeatedly without thinning skin or raising eye pressure.
No. Tacrolimus 0.1% ointment is more powerful for moderate eczema. Pimecrolimus is better tolerated and cosmetically easier, so it is often the one people keep using.