Steroid Acne vs Steroid Rosacea

A uniform acne-like eruption associated with systemic corticosteroids or anabolic steroids. A burning rosacea-like facial eruption caused by potent topical steroids or their withdrawal.
Research updated 2026-10-23
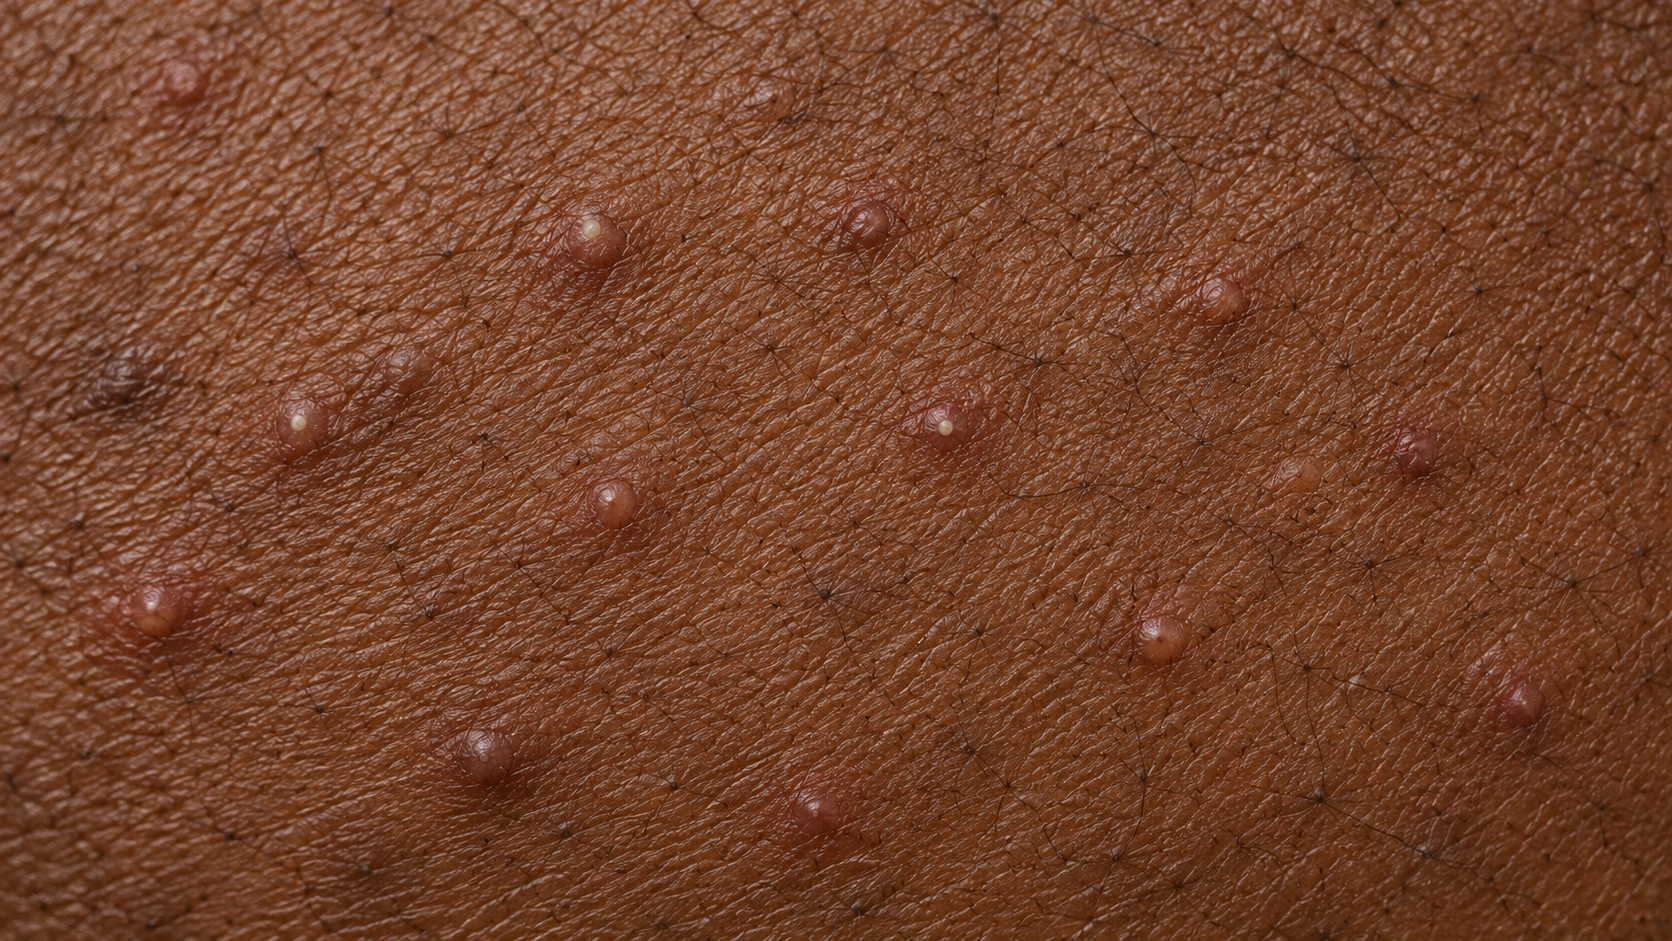
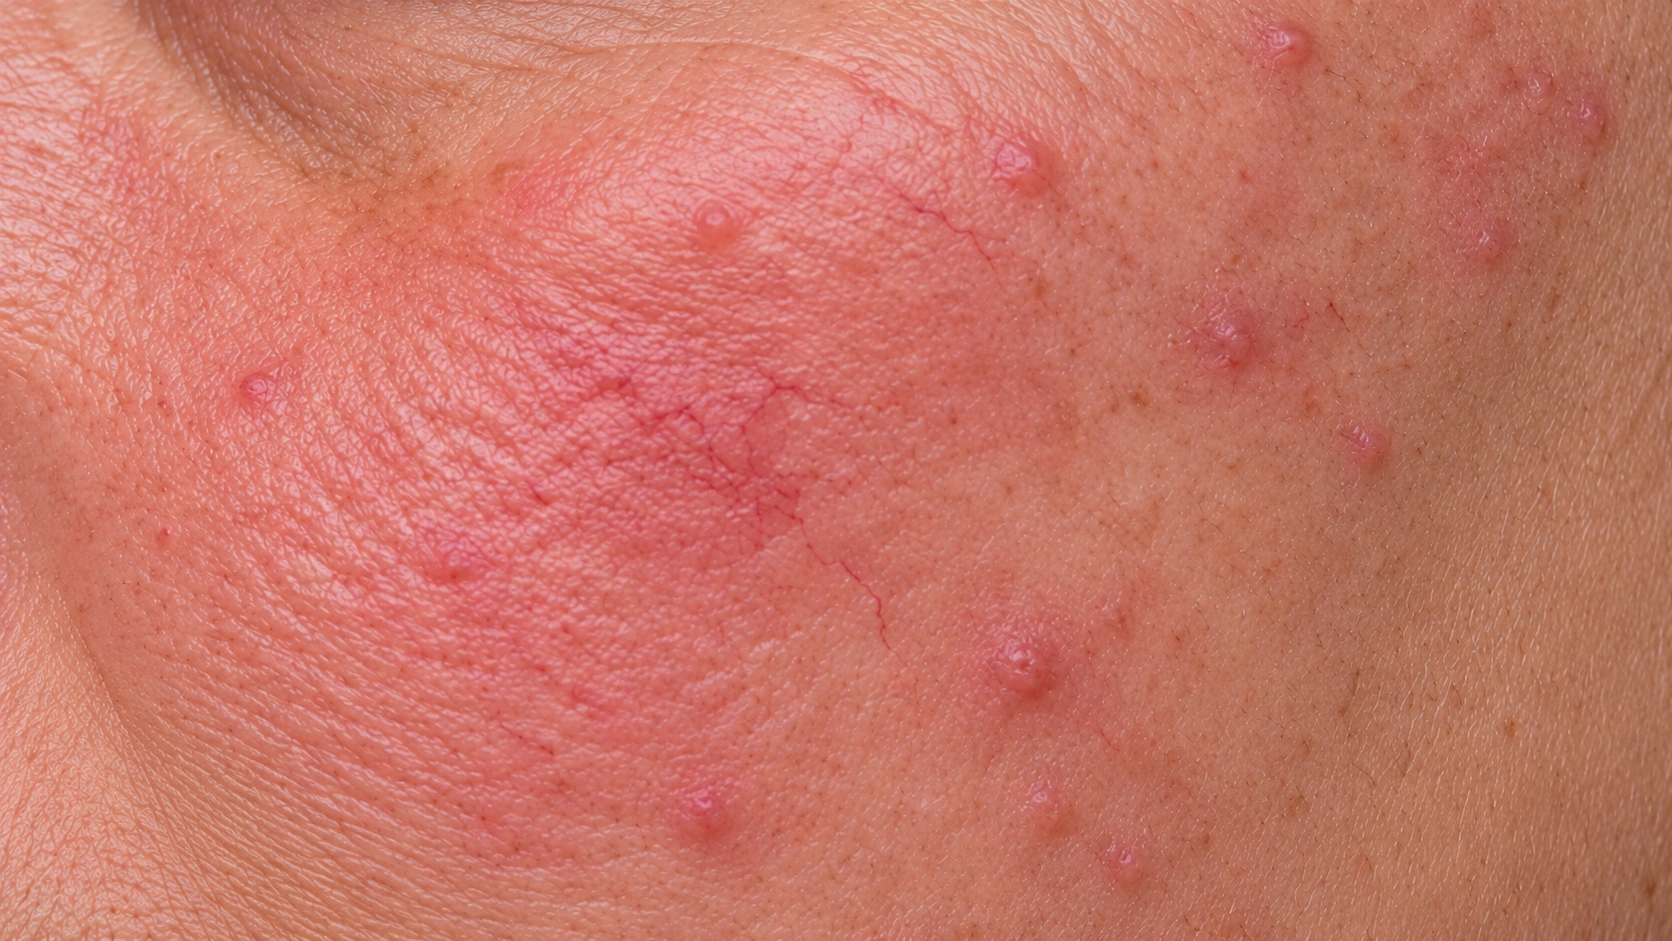
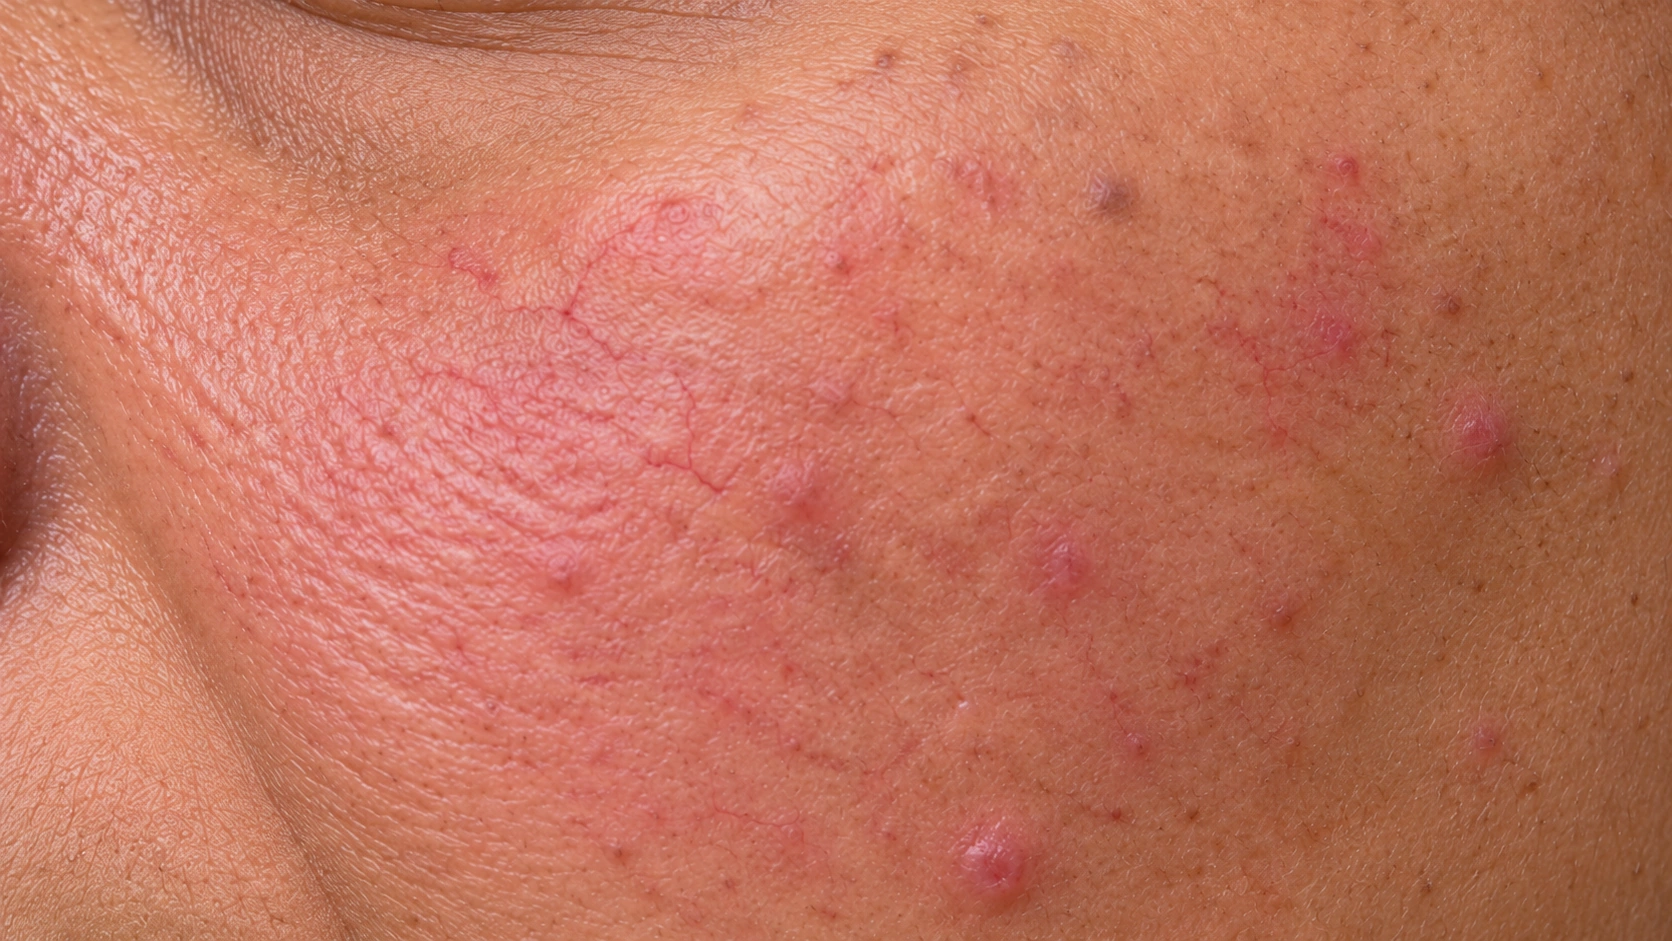
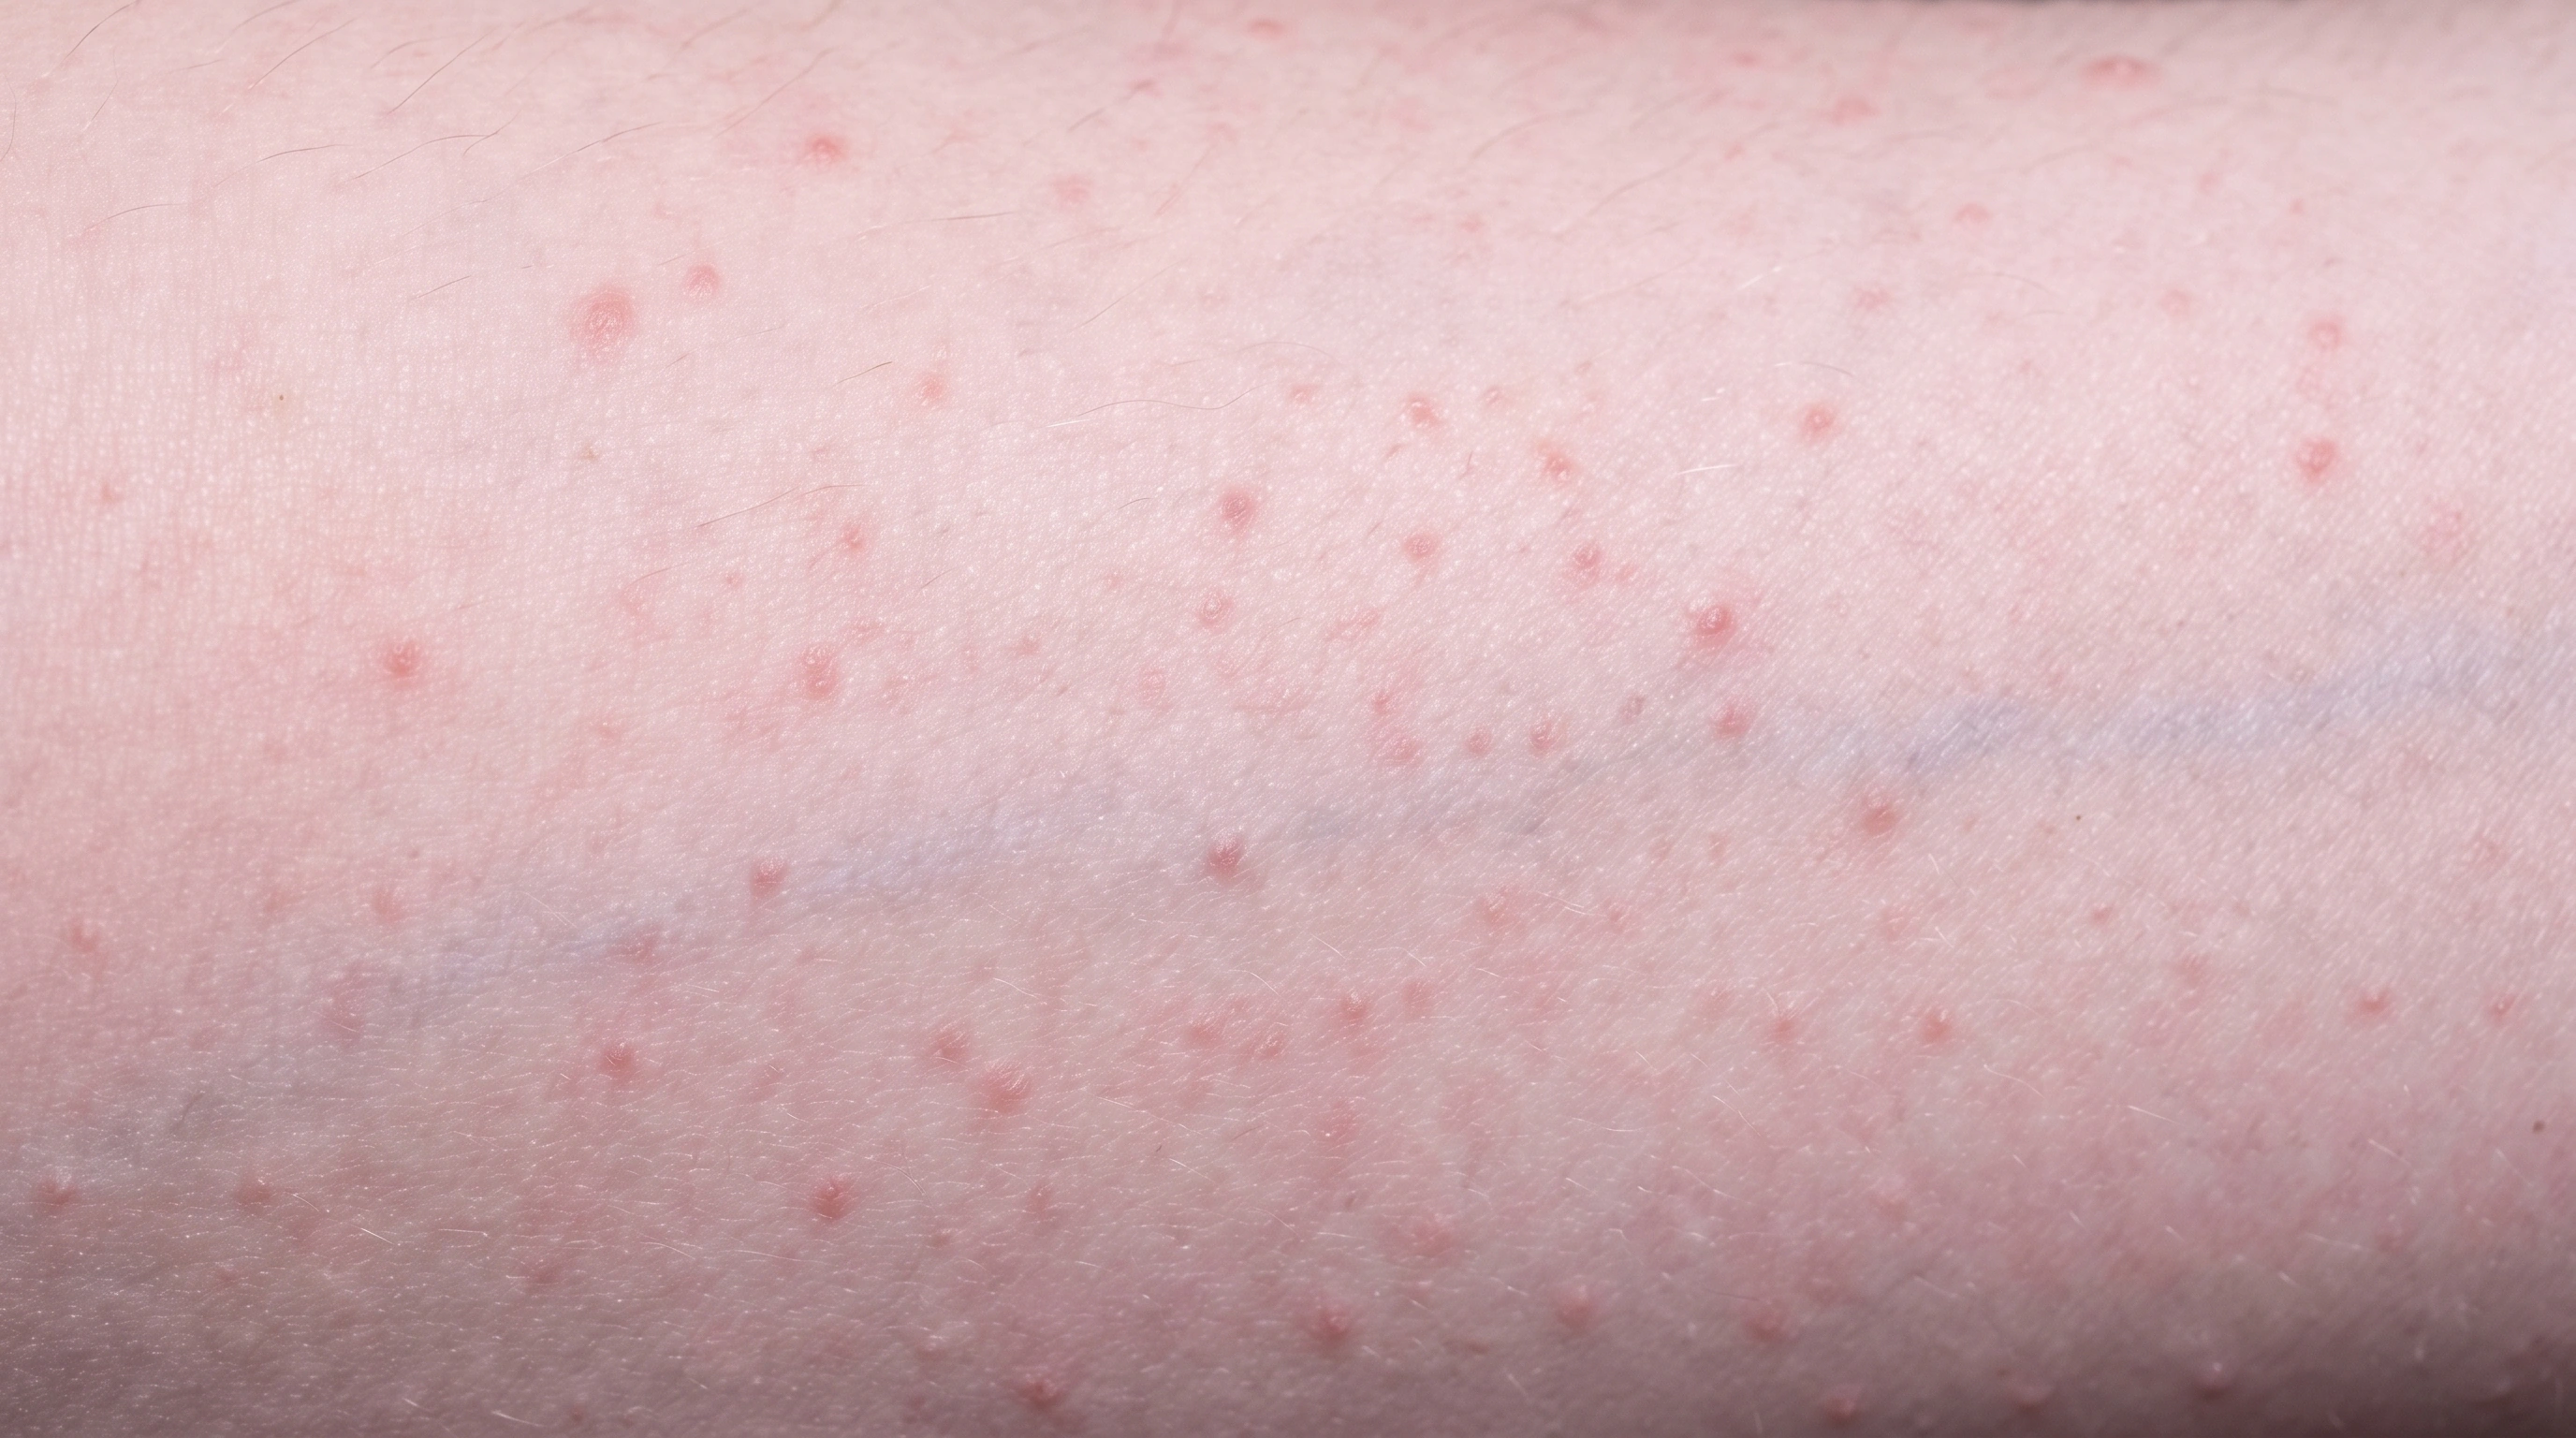
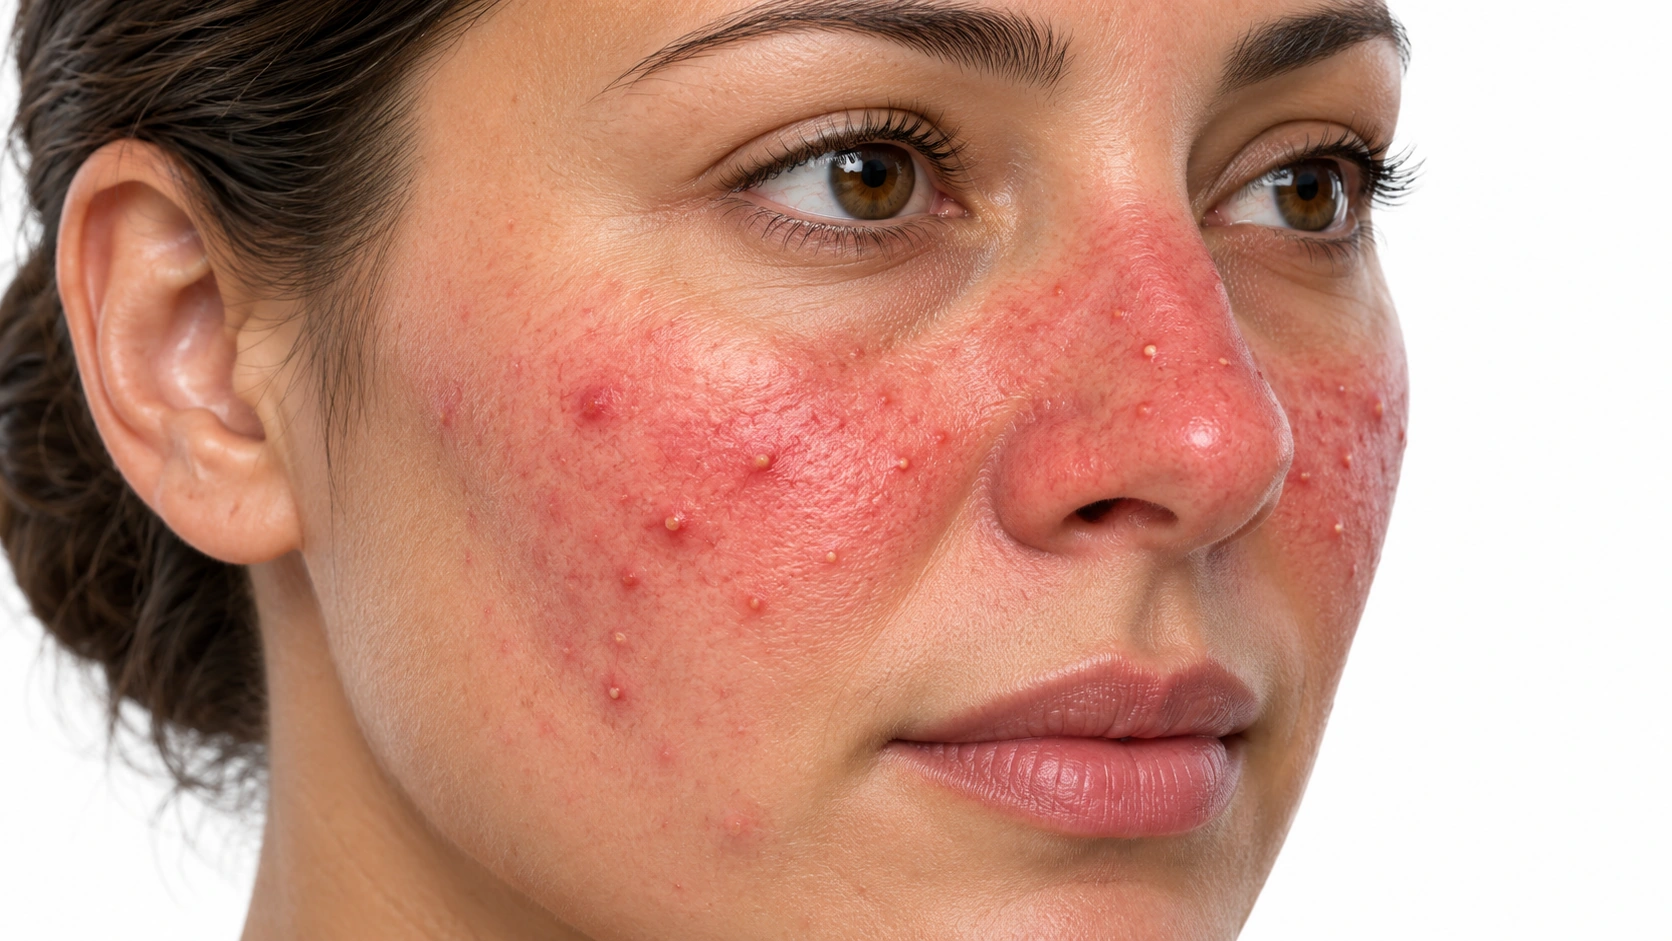
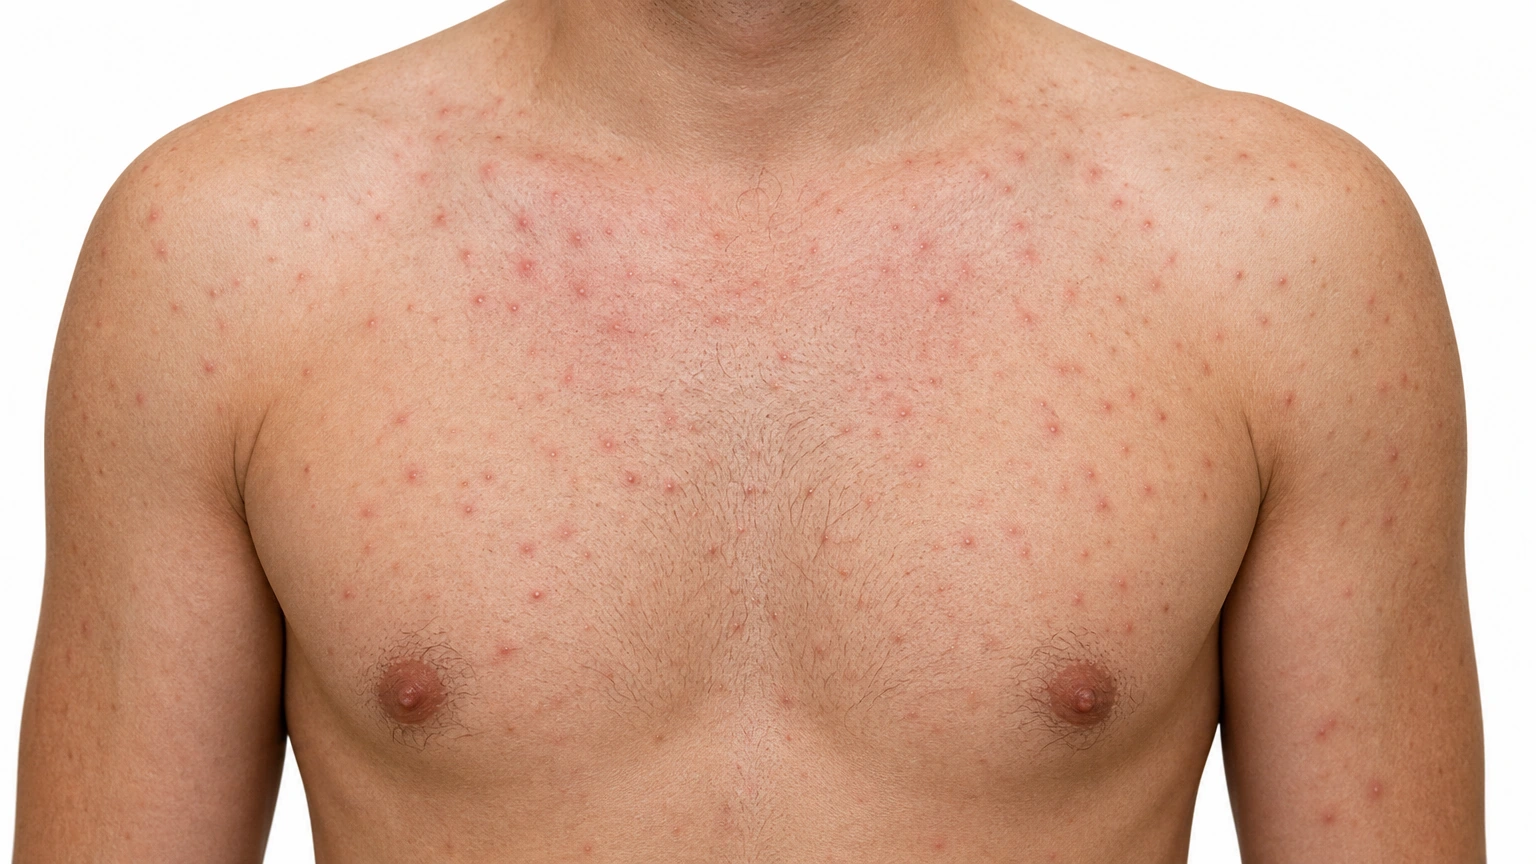
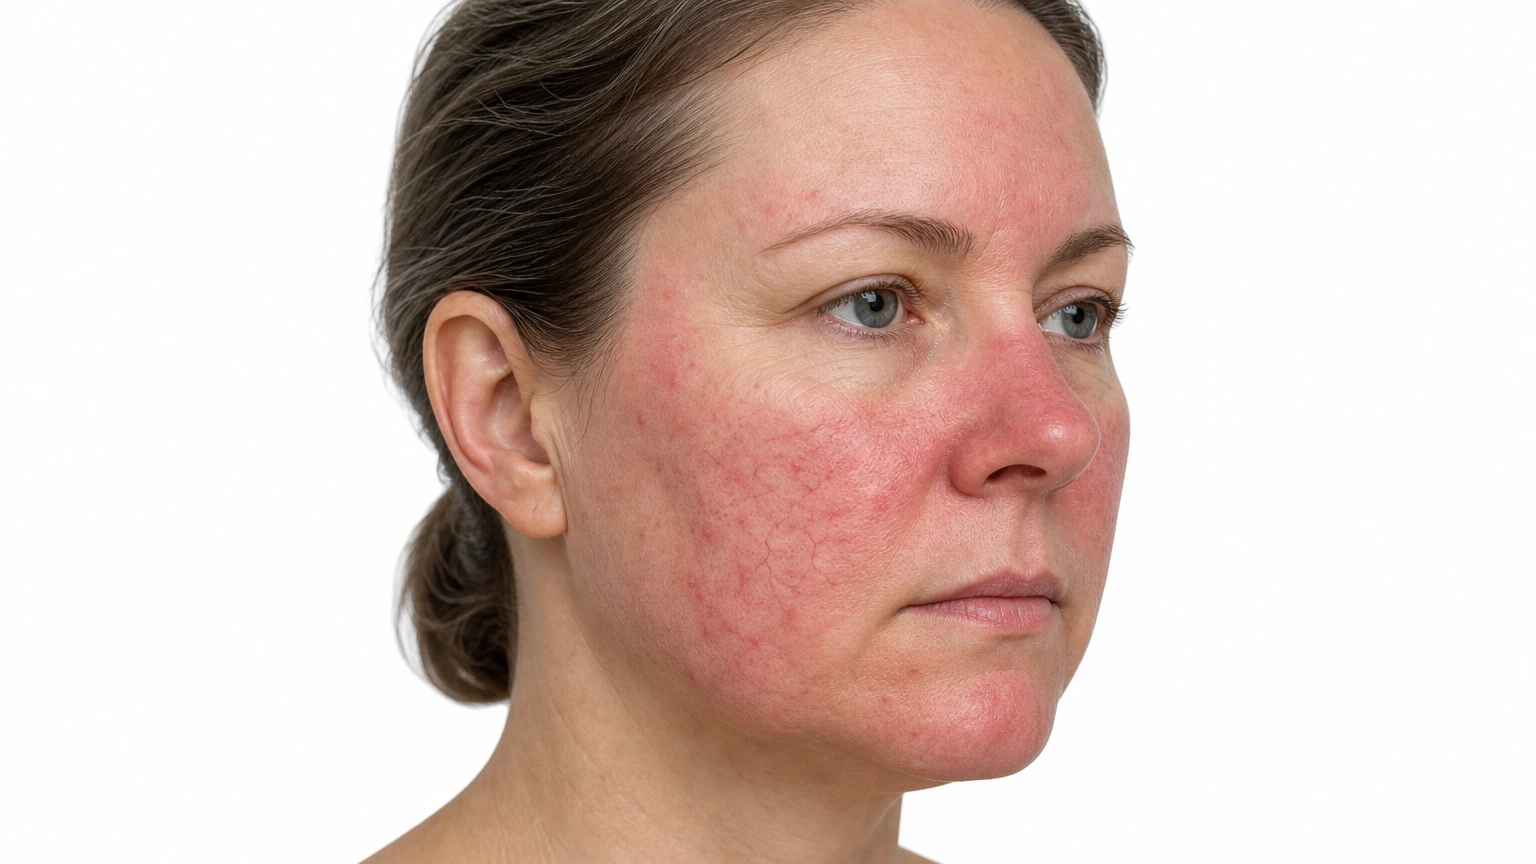
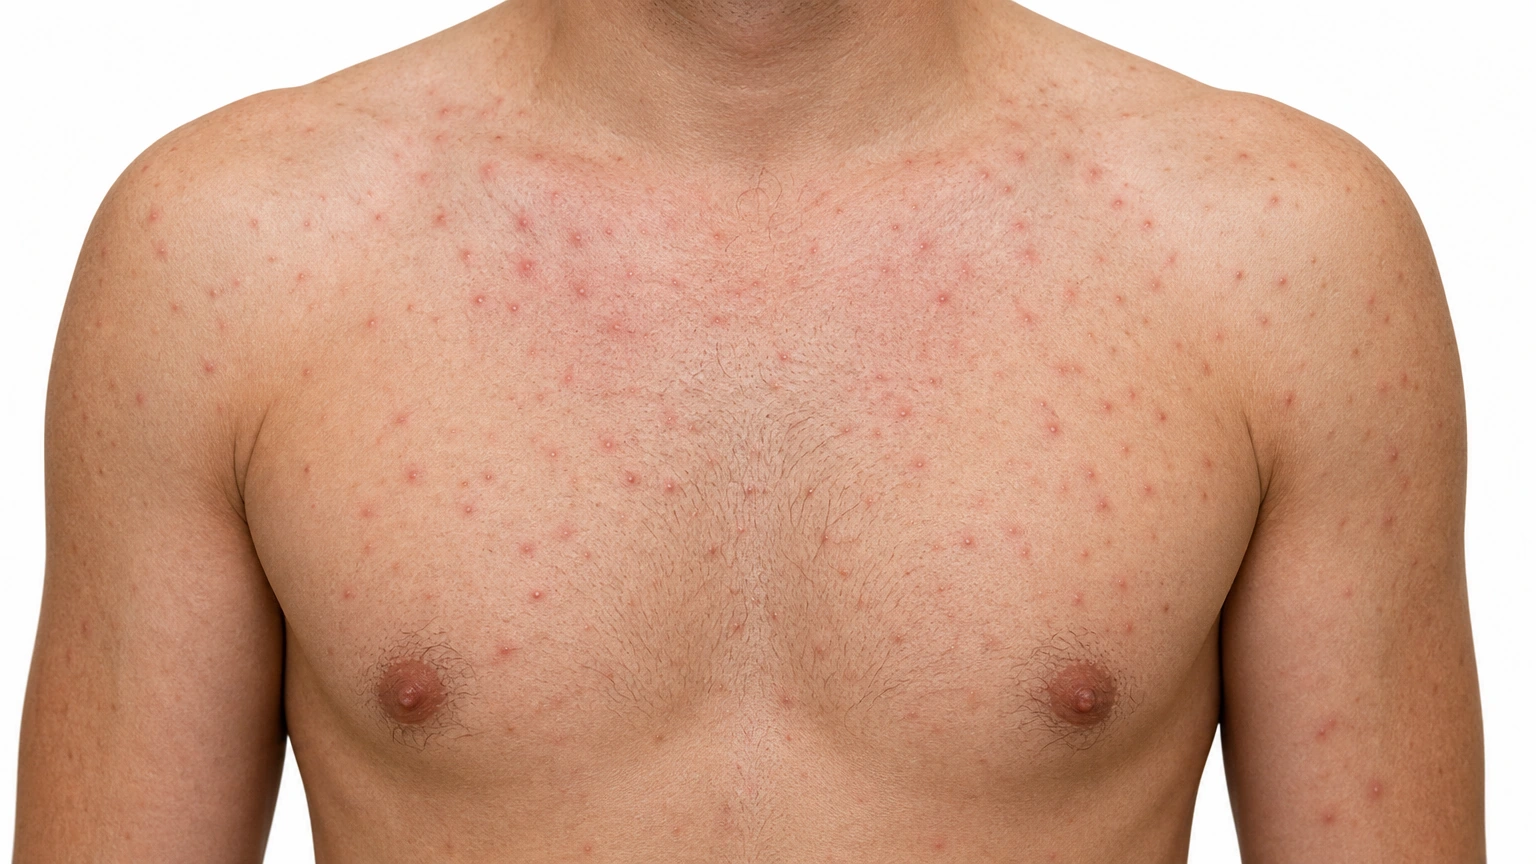
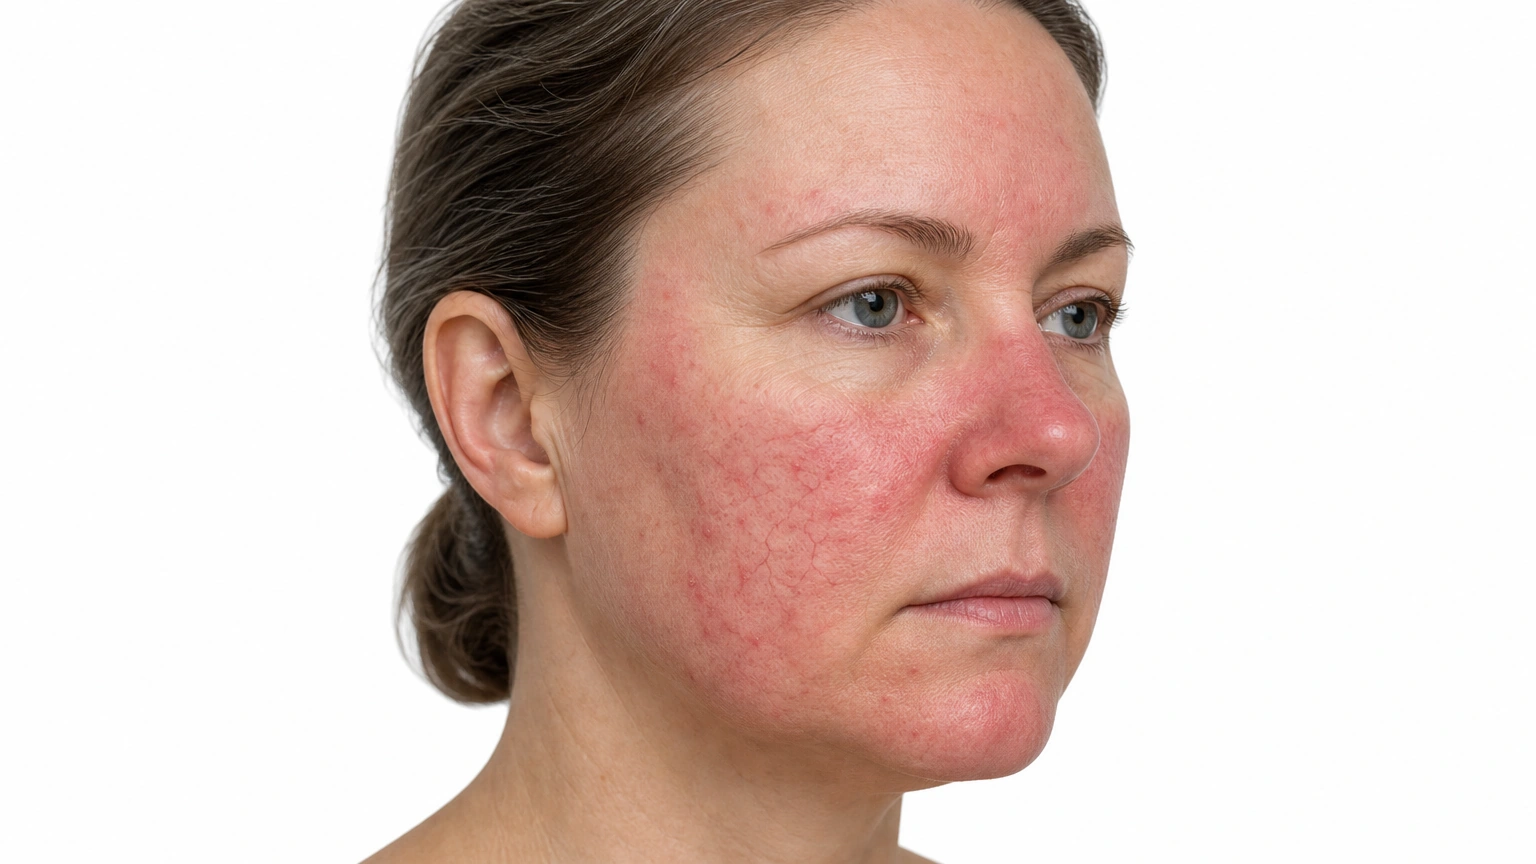
AI-generated educational illustration: Small similar-sized acneiform papules and pustules across the adult upper chest, representing a steroid-acne appearance.AI-generated educational illustration: Central facial redness, fine vessels and small papules, representing a steroid-associated rosacea appearance.

Key differences

The same eight facts on every condition comparison.
Usual age
Any age on steroids
Adults
Where
Chest, back, shoulders
Central face
Main sign
Uniform small red bumps
Red, burning, bumpy face
Itch or pain
Mild
Burning
Contagious
No
No
Long term
Clears after stopping
Clears slowly after stopping
Scars
Rarely
No
Who gets it
People taking steroids
People using strong steroid cream on the face

What is it?

Steroid Acne
Steroid Rosacea
What is it?
  • What it is
    A uniform acne-like eruption associated with systemic corticosteroids or anabolic steroids.
  • What it is
    A burning rosacea-like facial eruption caused by potent topical steroids or their withdrawal.

What it looks like

Steroid Acne

An upper torso with numerous small pink bumps across the chest and shoulders.

Steroid Acne Small, closely sized spots are spread over the chest and shoulders.
Steroid Rosacea

A face with marked redness across the cheeks and nose and scattered small bumps.

Steroid Rosacea Pink-red patches extend across the cheeks and nose.
Skin tones
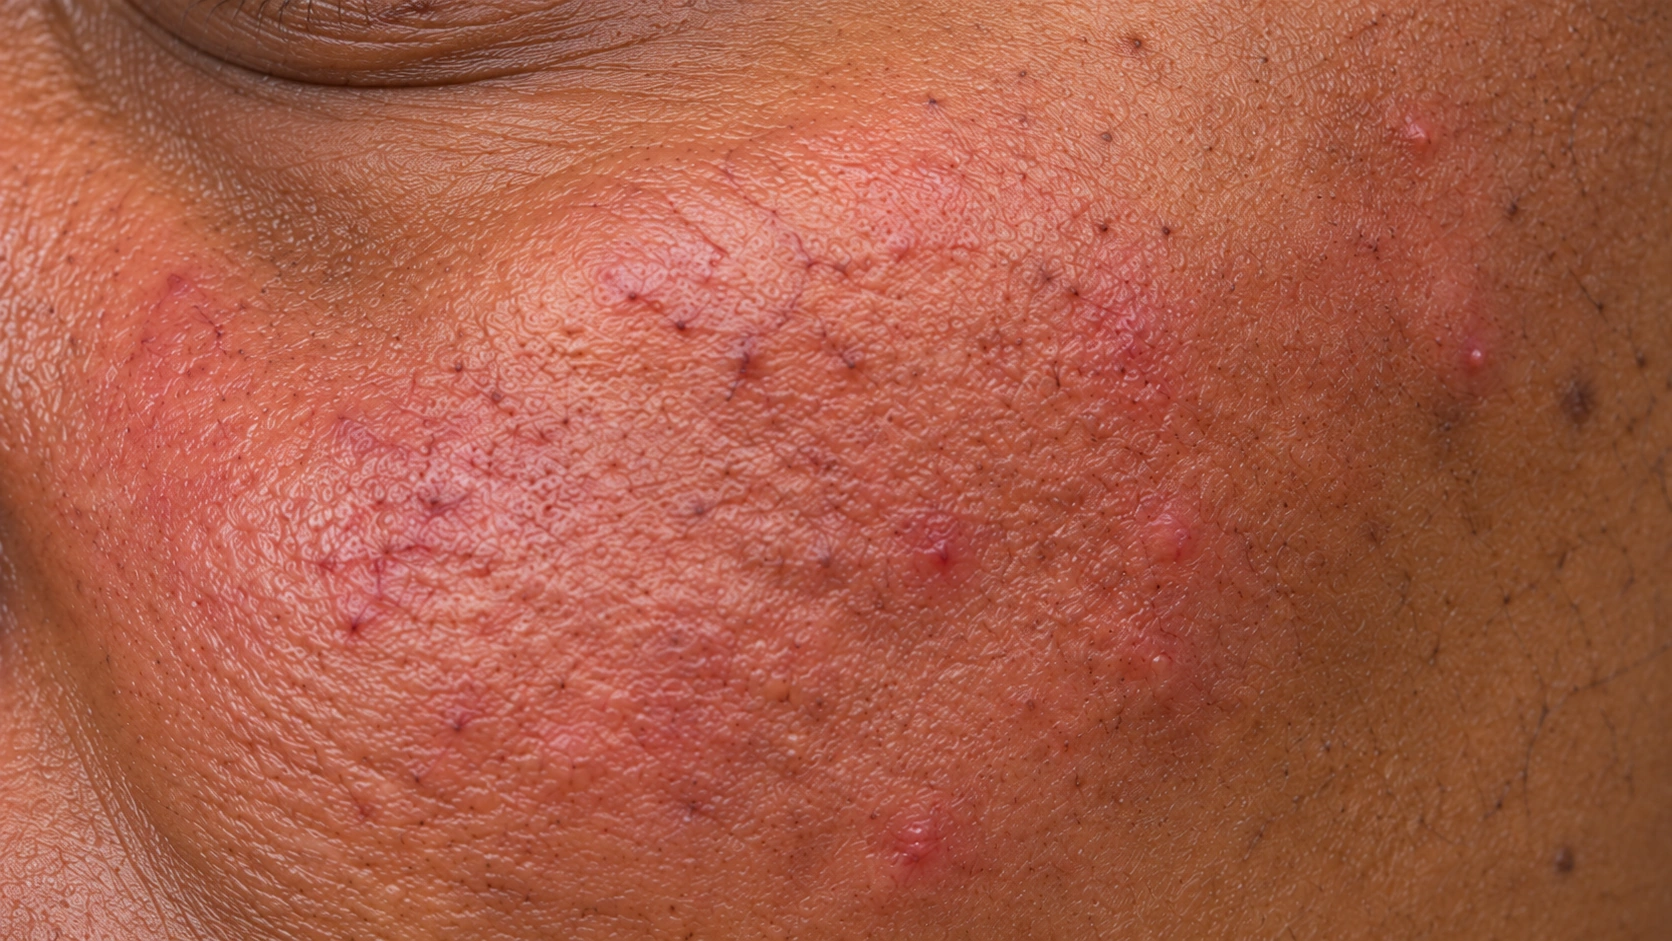
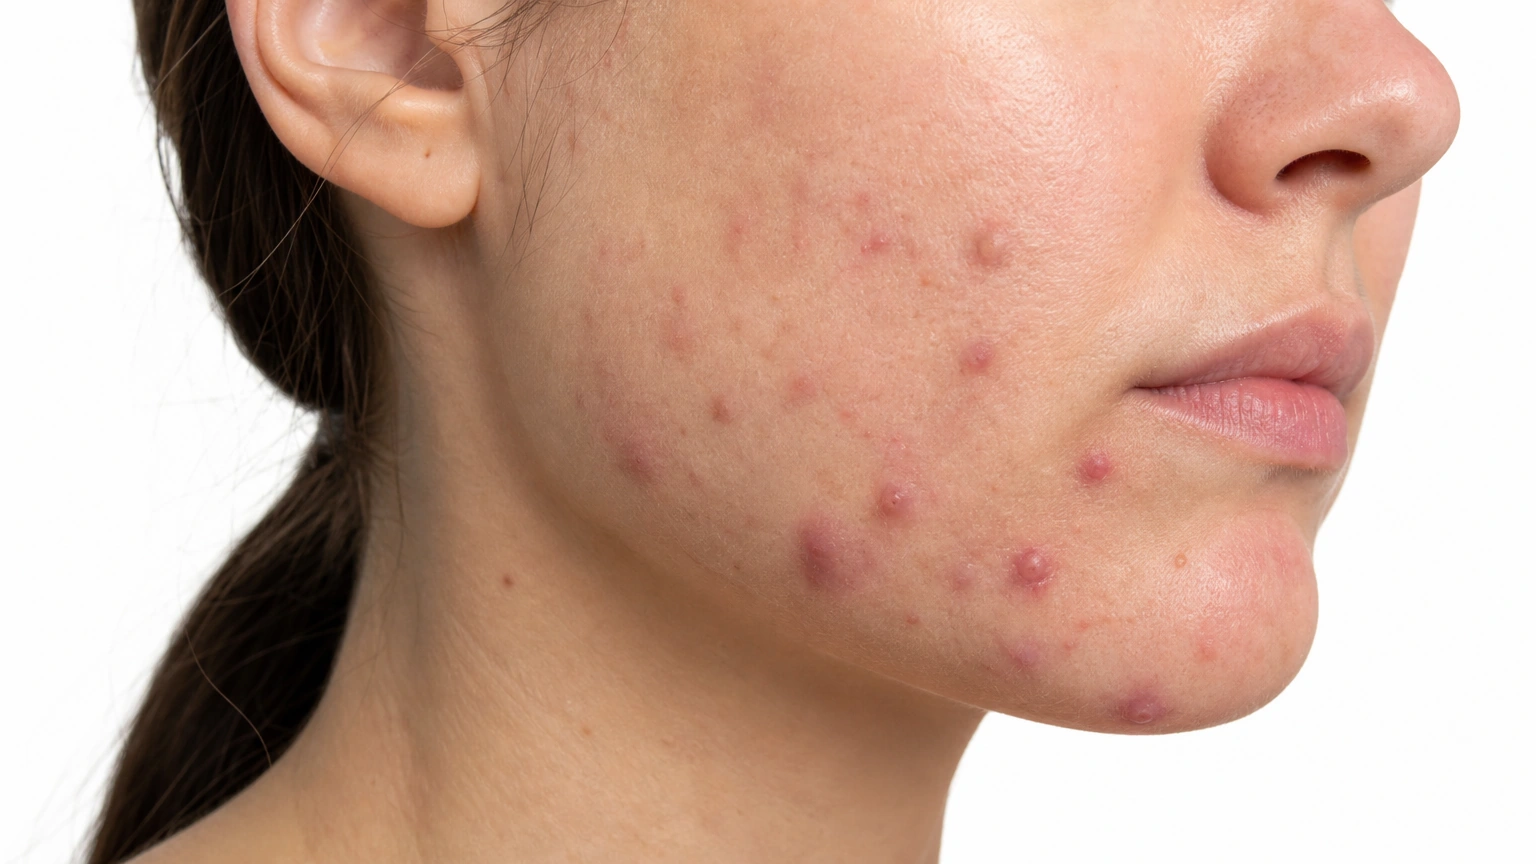
Steroid Acne on light skin.
Steroid Acne.
Steroid Acne.
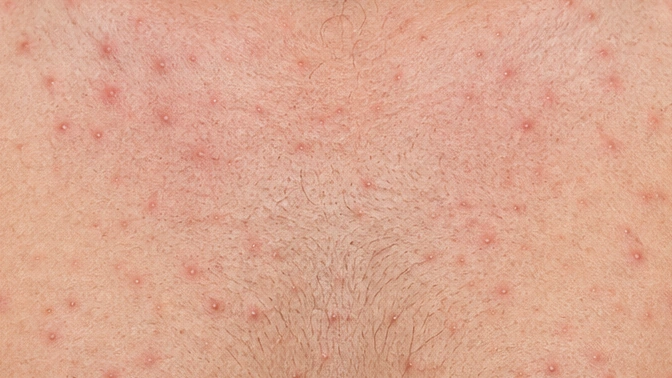
Steroid Acne, close-up of representative skin findings.
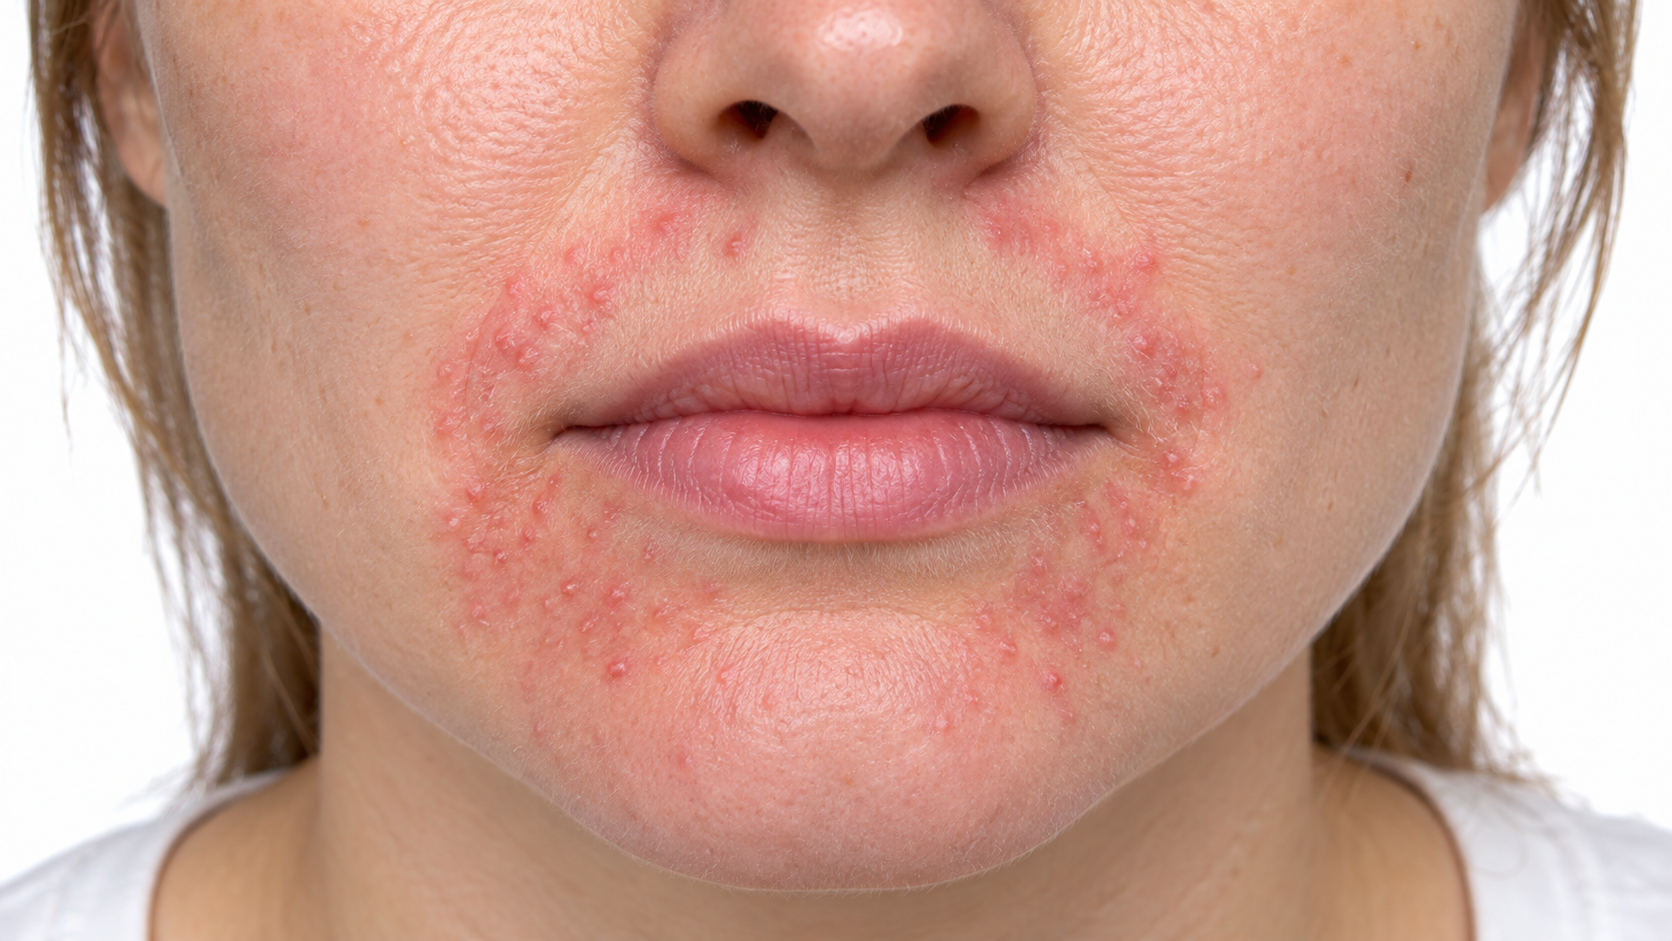
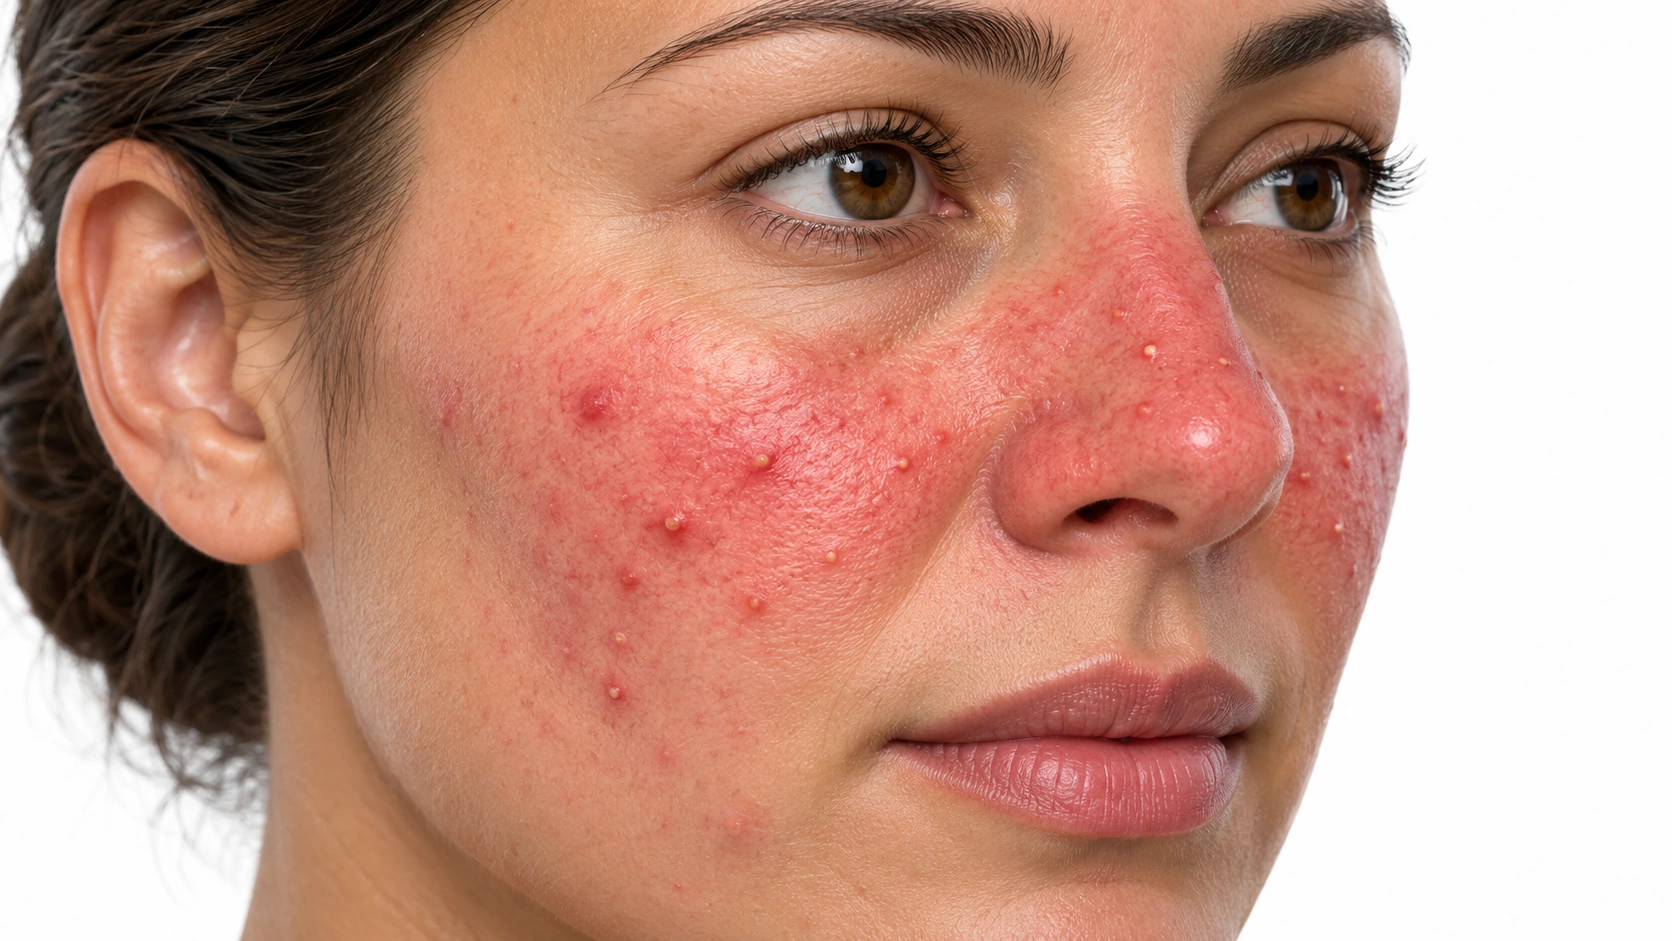
Steroid Rosacea on light skin.
Diffuse facial irritation with fine vessels and scattered small papules.
In the skin

Steroid exposure can promote acne-like follicular inflammation or yeast-related folliculitis. These processes can look similar but have different underlying mechanisms.

Repeated topical steroid exposure can disrupt facial skin and provoke rosacea-like inflammation. Withdrawal after prolonged use can be followed by rebound redness and bumps.

When it usually starts

010203040506070+

Steroid Acne. Can develop after weeks of steroid exposure.

Steroid Rosacea. Usually follows weeks or longer of steroid use on the face.

Causes and triggers

Causes

Steroid exposure can promote acne or yeast-related folliculitis; treatment depends on which is present.

Repeated topical steroid exposure disrupts facial skin and can produce rebound inflammation.

Risk factors
Systemic corticosteroids, Anabolic steroids
Potent facial steroid use, Prolonged steroid exposure
Trigger
● Steroid Acne
● Steroid Rosacea
Steroid exposure
Can contribute
Not listed
Topical steroid exposure or withdrawal
Not listed
Can contribute
Irritating products
Not listed
Can contribute

Daily Care

Steroid Acne
Steroid Rosacea
Daily care

Habits that help

  • Keep cleansing gentle and change sweaty clothing promptly
    Use a mild cleanser rather than scrubbing the bumps.
  • Choose light non-comedogenic moisturizer and sunscreen
    Avoid heavy products that worsen follicle blockage.
  • Tell the clinician about prescribed and non-prescribed steroids
    Include tablets, injections, inhalers, creams and bodybuilding products.
  • Follow the agreed acne or folliculitis treatment plan
    Steroid-related eruptions can have different causes and may need different medicines.
  • Discuss medication and diagnosis review
    The prescriber should distinguish acne from yeast folliculitis and review steroid exposure. Do not stop systemic steroids abruptly.

Avoid

  • Avoid: Abruptly stopping a prescribed systemic steroid
    Withdrawal can be dangerous; changes need the prescriber’s guidance.
  • Avoid: Picking bumps or adding several harsh acne actives
    This can worsen irritation without addressing the cause.

Habits that help

  • Cleanse gently with lukewarm water
    Use a fragrance-free, non-abrasive cleanser and pat the face dry.
  • Moisturize with a bland, fragrance-free product
    Apply gently to reduce dryness and help the skin tolerate prescribed treatment.
  • Use broad-spectrum SPF 30 or higher each day
    Add shade and a hat; choose a sunscreen your skin tolerates.
  • Track your own triggers rather than avoiding everything
    Brief notes may identify links with heat, drinks, alcohol, food or particular skin products.
  • Follow a clinician-led plan for facial steroid withdrawal
    Stopping or restarting a potent steroid on your own can lead to rebound flaring; do not change unrelated prescribed medicines.

Avoid

  • Avoid: Scrubs, facial brushes and products that sting
    Irritation can worsen redness and bumps that resemble acne.
  • Avoid: Overheating during showers or exercise
    Use cooler water, a fan and rest breaks while continuing comfortable physical activity.

Treatment differences

Evidence labels come from each condition’s own treatment list.

Treatment
● Steroid Acne
● Steroid Rosacea
Prescription topicals

Diagnosis-specific topical treatment

Listed

Acne may respond to acne medicines; confirmed yeast folliculitis needs an antifungal approach.

None listed
Prescription pills
None listed
An amber prescription bottle lying on its side on a white background with a plain white label reading Doxycycline, and six small round white tablets spilled out in front of it.

Doxycycline

Listed

May be used for the inflammatory eruption when suitable; pregnancy and other contraindications need review.

Procedures
None listed

Supervised steroid withdrawal

Listed

A clinician can plan withdrawal and manage rebound rather than escalating facial steroid strength.

Outlook

Long term

Steroid-related acne can improve when the responsible exposure is reduced or changed with the prescriber. Do not abruptly stop prescribed steroids; an acne treatment plan may be needed while they continue.

Recovery may take months with a supervised withdrawal and treatment plan. Temporary rebound can occur, and visible small vessels may persist even after the inflammatory rash settles.

Complications

Possible complications

The eruption may persist with the medicine; yeast folliculitis and ordinary acne require different treatments.

Rebound flares and persistent visible vessels can occur.

When to get help

When to get help

Do not abruptly stop a prescribed systemic steroid. Seek care for painful lesions or an uncertain diagnosis.

Discuss the steroid with its prescriber; do not keep escalating potency to control rebound.

Common questions

Steroid Acne:What is Steroid Acne?

A uniform acne-like eruption associated with systemic corticosteroids or anabolic steroids.

Steroid Acne:What can I do day to day?

Use gentle skin care and discuss all prescribed and non-prescribed steroids with the prescriber.

Steroid Acne:When should I get medical advice?

Do not abruptly stop a prescribed systemic steroid. Seek care for painful lesions or an uncertain diagnosis.

Steroid Rosacea:What is Steroid Rosacea?

A burning rosacea-like facial eruption caused by potent topical steroids or their withdrawal.

Steroid Rosacea:What can I do day to day?

Use a simple gentle routine and arrange a supervised steroid withdrawal plan.

Steroid Rosacea:When should I get medical advice?

Discuss the steroid with its prescriber; do not keep escalating potency to control rebound.

Sources

Sources and further reading

  1. Steroid acne
  2. Steroid rosacea
Dermapedia on YouTube