Acne
Reduces inflamed spots with benzoyl peroxide.
Clindamycin: A prescription antibiotic lotion, gel or foam for inflamed acne. It should never be used on its own, because bacteria become resistant to it quickly. Tretinoin: A prescription vitamin A cream or gel for acne. It works underneath the skin, on the plug that forms weeks before a pimple appears.

Choose for red, inflamed acne as a short-term partner to benzoyl peroxide or a retinoid — never on its own.
Choose for acne or sun-aged skin as the classic, well-studied prescription retinoid — cheap as a generic.
Can you take them together?
A standard acne pairing, also sold as one combined gel. Tretinoin clears pores and clindamycin calms inflamed spots.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.

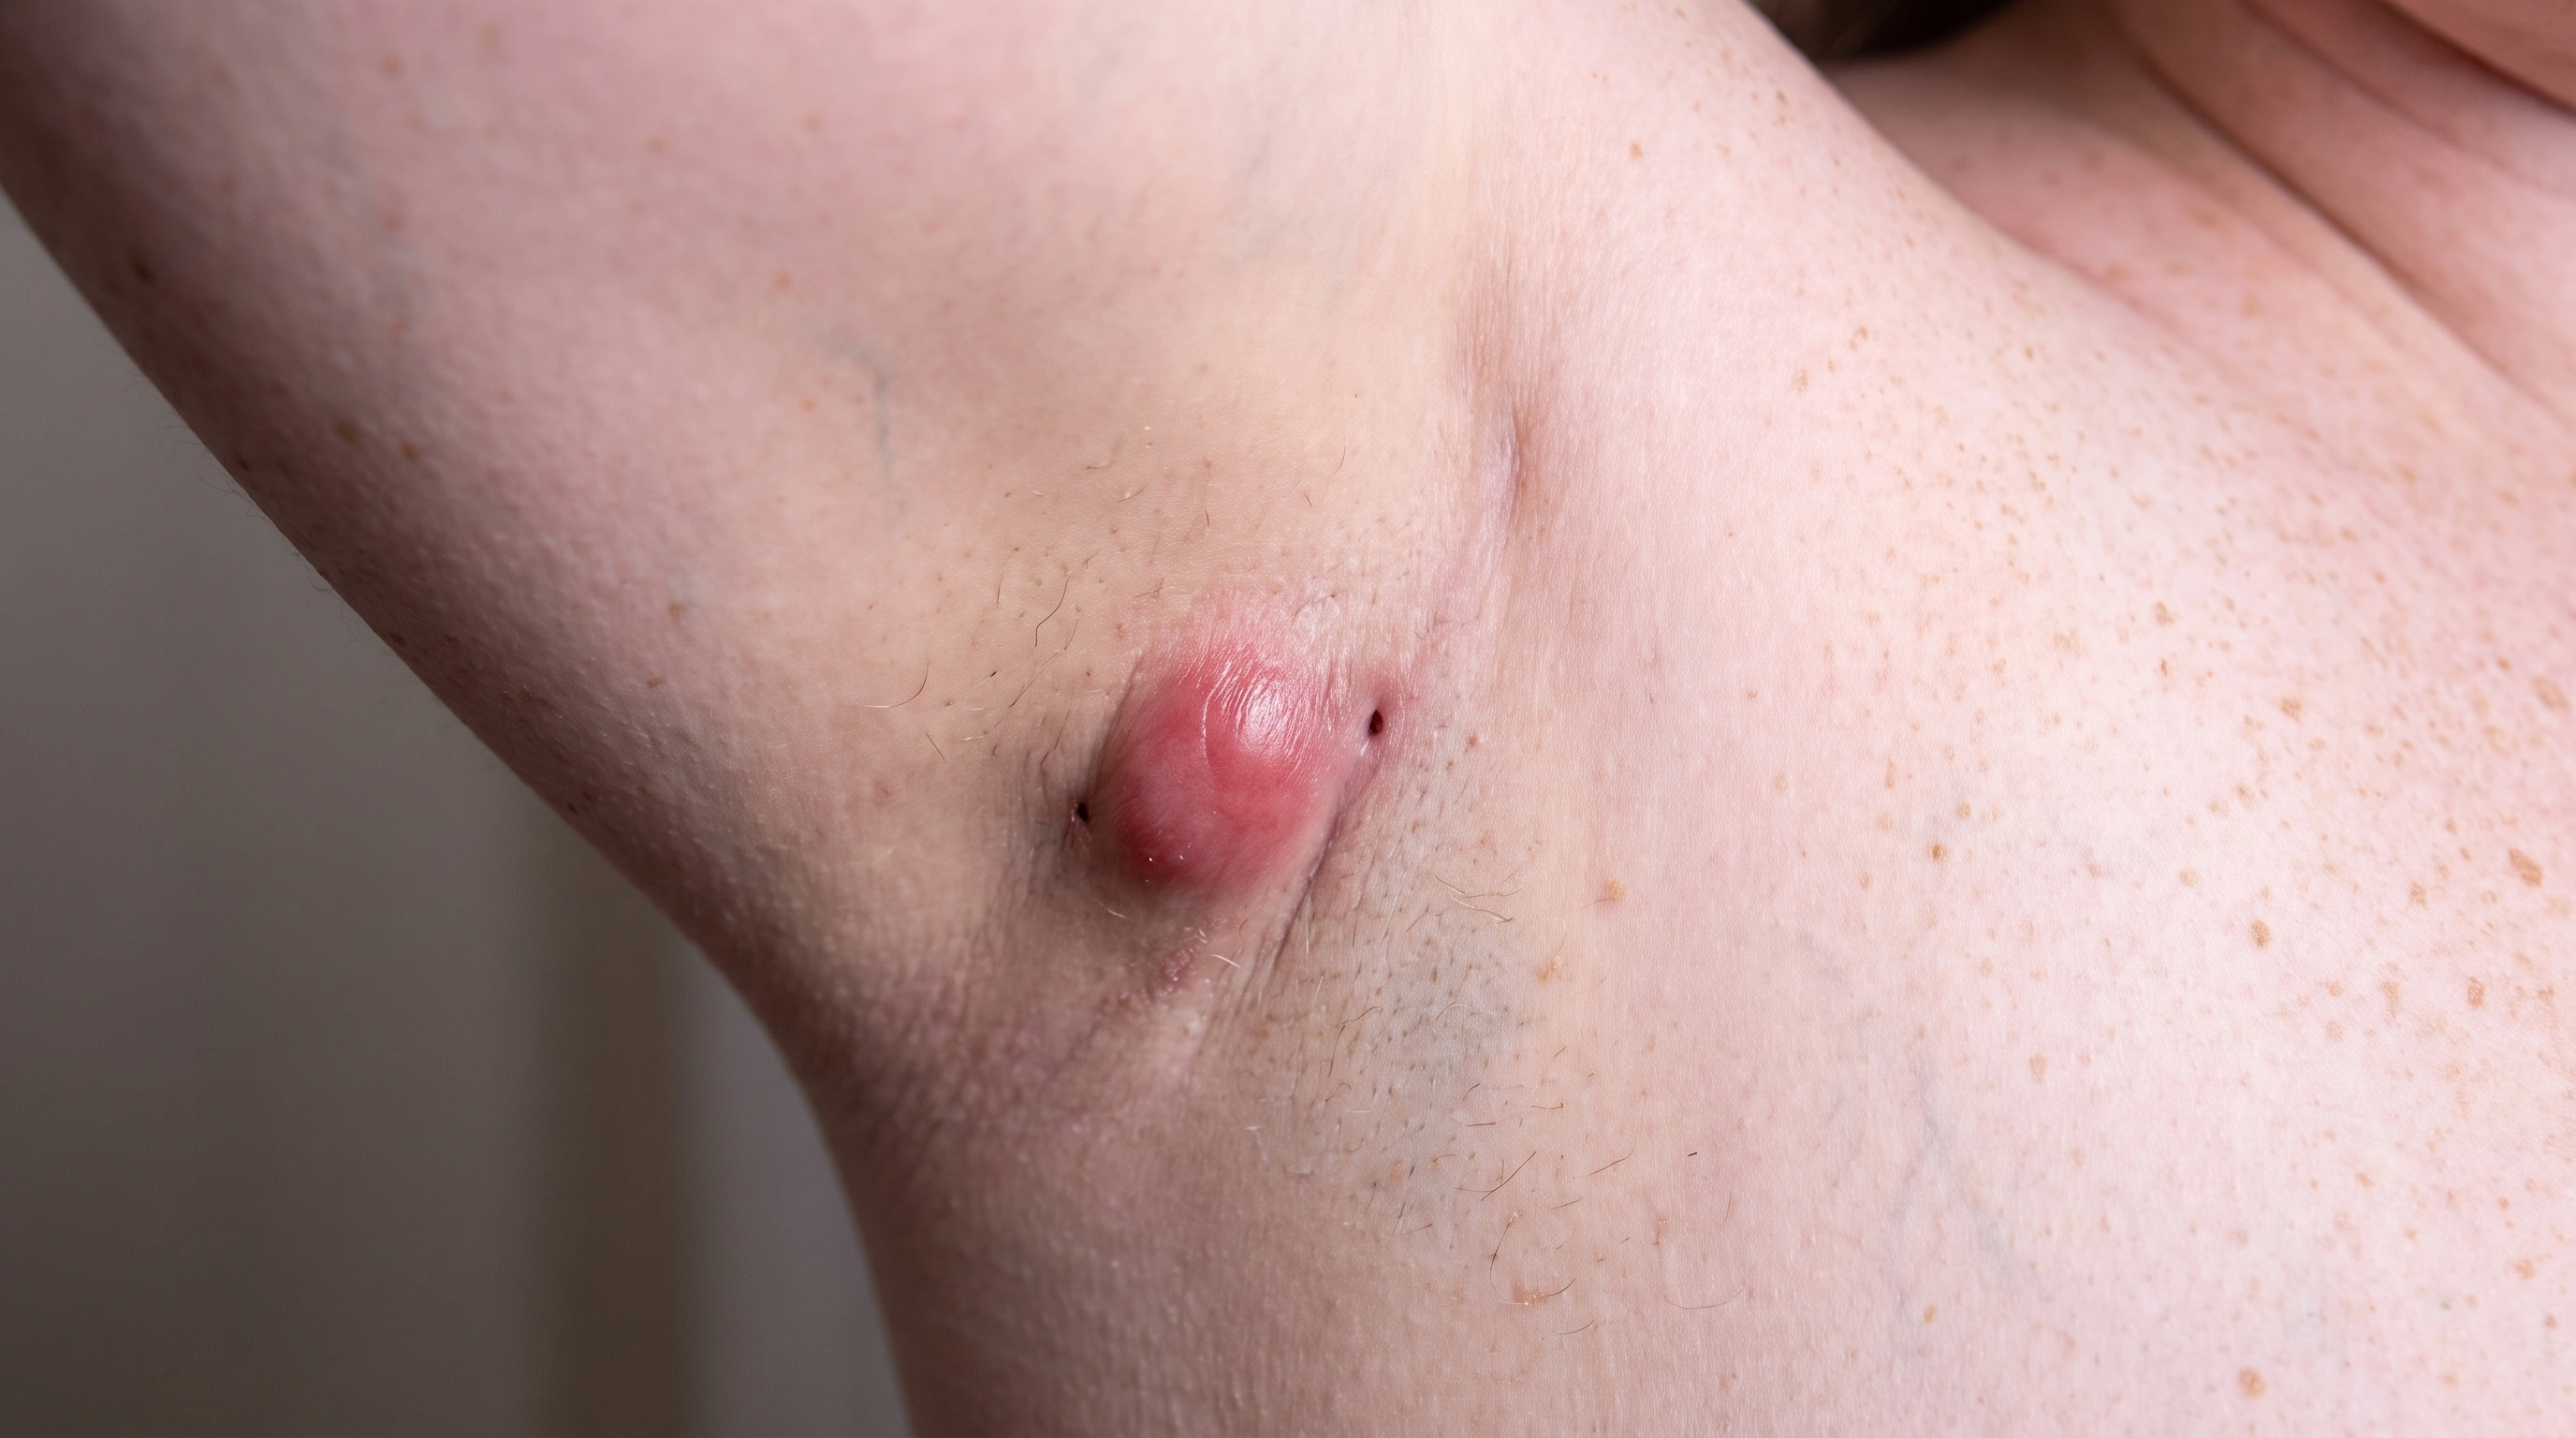



Slows acne bacteria: Blocks the 50S ribosome that bacteria use to make proteins. Limits bacterial growth: Susceptible C. acnes has less ability to multiply. Reduces inflamed spots: Red bumps and pimples can gradually improve.
Bacterial protein-synthesis inhibition is established. The complete acne mechanism and the contribution of individual antibacterial and anti-inflammatory effects are not fully defined. This does not imply direct exfoliation, oil-gland shrinkage, or treatment of resistant bacteria.

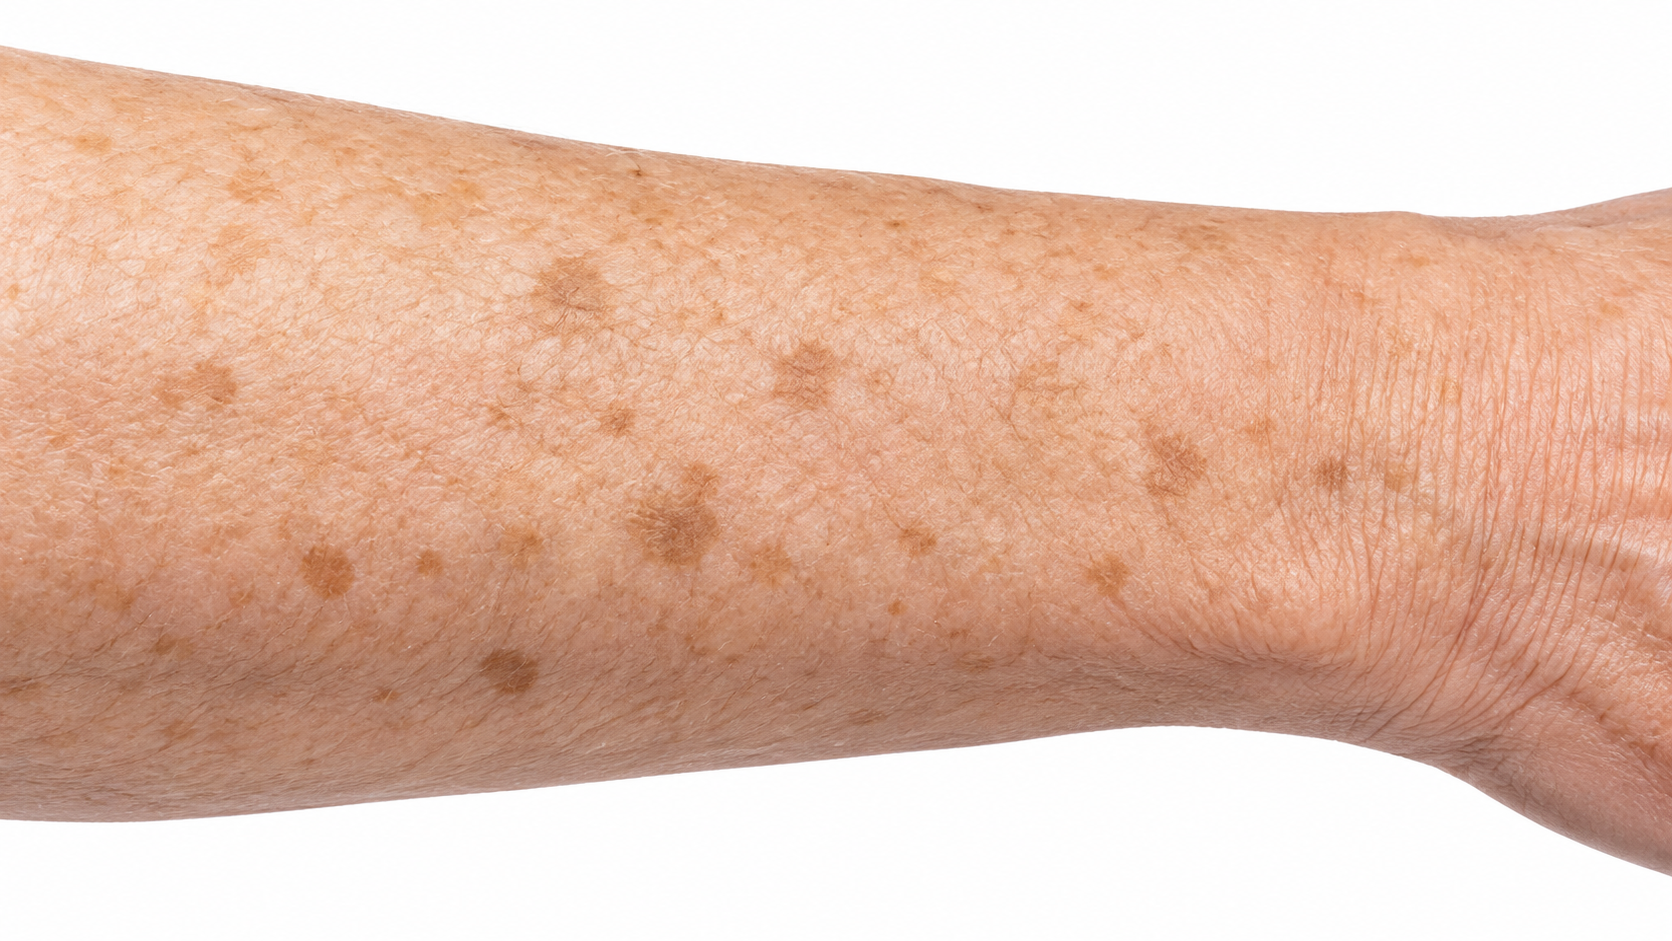
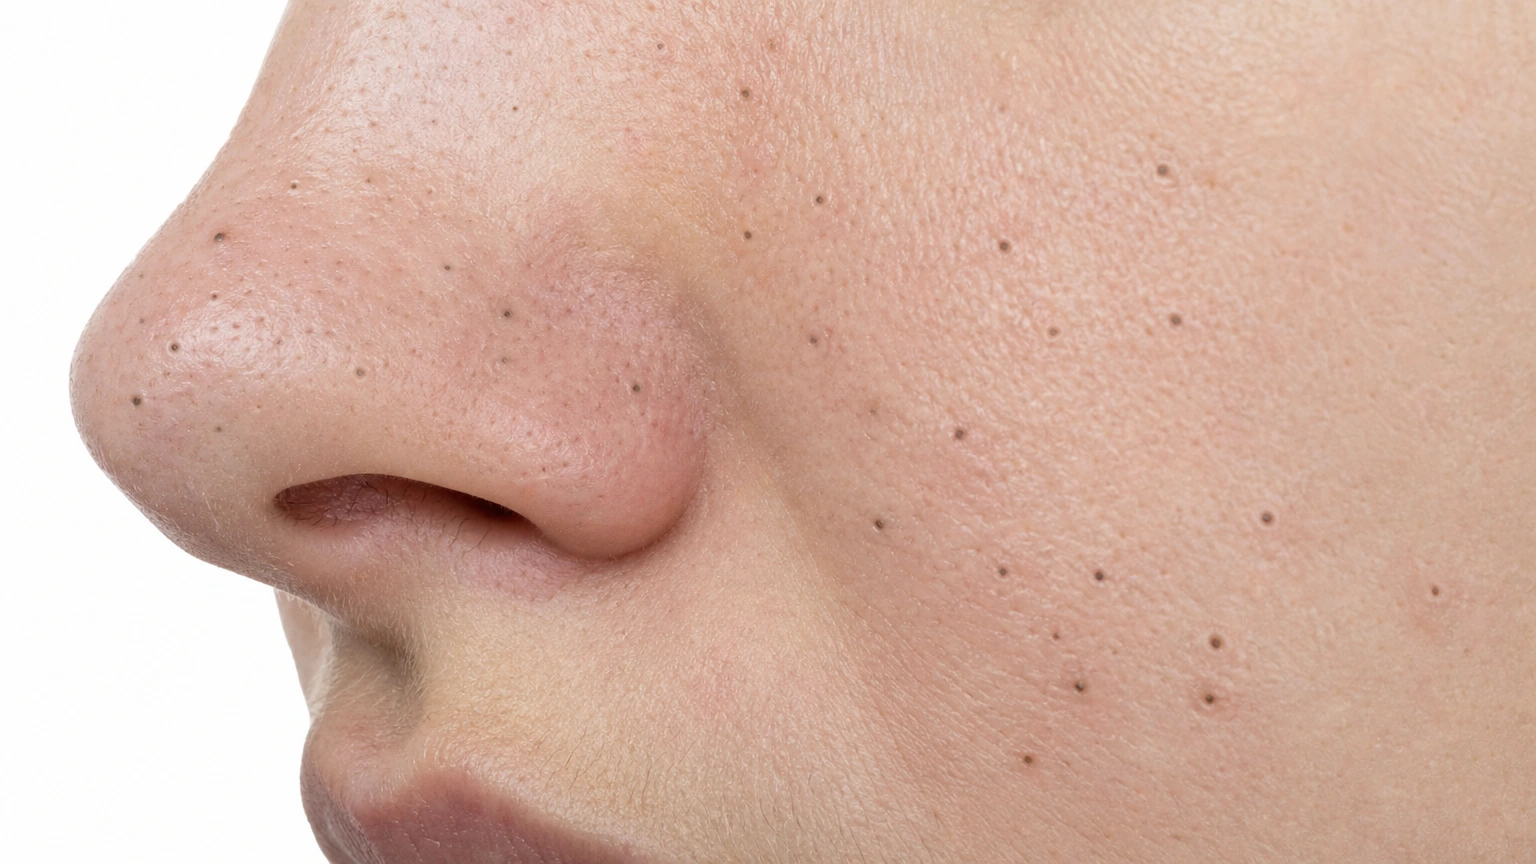
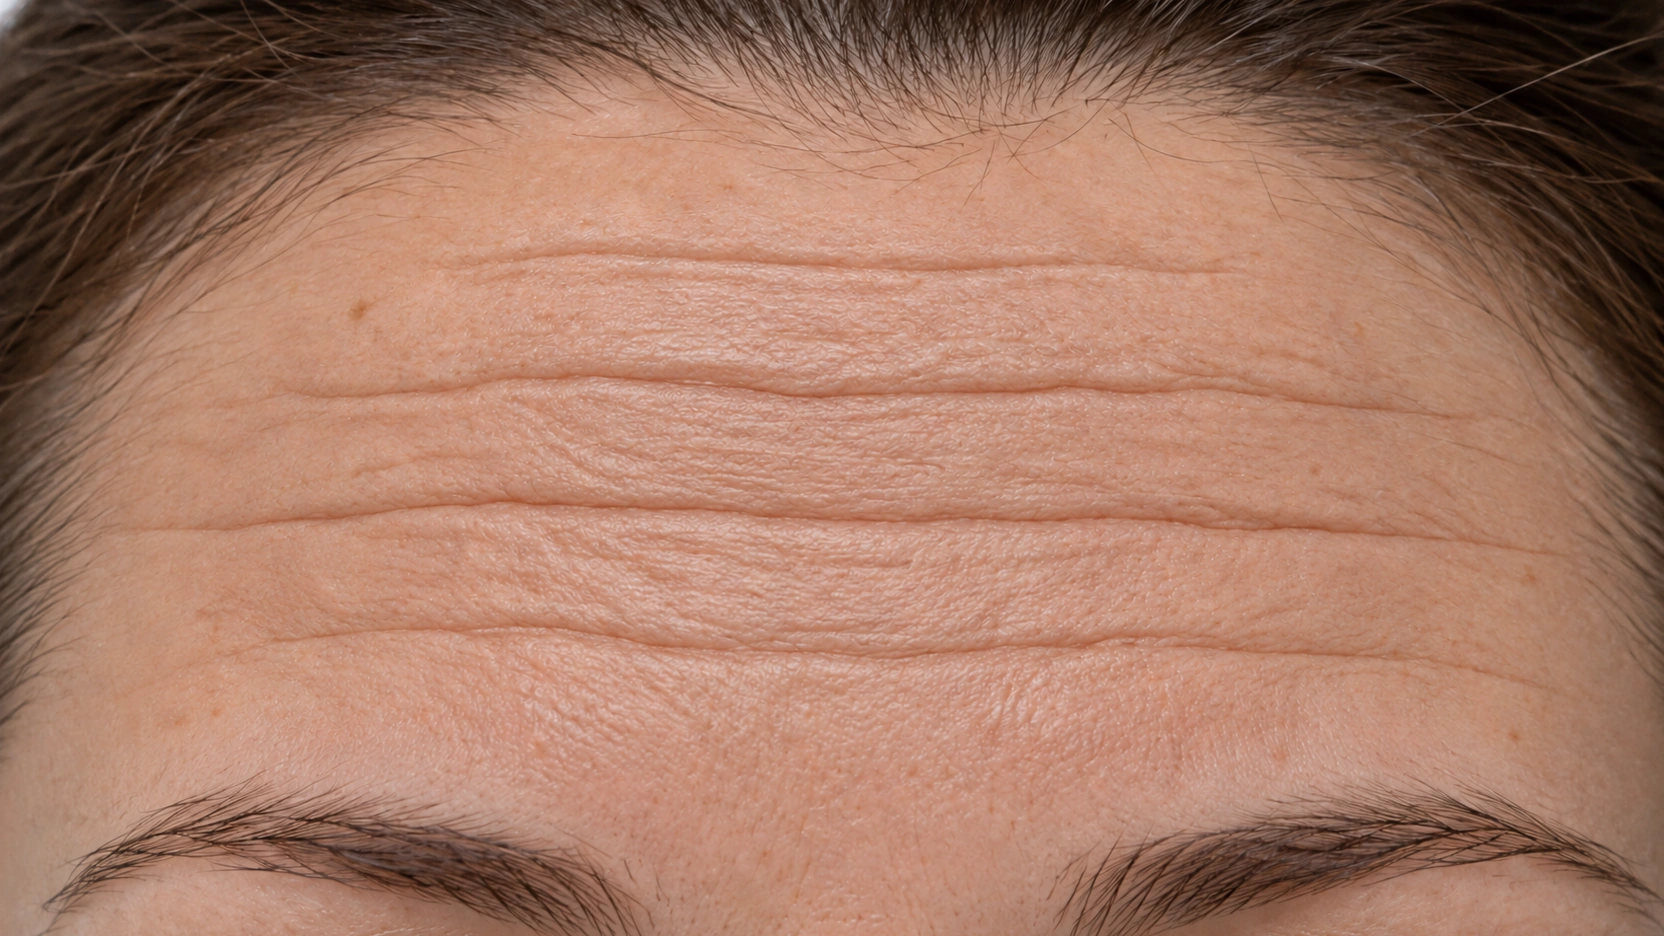
Unclogs pores: Reduces dead-cell buildup inside follicles. Helps fade dark marks: Helps clear pigment-containing cells as skin renews. Builds collagen: Helps fibroblasts produce new collagen. Reduces collagen breakdown: Reduces signals that increase collagen-cutting enzymes.
Conceptual illustration of the main skin effects, not every molecular pathway. Pigment clearance with epidermal renewal is a simplified mechanism; the exact pigment effects are not fully settled. Collagenase pathway evidence includes UV-challenge studies. Changes develop gradually with continued use.
When to Apply: Once or twice a day depending on the product, a thin layer over the whole area, not single spots. With a retinoid at night, clindamycin goes in the morning.
How to Start: Full strength from day one. No ramp-up, because it rarely irritates.
If It Irritates: Uncommon. Mild dryness settles with a moisturizer. Redness or itch that builds over days can be a reaction to the base — stop and ask.
If It’s Not Working: No higher dose. It belongs alongside benzoyl peroxide or a retinoid, so the next move is a partner drug, not more of this one.
When to Apply: At night only, on clean dry skin. Wash, dry fully, then spread a pea-sized amount over the whole face — not just the spots. Moisturizer before or after, either way.
How to Start: Every other night for two to four weeks. Go nightly once you have had two weeks with no stinging or flaking.
If It Irritates: Drop to every second or third night, or put moisturizer on first and the tretinoin on top. Either works.
If It’s Not Working: Give it twelve weeks before judging. If acne has stalled, ask your doctor about a higher strength or a second treatment.
No blood tests. Monitoring is clinical — at eight to twelve weeks, has the inflamed acne improved.
Not a drug to stay on for years. Bacterial resistance builds with use, which is why a course that worked once may not work again. Stop once acne is controlled and hold the result with a retinoid and benzoyl peroxide.
No blood tests and no routine labs. Monitoring is a visit at about twelve weeks — is it working, should the strength change?
People stay on this for years, and nothing builds up. Skin usually becomes less irritated over time, not more, so a strength that was impossible at the start may be comfortable a year in. Once you are stable, a yearly review is enough.
Approximate windows, not promises.
Weeks 1 to 2Little visible change.
Weeks 2 to 6Red bumps get less sore and less frequent. Blackheads do not change; it does not act on them.
After 12 weeksIf inflamed spots still appear at the same rate, resistance or another diagnosis is likely.
First few minutesApplying it: A pea-sized amount on dry skin at night. Stinging is common early.
Weeks 1 to 3Adjusting: Dryness, flaking and stinging peak around week three. This is retinization, and the acne looks much the same.
Weeks 3 to 12Settling: Irritation settles and the first real results show.
Weeks 4 to 8Sun spots: Sooner than most expect. Dark patches lighten within a month or two and keep fading; in one ten-month trial, 83 percent had lighter spots by the end.
Weeks 8 to 12Judge it here for acne: Blackheads and whiteheads go first; red inflamed spots take longer. If nothing has changed after twelve weeks, change the strength or the plan.
Months 3 to 6Fine lines: They soften gradually with nightly use.
Sorted by what to do about them.
Generic 1% solution and gel are cheap and widely stocked. Combinations with benzoyl peroxide are moderately priced, some generic. The triple combination with a retinoid is brand only and needs prior authorization.
Generic tretinoin cream and gel are widely available and usually the cheapest prescription retinoid. What costs money is the newer vehicles — branded lotions, microsphere gels and combination creams often need prior authorization and can cost many times a plain generic tube.
Adapalene is a related retinoid sold without a prescription and a reasonable substitute if cost is the barrier. It is gentler, it is stable alongside benzoyl peroxide by design, and the guidelines grade the two in the same band.
The bacteria adapt within months, and it does nothing to the clog that starts the spot. Benzoyl peroxide alongside prevents most of the resistance.
The expected pattern after repeated solo courses. Resistant bacteria are already there when you restart.
Less reaches the body, so side effects are milder. Resistance still develops, and rare bowel effects are reported.
Yes. Antibiotic in the morning, retinoid at night.
No, and it is the most repeated claim about the drug. A review hunting for trial data on retinoid-induced flares found none — acne improved even in the first couple of weeks. What does happen is irritation — dryness, flaking and redness peaking around week three and settling by week twelve. That can make your face look angrier without new spots. Lesions genuinely worse at week six are information, not a phase to endure.
No. It prevents the next spot rather than treating today's, so it goes on the whole area that breaks out.
No. Plenty of people stop peeling by week four and keep clearing. Chasing peeling is how people end up on a strength they cannot stay on.
The opposite, over time. It briefly thins the dead surface layer, which is why skin feels smoother and burns more easily early on. Underneath it thickens the living layer and increases collagen — measured on biopsy.
Your skin is more sun-sensitive on it, and daylight destroys the drug. After eight hours of UVA a conventional gel lost about 72% of its tretinoin and a micronized one lost about 9%.
Usually yes. The warning comes from a lab test, not from patients — tested properly, the two in one routine worked as well as spacing them apart, and there is now an approved single cream containing both. With a plain older gel, use one in the morning and the other at night.
It is not recommended in pregnancy, and it is not oral isotretinoin — the two get confused constantly. Published data on topical tretinoin do not show more birth defects, and the newest FDA labels say no drug-associated risk has been established. There is real reassurance if you used it before you knew. Stop once you know, and speak to the doctor managing your pregnancy.