Rosacea
Two large trials support 15% gel for inflammatory bumps, with some erythema improvement.
Azelaic Acid: Treats acne and rosacea bumps; may also help uneven pigmentation. Retinaldehyde: Some formulas improve photoaged texture and pigmentation over months.


Choose for acne or rosacea bumps, especially when uneven tone is also a concern.
Consider for photoaged texture; introduce slowly and judge the complete formula.
Can you use both?
Use azelaic acid in the morning and retinaldehyde at night to limit irritation.
Compare uses by strength of evidence. Evidence level describes confidence in a benefit, not its size.


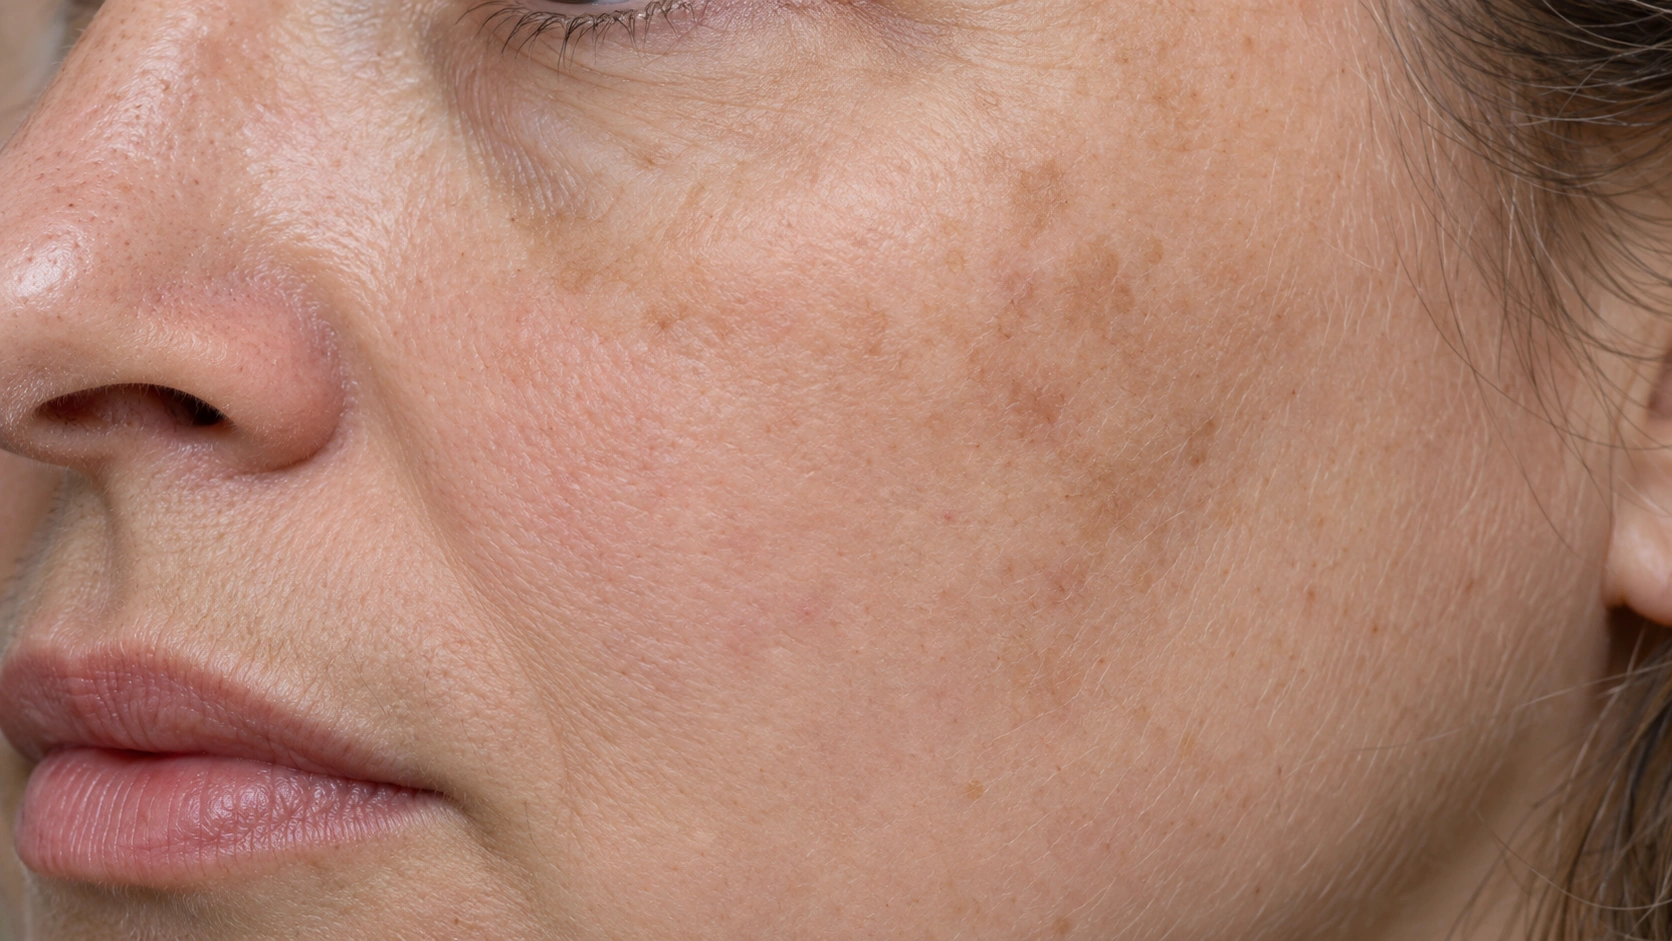
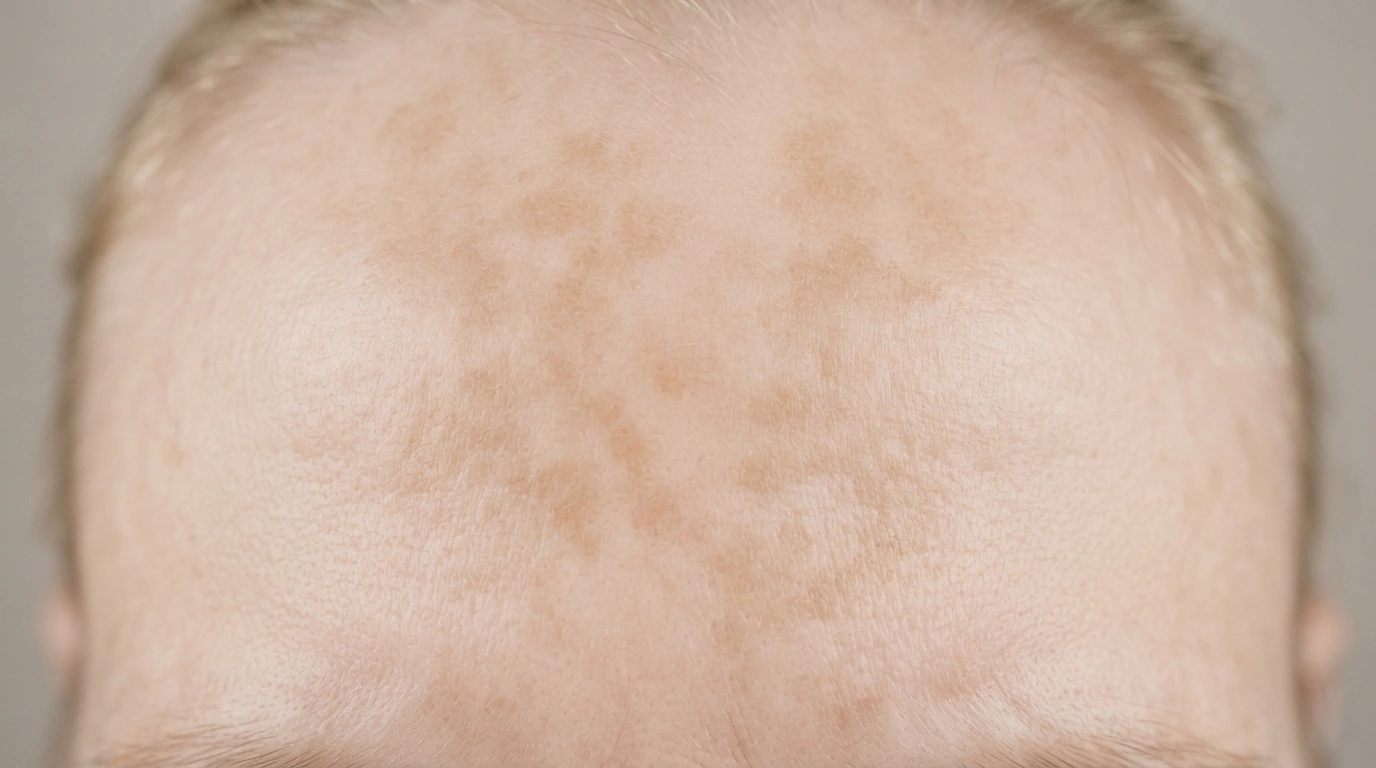

Helps calm inflammation: Acts on pathways involved in acne and rosacea. Affects pigment production: Tyrosinase-related activity may help dark marks.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.

Converts to retinoic acid: Skin enzymes can activate retinaldehyde. Changes cell activity: Retinoic acid acts through nuclear receptors.
Schematic illustration; not a measurement of skin penetration. Effects vary with ingredient identity and formulation.
Built from where each one usually sits in a routine. Introduce one at a time.
Azelaic acid strength should be read together with the product’s indication. Prescription examples include 15% gel for inflammatory rosacea and 20% cream for acne.
15%
20%
Prescription rosacea formulation
Gel formulations are labeled for inflammatory papules and pustules of rosacea. They are not simply a weaker version of a 20% acne cream.
Prescription acne cream
A cream strength used for acne. The cream base and indication differ from the 15% rosacea gel.
Choosing a strength: Choose by the concern and finished product. Cosmetic azelaic acid products are not automatically equivalent to prescription formulations.
Higher strengths: Stinging and irritation can limit use. A larger number does not prove better delivery or better results for a different diagnosis.
Formula matters: Gel, foam and cream vehicles affect delivery and tolerability. Do not compare their percentages as if they were identical formulations.
0.05% and 0.1% retinaldehyde creams have been compared in a controlled photoaging trial. These percentages cannot be directly compared with retinol or tretinoin.
0.05%
0.1%
Lower studied retinal strength
A cream studied for skin texture and hydration. The result applies to that finished formula.
Higher studied retinal strength
Also studied for photoaging; not better for every measured outcome. Tolerance still determines whether a product suits you.
Choosing a strength: Choose retinaldehyde for its own formula and instructions, not a retinol-to-retinal conversion chart.
Higher strengths: A higher percentage may be harder to tolerate. Stronger products sold commercially do not automatically have stronger comparative clinical evidence.
Formula matters: Encapsulation, stability and the cream or serum base affect delivery. A percentage alone is not a measure of how much reaches skin cells.
Approximate windows, not promises.
First few weeksAssess tolerance and texture; immediate softness can come from the base formula.
First few weeksAssess tolerance and texture; immediate softness can come from the base formula.
4–8 weeksSubtle changes may appear in some tested products; evidence varies.
4–8 weeksSubtle changes may appear in some tested products; evidence varies.
8–12 weeksCompare photographs in the same lighting and reassess benefit.
8–12 weeksCompare photographs in the same lighting and reassess benefit.
3–6 monthsPhotoaging trials often need several months; expect modest rather than dramatic change.
3–6 monthsPhotoaging trials often need several months; expect modest rather than dramatic change.
6–12 monthsLong-term evidence is limited for many cosmetic actives; continue only if useful.
6–12 monthsLong-term evidence is limited for many cosmetic actives; continue only if useful.
Stinging, itching and dryness can occur; reduce use for persistent irritation.
Dryness, stinging and peeling can occur; avoid irritated areas.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Stop for persistent burning, swelling, blistering or a new rash. Seek urgent care for breathing difficulty or a severe allergic reaction.
Choose a simple formula and test a small area first. Individual tolerance matters more than an ingredient’s reputation for being gentle.
Choose a simple formula and test a small area first. Avoid actively inflamed or broken skin unless the product is specifically directed for it.
Do not use a cosmetic product as a substitute for diagnosis of an unexplained, changing or persistent skin problem.
Do not use a cosmetic product as a substitute for diagnosis of an unexplained, changing or persistent skin problem.
It is the usual first choice. Very little is absorbed through the skin, it has a long record, and it is what dermatologists switch people to when retinoids stop. Confirm with the doctor managing your pregnancy.
Retinoids are conventionally stopped in pregnancy and while trying to conceive. Ask the doctor managing your pregnancy. Azelaic acid is the usual alternative.
On the skin. The finished product delivers azelaic acid in a particular vehicle.
Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Conversion. No activation step is established as necessary for its intended topical role.
Skin response. Acts on inflammation, acne-related bacteria and pigment pathways; it is not simply an exfoliating peel.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
On the skin. The finished product delivers retinaldehyde in a particular vehicle.
Entering skin. Below the 500 Da guideline; delivery still depends on the formula, solubility, stability and skin condition. Size does not prove effectiveness or penetration depth.
Conversion. Skin can convert retinaldehyde into retinoic acid.
Skin response. Skin can convert retinaldehyde into retinoic acid, which influences cell activity through retinoid receptors.
Additional effects. Proposed pathways do not establish a measured depth of delivery or clinical benefit beyond the studies cited.
Choose for acne or rosacea bumps, especially when uneven tone is also a concern.
Two large vehicle-controlled trials support 15% gel for papulopustular rosacea. Acne has guideline support, but a 10% cosmetic serum should not be assumed equivalent to a studied prescription formula.
Consider for photoaged texture; introduce slowly and judge the complete formula.
A 40-woman trial compared two active strengths without a retinoid-free vehicle group. It supports cautious formula-specific claims, not guaranteed superiority to retinol or acne medicines.
Sources