HPV

HPV is the family of viruses behind warts. On the skin it makes rough, thickened growths, mostly on the hands and feet. Molluscum contagiosum is a different virus, from the pox family. It makes smooth, pearly bumps with a small dimple in the middle, mostly on the trunk and in skin folds. Comparing them means comparing two viruses and the two very different bumps they leave.
| The difference | HPV | Molluscum Contagiosum |
|---|---|---|
| What it is | A large family of papillomaviruses | A single poxvirus |
| Does it hurt | Only under pressure | Usually not |
| What it does over time | Clears, often after months or years | Clears in about 6 to 18 months |
| Treatment | Salicylic acid, then freezing | Often nothing at all |
Side by side
HPV
A large family of papillomaviruses
More than 200 HPV types are known. Only a handful cause the ordinary warts people get on hands and feet, and those are the ones this page is about.
Molluscum Contagiosum
A single poxvirus
Molluscum contagiosum virus has only a few types, and one of them accounts for most childhood cases. It is not related to HPV.

The barrier is intact and nothing is getting through it.

A poxvirus, spread by skin-to-skin contact and by shared towels, mats and baths. Damp or eczema-prone skin lets it in more easily.

The virus makes skin cells multiply into small firm domes with a dimple in the middle, each one full of virus.

Scratching or shaving over a bump carries the virus along the line of the scratch, which is why new ones appear in rows.

Eventually it recognizes the infection and clears it, often with a red, sore-looking flare first. That flare is the sign it is ending, not worsening.
HPV
Rough, thickened warts
A firm grey-brown lump with a cauliflower surface and a thickened rim. Most warts have tiny dark dots inside, which are small clotted blood vessels.
Molluscum Contagiosum
Smooth bumps with a centre dimple
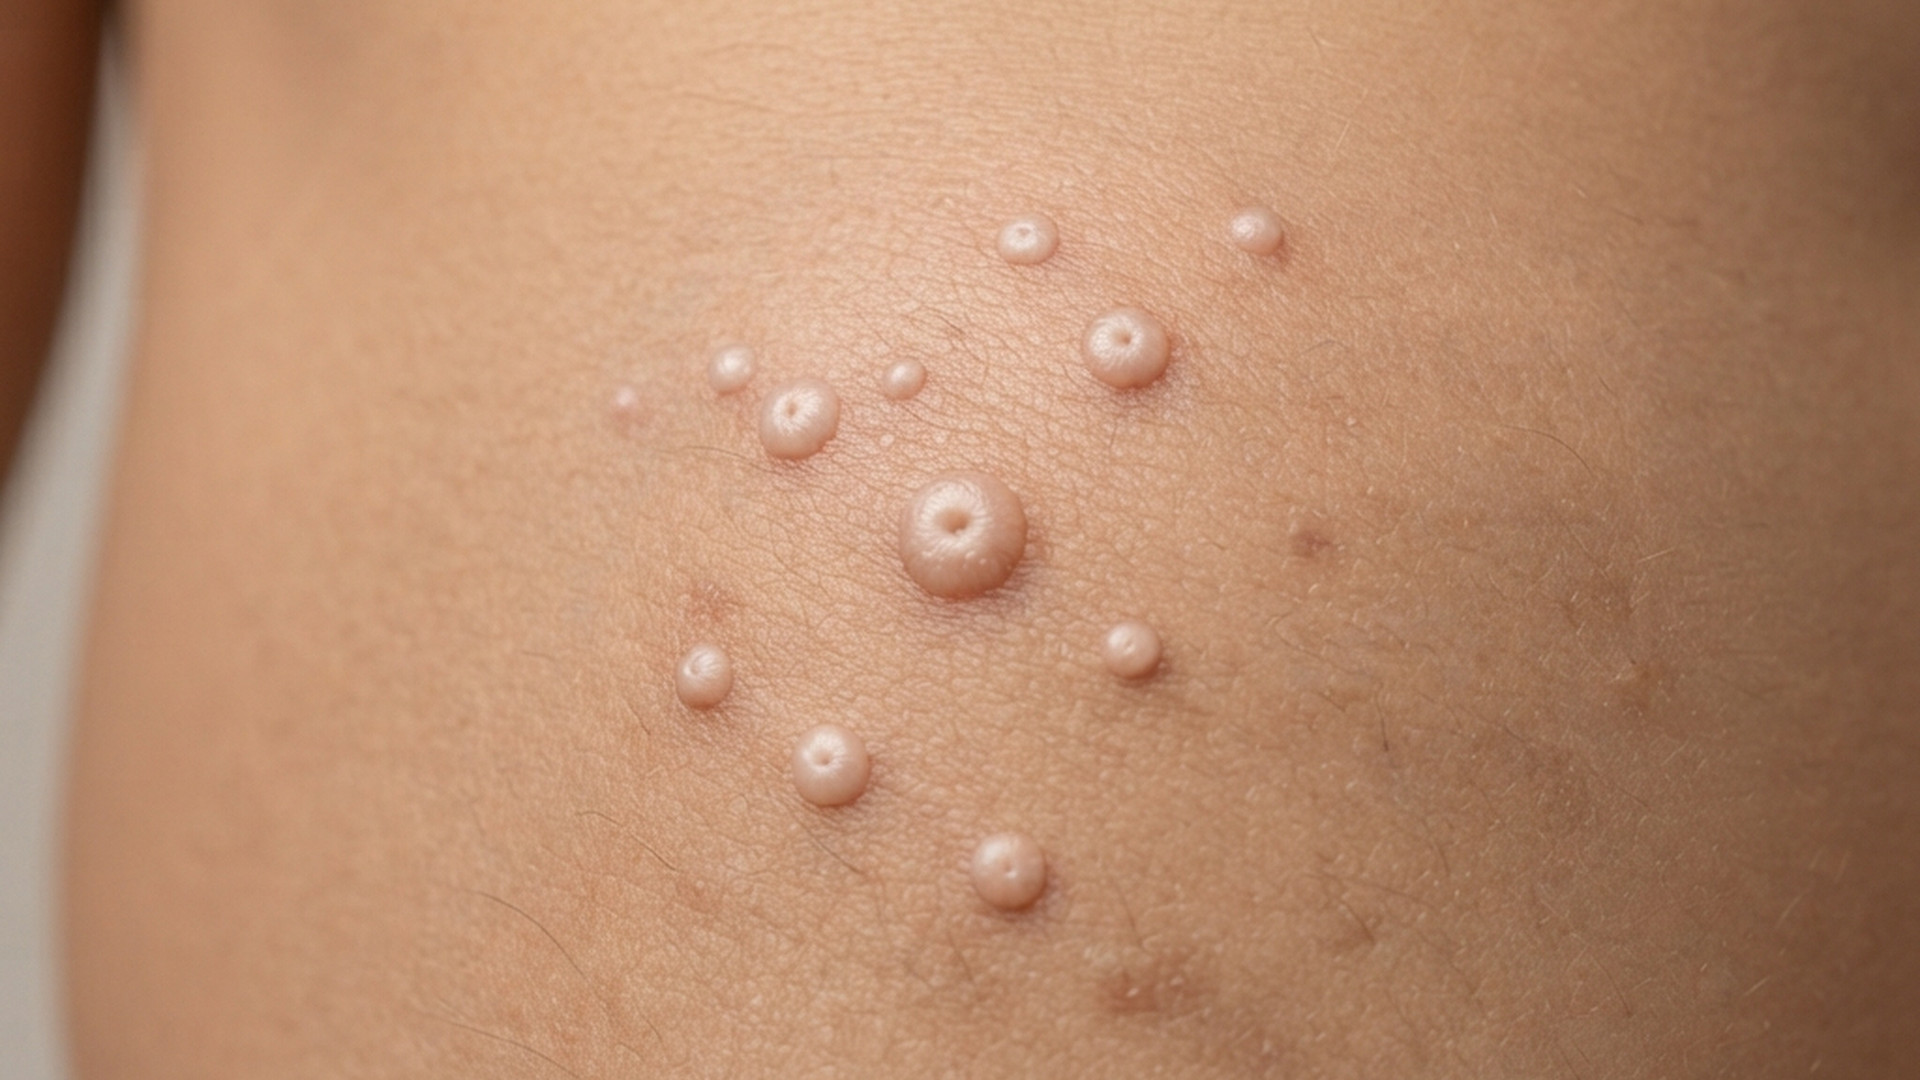
Firm, dome-shaped and shiny, skin-coloured or slightly pink. The small central pit is the most useful sign, and it holds a soft white core.
HPV
A pinhead to a pea
A single wart thickens over weeks, and several can merge into one larger patch.
Molluscum Contagiosum
Two to five millimetres
Each bump stays about the size of a small bead. What increases is the number of them.
HPV
Only under pressure
A hand wart is painless. A wart on the sole takes your weight and can feel like standing on a stone.
Molluscum Contagiosum
Usually not
Some bumps itch. A scratched one turns red and sore, which often means it is about to clear.
HPV
Hands, fingers and feet
Backs of the hands, around the fingernails, knees, and the soles of the feet.
Molluscum Contagiosum
Trunk, armpits and skin folds
Chest, tummy, sides, armpits, the crooks of the elbows and the backs of the knees. Face and neck in small children.
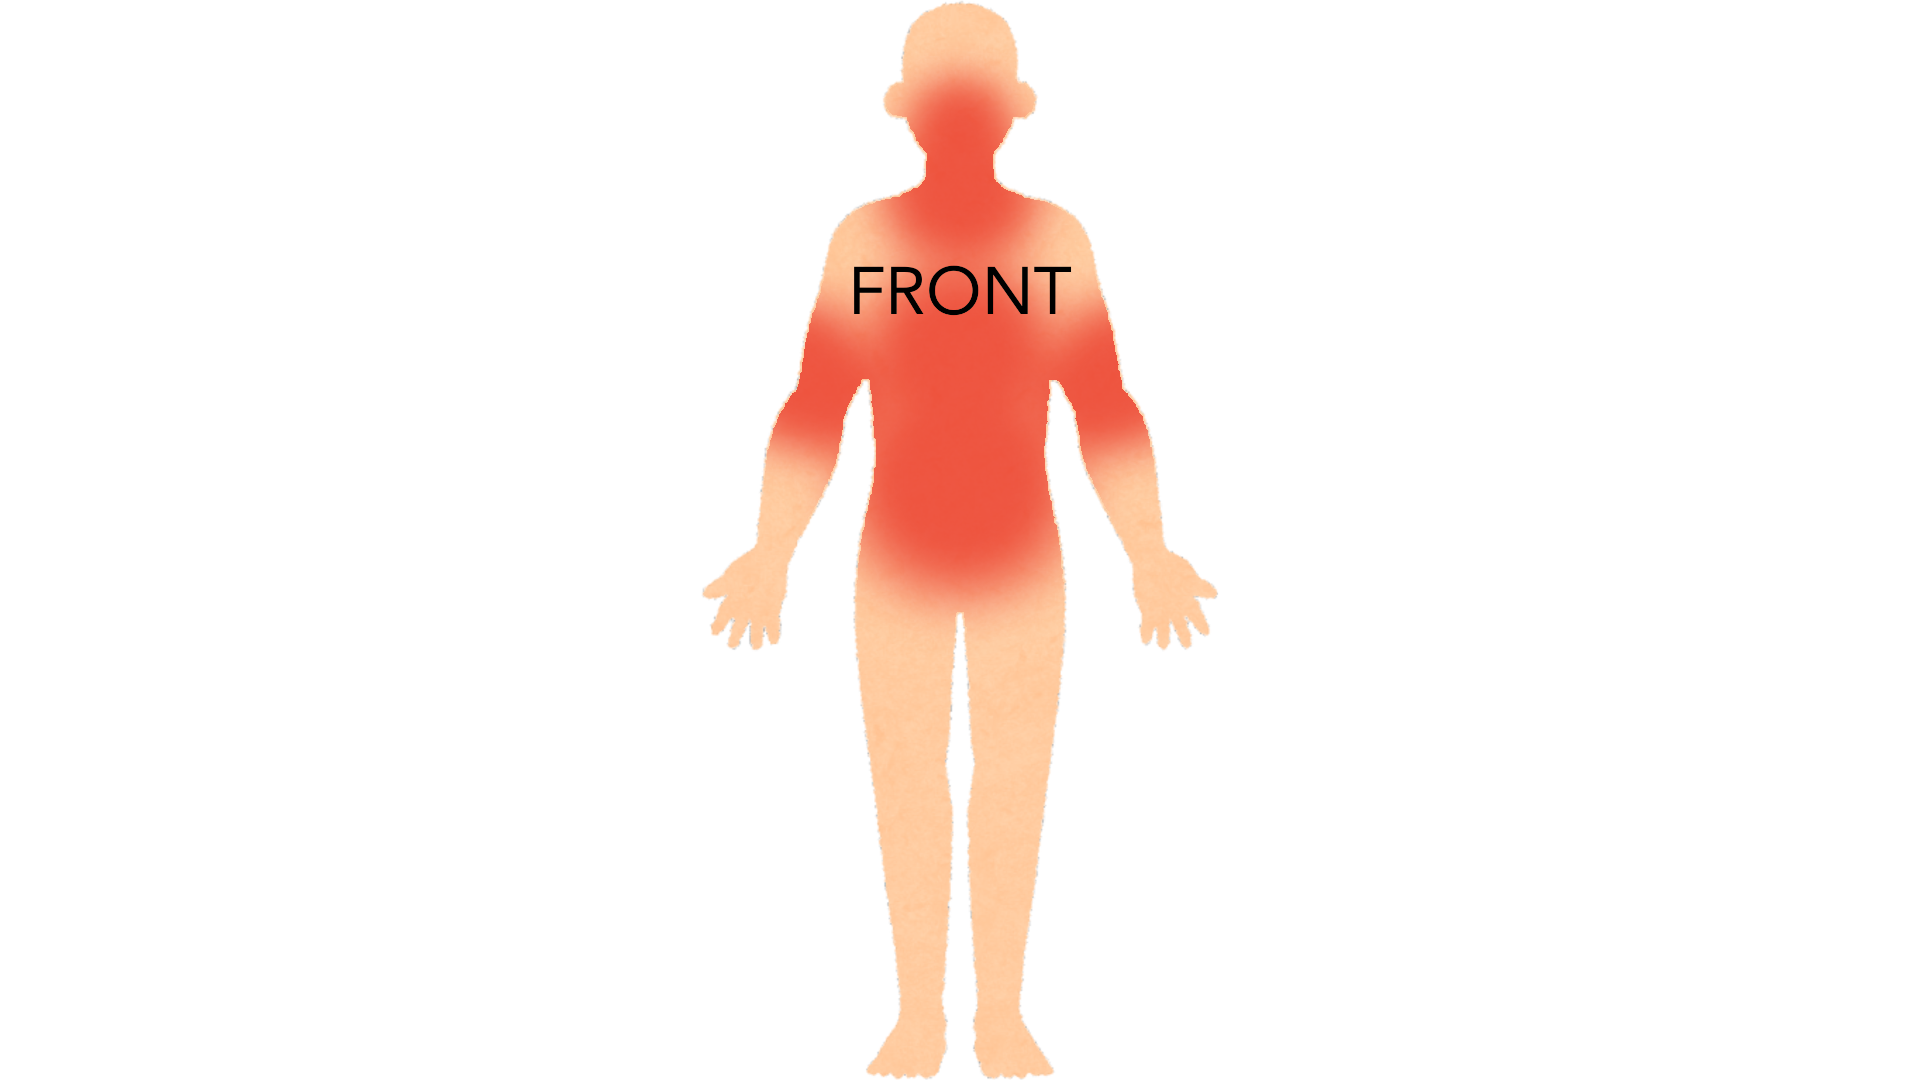
In children the usual places are the trunk, the armpits, the inner arms, the neck and the face — skin that is warm, folded and rubbing. Wherever they are, they cluster in creases and run in lines where a child has scratched and carried the virus along.
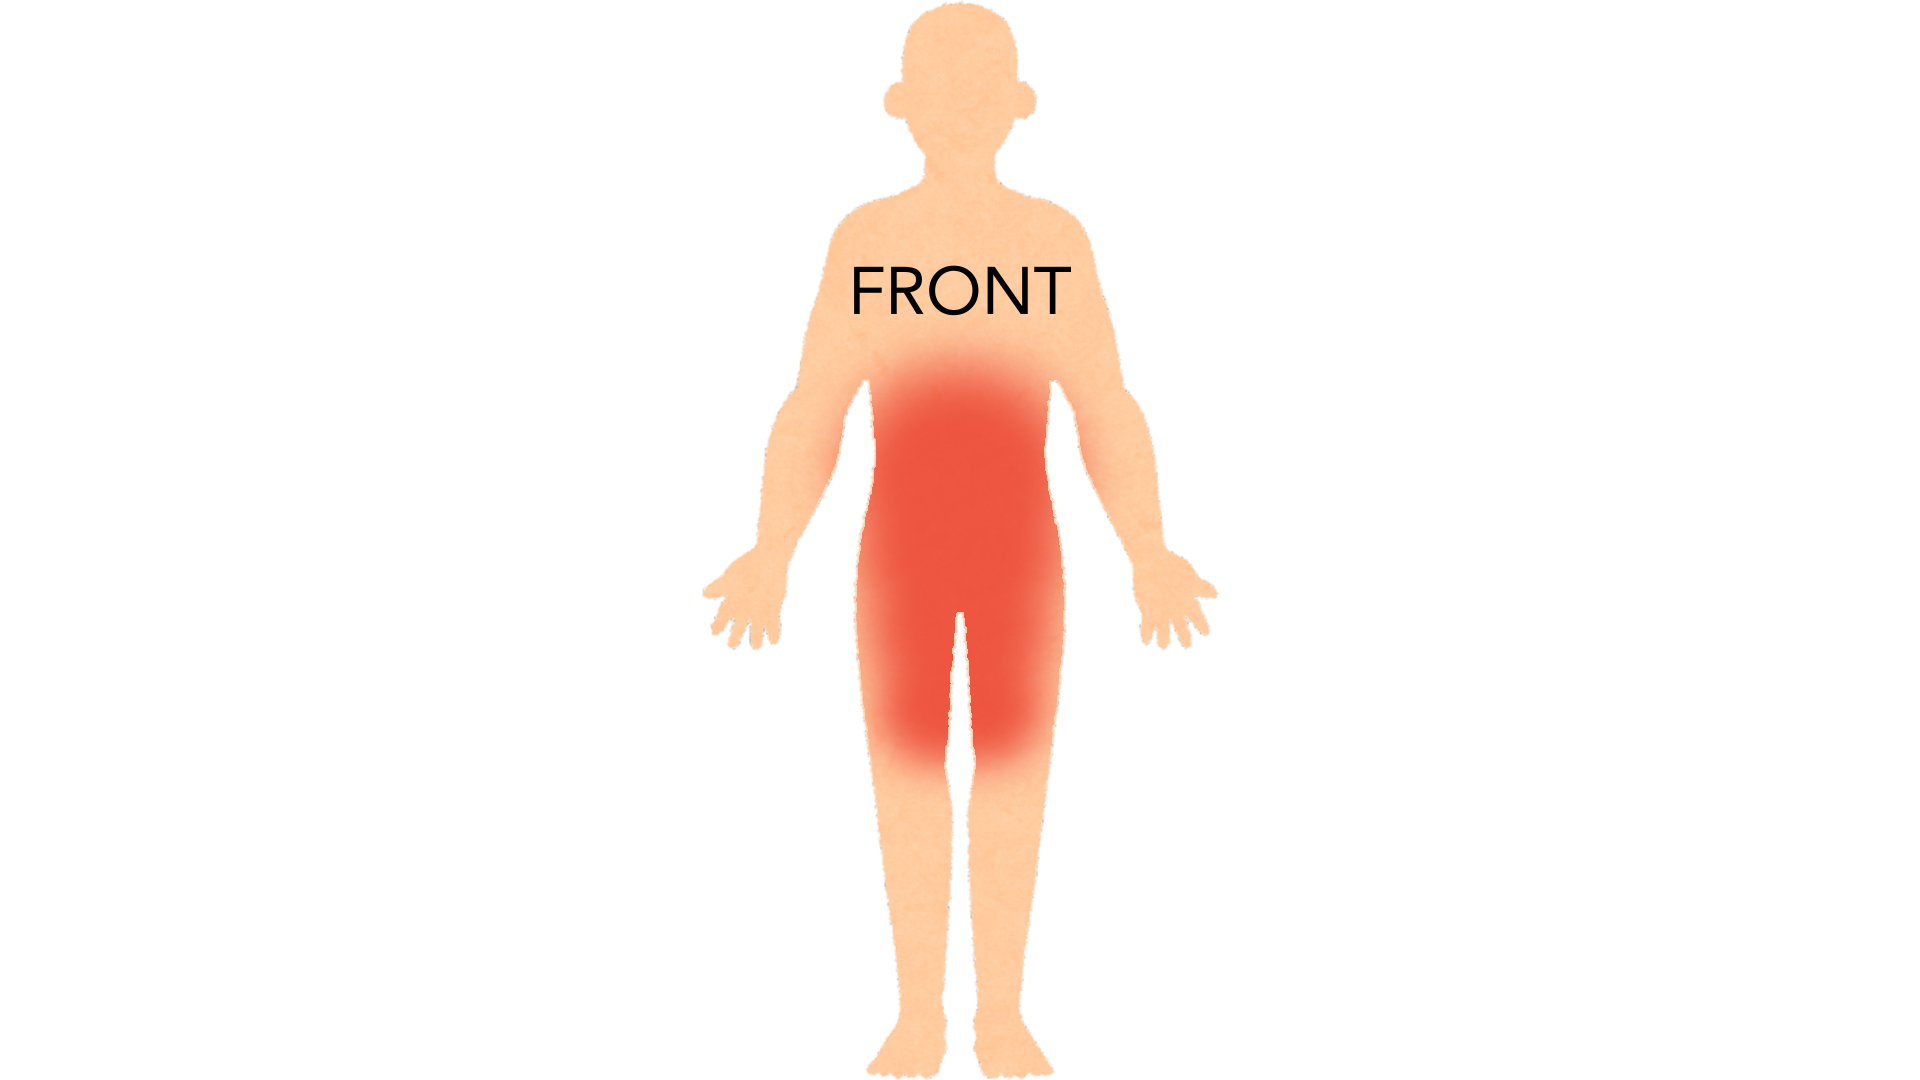
In adults, bumps on the lower abdomen, the groin, the inner thighs and the genitals usually mean the virus was passed on through sexual contact, and testing for other infections is normally offered at the same time.
HPV
Clears, often after months or years
The immune system recognises the virus eventually. Children clear warts faster than adults do.
Molluscum Contagiosum
Clears in about 6 to 18 months
New bumps appear while old ones fade. Once the immune system catches up, the whole crop goes.
HPV
Salicylic acid, then freezing
Salicylic acid daily, with gentle filing between applications, then liquid nitrogen freezing in a clinic if that is not enough.
Molluscum Contagiosum
Often nothing at all
Most crops are left to clear naturally. A clinician can scrape or freeze individual bumps that are irritated or awkwardly placed.
Doing nothing is a real plan, and for a lot of children it is the best one. The infection ends on its own, usually within six to eighteen months, and it leaves nothing behind if the bumps are left alone. No treatment has been shown to change the long-run outcome dramatically. The cost of waiting is time; the cost of treating is discomfort and, sometimes, marks that outlast the bumps.

Most molluscum spread is self-spread, carried from one patch of skin to another on fingernails, razors and towels. Trimmed nails do less damage during sleep scratching, clothing or a plaster over the bumps stops them being caught and stops them reaching other children, and everyone having their own towel keeps it out of the rest of the household. In adults, simply stopping shaving over the area often halts the spread on its own.
For the dry itchy eczema-like patch that develops around the bumps in about a third of children — not for the bumps themselves. Treating it properly matters, because the itch drives the scratching and the scratching is what spreads the infection. Use it on the skin between and around the bumps, thinly and for a short course. Strong steroid creams applied over the bumps calm the redness and can help the virus stay longer.

The wart products in the pharmacy are the wrong tool here. Molluscum is a poxvirus, not the wart virus, and the bumps are soft domes rather than thickened skin for an acid to dissolve. On thin skin, on a child, and on thirty bumps at once, it mostly buys irritation and dark marks. If a bump is going to be treated, the clinic options are more reliable and better controlled.

A common suggestion, usually combined with iodine, and the evidence behind it is a small number of low-quality studies. Against an infection that clears by itself, that is very hard to read. The real drawback is that it stings and it commonly causes an allergic rash on children's skin, which then itches, which then gets scratched.

A blistering liquid painted onto each bump in the clinic and washed off a few hours later at home. A small blister forms over the next day and the bump lifts off with it. It is painless to apply, which is why it suits children, and it usually takes two or three visits. It is not used on the face or the genitals, and it can leave a dark or pale mark, so a few bumps are treated first to see how the skin reacts.
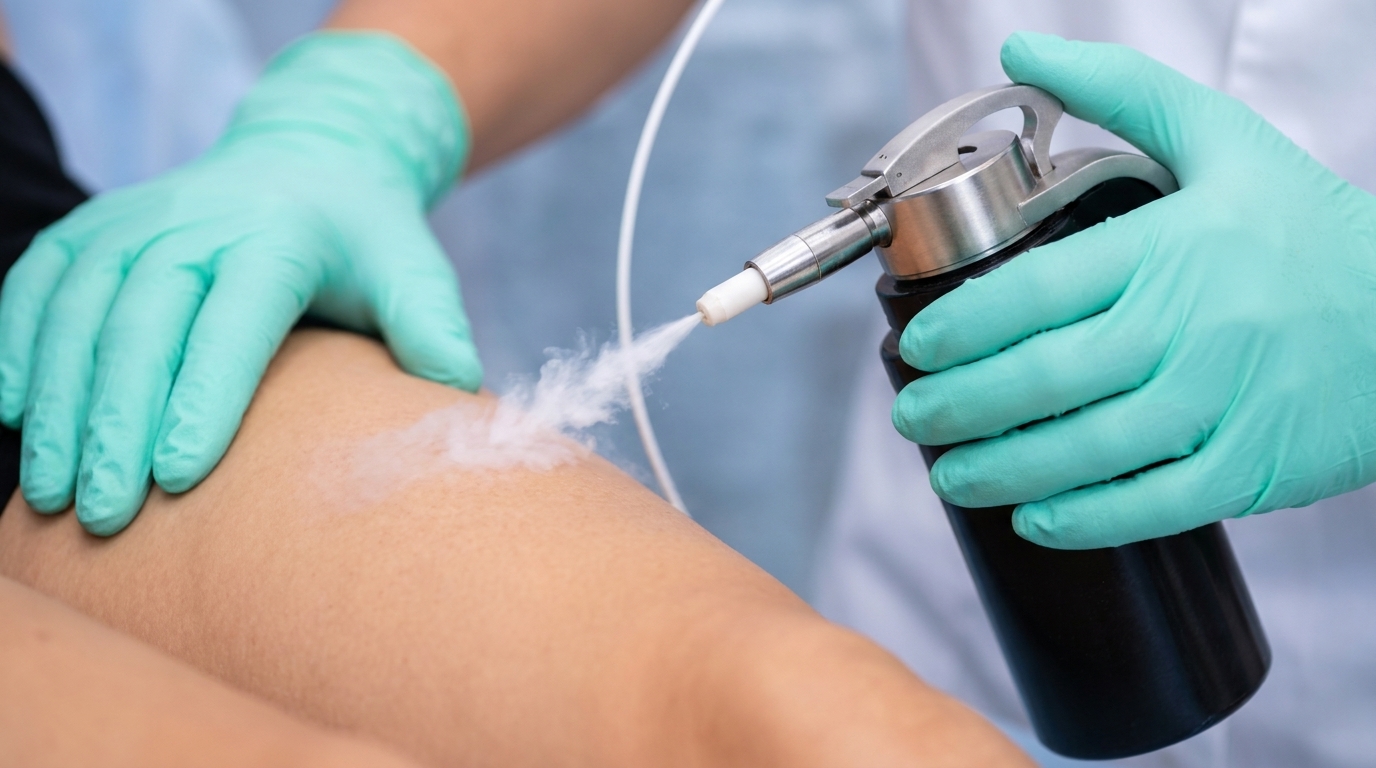
Each bump is frozen for a few seconds, and it usually takes several visits a few weeks apart. It works, and it is quick. It also stings sharply at the time, which most young children will not sit through twice, and it leaves dark or pale marks more readily than the other options — a real consideration on deeper skin tones, where those marks can last longer than the infection would have.
An old stomach-acid tablet, taken by mouth for several weeks in the hope of nudging the immune system into recognizing the virus. It appeals because it is painless and needs no procedure, which matters for a frightened child with many bumps. The trials do not support it, and it interacts with a number of other medicines, so it is a long shot rather than a plan.

A dilute alkaline solution dabbed on individual bumps at home, usually once or twice a day until each bump becomes inflamed and then clears. It is cheap and it can be done without appointments. It stings, it works by irritating the skin, and it can leave dark or pale marks if it is overdone — so it goes on the bumps only, and starting with a few is sensible.

A newer prescription gel mixed and applied at home once a day, designed specifically for molluscum. In its trials about a third of children had all their bumps clear at twelve weeks, against roughly one in five given the placebo gel — a real effect, but a modest one. Redness and irritation where it is applied are common, and cost and availability are the practical limits.

A retinoid dabbed onto individual bumps to irritate them into clearing. It is sometimes chosen for bumps on the face, where blistering or scraping is less appealing. The evidence for it in molluscum is thin, it is slow, and it makes the skin around the bumps red and flaky, which is its own reason to scratch.

This one was studied properly in children, in two large trials, and it did not work any better than the placebo cream — while causing more skin reactions, and in some children pain and swelling. It is still prescribed for molluscum out of habit. On the evidence there is, it should not be.
HPV
Bleeding, changing, or spreading
Worth a visit if a growth bleeds without being knocked, changes colour or shape, or keeps spreading despite months of treatment.
Molluscum Contagiosum
Near the eye, or turning hot
Worth a visit if bumps sit on the eyelid, if one becomes hot and swollen with spreading redness, or if you are not sure what it is.
HPV
HPV thickens the skin. It drives the cells in the outer layer to multiply, so the result is a hard, raised, rough growth. The dark specks people call seeds are the small blood vessels the wart has recruited.
Molluscum Contagiosum
Molluscum fills a pocket. The virus multiplies inside skin cells and leaves a soft white core in the middle of each bump. The surface stays smooth, and the dimple is the opening over that core.
HPV
HPV needs a break in the skin. It travels on direct contact and on damp shared surfaces such as pool decks and changing room floors. It also travels on your own body, so picking a wart or shaving over one can move it.
Molluscum Contagiosum
Molluscum needs contact more than a break. It passes between children through skin contact, shared towels and shared bath water. Scratching one bump and then scratching normal skin is how a line of them appears.
HPV
The HPV types that cause hand and foot warts are not the same types found elsewhere in the body. HPV is a large family, and different members prefer different tissue. This page covers the skin ones only.
Molluscum Contagiosum
Molluscum has no such split. It is one virus that lives in the outer layer of skin, and it does nothing beyond making the bumps you can see.

This is the textbook picture: firm, dome-shaped bumps two to five millimetres across, pink to pearly white, each with a small dip in the center. They are commonly mistaken for warts, for whiteheads, or for a few stray bug bites, and children are often treated for acne or eczema first. The dip in the middle is the giveaway. Scratching them is what spreads them, so a line of bumps along a scratch mark is a normal part of the picture.

The pearly shine textbooks describe already starts to fade here, and the bumps read as pale pink to skin-colored. The shape is the more dependable sign: firm, domed, with a central dip, and often in a small group in one warm fold of skin. One bump going red and sore usually means the immune system has finally found it and that bump is on its way out. That flare looks like an infection and is often treated as one, when the better answer is usually to leave it alone.

On brown skin the bumps usually look skin-colored or slightly gray rather than pink or pearly, and the shine is much less obvious. The dip in the center and the firm dome shape are the reliable signs, and running a finger over the area often finds them faster than looking does. Because the color cue is weak, molluscum here is regularly read as small warts, as a rash, or as nothing at all, and a child can be treated for the wrong thing for months.

What molluscum leaves behind matters more here than the bumps do. Bumps that have been scratched, picked or treated with something that blisters the skin heal into flat dark marks, and on deeper skin tones those routinely take six to twelve months to fade — far longer than the bump lasted. Pale spots can be left as well, and they show up more. Since molluscum clears on its own, watchful waiting and the gentler treatments are often the better trade, and treating a few bumps first to see how the skin answers is sensible.
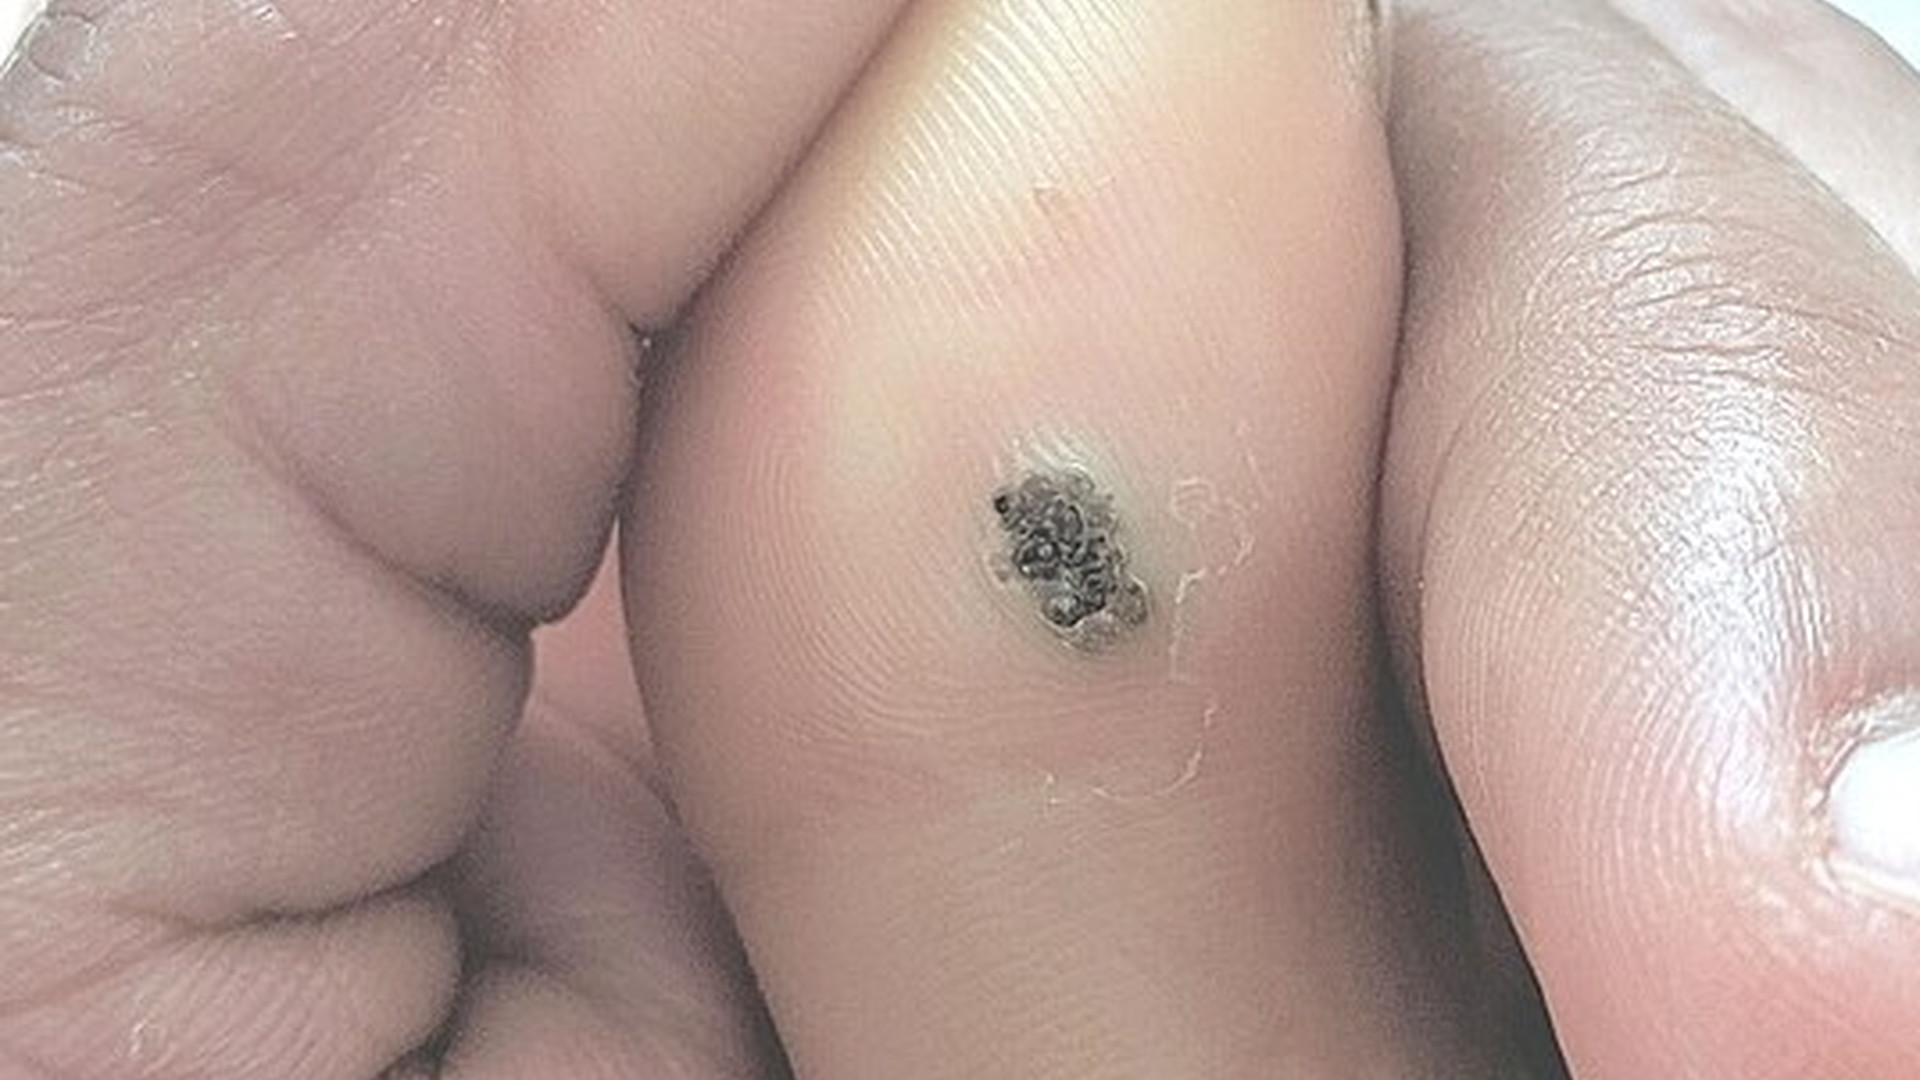
The mix-up that matters most, because the treatments are different. Both are small firm bumps a child picks up from contact, but a wart has a rough, grainy surface, often with tiny dark dots in it, and no dip in the middle. Molluscum bumps are smooth, dome-shaped and pearly with a central dip. They are caused by completely different viruses, and wart removers bought for one are not the answer for the other.
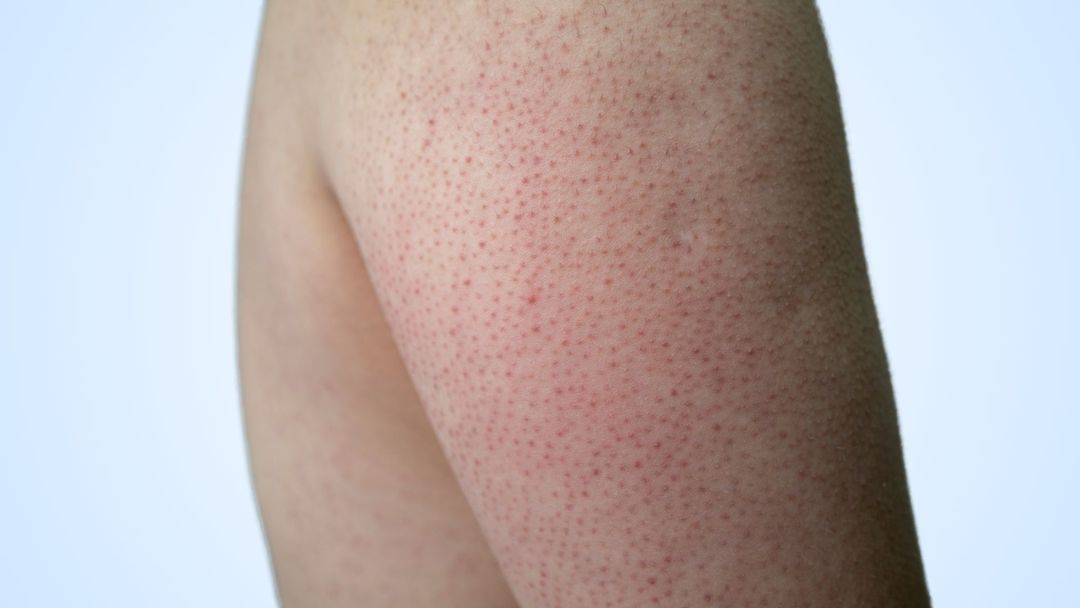
Both cover a child's arms in small bumps, and both are harmless. Keratosis pilaris bumps are much smaller, rough like sandpaper, and there are dozens of them evenly spread over the backs of the upper arms and the fronts of the thighs, one at each hair. Molluscum bumps are bigger, smooth, dome-shaped with a dip on top, and they come in scattered clusters and lines rather than covering an area evenly.
Common questions
No. Molluscum is caused by a poxvirus called molluscum contagiosum virus. HPV is a completely separate family of viruses, and it is the one that causes warts.
It is an everyday nickname for the smooth, shiny look of the bumps. The name is misleading, because molluscum is not a wart and not related to the wart virus.
HPV makes rough, thickened growths with tiny dark dots, usually on hands and feet. Molluscum makes smooth, firm, dome-shaped bumps with a small dimple, usually on the trunk and in skin folds.
Yes. They are two common infections that pass around children, and having one does not protect you from the other.
Neither is thought to linger once the skin clears. When the immune system catches up, the bumps go and usually do not come back in the same place.
Molluscum, usually. It tends to run 6 to 18 months, while warts often take a year or more in children and longer in adults.