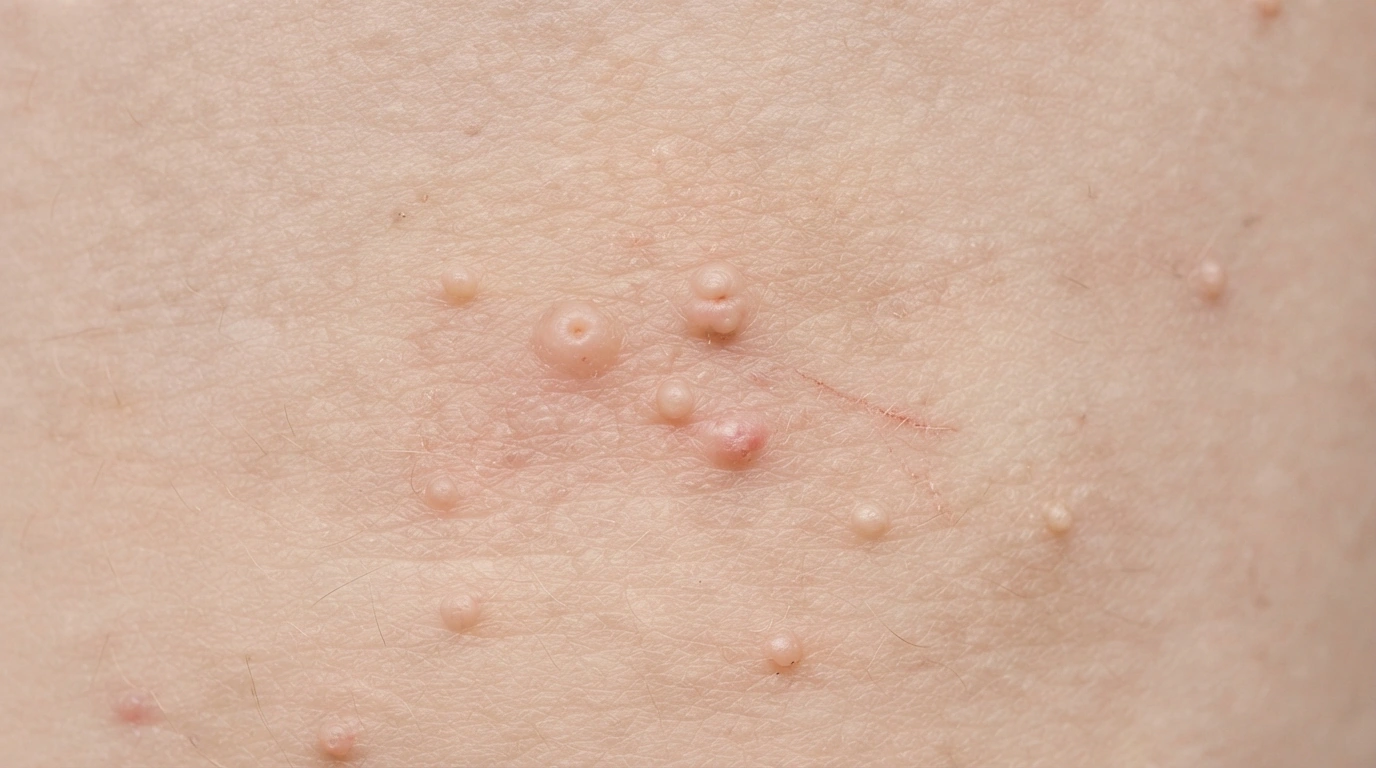
Impetigo
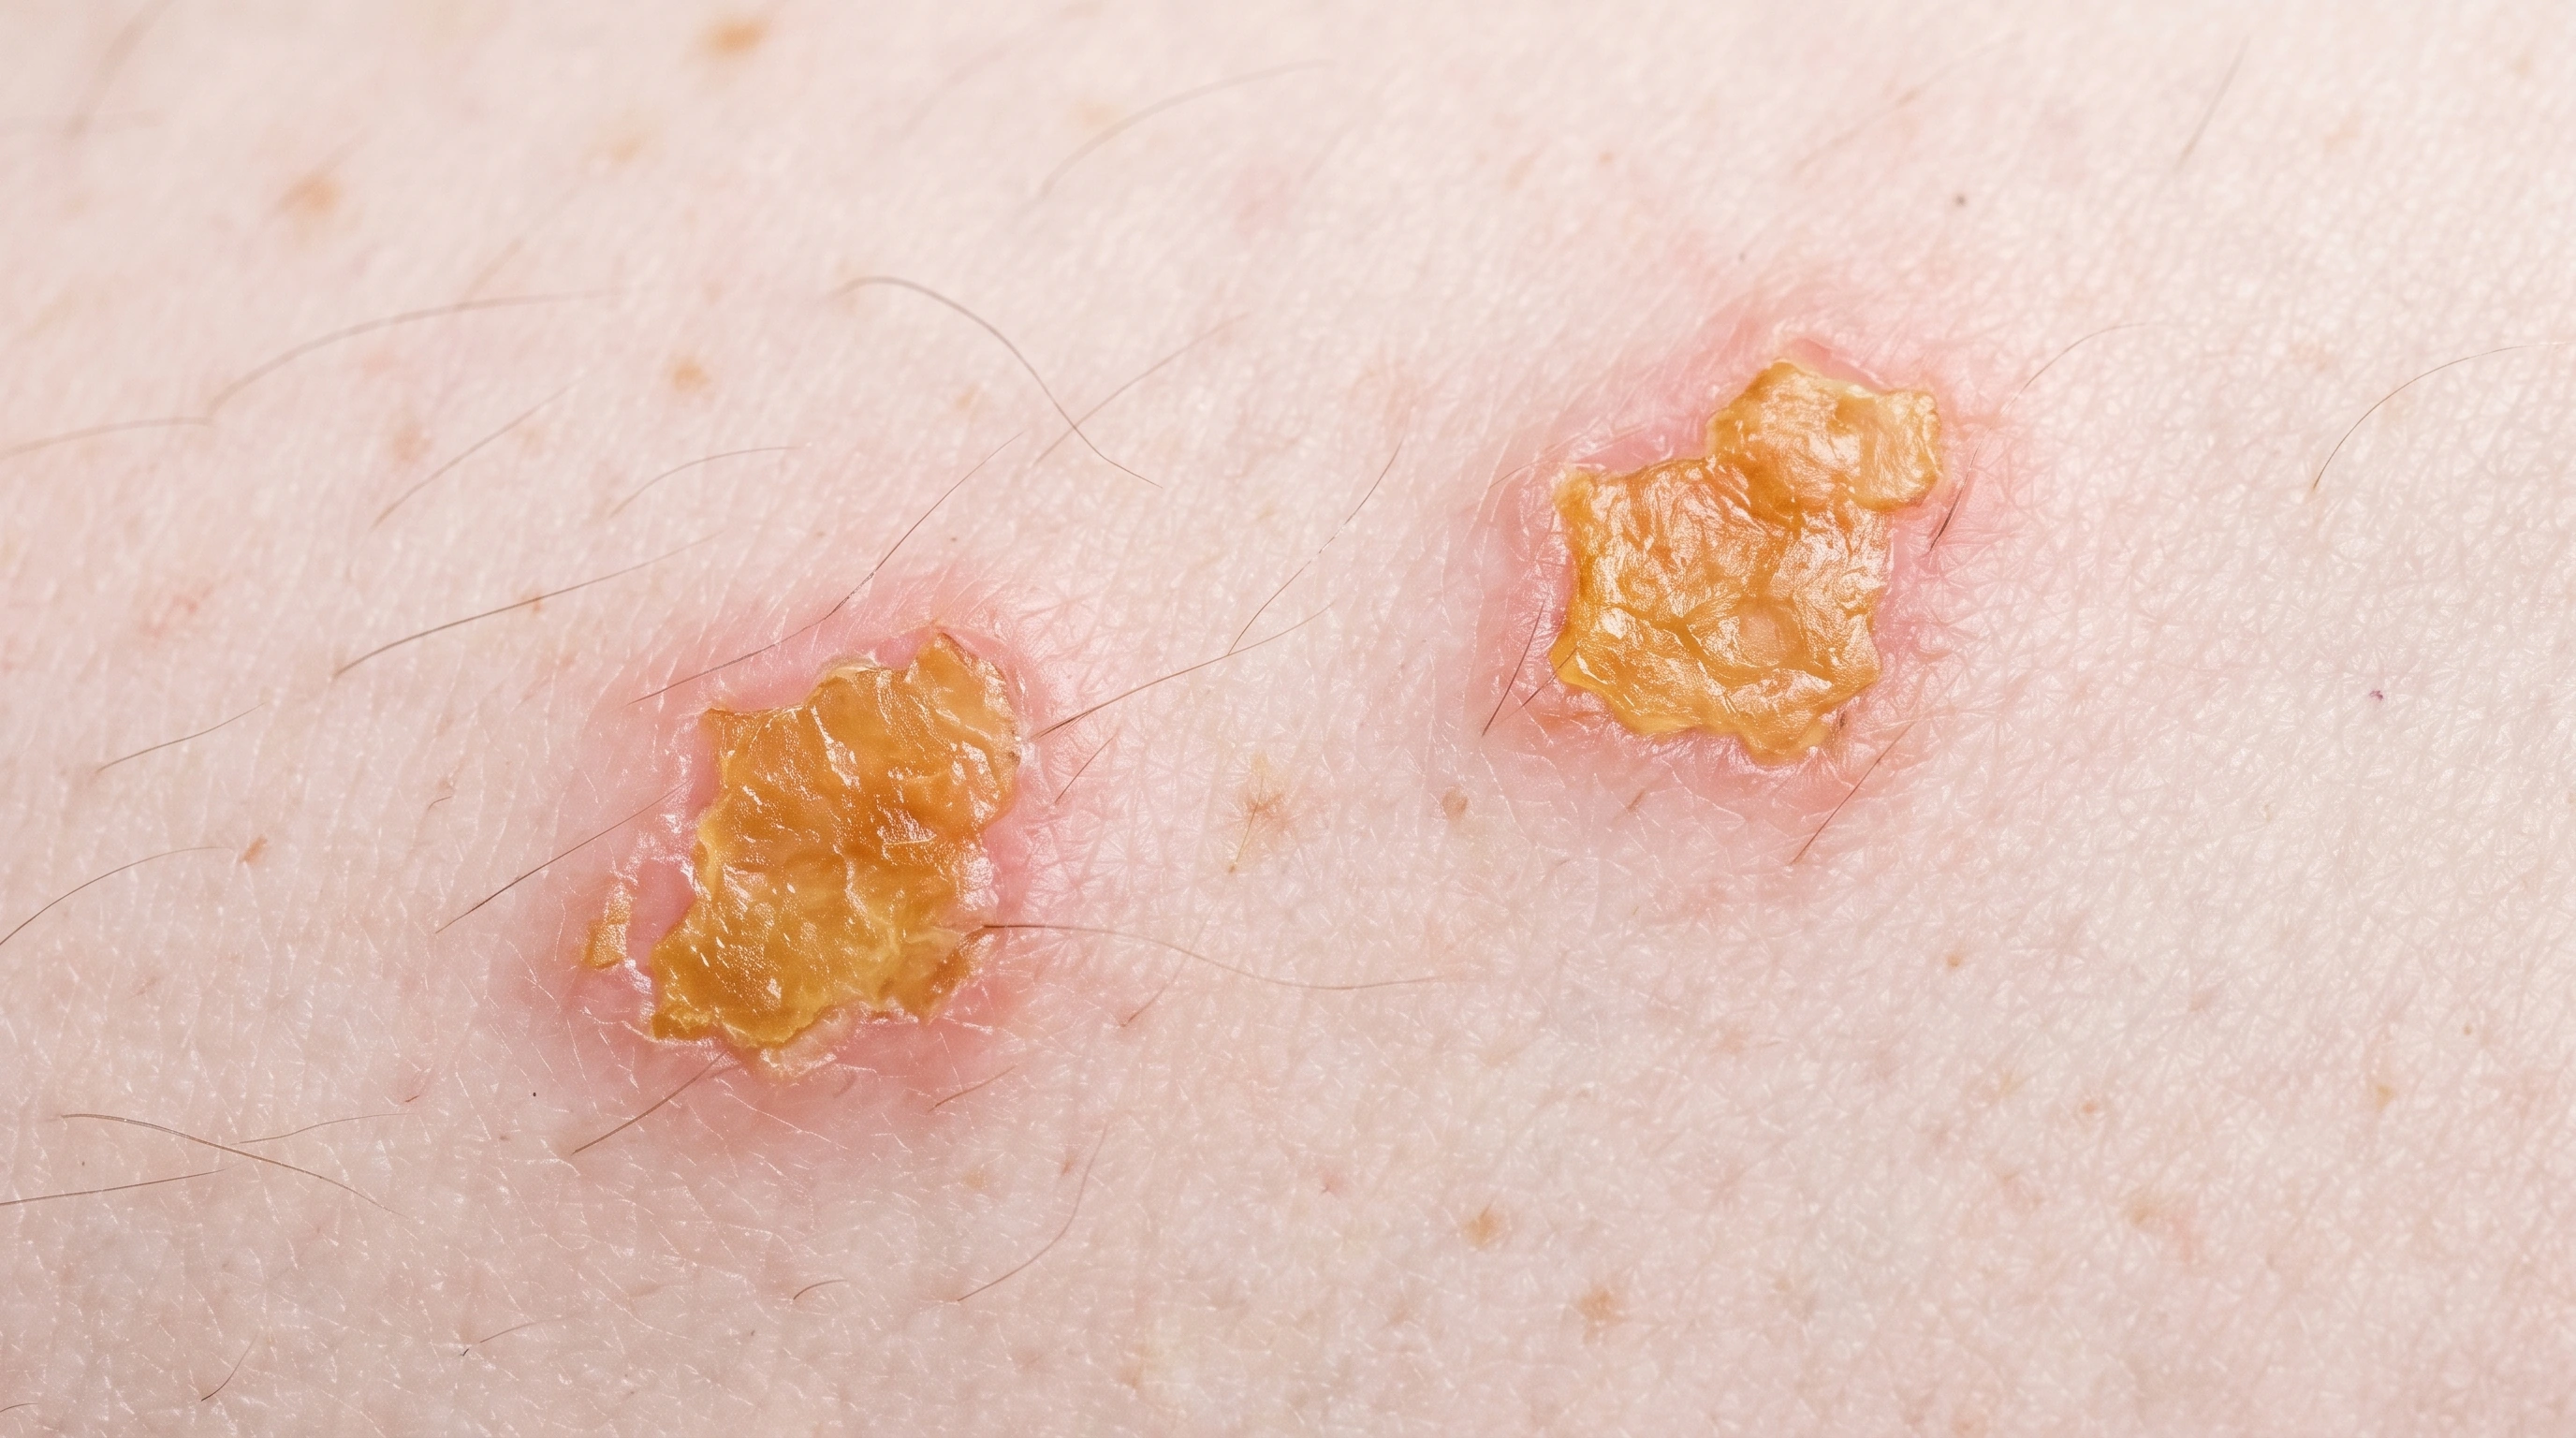
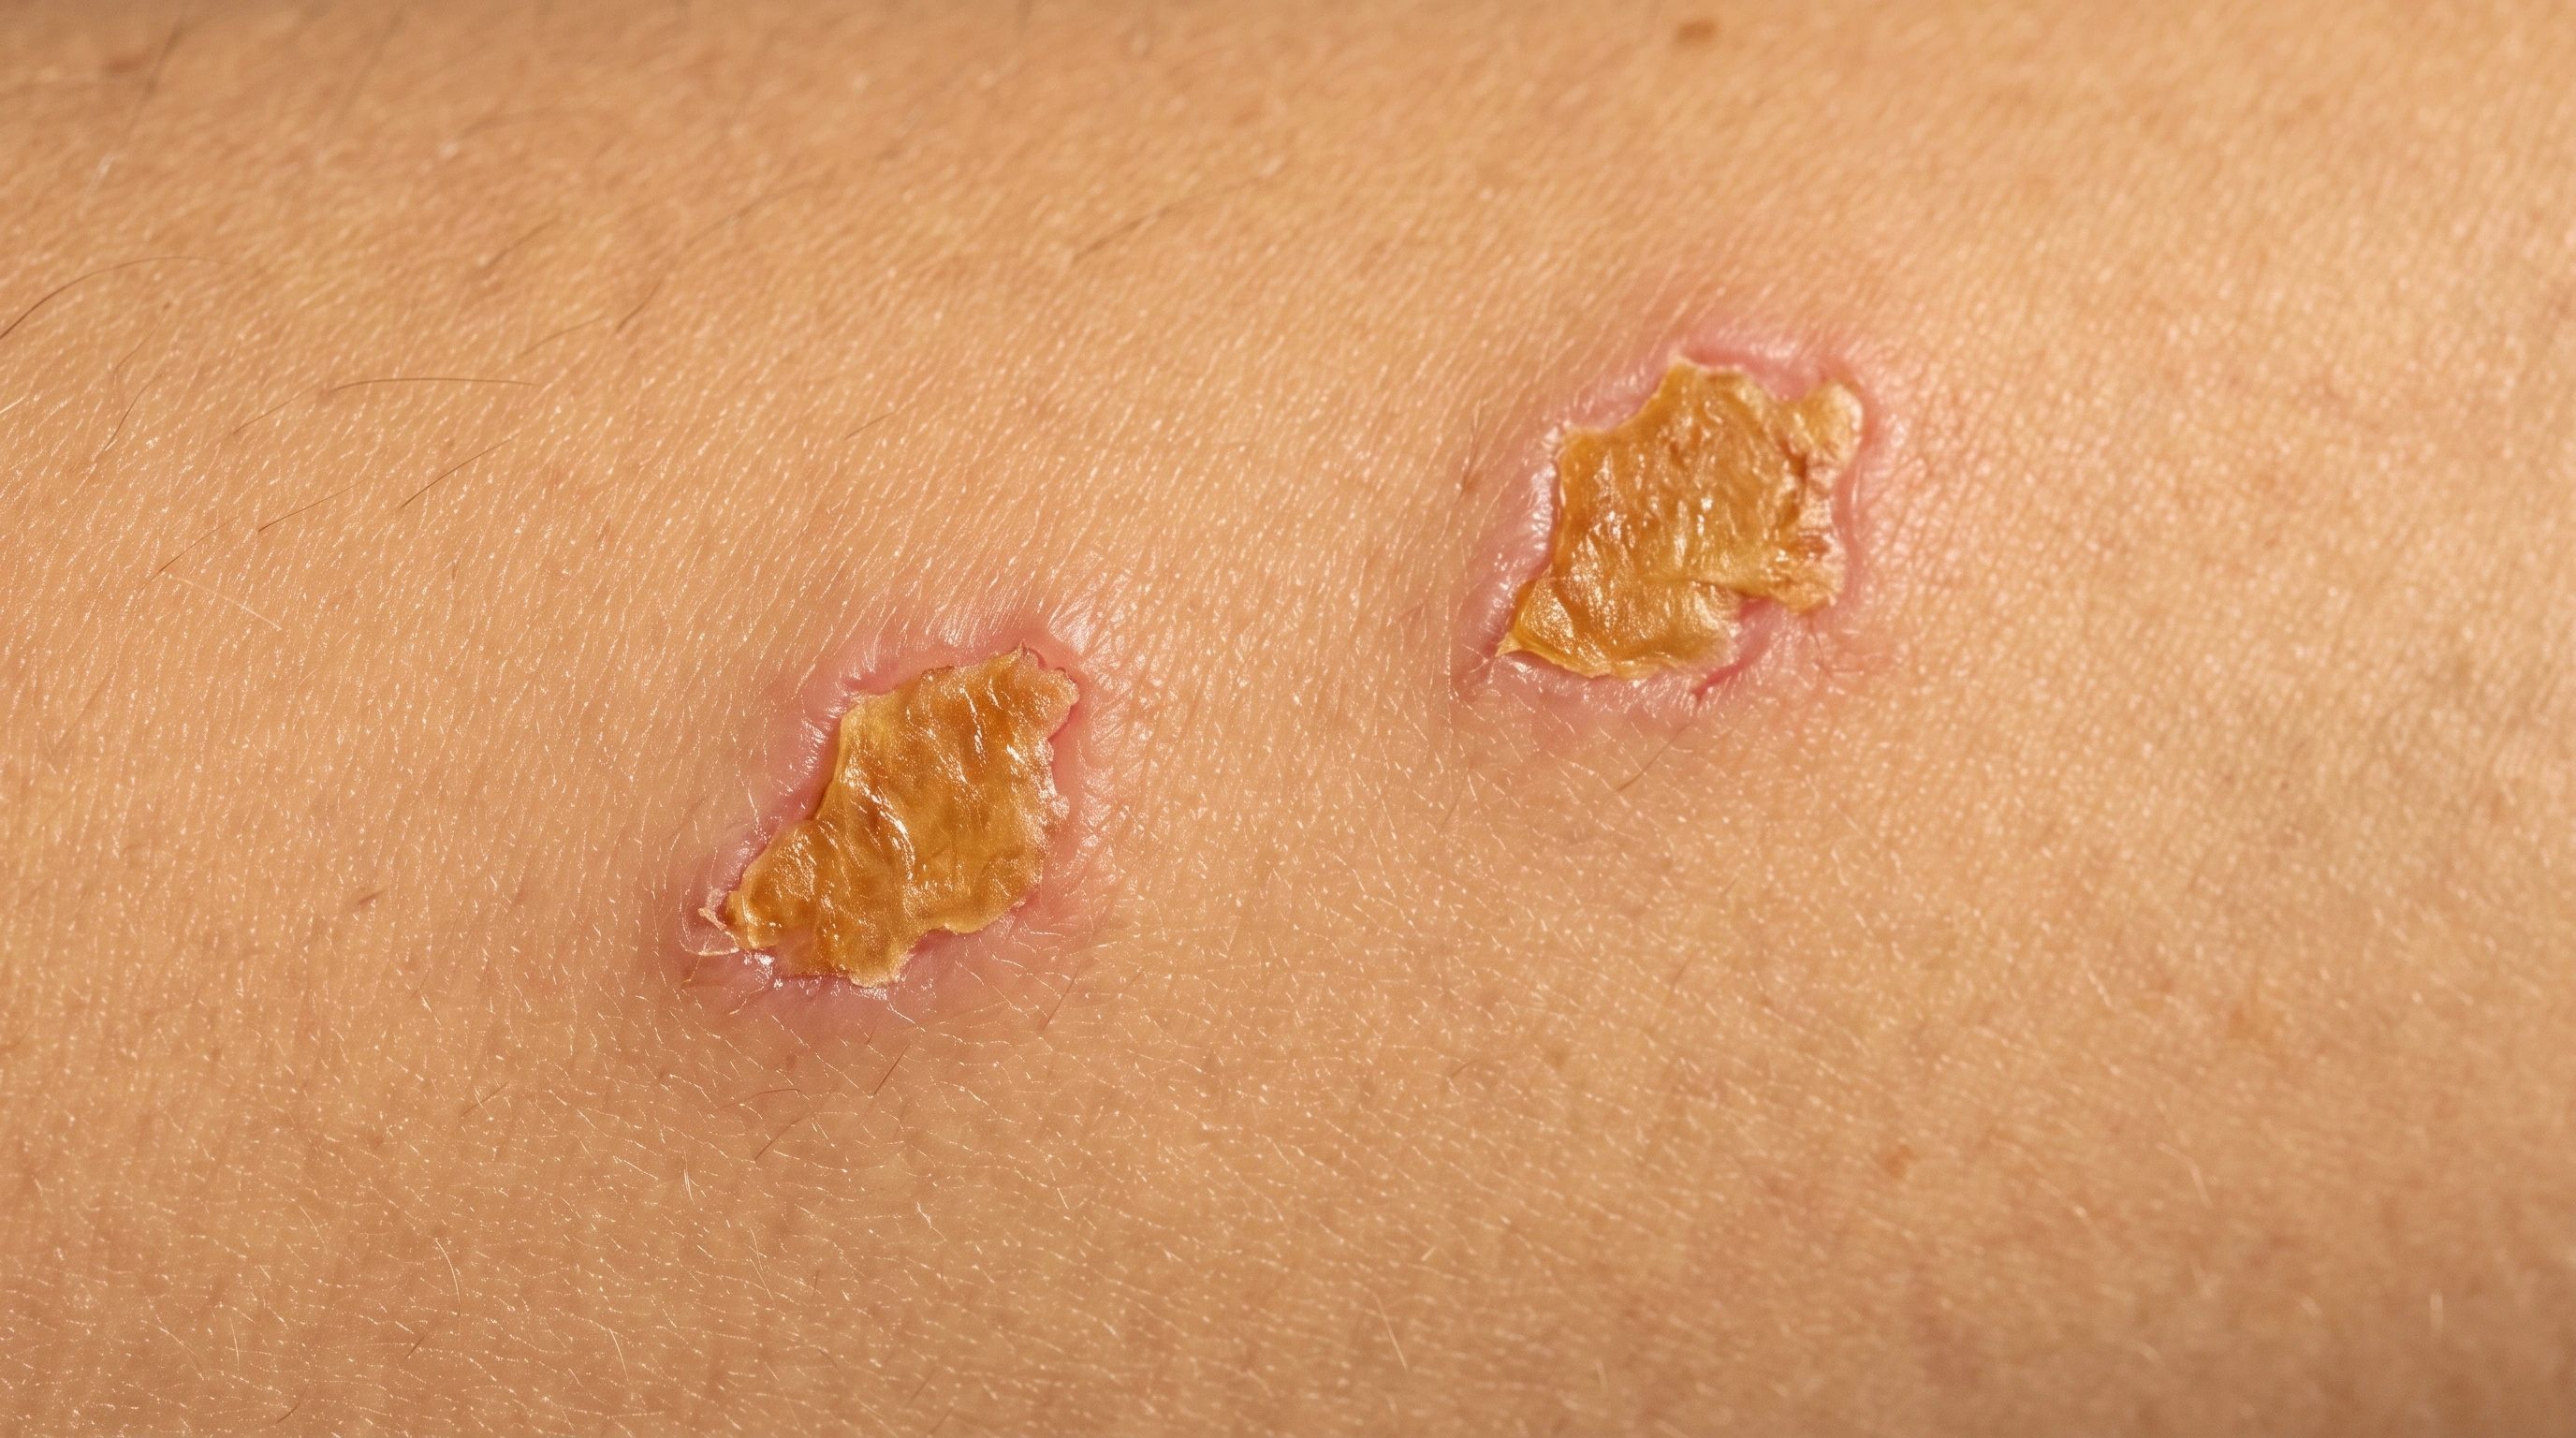
Impetigo is a common bacterial skin infection that sits in the top layer of the skin. It shows up as sores that break open and dry into a golden-yellow crust. It is very contagious, mostly affects children, and clears quickly once it is treated.

Key facts
Impetigo at a glance.
Typical signs
Sores with golden crusts
Common locations
Nose, mouth, arms, legs
Expected course
Usually clears promptly with treatment
Treatment options
Topical or oral antibiotics
What is it?
Top things to know about Impetigo
- It is a bacterial skin infection. Staphylococcus aureus and group A streptococci are the usual causes.
- It has two forms. Nonbullous impetigo forms crusts; bullous impetigo forms blisters.
- Bacteria enter broken skin. Eczema, scratches and bites are common entry points.
- Testing is selective. Swabs help with recurrent, resistant or unusual cases.
What it looks like
What Impetigo looks like
Impetigo is a contagious bacterial skin infection, most common in young children. It usually starts as small red sores or blisters that burst and leave honey-colored crusts. It often appears around the nose and mouth, but can show up anywhere, especially on broken skin like scrapes or eczema. The sores can itch and spread quickly through scratching and close contact.
Impetigo has two main forms, plus a deeper version.
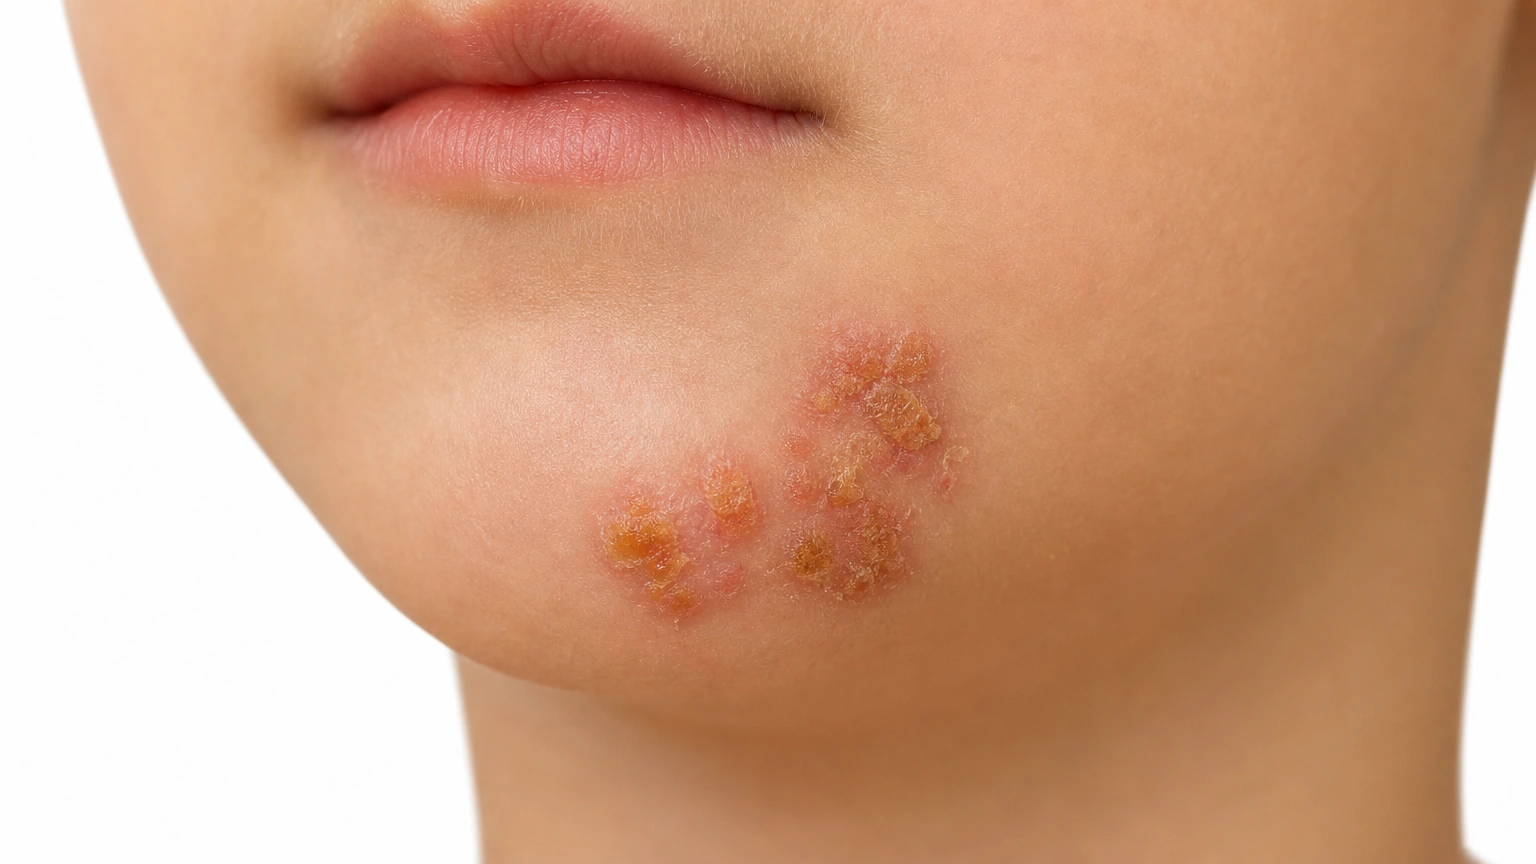
Non-bullous impetigo
Sores with honey-colored crusts; most common.
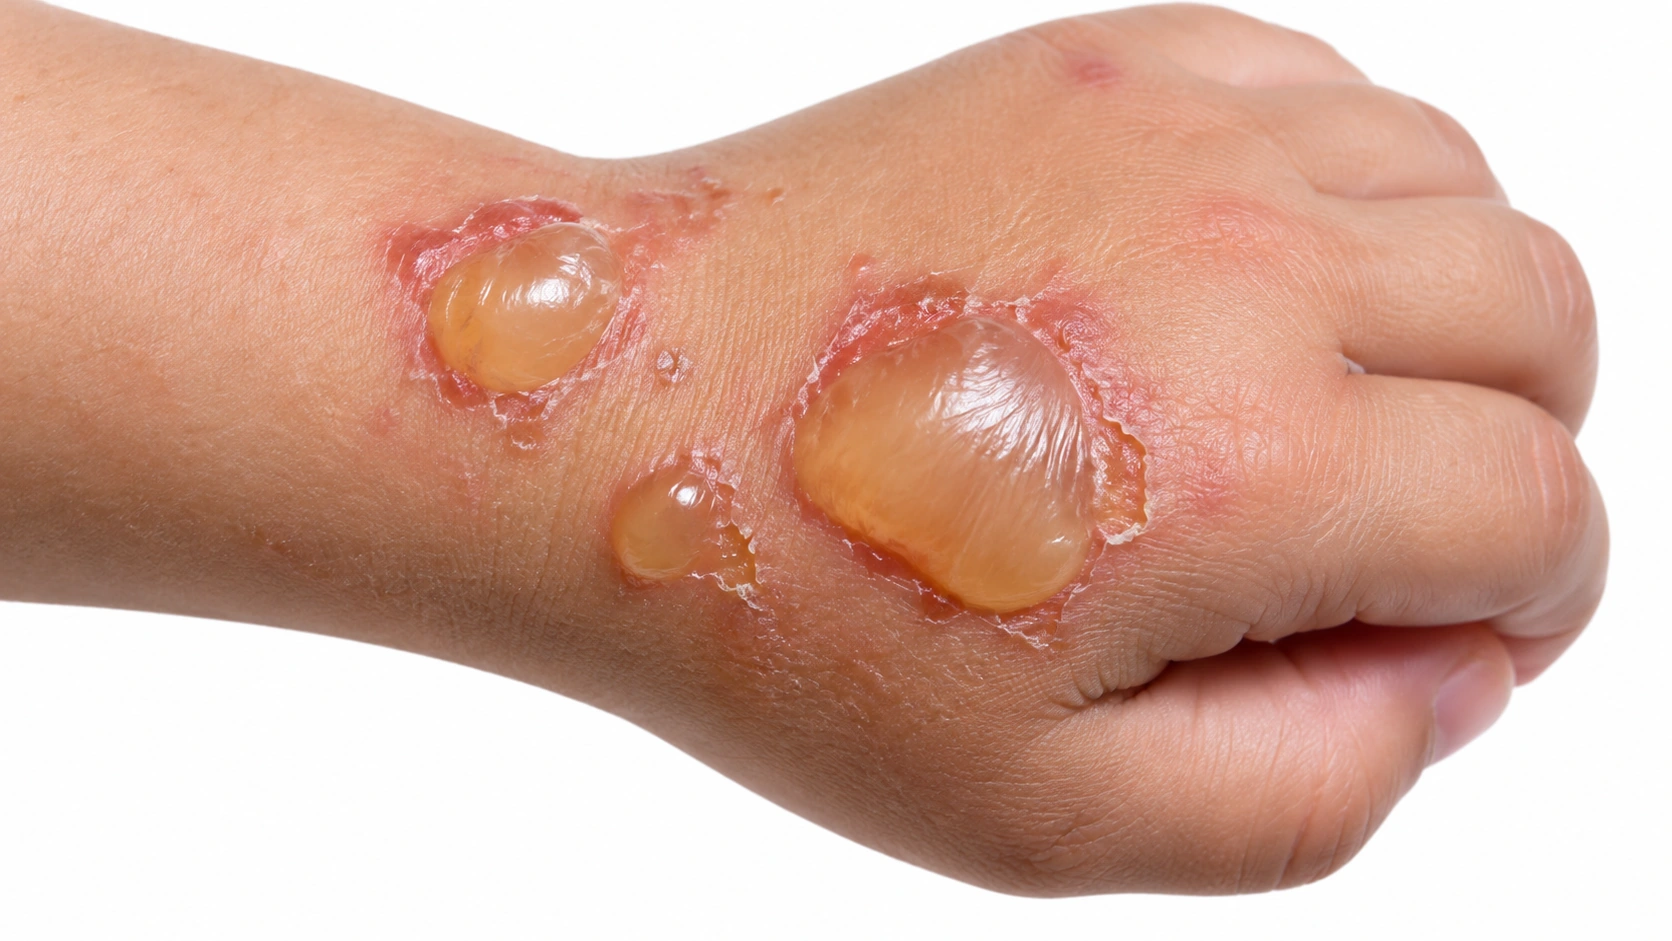
Bullous impetigo
Larger fluid-filled blisters.
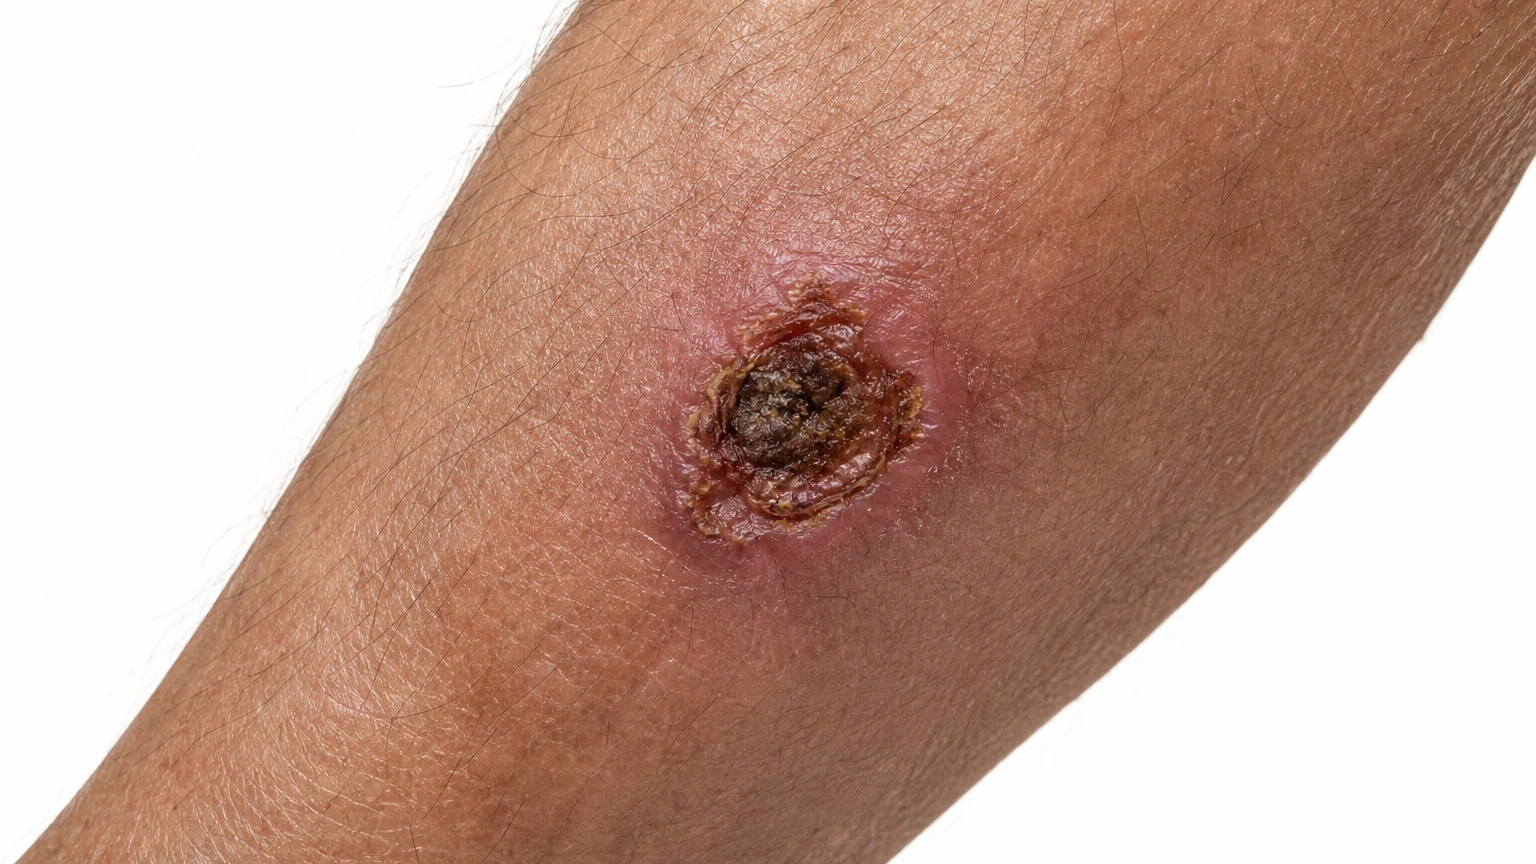
Ecthyma
Deeper, punched-out ulcers.
Where it shows up
The face, especially around the nose and mouth, is a common site. Exposed arms or legs can also be affected.
Face
Facial locations.
Arms
Locations along the forearms.
Lower legs
Locations on the lower legs.
On different skin tones
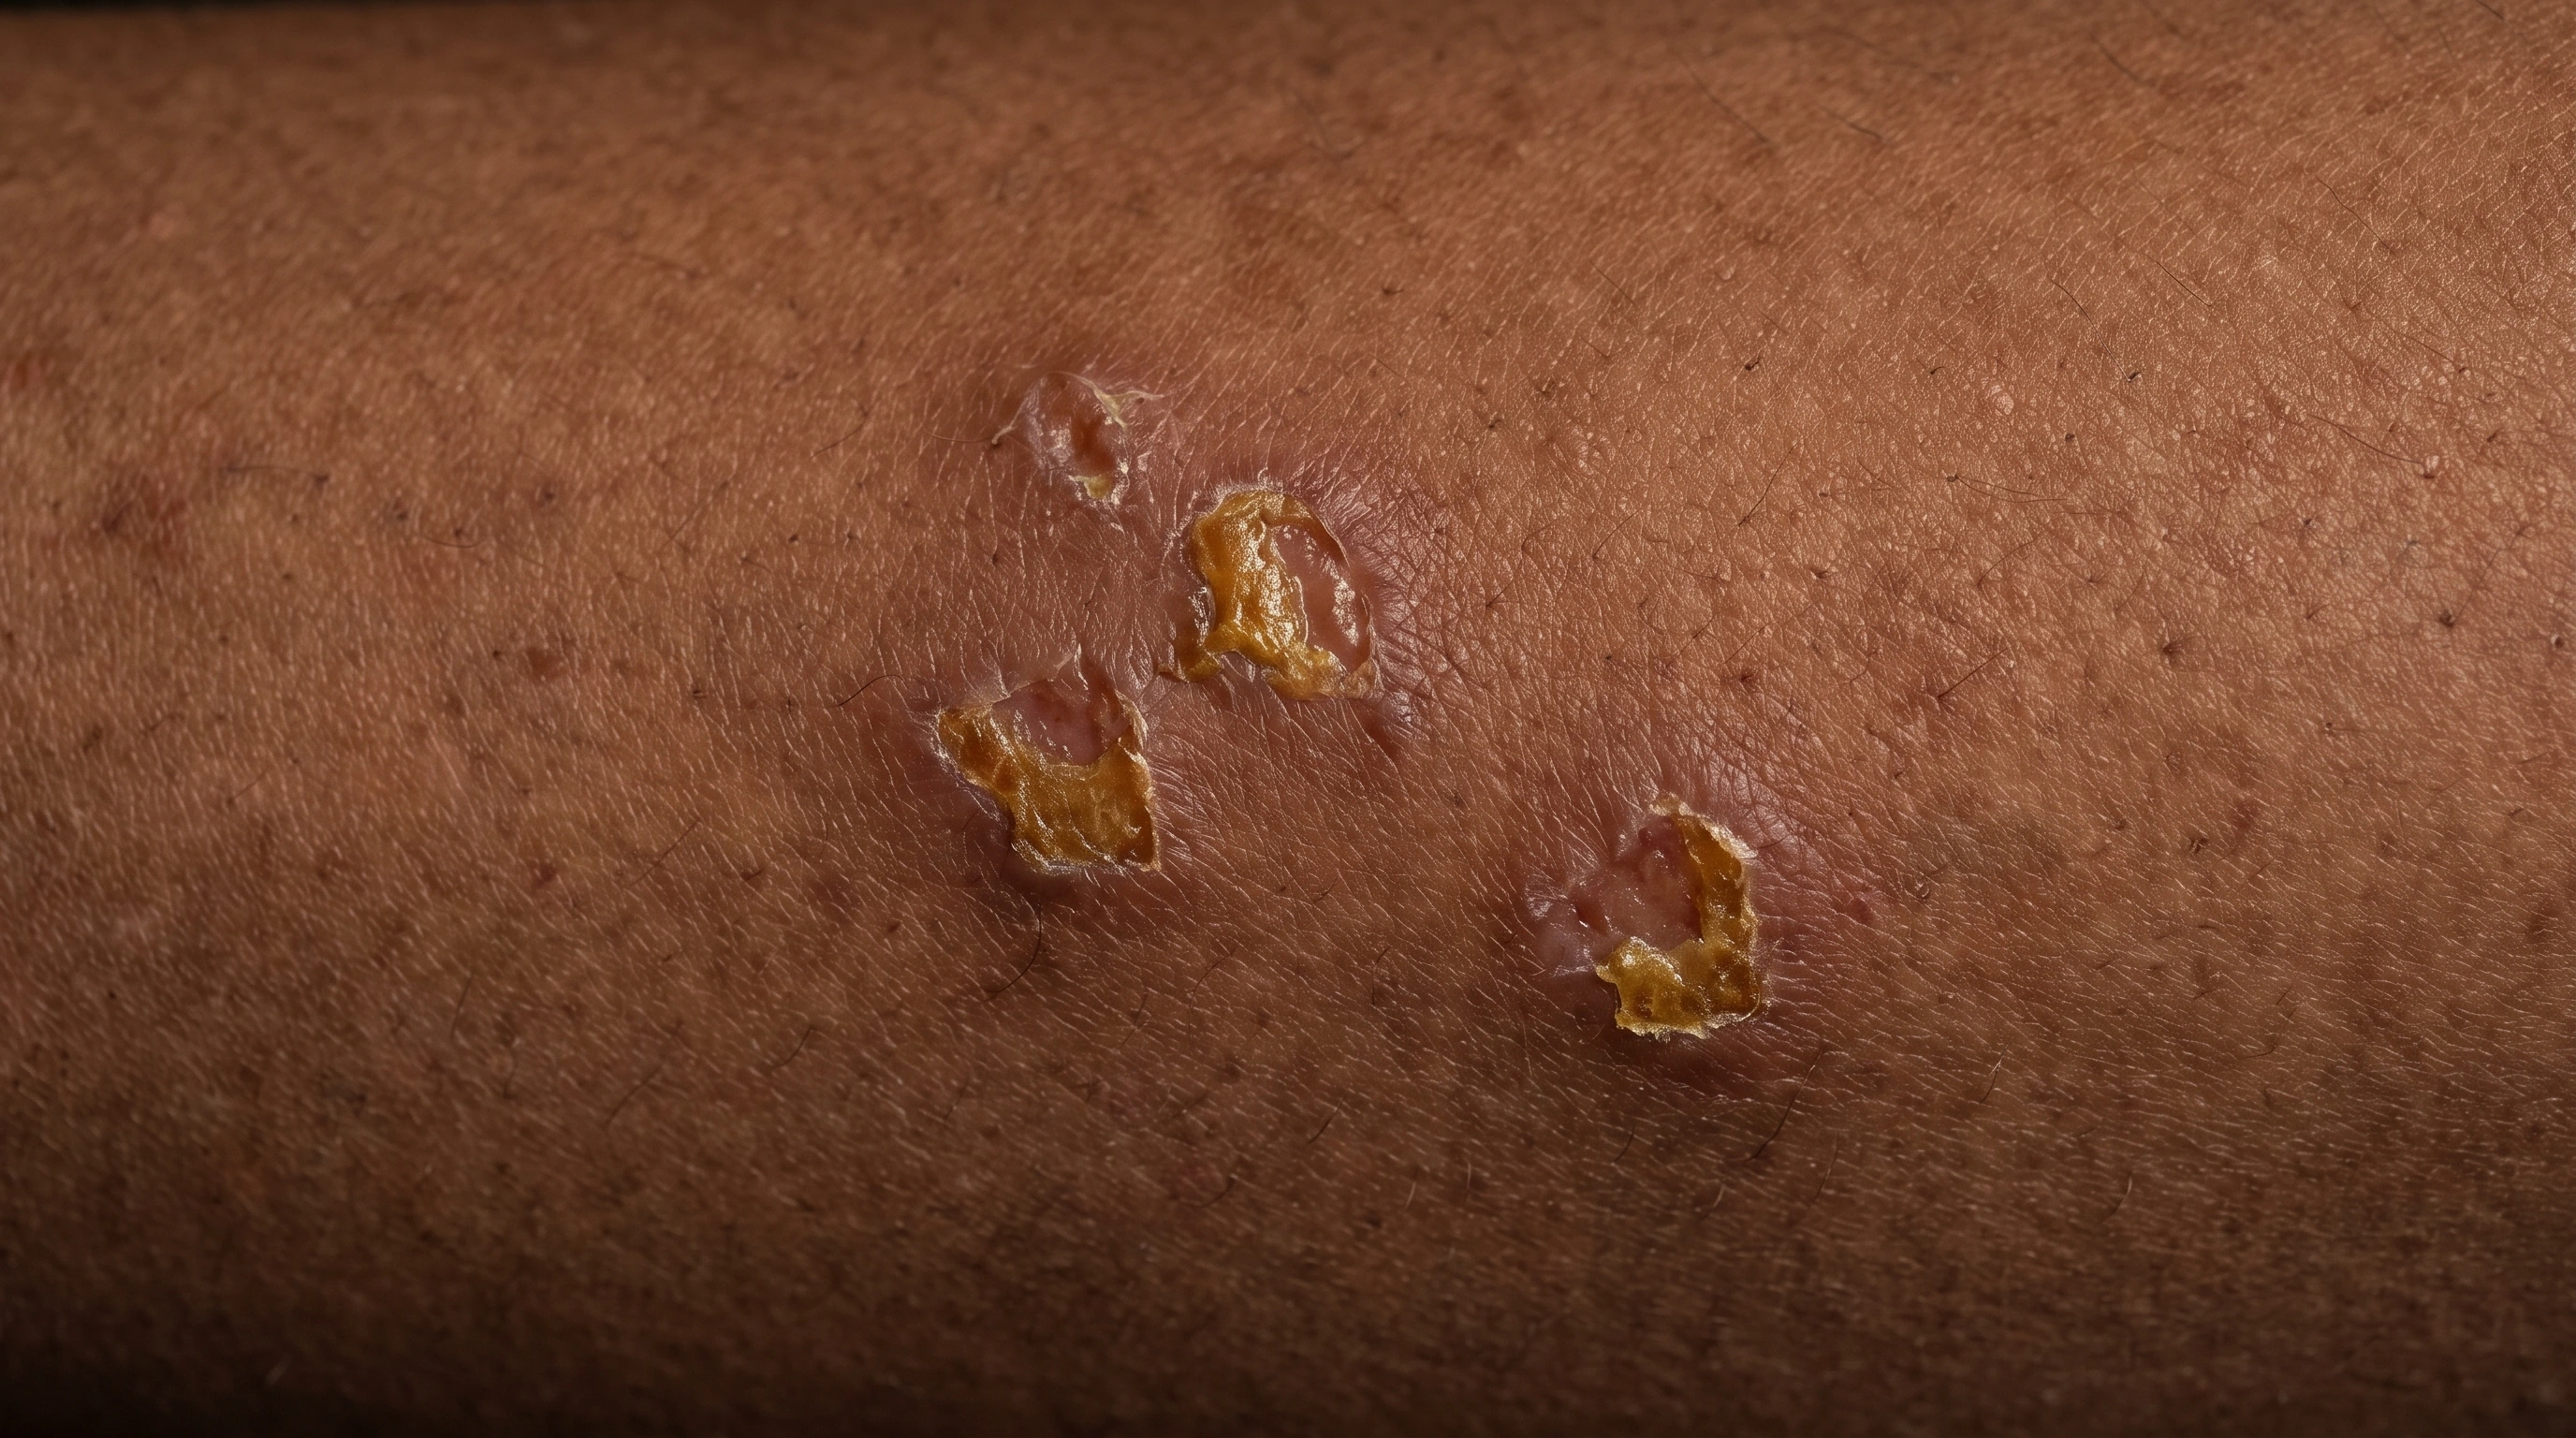
Impetigo on different skin tones
On lighter skin, impetigo sores look red with golden crusts. On brown and Black skin, the surrounding skin may look darker or purplish instead of red, while the honey-colored crusts look much the same. Healed spots can leave dark or light marks.
What happens in Impetigo?

Bacteria infect the superficial skin, often after a small break in the barrier. Shallow sores or blisters can release fluid that dries into a honey-colored crust.
- Dried fluid forms a crust: Honey-colored crust is a common clue.
- Bacteria reach damaged skin: Staph or strep can enter small breaks.
- A shallow blister or sore develops: The infection involves the skin surface.
Causes and triggers
What causes Impetigo
Causes
Why it happens
Impetigo is a skin infection caused by staph or strep bacteria entering through small breaks in the skin.
Risk factors
Raise the odds
- Children aged 2 to 5
- Eczema
- Hot, humid weather
- Contact sports
Triggers
Passes it on
- Touching sores (Well established)
- Scratching (Well established)
- Cuts, bites and scrapes (Strong link)
- Shared towels and clothing (Strong link)
When it usually starts
When it usually starts
Impetigo
Most common in young children, although any age can be affected.
Daily care
Daily care for Impetigo
Soaking off the crusts gently
The ointment reaches the sore.
Wash gently with soap and water
Twice a day, clean cloth.
Short fingernails and clean hands
Limits the spread.
Cover the sores loosely
A light non-stick dressing.
Own towel, flannel and bedding
One each, washed hot.
Keep away from school and sport
Until about 24 hours of treatment.
Treat the underlying skin problem
This prevents the next one.
Avoid: Scratching
Opens fresh breaks, carries bacteria on.
Avoid: Picking off the crusts
Reopens the sore, loads the fingers.
Avoid: Sharing towels, bedding and clothing
The main household route.
Avoid: Warm, humid conditions and heavy sweating
Soften the skin; bacteria establish easily.
Avoid: Leaving weeping sores uncovered
They load every surface.
Avoid: Untreated or undertreated eczema
Scratched skin is the entry point.
Avoid: Close contact before treatment starts
Nursery, school and sport spread it fast.
Avoid: Scabies, head lice or insect bites
Untreated, they keep breaking skin.
Avoid: Steroid cream on its own
A steroid cream calms redness and itch but does nothing to bacteria, so used alone on impetigo it lets the infection carry on. This matters most where impetigo has landed on a patch of eczema and the steroid is already in the house. In that situation both problems are treated, with the antibiotic doing the work on the infection.
Treatments
Treatments for Impetigo

Shop antiseptic creams
General antiseptic ointments from the shelf are not the same thing as a prescription antibiotic ointment and usually do not clear impetigo. The main cost of trying them is time: the infection keeps spreading and the child stays off school for longer than they needed to.
Mupirocin
The usual first choice for a small number of patches, applied three times a day for about five days after the crust has been softened off. For a few sores it works as well as tablets and avoids their side effects. It is also the ointment used inside the nostrils when impetigo keeps coming back and long-term carriage in the nose is the reason.
Fusidic acid
An equally effective alternative ointment for a few small patches, used three times a day for five to seven days. Which of the two you are given depends mostly on local resistance patterns and what your country prescribes first. Neither is enough on its own once the infection is widespread.
Ozenoxacin
Ozenoxacin cream. A newer antibiotic cream for the crusted form, used twice a day for five days. It is an option where resistance to the older ointments is a problem, and it works against some resistant staph. It is not widely stocked and is usually the more expensive choice.
Antibiotics
Flucloxacillin or cephalexin. The usual tablets or liquid when the infection is widespread, spreading fast, blistering, or the person feels unwell. A course runs about seven days, and the contagious period ends after roughly the first day of it. Finish the course even once the crusts have gone, because stopping early is one of the common reasons it comes straight back.
Clindamycin
Used when there is a penicillin allergy, or when a swab shows resistant staph. It works well against the bacteria that cause impetigo. It upsets the stomach more than the first-choice options and, uncommonly, can cause a serious bowel infection, so any diarrhoea during or shortly after a course is worth reporting.

Doxycycline
Reserved for adults and older children when a swab shows resistant staph, and not used in young children or in pregnancy — ask your doctor if either applies. It is a reasonable option for the age group that fits it, but for the usual patient with impetigo, a small child, it is not the drug.
Outlook
What to expect with Impetigo
Impetigo moves fast - it appears over days and, treated, clears in about a week. Untreated it usually resolves in around 2 to 3 weeks, but it spreads much further meanwhile, stays contagious throughout, and carries more risk of complications. Ecthyma, the deeper form, takes several weeks and does scar.
- 1
Days 1 to 3 · After the skin breaks
Small red, brown or violet spots appear, often around the nose and mouth or on a scratched bite. They itch slightly and get mistaken for a graze or cold sore.
- 2
Days 2 to 5 · Blistering
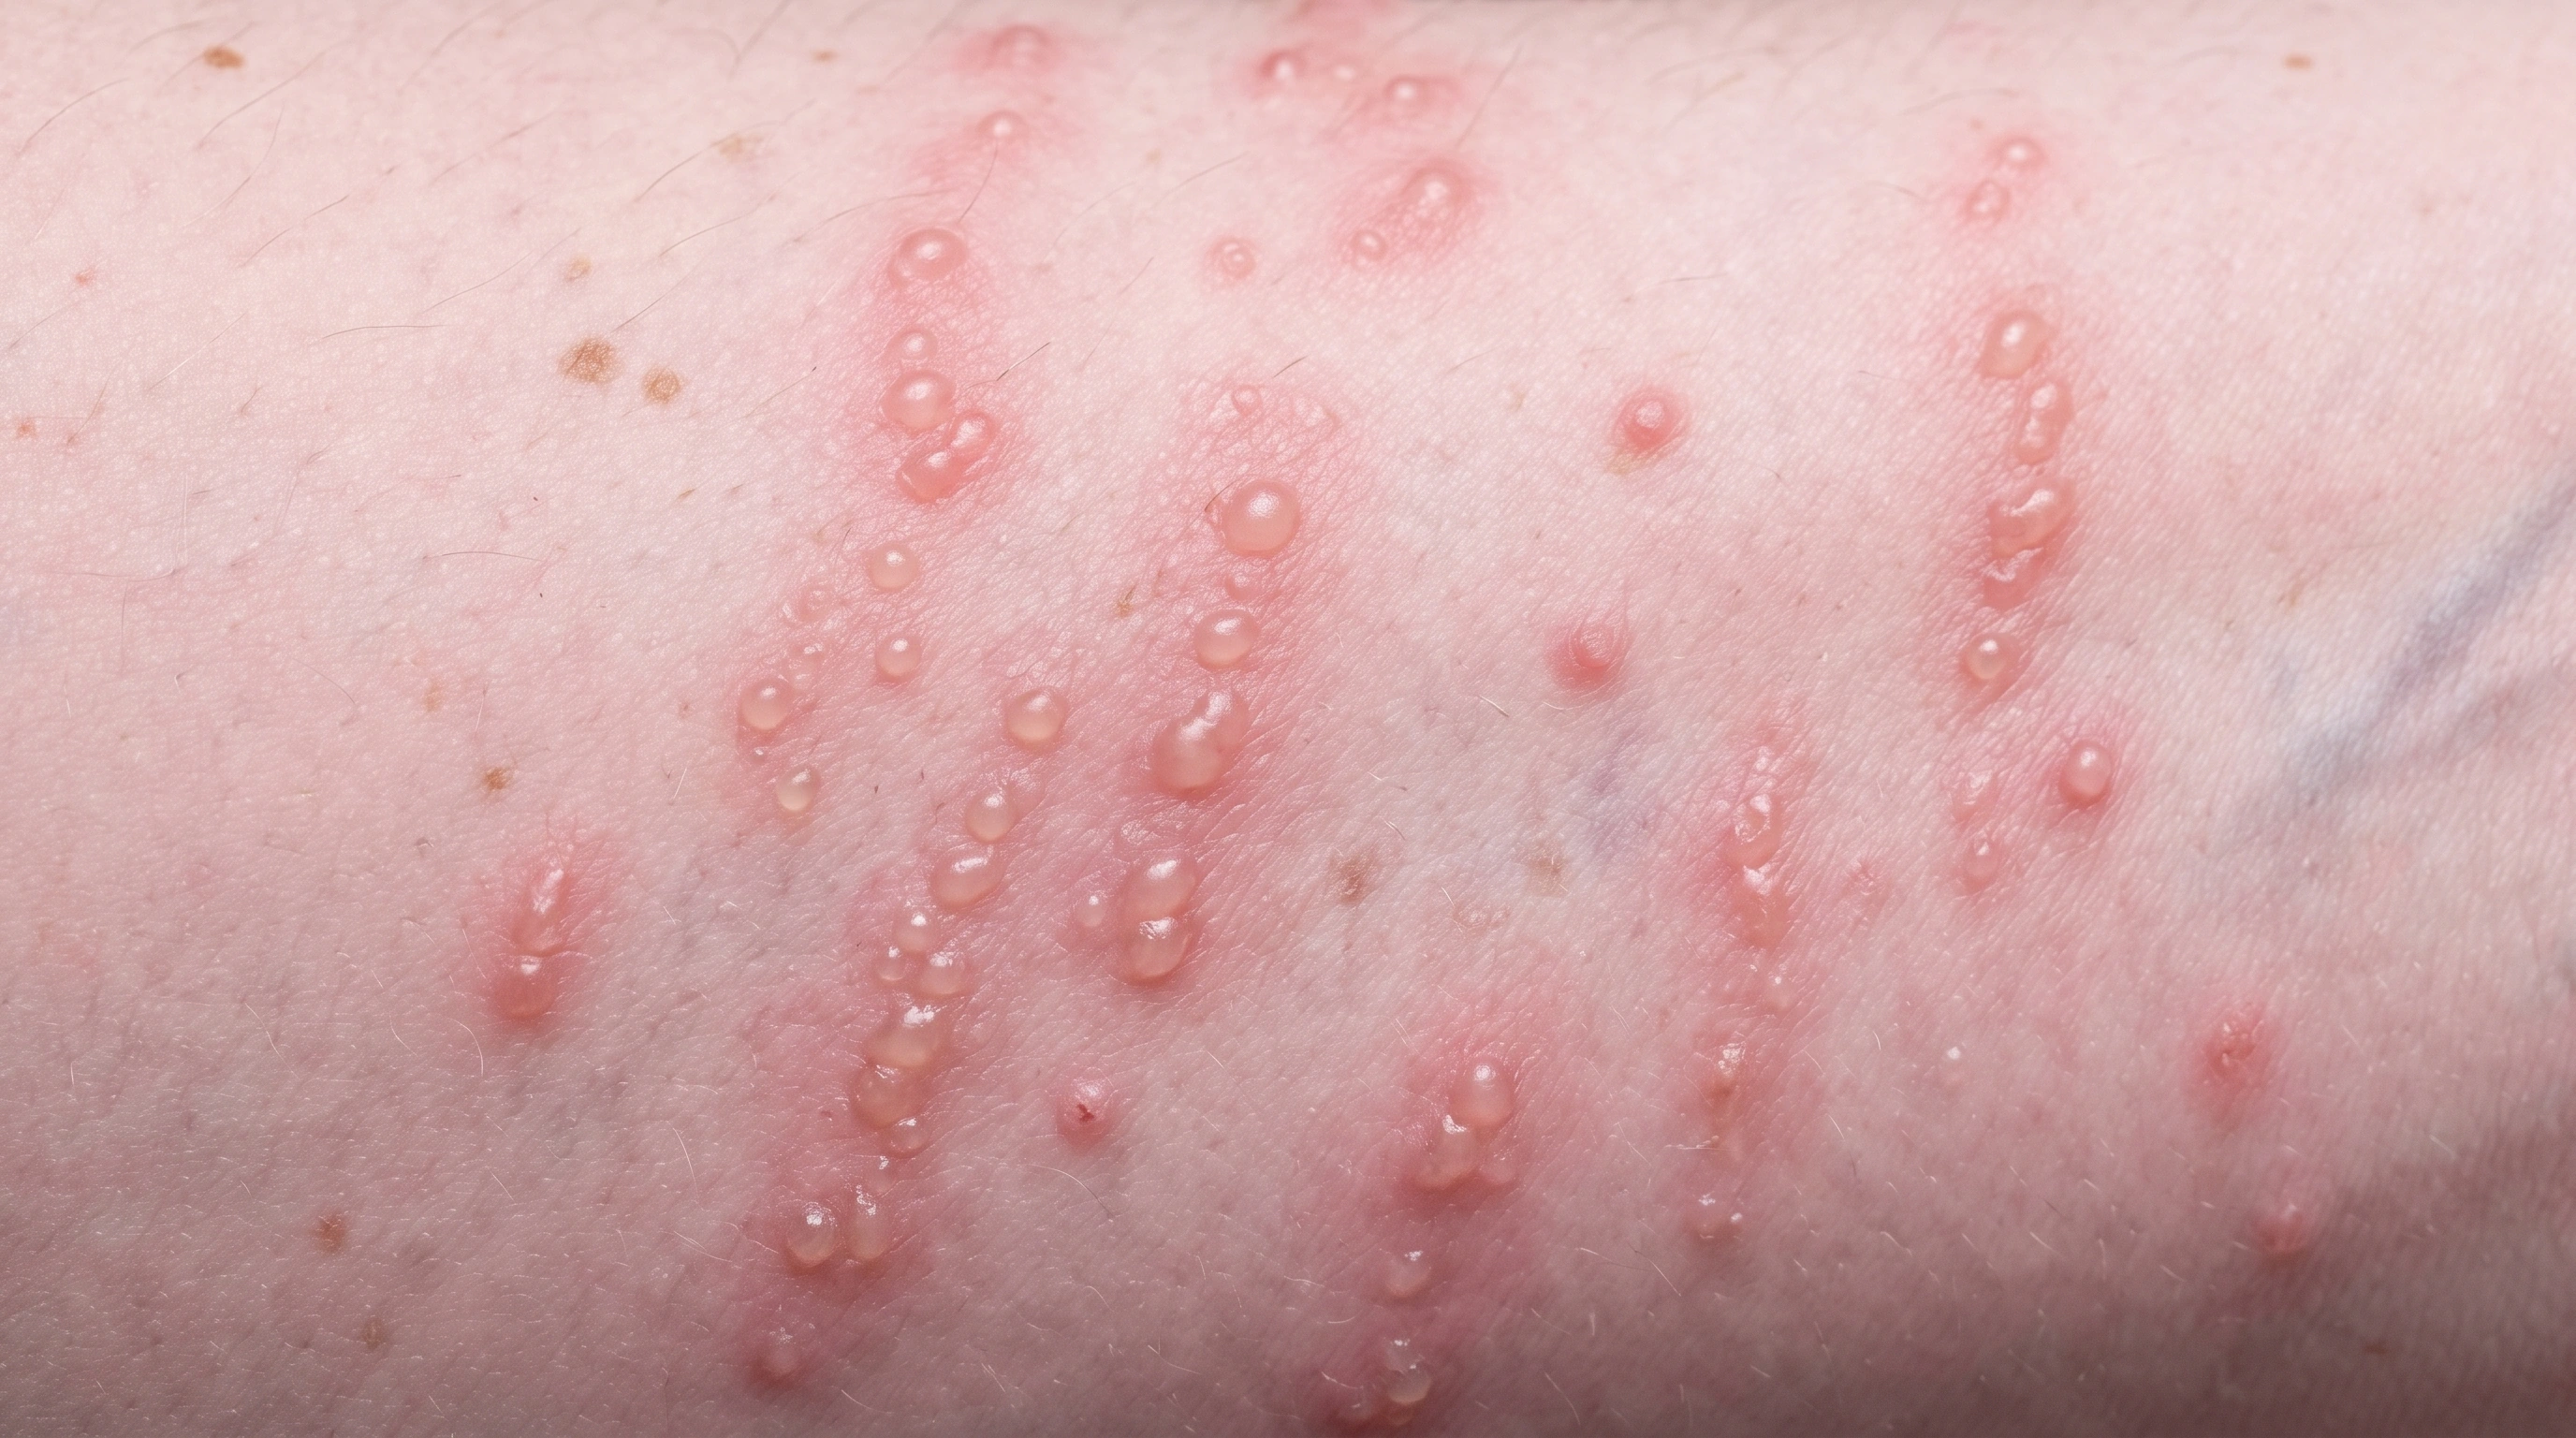
The spots become thin, fragile blisters that break as soon as they form. In bullous impetigo they are larger, floppier and last longer.
- 3
Days 3 to 7 · Crusting
The sores weep and dry into a thick, stuck-on golden crust. New patches appear nearby or wherever fingers carried it.
- 4
Within 24 to 48 hours of antibiotics · Turning
Spread stops, the weeping settles, and after about a day of treatment the person is no longer considered contagious. Most schools use that as the point of return.
- 5
Days 7 to 10 of treatment · Clearing
Crusts lift and the skin underneath is intact. Non-bullous impetigo almost never scars. A flat pink, brown or pale mark can stay for weeks to months, especially on deeper skin tones. Not infection.
Complications
Complications to know about
Cellulitis
Occasionally the bacteria get past the top layer and into the deeper tissue. The area around the sores becomes swollen, hot and increasingly painful, with redness or darkening spreading outward into normal skin, and the person often feels unwell with it. It is uncommon and it is treatable, but it needs antibiotic tablets rather than a cream, and it is a same-day problem rather than one to watch overnight.
Ecthyma — the deeper form
When the infection punches through into the layer below, it forms a punched-out ulcer under a thick, hard crust, most often on the lower legs. It is the one form of impetigo that heals slowly and does leave a scar. It is more likely where sores have been picked at, where treatment was delayed, and in people with diabetes or a weakened immune system. It needs antibiotic tablets, not an ointment.
Days off school and spread at home
Most settings ask for about 24 hours of antibiotic treatment before a child returns, with any remaining sores covered, so treating early is what gets them back soonest. The bigger cost is usually at home: without separate towels, bedding and hot washing, it works its way through the other children and sometimes the adults, and each new person starts the clock again.
When to get help
When to get help
When to seek care
Seek treatment for suspected impetigo. Spreading redness, fever, marked pain or a newborn with blisters needs prompt assessment.
Lookalikes
What else could it be?

Eczema
Eczema usually causes dry, itchy patches. Impetigo more often weeps, forms golden crusts, and spreads to new spots; it can also infect an eczema patch.
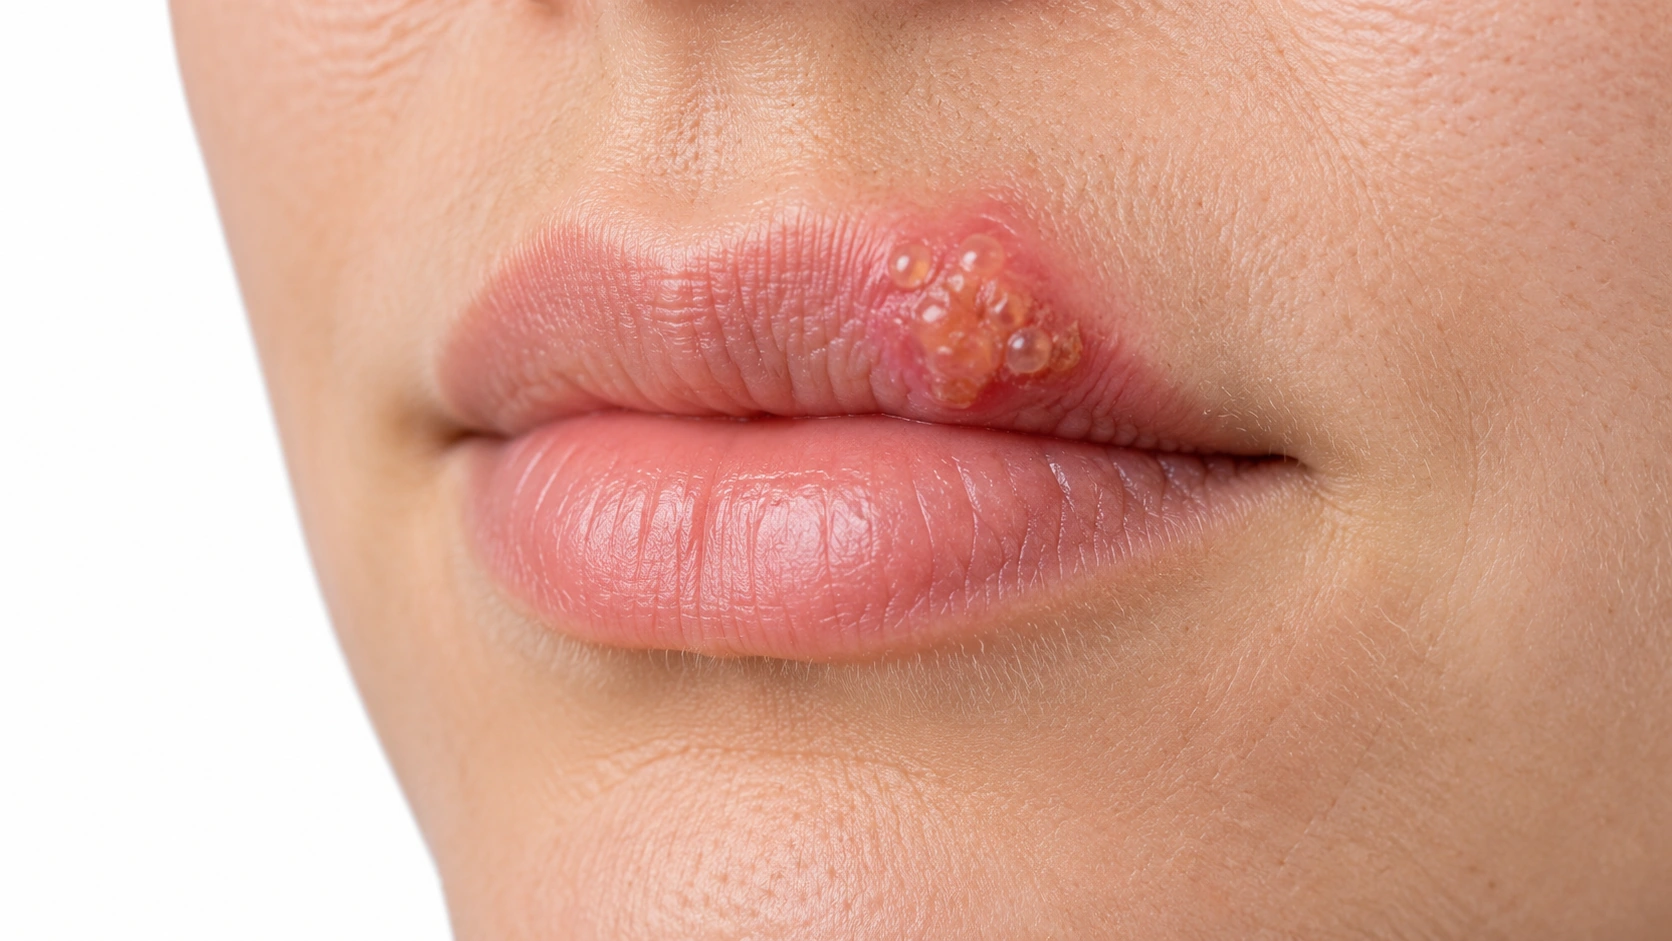
Cold Sores
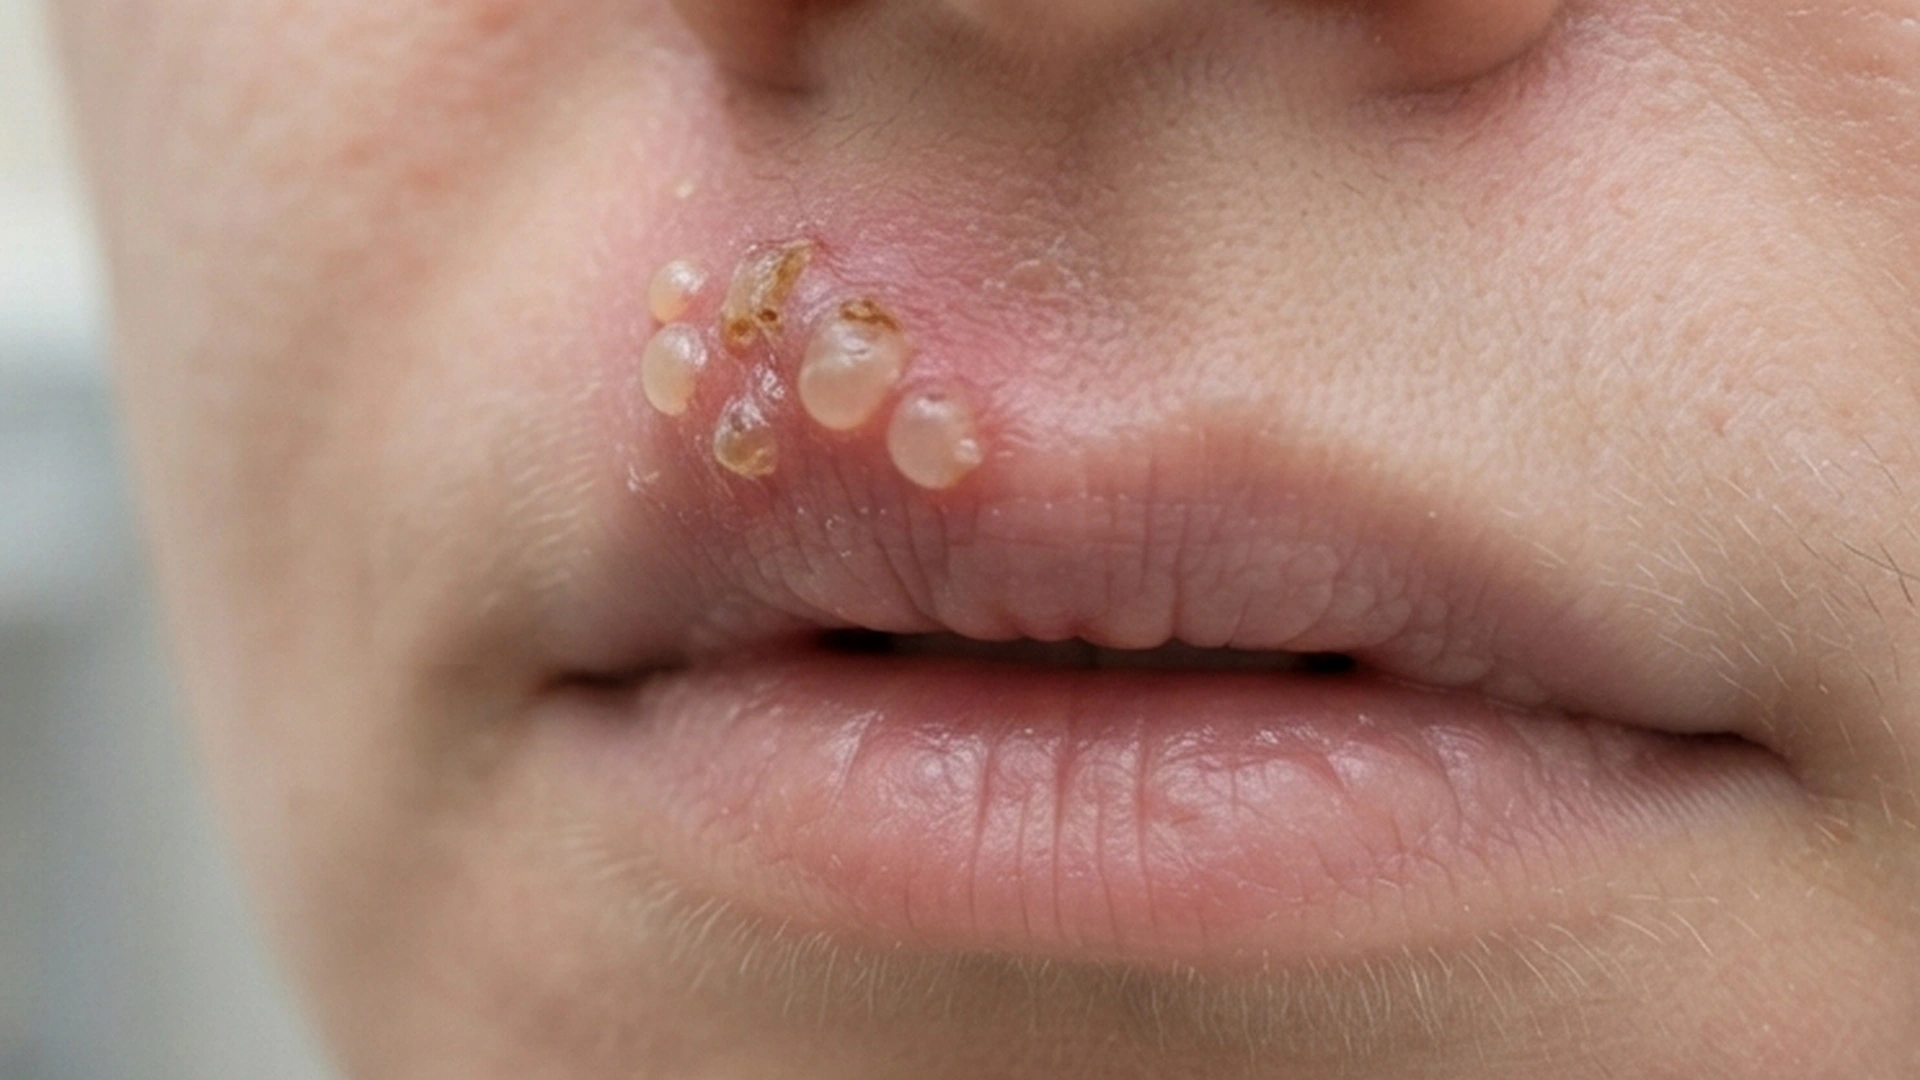
Cold sores usually stay in one small cluster and may tingle first. Impetigo forms thicker, honey-colored crusts and can spread to new areas.
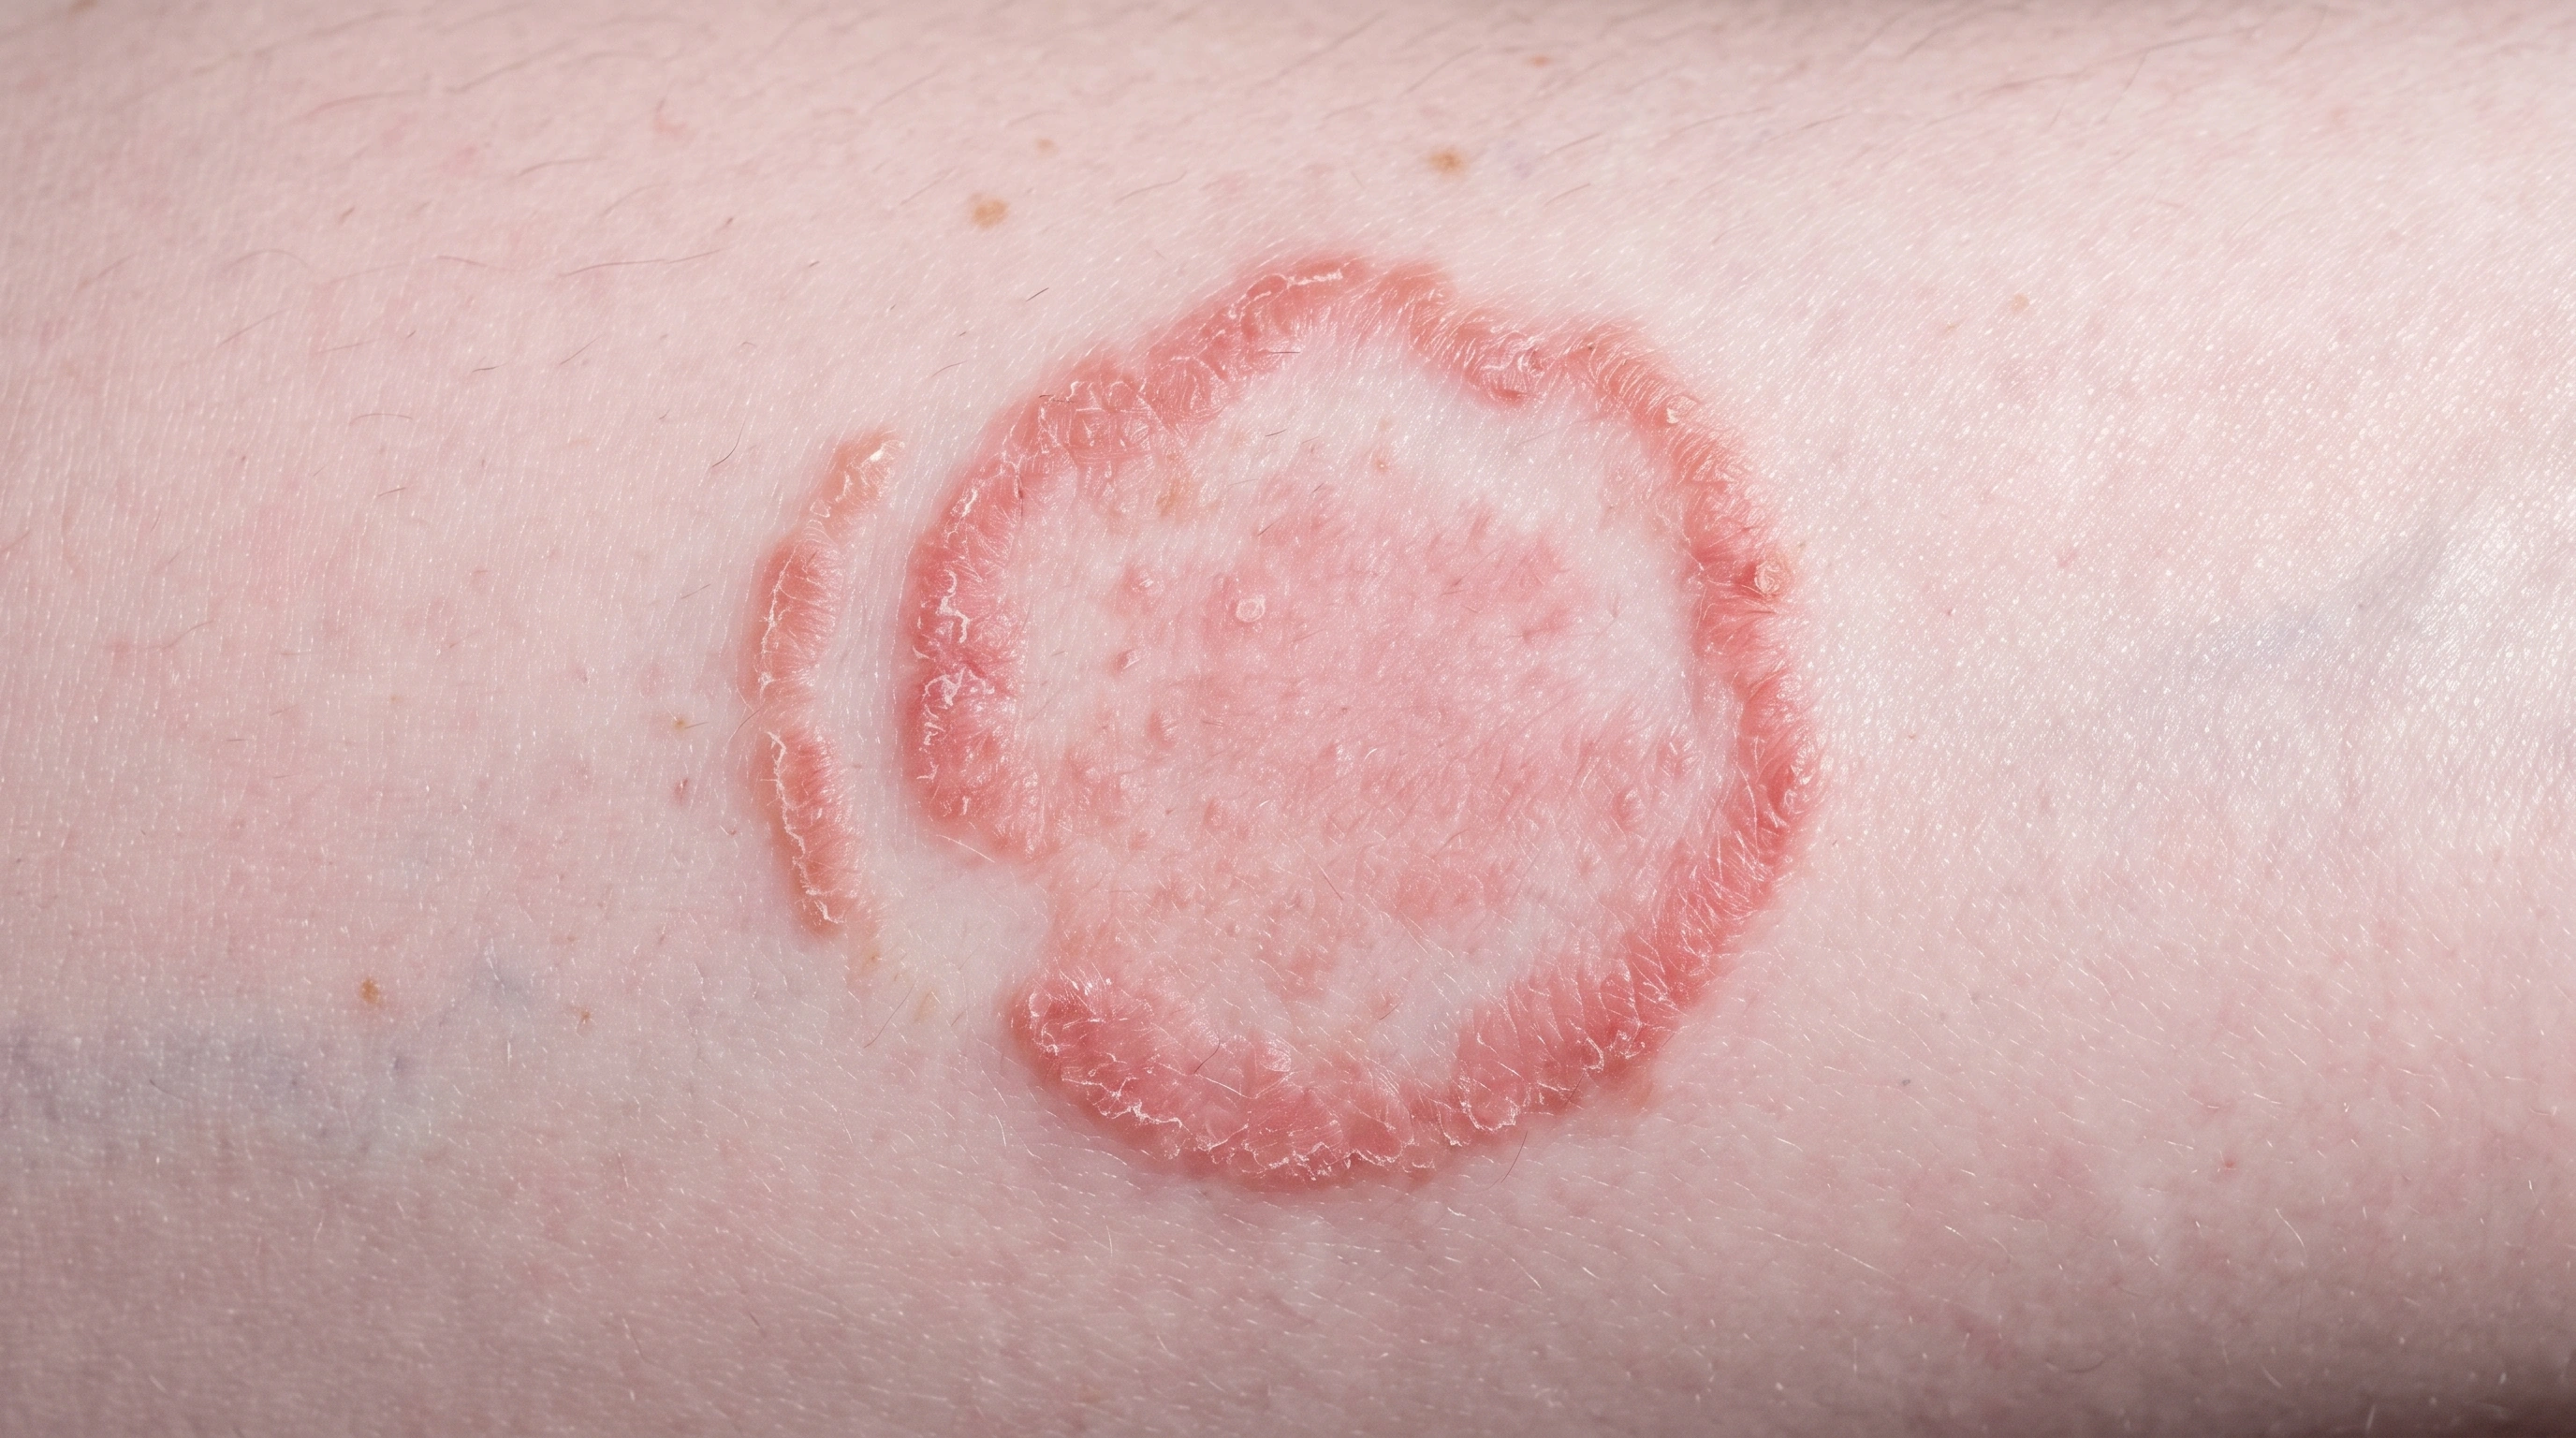
Ringworm
Ringworm usually grows outward as a ring with a scaly edge and clearer center. Impetigo forms moist sores with golden crusts and may spread more quickly.
Questions
Questions you might be asking.
How long is it contagious?
Until about 24 hours after antibiotics start, or until the sores have fully dried and crusted if untreated, which takes far longer. That is why treatment is offered even though it would clear on its own - it cuts the contagious period from a week or more to about a day.
When can my child go back to school or nursery?
Most settings ask for around 24 hours of antibiotic treatment first, with remaining sores covered. Rules vary between countries, schools and nurseries, so check the policy.
Will it leave a scar?
Ordinary impetigo almost never scars, because it sits in the top layer of skin. Flat pink, brown or pale marks fade over weeks to months, more slowly on deeper skin tones. Ecthyma, the deeper ulcerating form, does scar, and picking raises the risk in any form.
Why does my child keep getting it?
Usually eczema that is not fully controlled, which keeps supplying broken skin. Other reasons are scratching from bites or scabies, shared towels and bedding, or long-term Staphylococcus aureus in the nose. Look at those rather than repeat the antibiotic.
Can adults catch it from their child?
Yes, though it is much less common in adults with healthy skin. The risk rises with eczema, a cut, a graze or any other break. Separate towels, handwashing after applying the ointment, and hot washing of bedding reduce the chance.
Should I use a cream or tablets?
It depends how much skin is involved. A prescription ointment works as well as tablets for a few patches and avoids the side effects of oral antibiotics. Tablets or liquid are for widespread infection, rapid spread, large blisters, or an unwell child. Make that call with a doctor.
Sources
Sources and further reading
Related
Keep exploring.
Cold Sores
Mupirocin
Eczema
Ringworm
Doxycycline
Clindamycin
Impetigo vs Eczema
Cold Sores vs Impetigo
Impetigo vs Contact Dermatitis

Impetigo vs Folliculitis
Perioral Dermatitis vs Impetigo