Melanoma
Melanoma is a skin cancer that starts in the cells that make pigment. It is much less common than other skin cancers but causes most skin cancer deaths, because it can spread. Found and removed while it is still thin, it is usually curable.

Key facts
Melanoma at a glance.
Typical signs
New or changing pigmented spot
Common locations
Anywhere, including nails and soles
Expected course
Outlook depends on stage
Treatment options
Surgery; further care depends on stage
What is it?
Top things to know about Melanoma
- It is a pigment-cell cancer. Melanoma arises from melanocytes, the cells that produce pigment.
- It can look many ways. It may be dark, multicolored, pink or almost unpigmented.
- Early assessment matters. Invasive melanoma can spread beyond the skin.
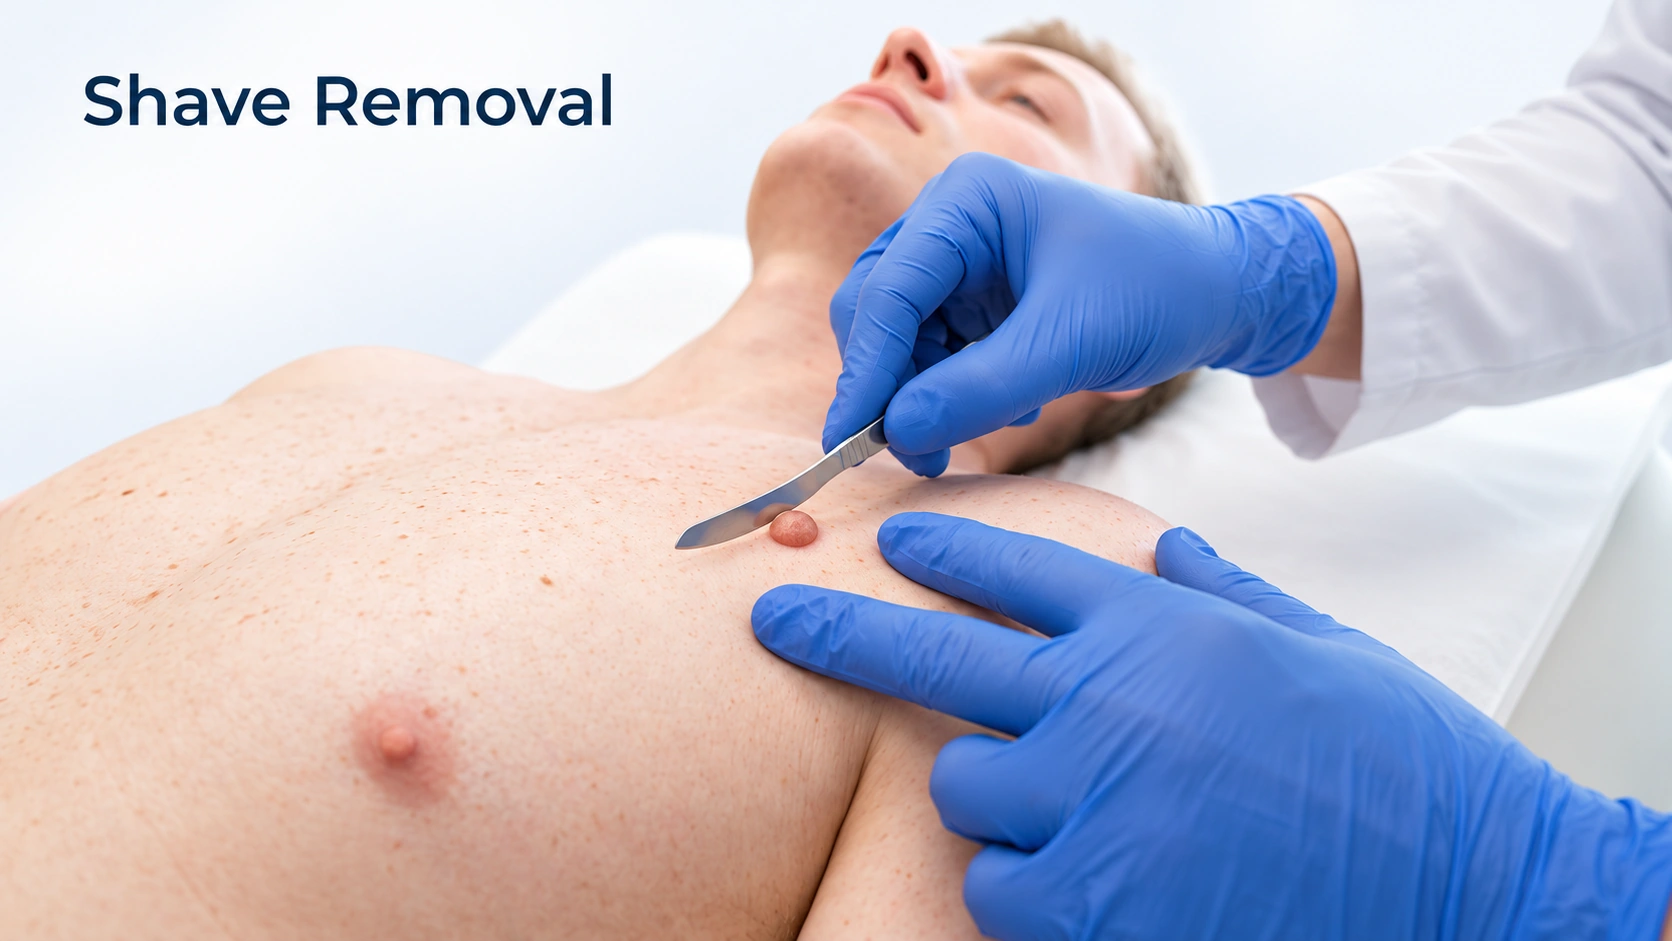
- Uncertain spots should not be removed at home. Biopsy, not cosmetic removal, is the right step.
What it looks like
What Melanoma looks like
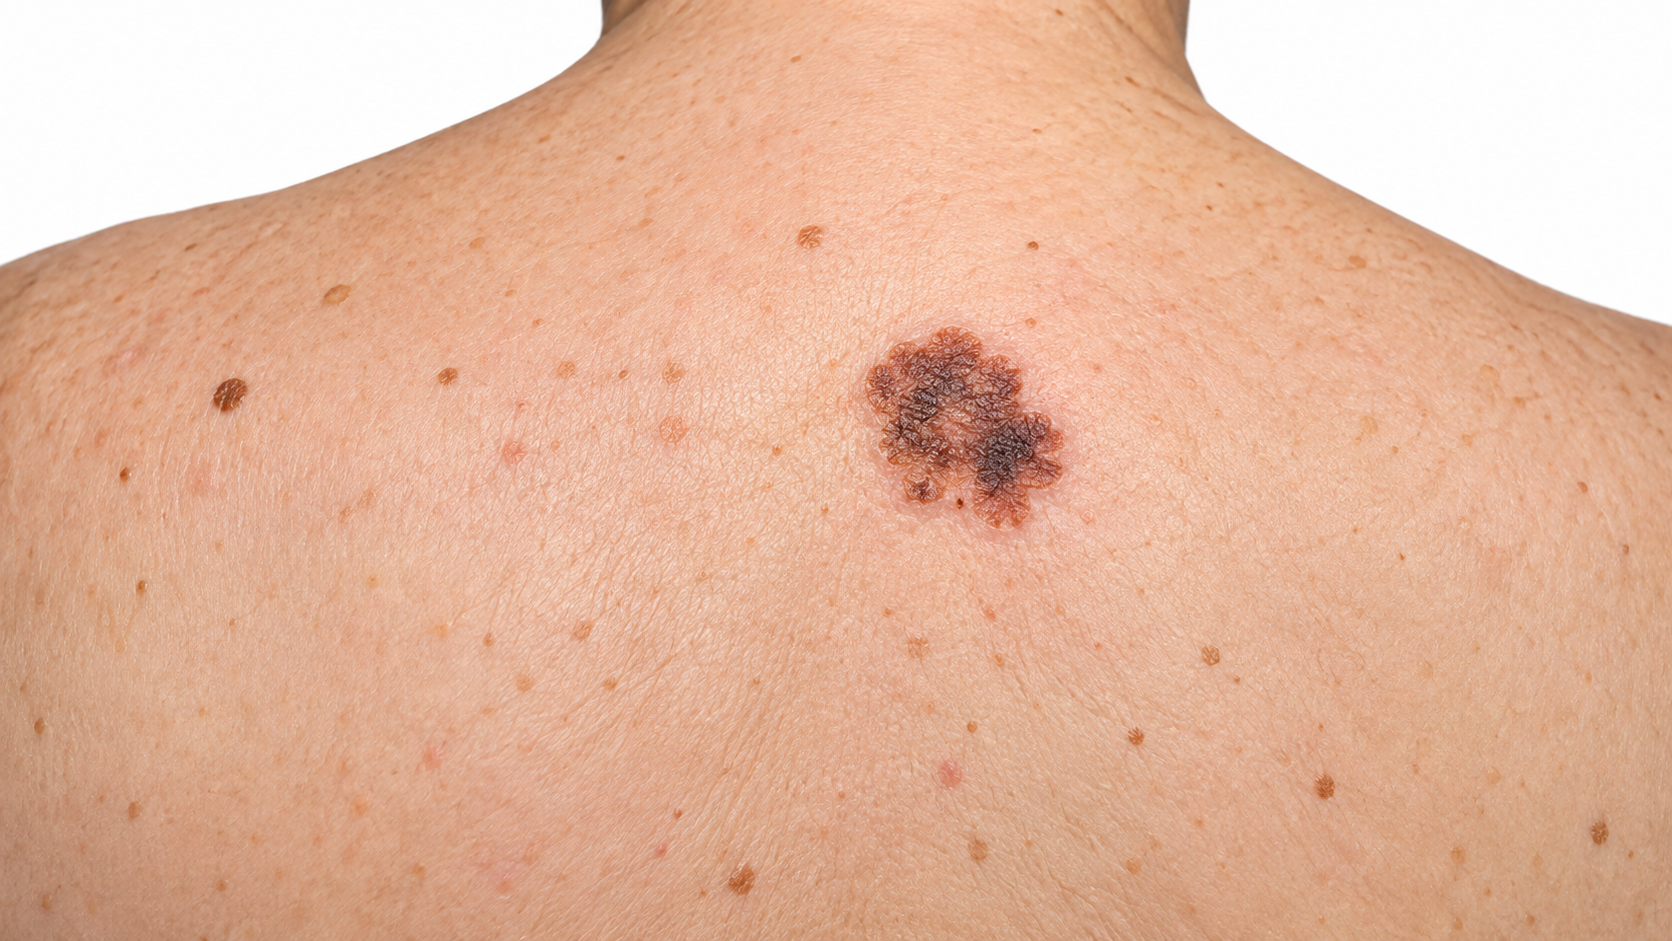
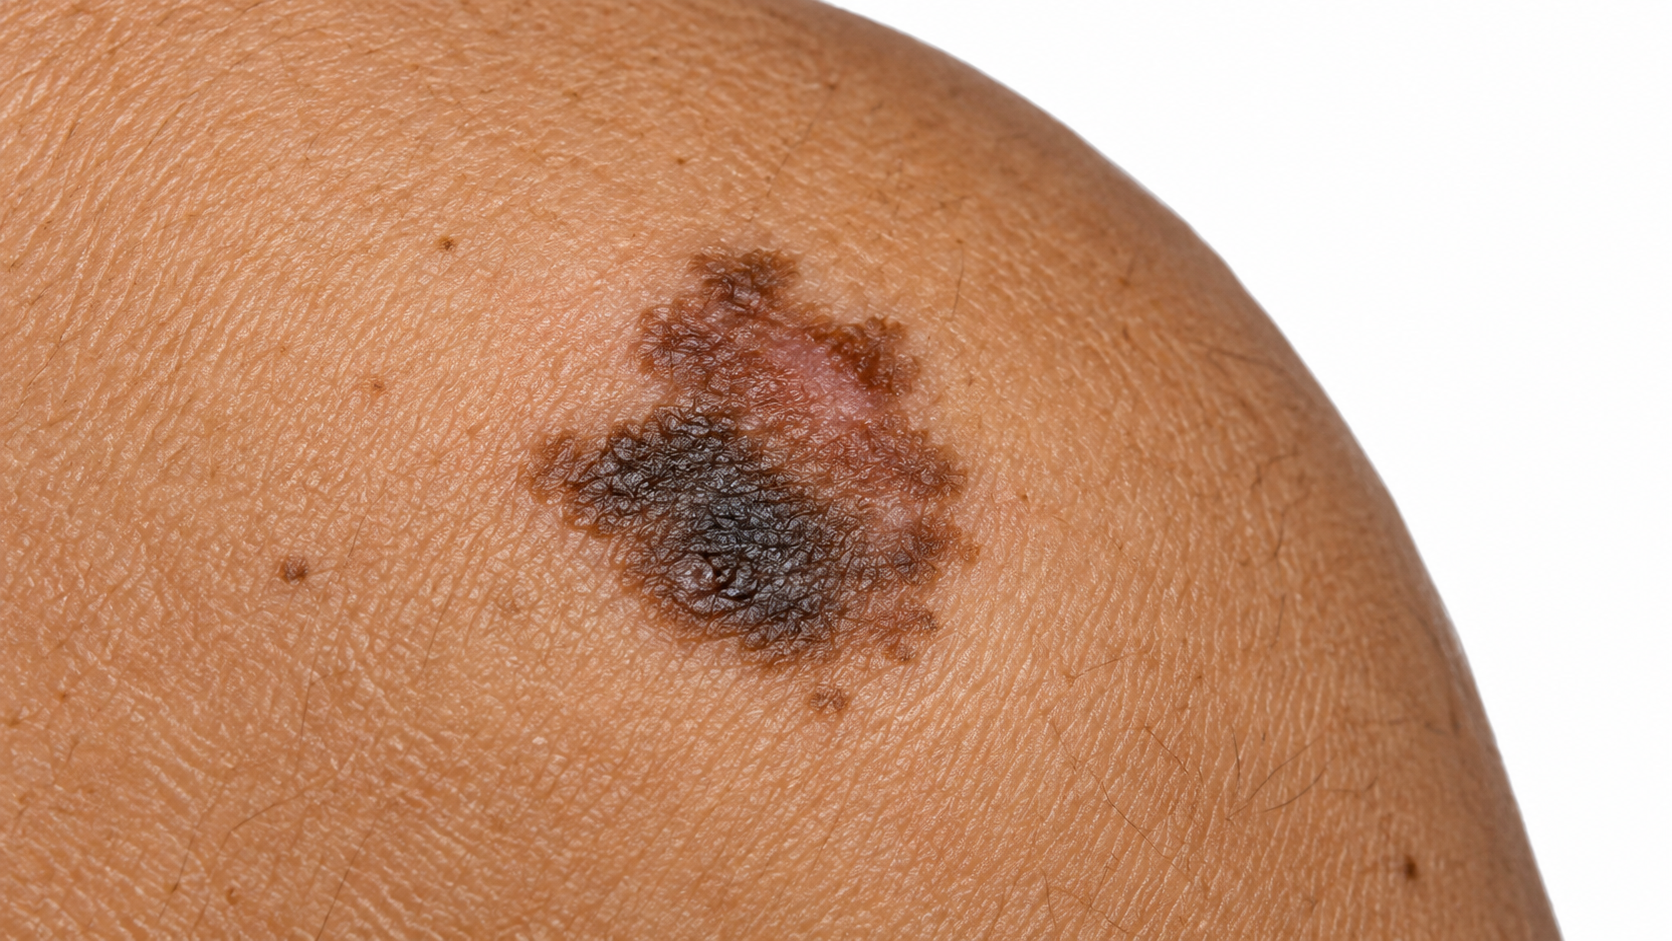
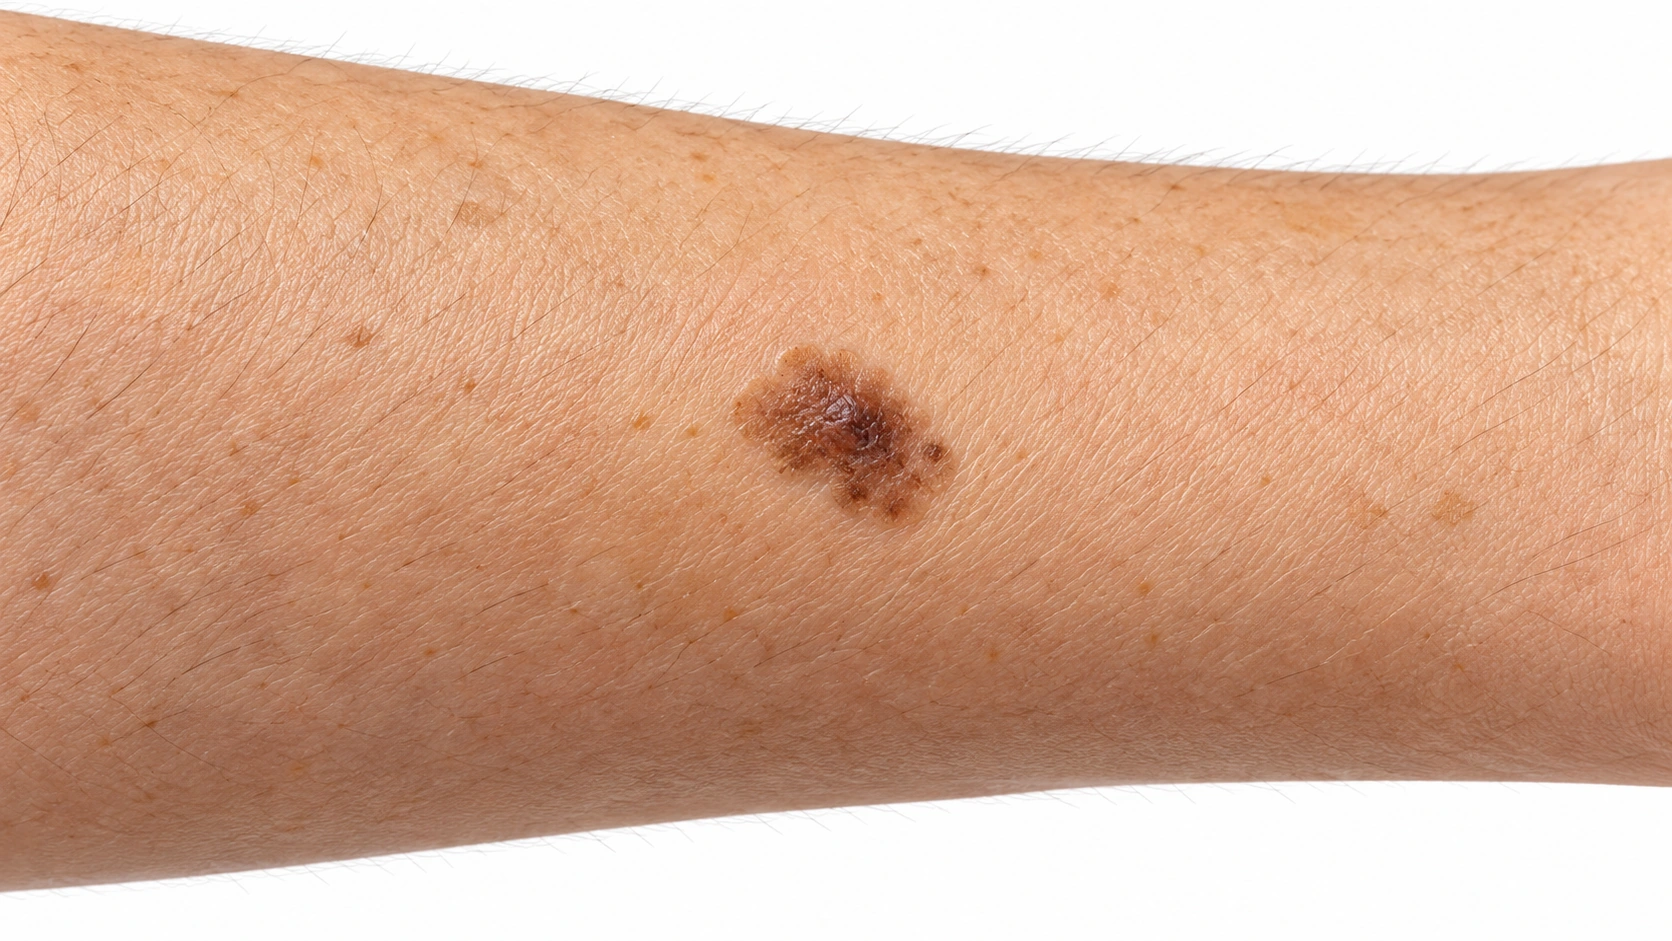
Melanoma is a skin cancer that most often looks like a new mole or a change in an existing one. Warning signs follow the ABCDE rule: asymmetry, irregular borders, more than one color, a diameter larger than a pencil eraser and evolution over time. A spot that looks different from your other moles, called the ugly duckling sign, is also a warning. Melanoma can appear anywhere, including places that get little sun.
Melanoma comes in several types that grow and look different. Some don't follow the classic ABCDE pattern.
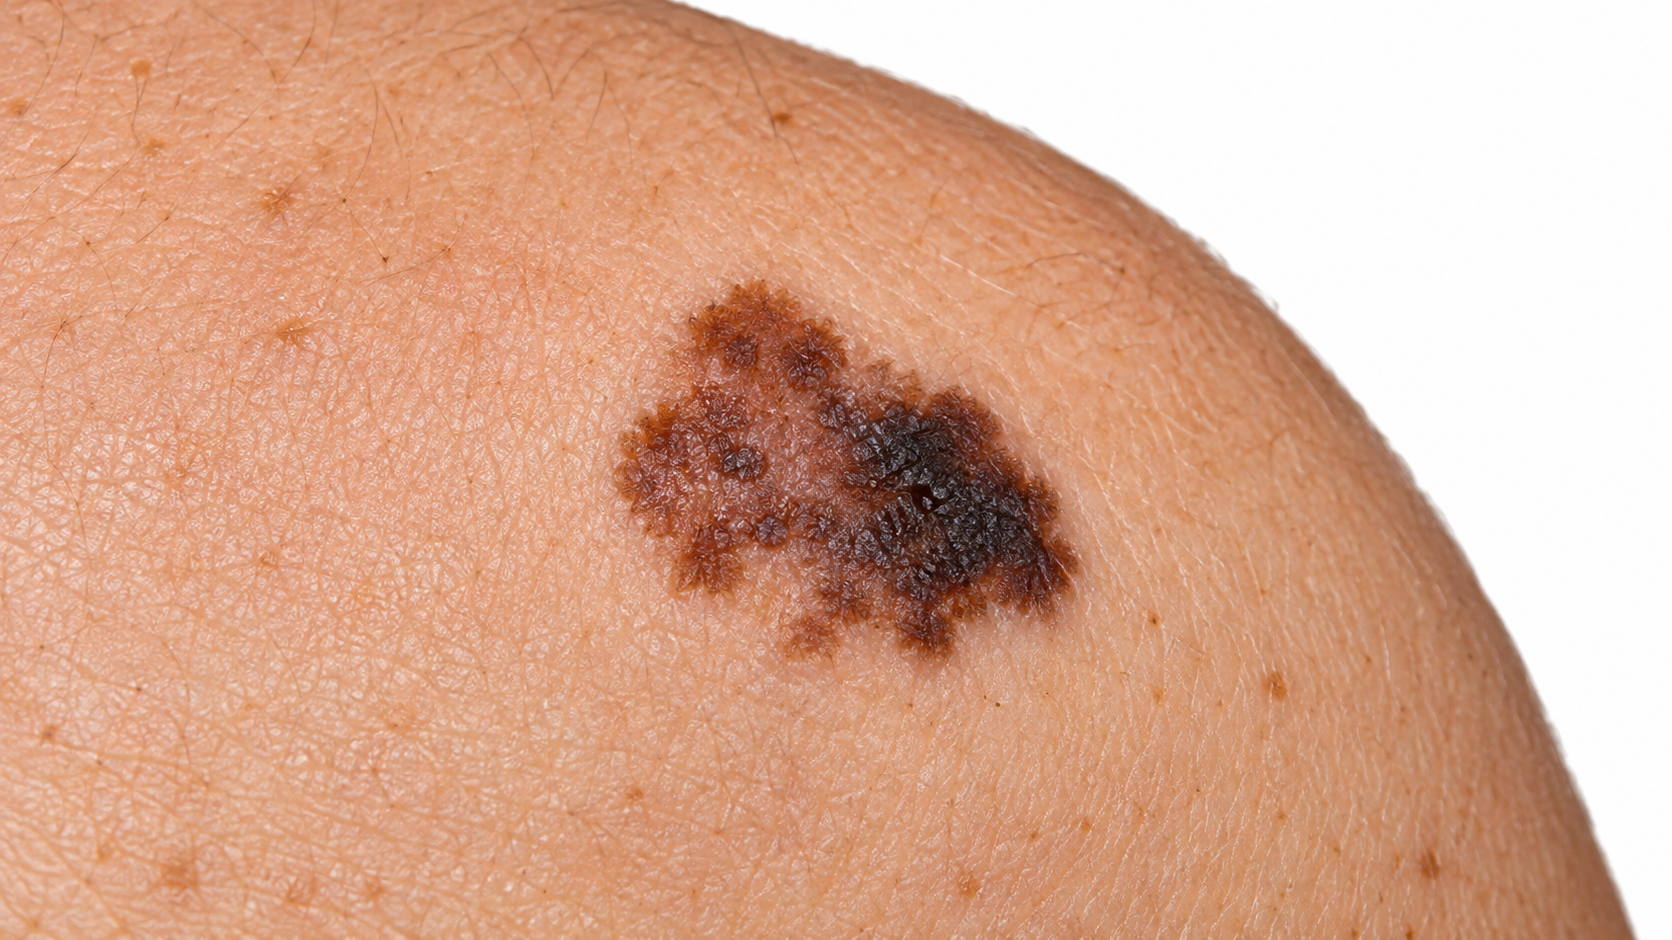
Superficial spreading melanoma
The most common, a growing flat spot.

Nodular melanoma
A fast-growing raised bump.
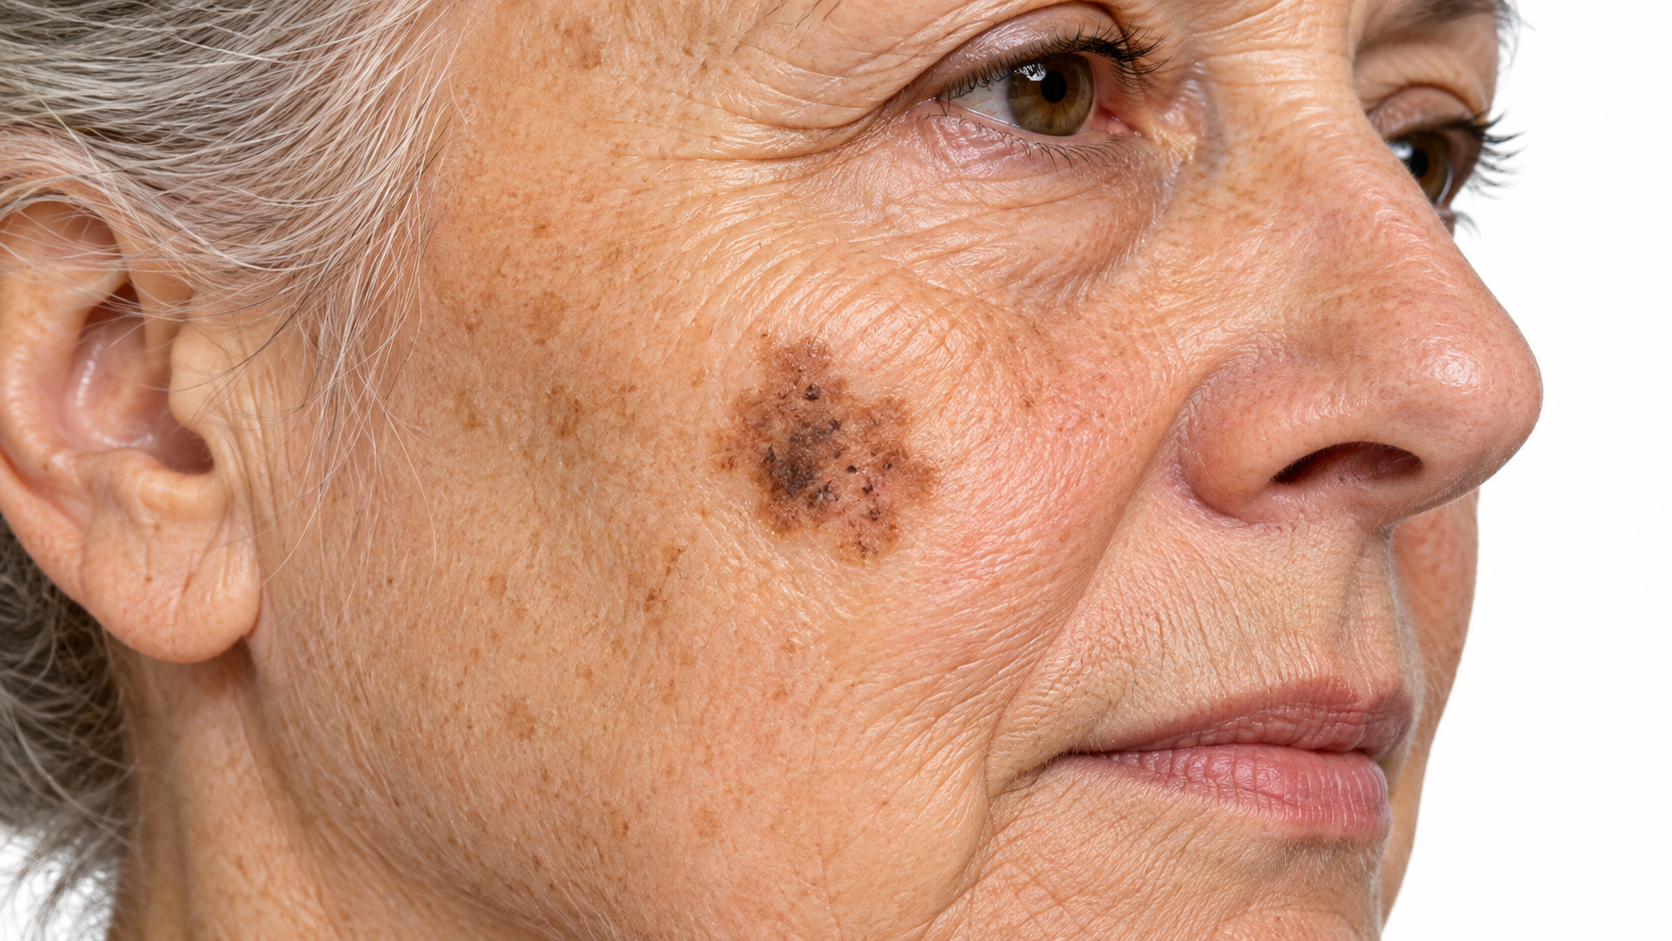
Lentigo maligna melanoma
Slow, flat brown patch on sun-damaged skin.
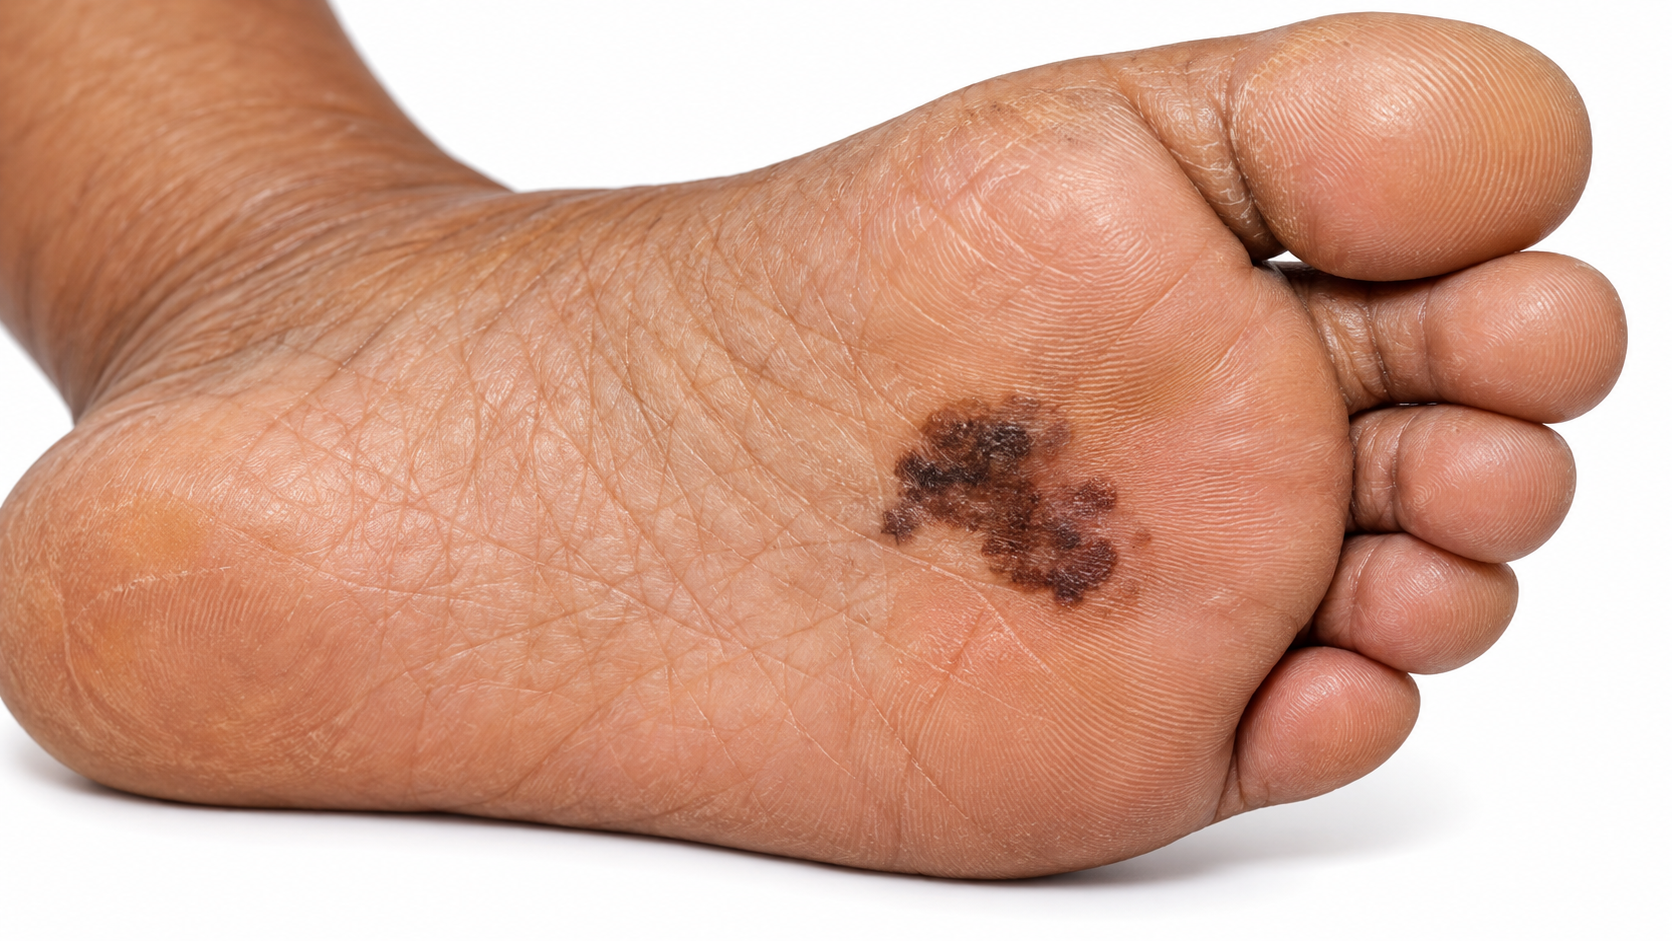
Acral lentiginous melanoma
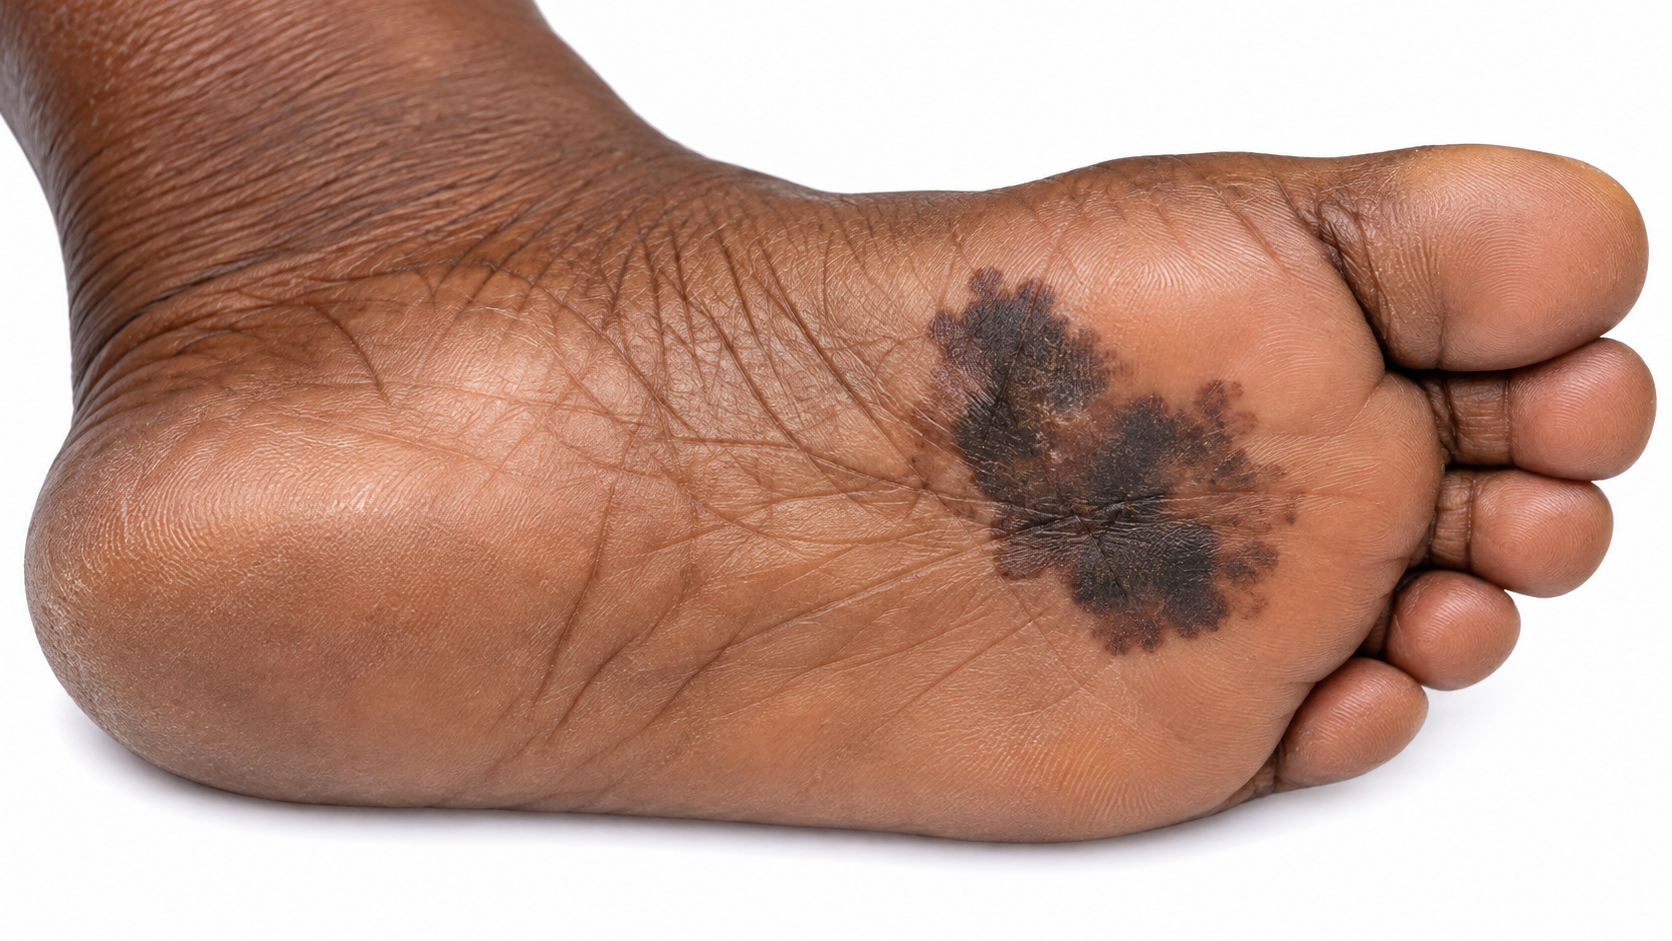
On palms, soles or under nails.
Where it shows up
Location varies
Melanoma can arise anywhere, including less sun-exposed skin, palms, soles and nail areas. No fixed distribution is shaded.
On different skin tones
Melanoma on different skin tones
Melanoma is less common in brown and Black skin, but it is more often diagnosed late. In darker skin, it most often appears on the palms, soles and under the nails, as acral lentiginous melanoma, rather than on sun-exposed skin. A new dark streak in a nail, or a growing dark spot on the sole, should always be checked.
What happens in Melanoma?

Abnormal pigment cells escape normal growth controls and multiply within the skin. Some melanomas grow into deeper tissue, and the depth of invasion helps determine their stage.
- Cells multiply unevenly: The patch can become irregular.
- Pigment cells acquire DNA changes: Abnormal melanocytes escape normal growth control.
- Some tumors invade more deeply: Depth helps guide staging and treatment.
Causes and triggers
What causes Melanoma
Causes
Why it happens
Melanoma starts when pigment cells develop DNA damage and grow out of control. Ultraviolet light is the main cause of that damage for most melanomas.
About 1 in 10 people with melanoma have a family history of it. Genes such as CDKN2A raise the risk.
Risk factors
Raise the odds
- Fair skin and red or blond hair
- Many moles
- Past blistering sunburns
- Weakened immunity
- Family history
Triggers
Bring it on or make it worse
- Sunburns (Well established)
- Tanning beds (Well established)
- Intense, on-and-off sun (Strong link)
When it usually starts
When it usually starts
Melanoma
More common in adults, but a concerning changing lesion needs assessment at any age.
Daily care
Daily care for Melanoma
Learning the ABCDE signs
Asymmetry, Border, Color, Diameter, Evolving above all.
The ugly duckling rule
The mole that does not belong is worth examining.
Knowing ABCDE is not complete
Firm, growing and new counts on its own.
Checking the places nobody checks
Scalp, ears, soles, between the toes, nails, genitals and mouth.
Photographing your own skin
Same distance and light, every few months.
Daily sun protection, no tanning beds
Cuts future risk, and you control it.
Review immune-suppressing medicines with the prescriber; do not stop them yourself
Immune suppression can change skin-cancer risk and follow-up needs. Do not stop a prescribed medicine without the specialist’s plan.
Avoid: Tanning beds
A recognized cause, riskier the younger you start.
Avoid: Blistering sunburns in childhood
Linked more strongly than steady daily exposure.
Avoid: Only checking sun-exposed areas
The scalp, soles, nails and mouth are found late.
Avoid: Assuming a pink bump is harmless
Melanoma without pigment is a recognized variant.
Avoid: A fast-growing bump ignored
Nodular melanoma grows downward from the start.
Avoid: Wearing sunscreen only on holiday
Risk builds over a lifetime of ordinary days.
Avoid: Waiting out a changing spot
A melanoma watched for six months is thicker.
Avoid: Treating a spot at home
Freezing kits and black salve destroy the evidence.
Avoid: Skipping follow-up
A second melanoma is meaningfully more likely.
Avoid: Not telling close relatives
It changes their screening advice.
Avoid: Cryotherapy or cosmetic laser
Freezing or lasering a pigmented spot off destroys it without anyone ever finding out what it was. If it was a melanoma, the thickness can no longer be measured and no one can check the edges. A spot that concerns you is examined and sampled, not erased for convenience, and this is one of the few places where the cheaper, quicker option costs something real.
Treatments
Treatments for Melanoma
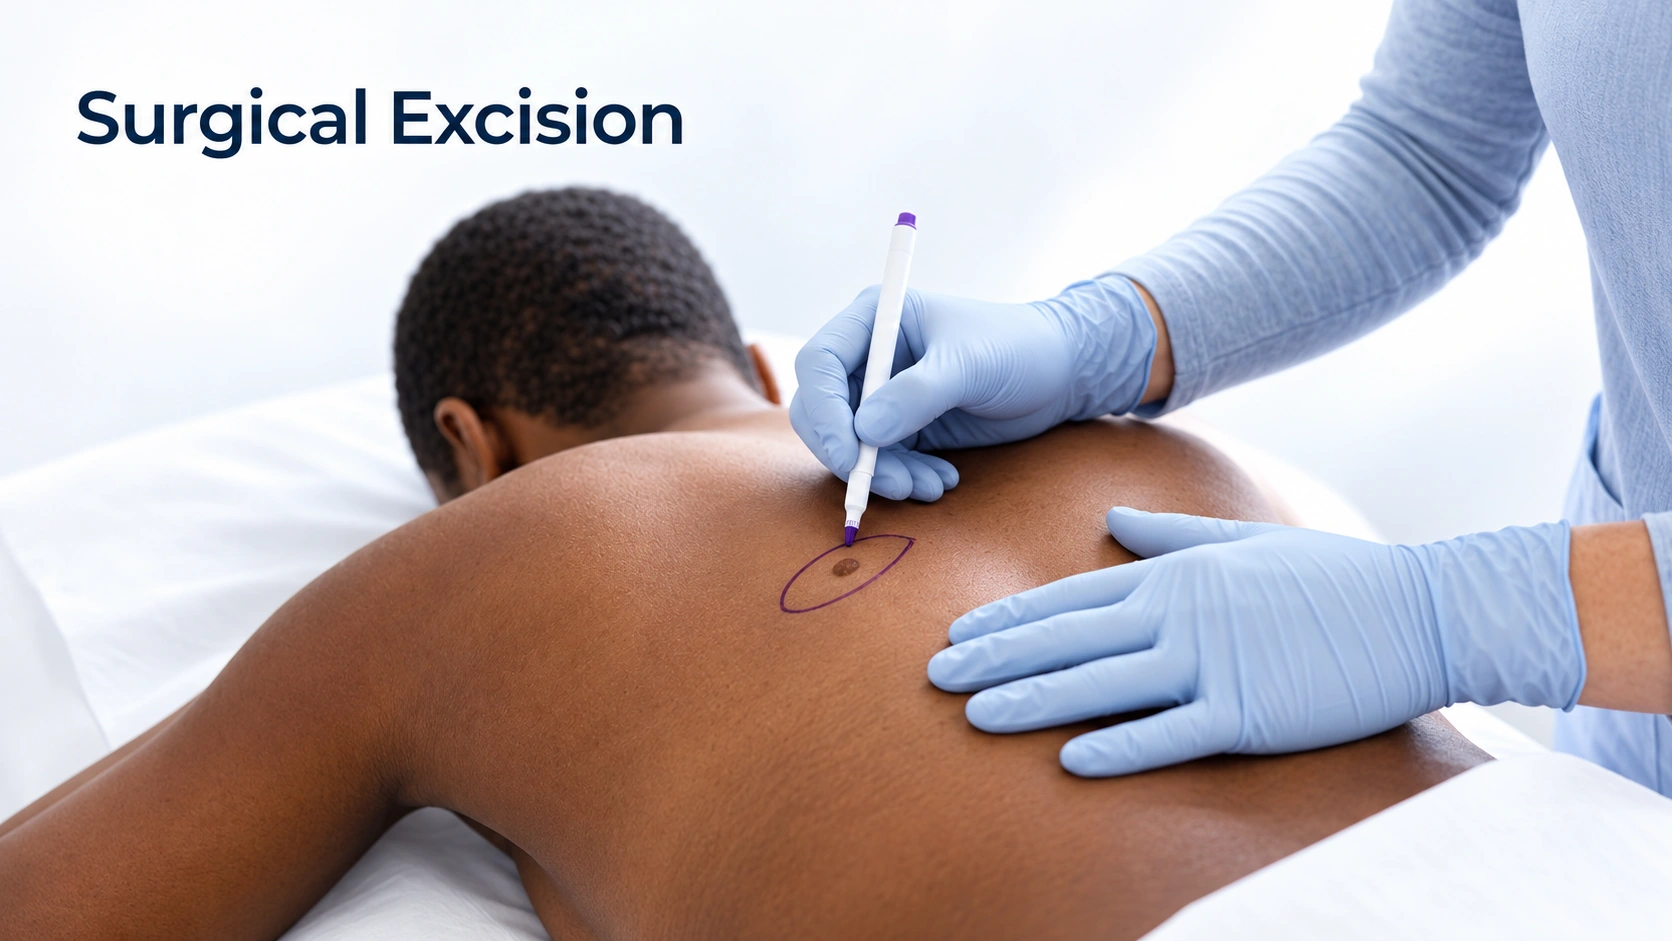
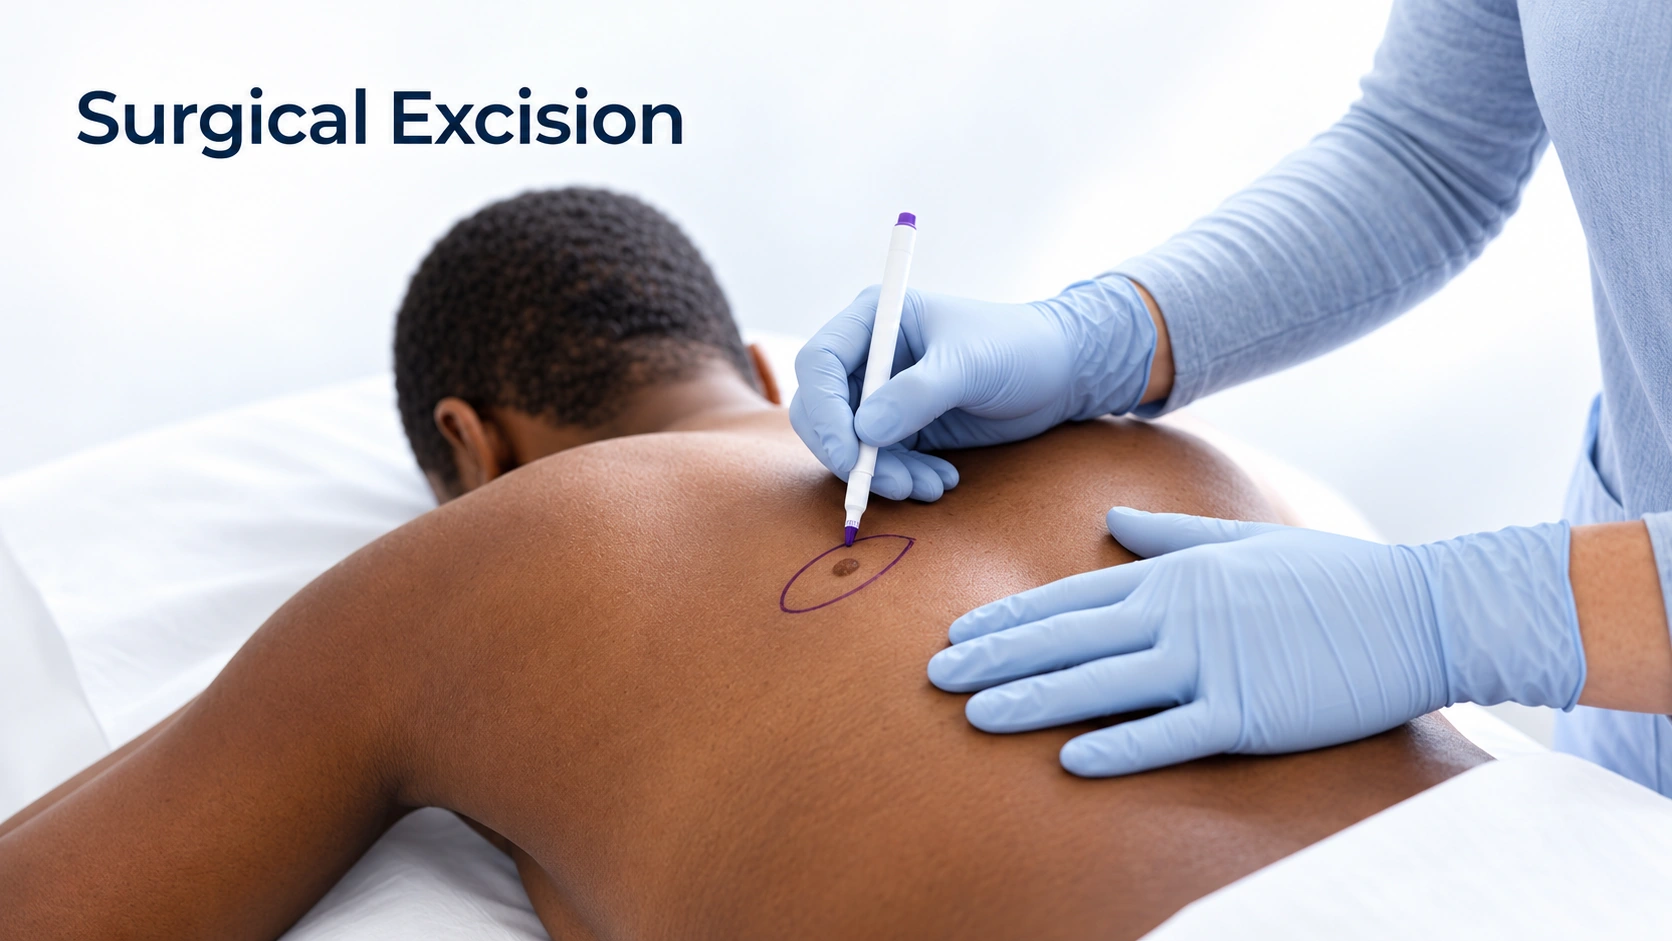
Excision
The treatment that cures the great majority of thin melanomas. Once the diagnosis is confirmed, a second and wider operation removes a margin of surrounding skin, with the width set by how thick the melanoma was. The scar is longer than most people expect, and that is the trade that stops it coming back at the site. Anything pigmented that is removed, anywhere, should be sent for pathology.
Sentinel lymph node biopsy
Above a certain thickness, the first lymph node the area drains to is located with a tracer and removed to see whether cells have reached it. It is a staging test rather than a treatment: it tells you where you stand and shapes what is offered next. It carries its own risks, including lasting swelling of the limb, so it is offered as a discussion rather than an automatic step.
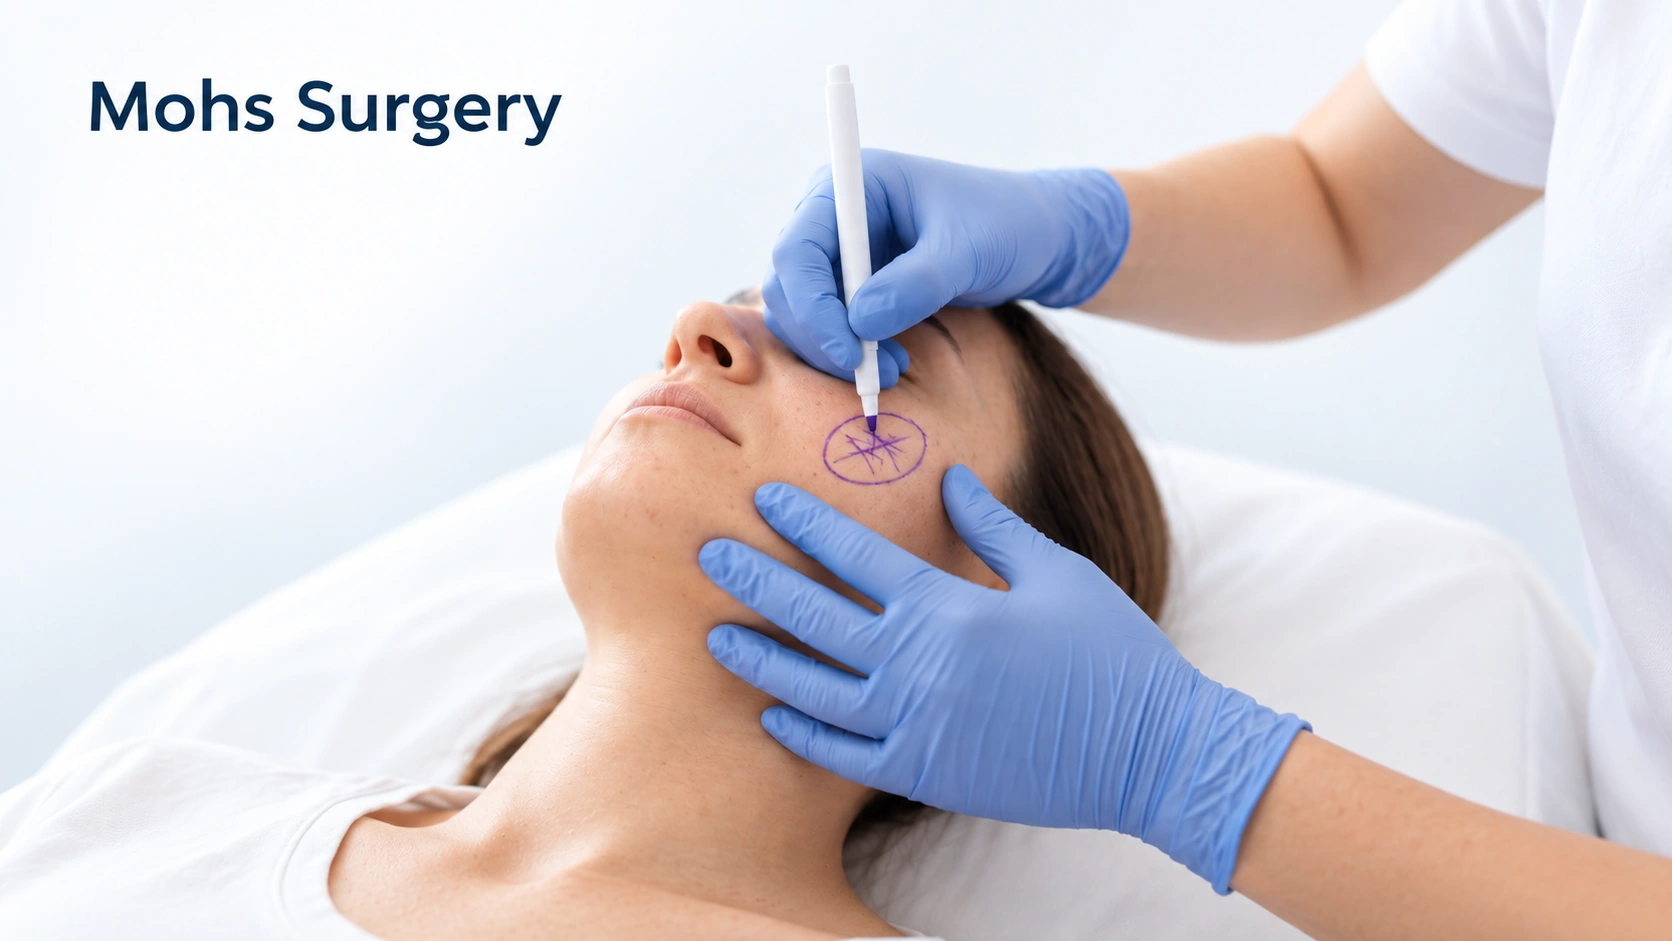
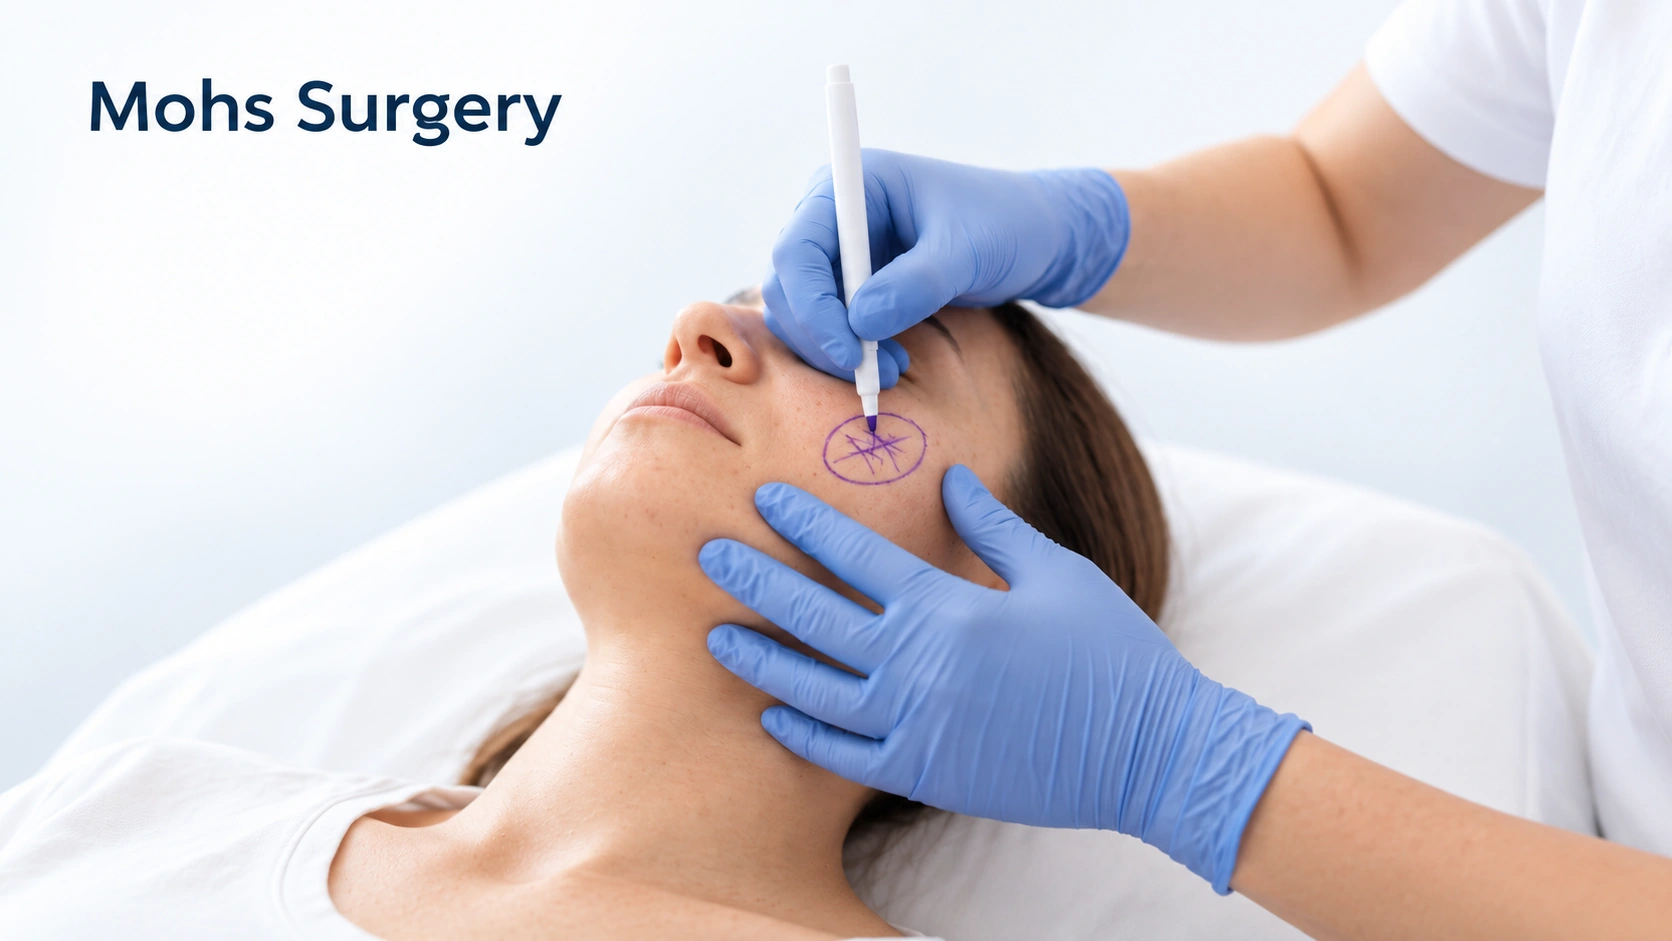
Mohs Surgery
Used at some centers for lentigo maligna on the face, where sparing skin matters and the true edge of the pigment is hard to see. It is not the standard operation for melanoma generally — wide excision is, and the evidence sits with that. If Mohs is offered to you, it is fair to ask why it suits this particular lesion in this particular place.
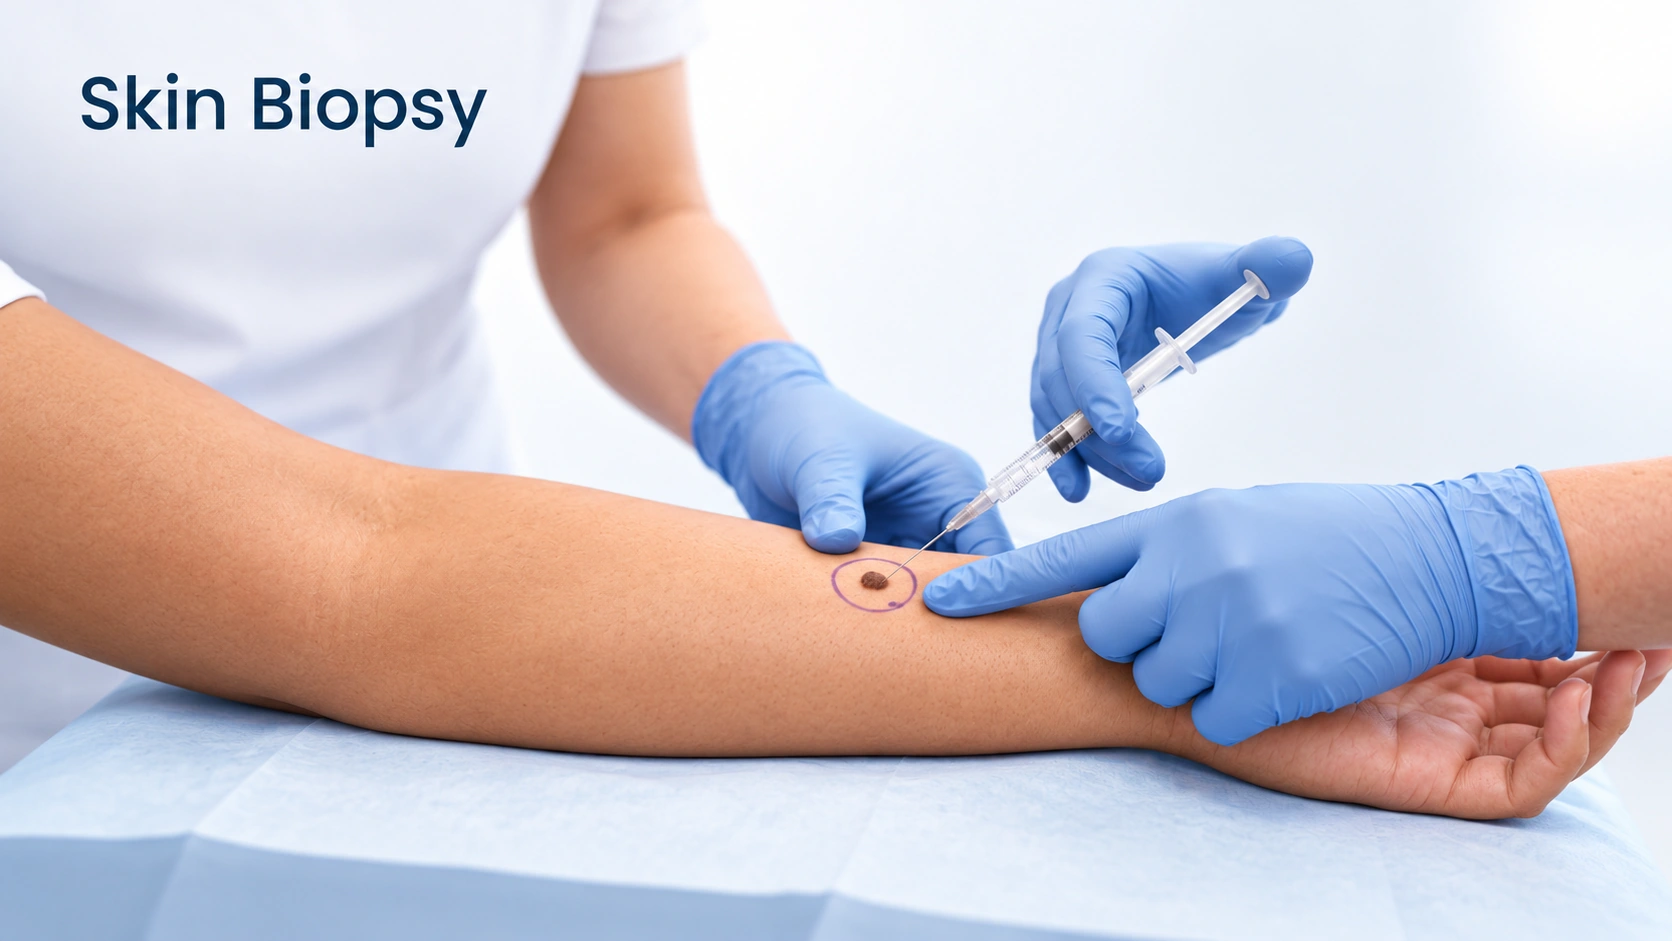
Skin Biopsy
Nothing diagnoses melanoma except a biopsy. Where it is possible, the whole spot is removed with a narrow margin rather than sampled, because the pathologist needs the full depth to measure the thickness, and thickness sets everything that follows. It is done under local anesthetic and usually takes under half an hour. A biopsy does not make melanoma spread, and believing that it does is a common cause of delay.
Outlook
What to expect with Melanoma
Melanoma does not progress on a fixed schedule. Some variants change over years, others over weeks, so this is the sequence, not a timetable. Skin checks continue for years after treatment, because a second melanoma and a recurrence are both possible, and close relatives are usually advised to have their skin checked.
- 1
In the top layer only · In situ
The abnormal cells sit in the outer layer only. It cannot spread from here, and removing it ends the story.
- 2
Growing sideways · Early invasive
Cells have entered the deeper skin, but only just. Thin melanomas, generally under one millimeter, are removed with a margin of skin. Superficial spreading melanoma often changes over months to years.
- 3
Growing downward · Thicker
The deeper the growth, the higher the chance cells have reached lymphatic channels. Thickness, and whether the surface has broken down, drive whether lymph nodes are checked. Nodular melanoma can grow downward over weeks to months, so a fast-growing firm bump is urgent whatever it looks like.
- 4
Reaching lymph nodes · Regional
A lump near a previous melanoma site is significant and checked promptly.
- 5
Reaching other organs · Advanced
Melanoma can spread to organs far from the skin. Immunotherapy and targeted therapy have changed outcomes substantially in the last decade.
Complications
Complications to know about
Cells travel to the nearest nodes first
A lump near a previous melanoma site is significant and checked promptly.
Treated by an oncology team
Melanoma can spread to organs far from the skin. Immunotherapy and targeted therapy have changed outcomes substantially in the last decade.
When to get help
When to get help
When to seek care
Arrange prompt assessment of a new or changing unusual spot, especially an evolving lesion or one that bleeds. Diagnosis requires clinical evaluation and usually biopsy.
Lookalikes
What else could it be?
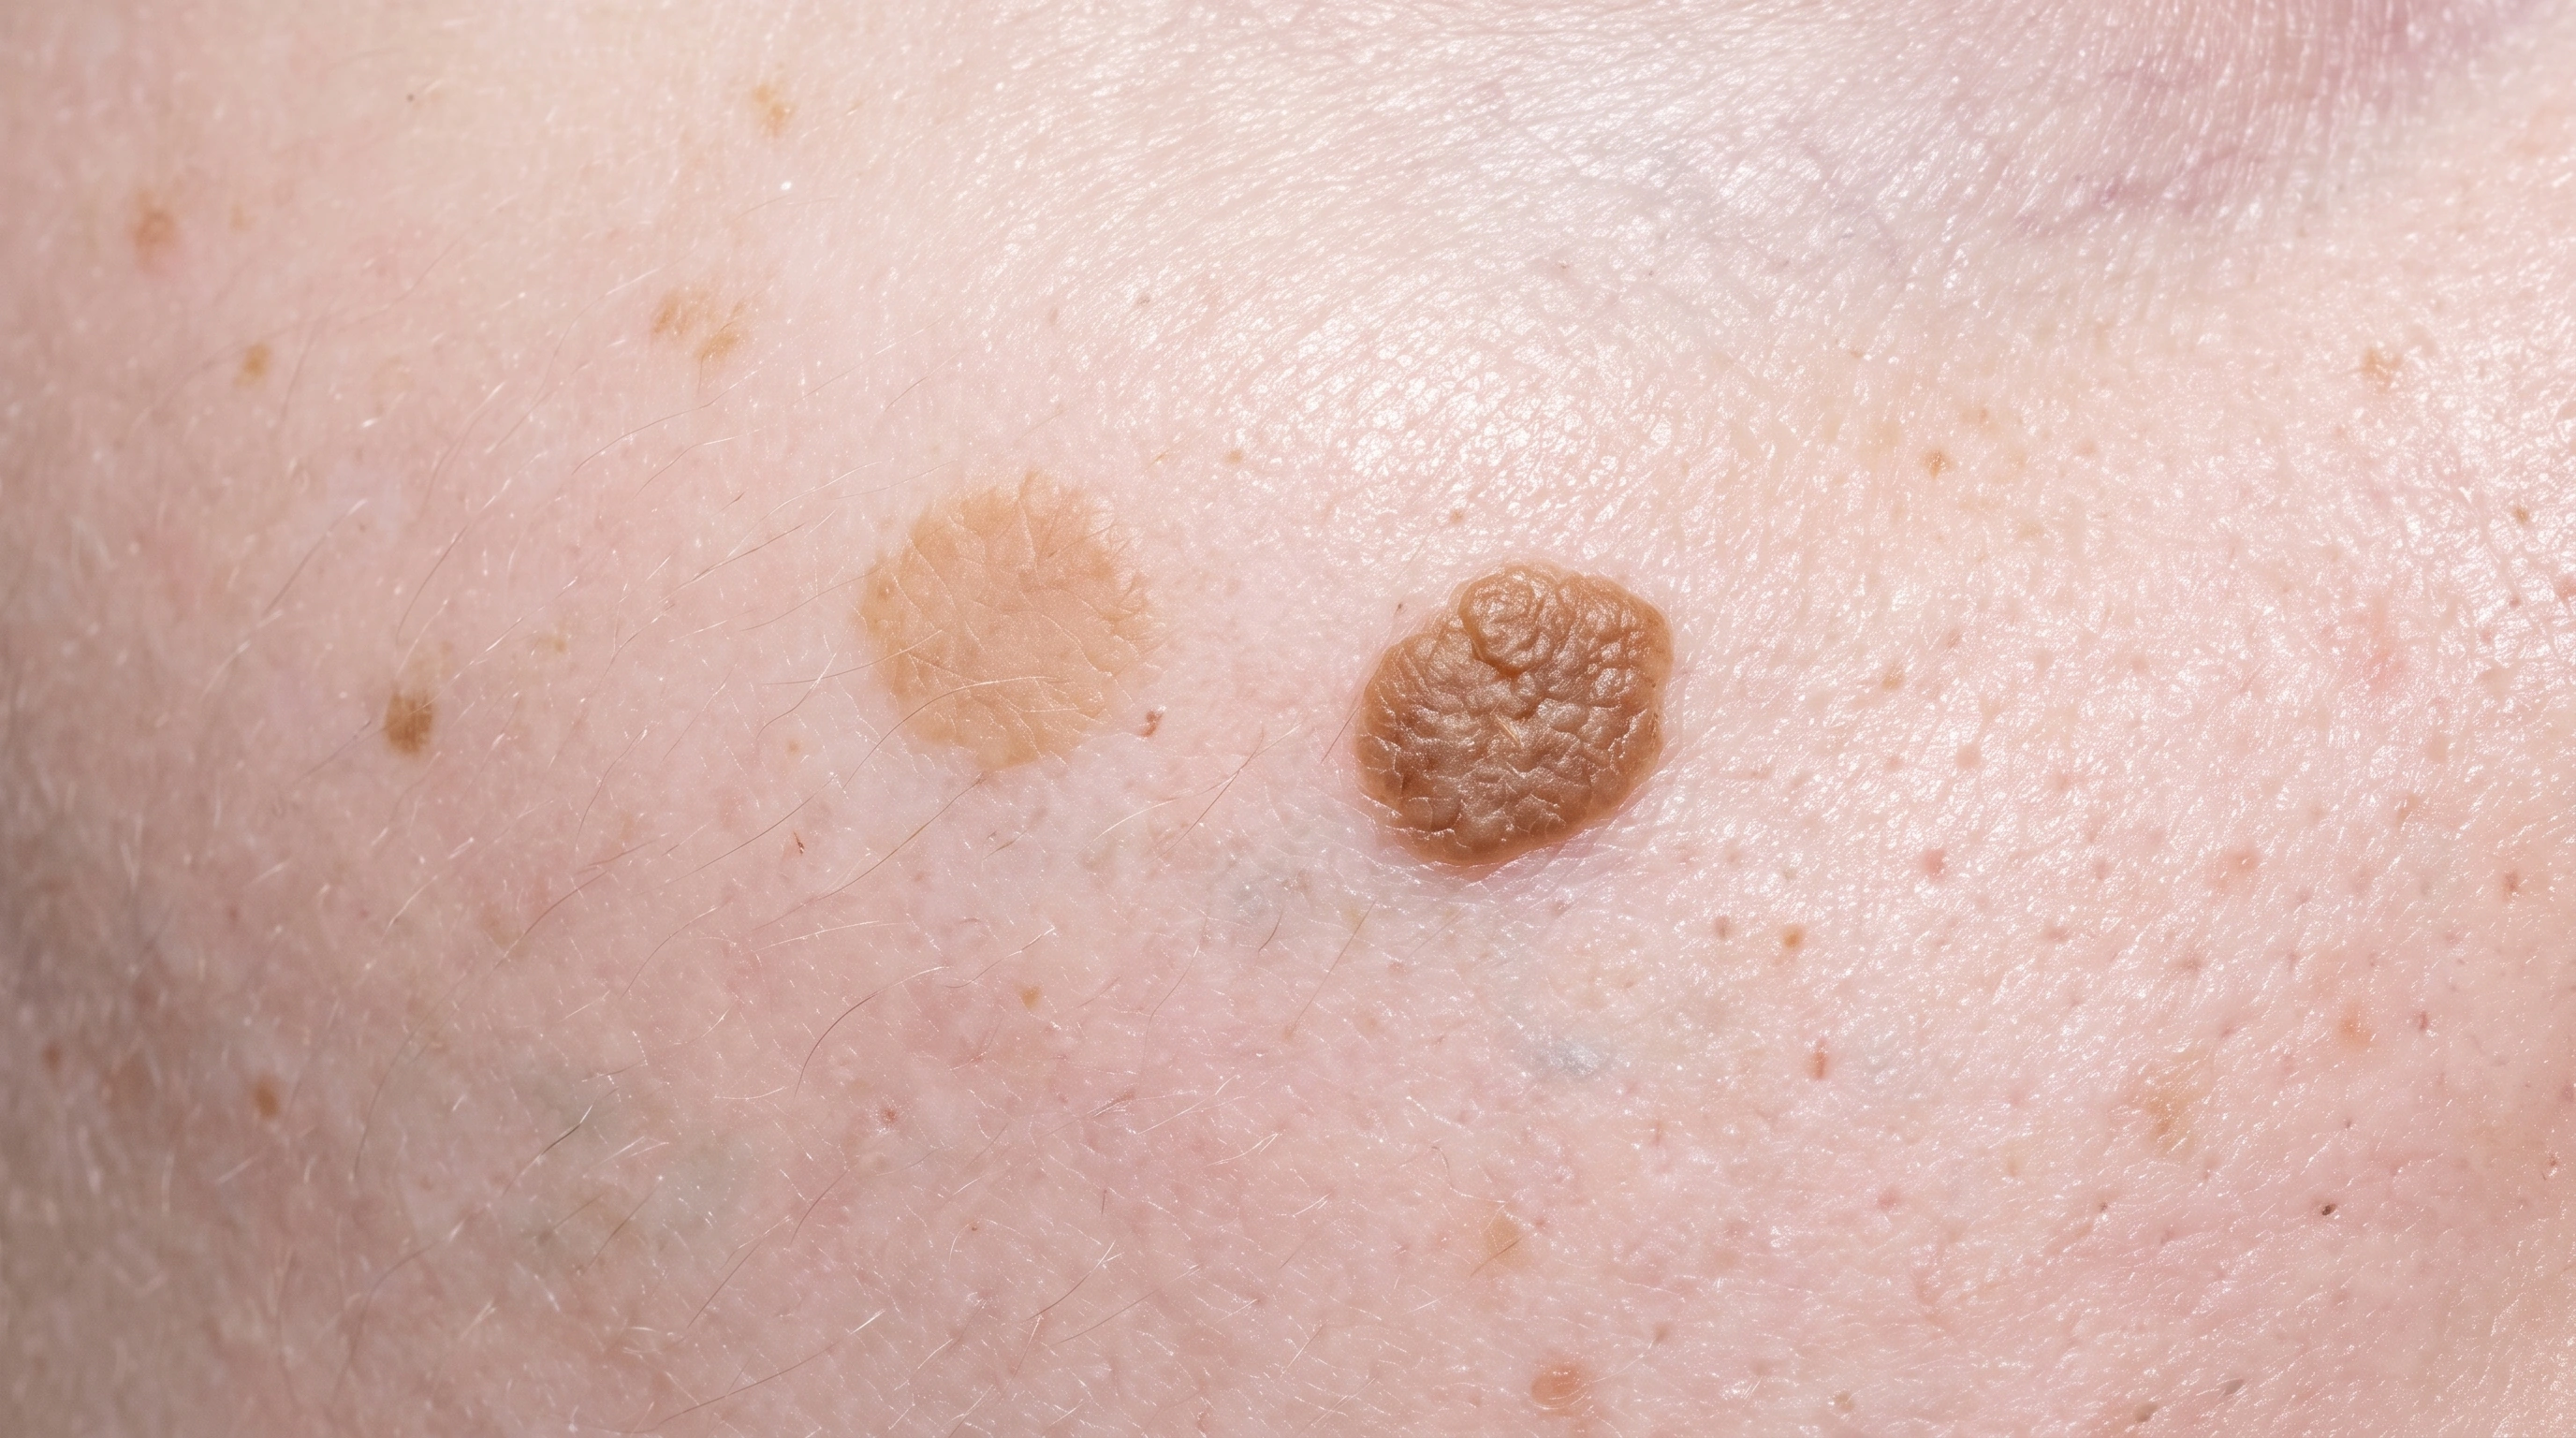
Seborrheic Keratosis
Seborrheic keratoses often look waxy, crumbly and stuck on. Melanoma may look unlike your other spots; an uncertain dark growth needs examination.
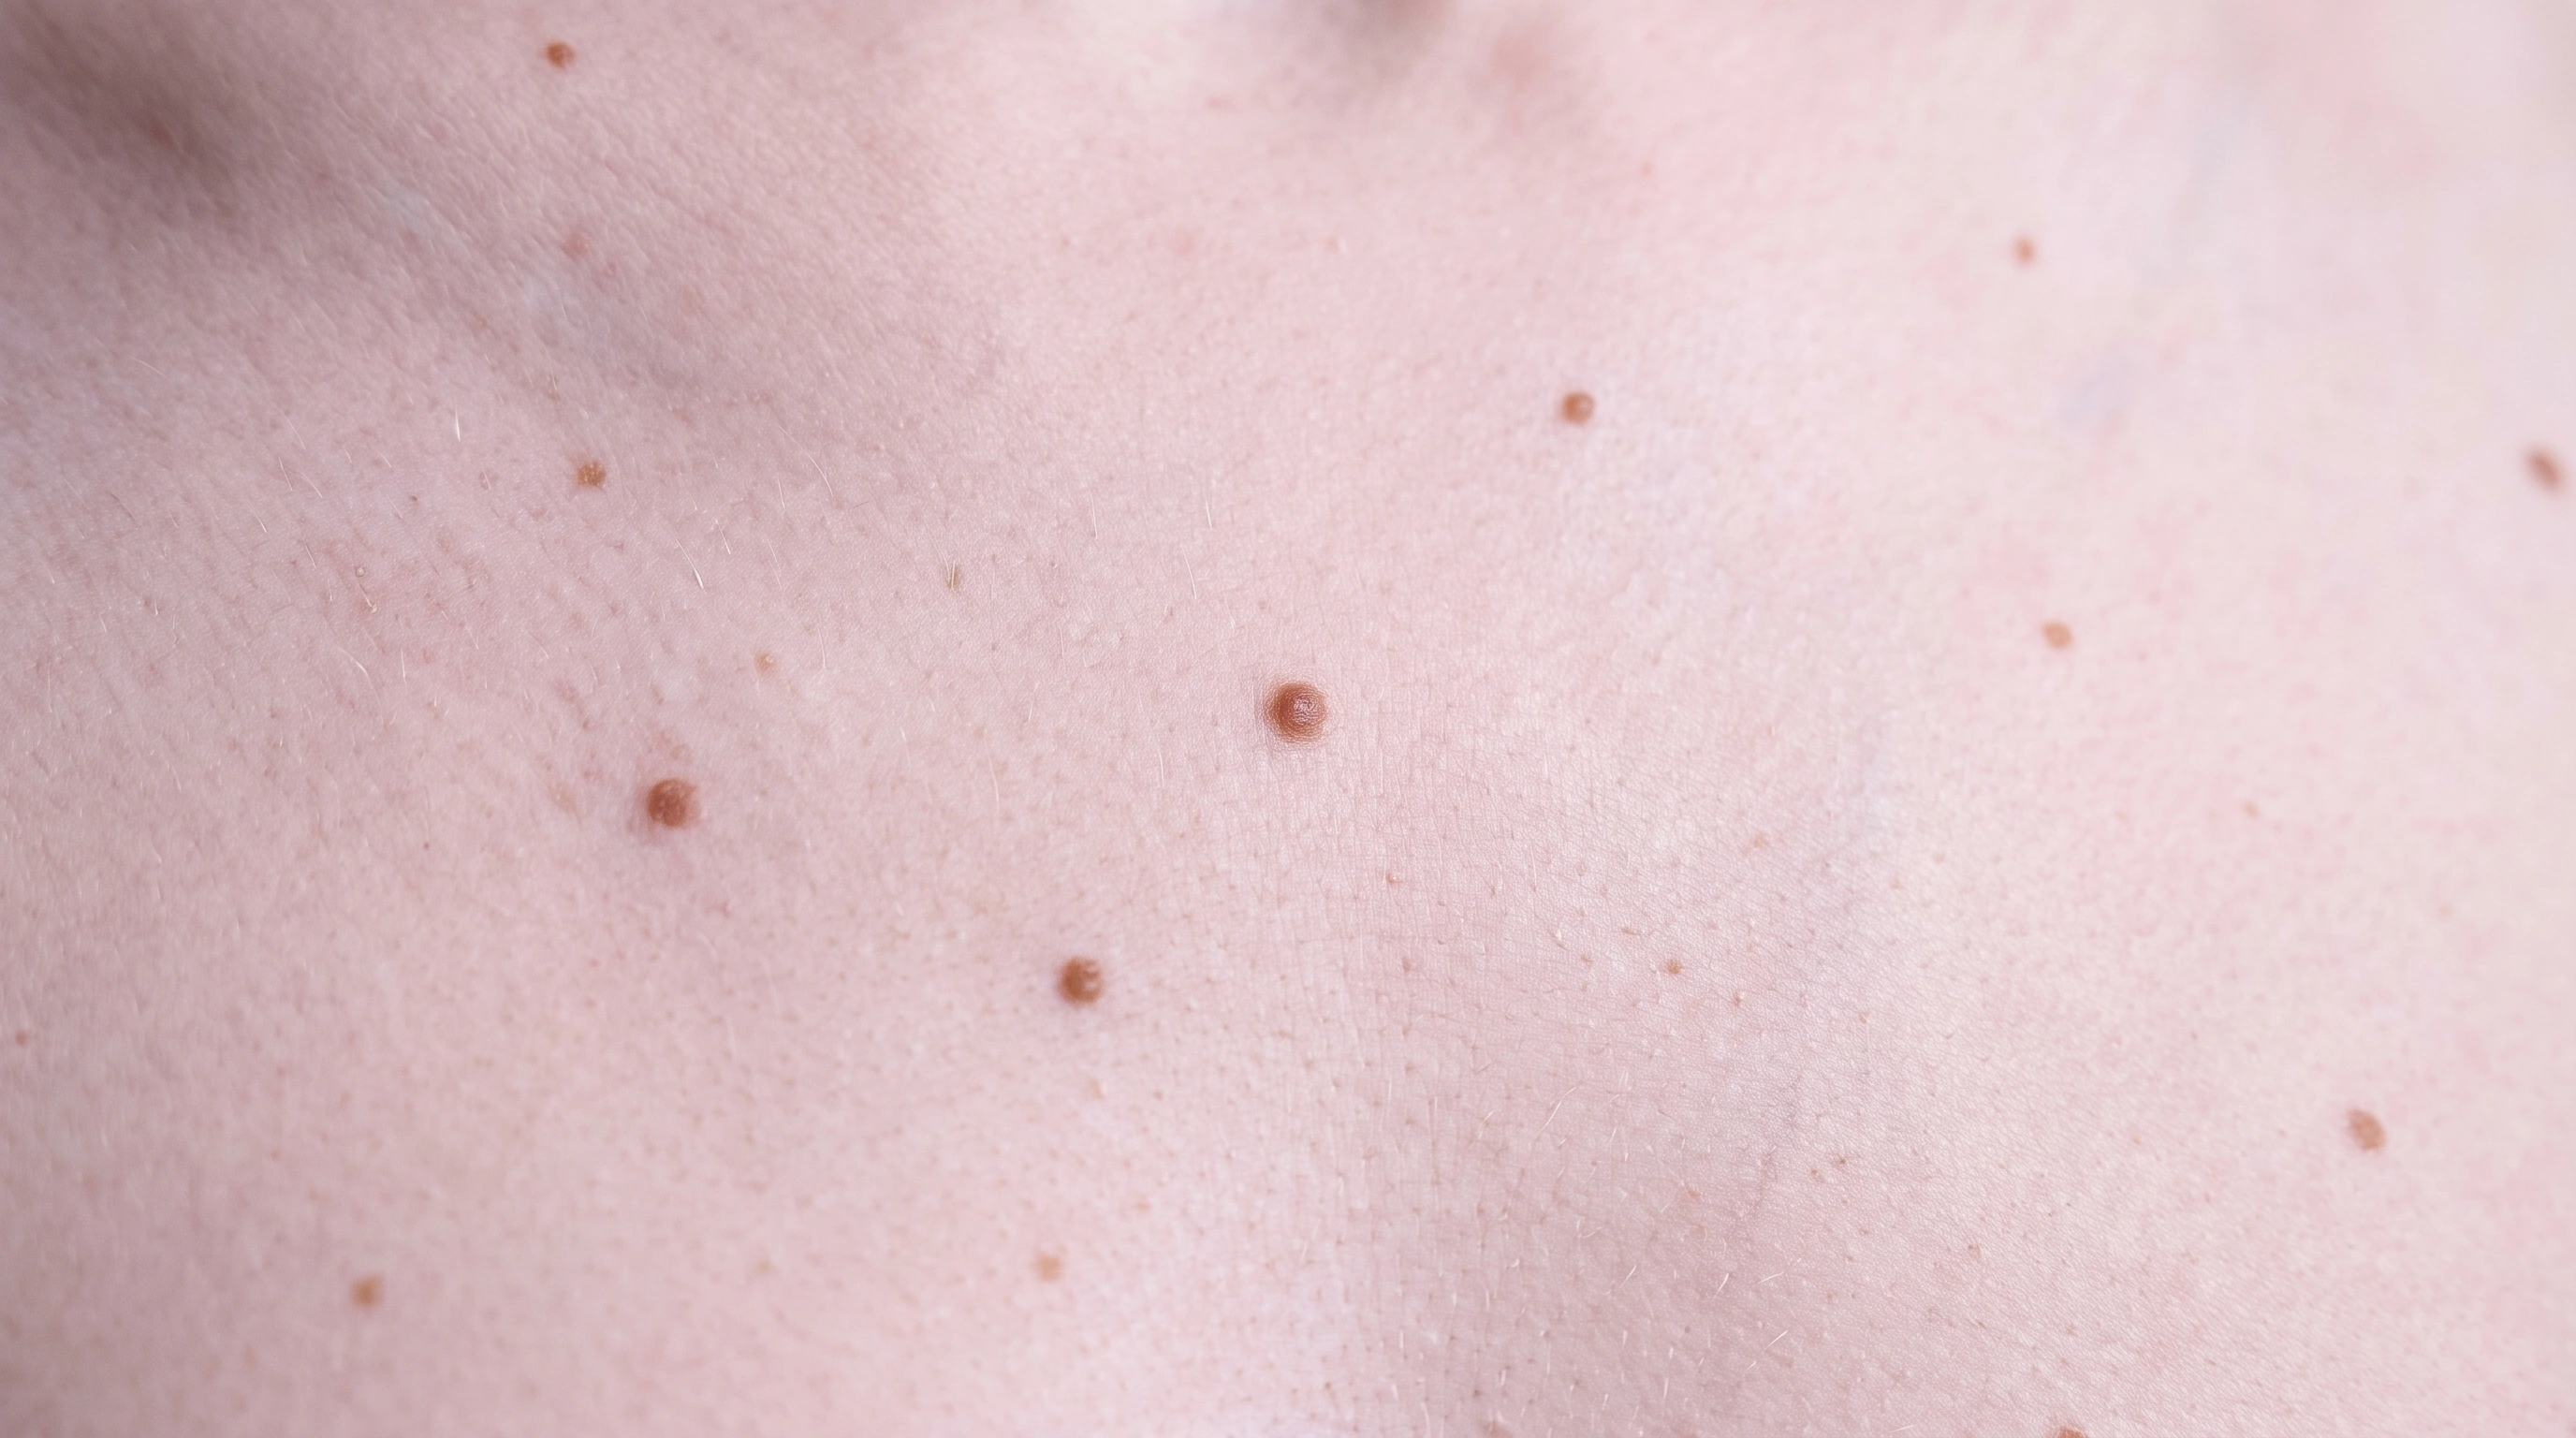
Moles
Ordinary moles are often fairly even in shape and color. A new or changing spot that looks different from your other moles needs checking.
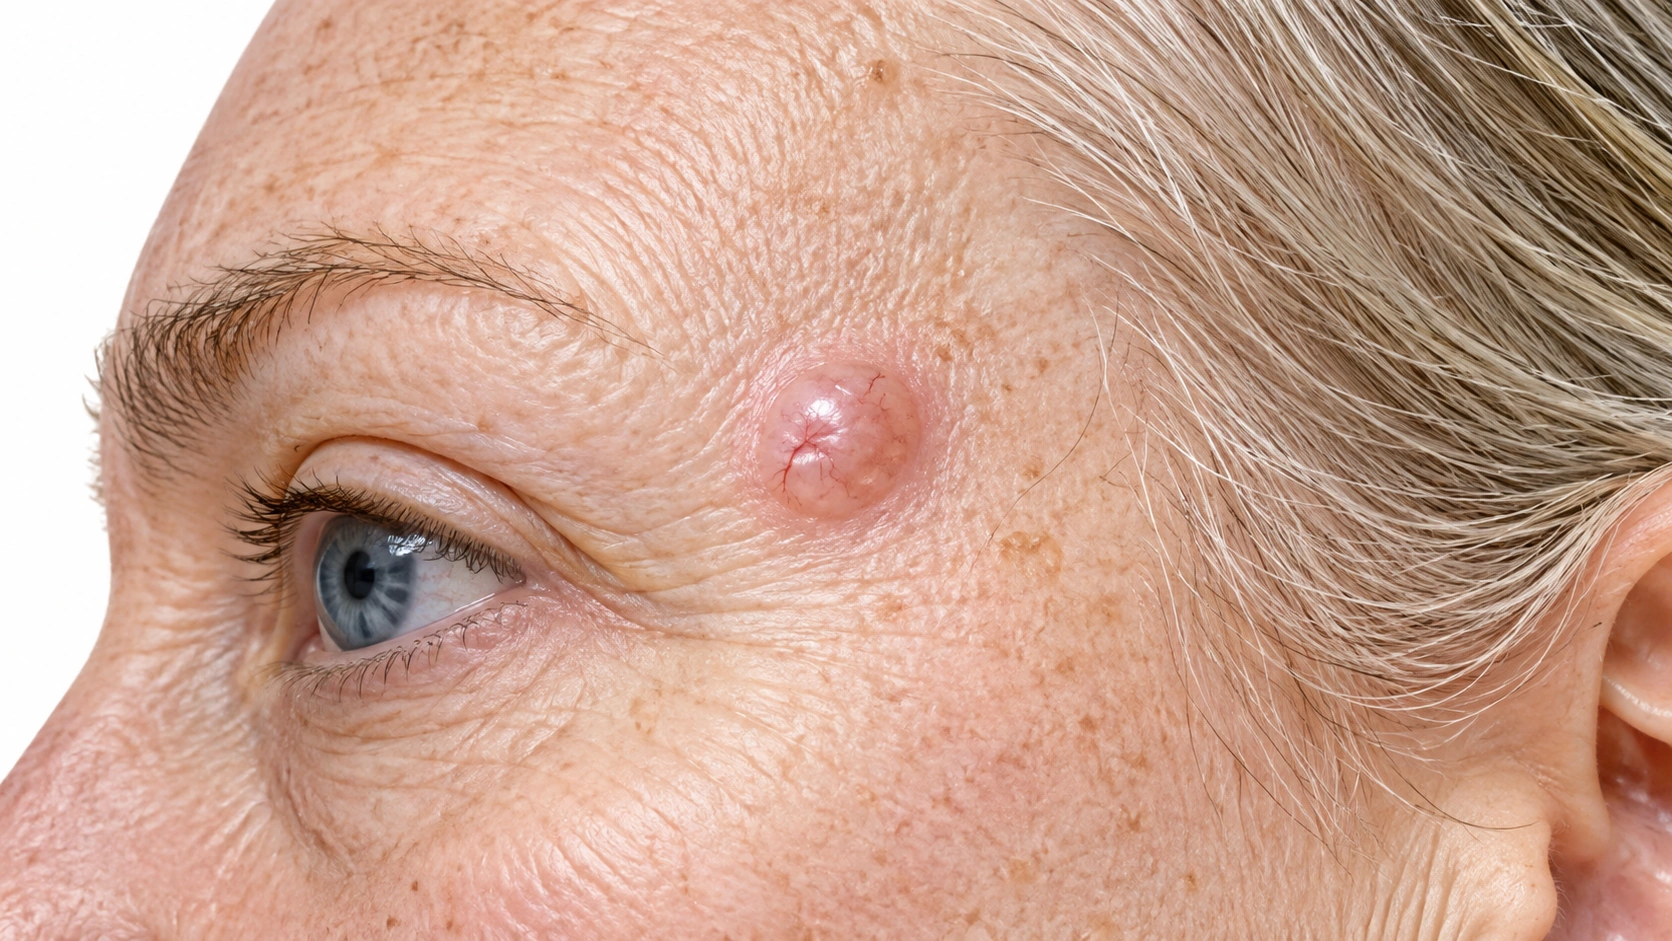
Basal Cell Carcinoma
Pigmented basal cell cancer may look pearly, with visible vessels or repeated scabbing. Melanoma can also look dark; either needs examination rather than watching at home.
Questions
Questions you might be asking.
How quickly does melanoma grow?
It varies more than people expect. The common superficial spreading variant often changes over months to a few years. Nodular melanoma can grow downward over weeks to a few months. You cannot tell which you have by looking, so a changing spot gets examined now, not in six months.
Does having a mole removed spread cancer?
No, and this belief causes delay. Removing a suspicious lesion is how melanoma is diagnosed and how the thickness is measured, and thickness determines the treatment. There is no evidence a biopsy spreads it.
Should I have all my moles removed to be safe?
No. Most melanomas arise as new spots, so removing moles does not remove the risk and means many scars for no benefit. Many or unusual moles are a reason for regular examinations, not preventive removal.
I have a dark line on my nail. Is that melanoma?
Usually not. Pigmented nail bands are common and often normal in deeper skin tones, frequently on several nails at once. It needs examining if it is on one nail only, if it is getting wider, if it has more than one shade, if the nail is splitting, or if the pigment spreads onto the skin around it.
If it is removed and the margins are clear, am I finished?
The melanoma is treated, but you are not discharged. Having had one raises the chance of a second, so skin checks continue for years, and close relatives are usually advised to have their skin examined. Ask how often yours should be and who arranges it.
I never sunbathe. Do I still need to worry about a changing spot?
Yes. Sun exposure raises risk, but melanoma also occurs on soles, palms, under nails and on skin never exposed, and in people who have never burned. Sun history changes your risk profile, not whether a particular spot should be looked at.
Sources
Sources and further reading
Related
Keep exploring.
Basal Cell Carcinoma
Seborrheic Keratosis
Skin Biopsy
Surgical Excision
Moles
Mohs Surgery
Melanoma vs Seborrheic Keratosis
Moles vs Melanoma
Melanoma vs Atypical Moles
Cryotherapy

Electrodesiccation and Curettage