Athlete's Foot
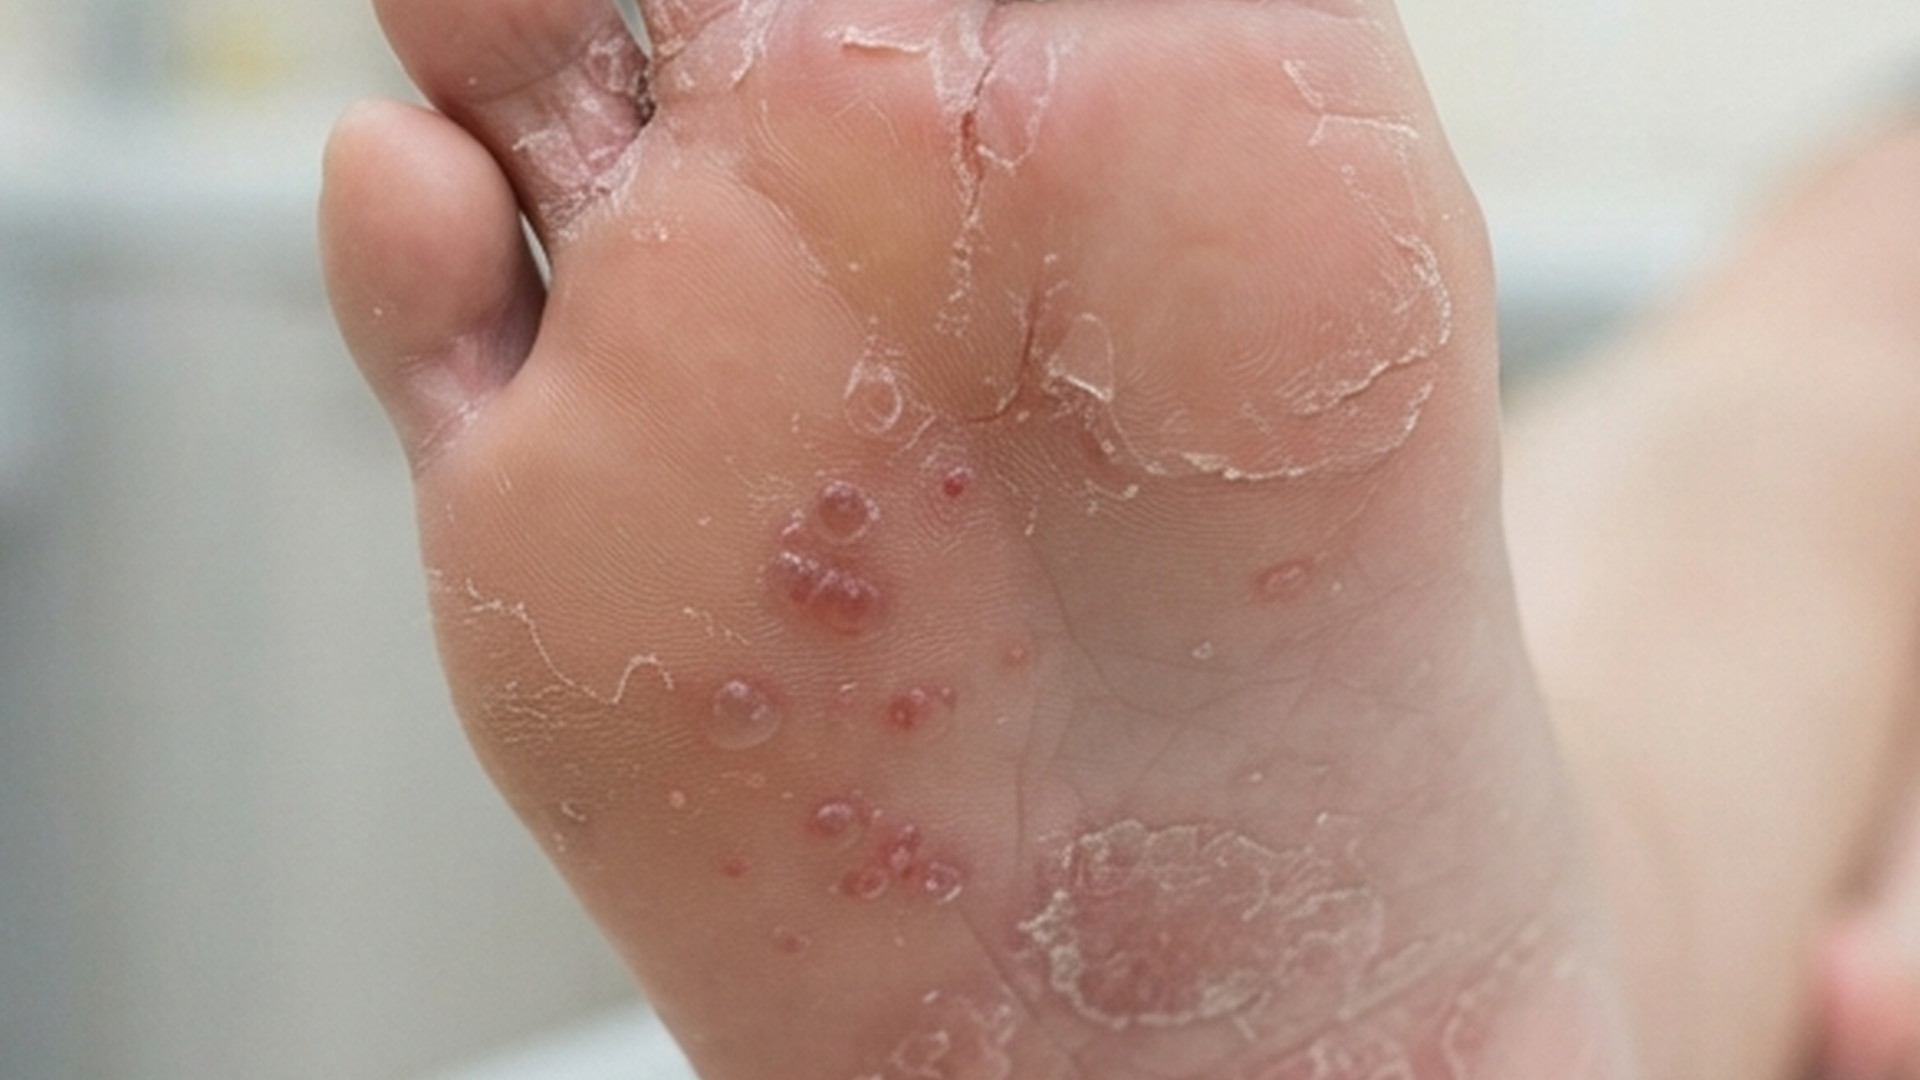
Athlete's foot is a fungal infection. It usually starts in the split between the smallest toes, it itches, and it spreads. Dry feet are skin that has lost water. The heel and the ball of the foot go tight, rough and pale, and they stay put. Soggy white skin between the toes is fungus, not dryness.
| The difference | Athlete's Foot | Dry Feet |
|---|---|---|
| What it is | A fungus feeding on the skin | Skin that has run out of water |
| What it looks like | White and soggy, or fine scale | Even, dull, flaky skin |
| What it does over time | Spreads, and comes back | Follows the weather |
| What actually treats it | An antifungal cream | A thick urea or lactic acid cream |
Skin that has run out of water The outer layer holds less moisture than it should, so it stiffens and flakes off. Soles have no oil glands, so they dry faster than the rest of you.
Side by side
Athlete's Foot
A fungus feeding on the skin
Dermatophytes are the same family of fungi that cause ringworm. They live on keratin in the top layer of skin. Warm, damp shoes are what let them take hold.
Dry Feet
Skin that has run out of water
The outer layer holds less moisture than it should, so it stiffens and flakes off. Soles have no oil glands, so they dry faster than the rest of you.

Dry, intact skin between the toes. The outer layer is a poor place for anything to grow.

Shoes, socks and sweat keep the skin between the toes wet for hours. Softened skin is what the fungus needs.

Dermatophytes feed on keratin, so they live in the dead outer layer and go no deeper. That is why an antifungal cream reaches them.

The barrier breaks down into peeling, cracking and itching, and those cracks let bacteria in. Untreated it spreads to the soles and the nails, and the nails are what reinfect the skin later.
Athlete's Foot
White and soggy, or fine scale
Between the toes the skin turns white, soft and split. On the sole it can look like dry scale that covers the heel and creeps up the sides, like a slipper.
Dry Feet
Even, dull, flaky skin
Rough and greyish on the heel and the ball of the foot. Deep cracks can open along the heel rim. The colour is even and there is no clear border.

This is the presentation most people picture. The skin reads pink to dull red under a layer of fine white scale, driest across the sole and the sides of the foot. The trap on light skin is that the pink is faint in the moccasin pattern, so it gets called winter dry skin and moisturized for years. The edge is what tells them apart. Plain dry skin fades out gradually. This stops at a line along the side of the foot, and the toenails are usually scaly or thickened too.

On medium skin the pink base is muted, so scale becomes the main clue and the rash is often mistaken for something else. Fine gray-white flaking on the sole gets treated as callus or eczema, and the raised scaling edge creeping onto the top of the foot gets treated as a ring of dry skin. Two checks help. Look between the fourth and fifth toes for white soggy skin or a split, and look at the toenails. Nail involvement almost always means the fungus is the cause.

On brown skin the pink or red base is usually not visible at all, so redness is a poor thing to go by. Everything else still works: fine dry scale, white soggy skin in the web spaces, splits at the base of the toes, and a raised scaling edge moving onto the top of the foot. Because the redness appears to be missing, these infections are regularly judged milder than they are and treated for too short a time.

After the fungus is gone, deep skin often keeps a flat dark mark where the skin was inflamed. That is post-inflammatory hyperpigmentation, a stain left by the inflammation rather than infection that is still there, and it can take several months to fade. It is a common reason people keep applying antifungal cream long after the fungus has cleared. The test is simple. Still scaling, itching or peeling means the infection is active. Flat, smooth and simply darker is a mark, and time is what fixes it.
Athlete's Foot
Usually yes
Itching and burning, worst between the toes and worst when the shoes come off.
Dry Feet
Not much
Tightness is the main feeling. A cracked heel can sting when you walk on it.
Athlete's Foot
Between the toes first
Most often the gap between the fourth and fifth toes. From there it moves to the sole, the sides and the toenails. It often starts on one foot.
Dry Feet
Heels and the ball of the foot
The pressure areas, on both feet, fairly evenly. It stops well short of the toe webs.
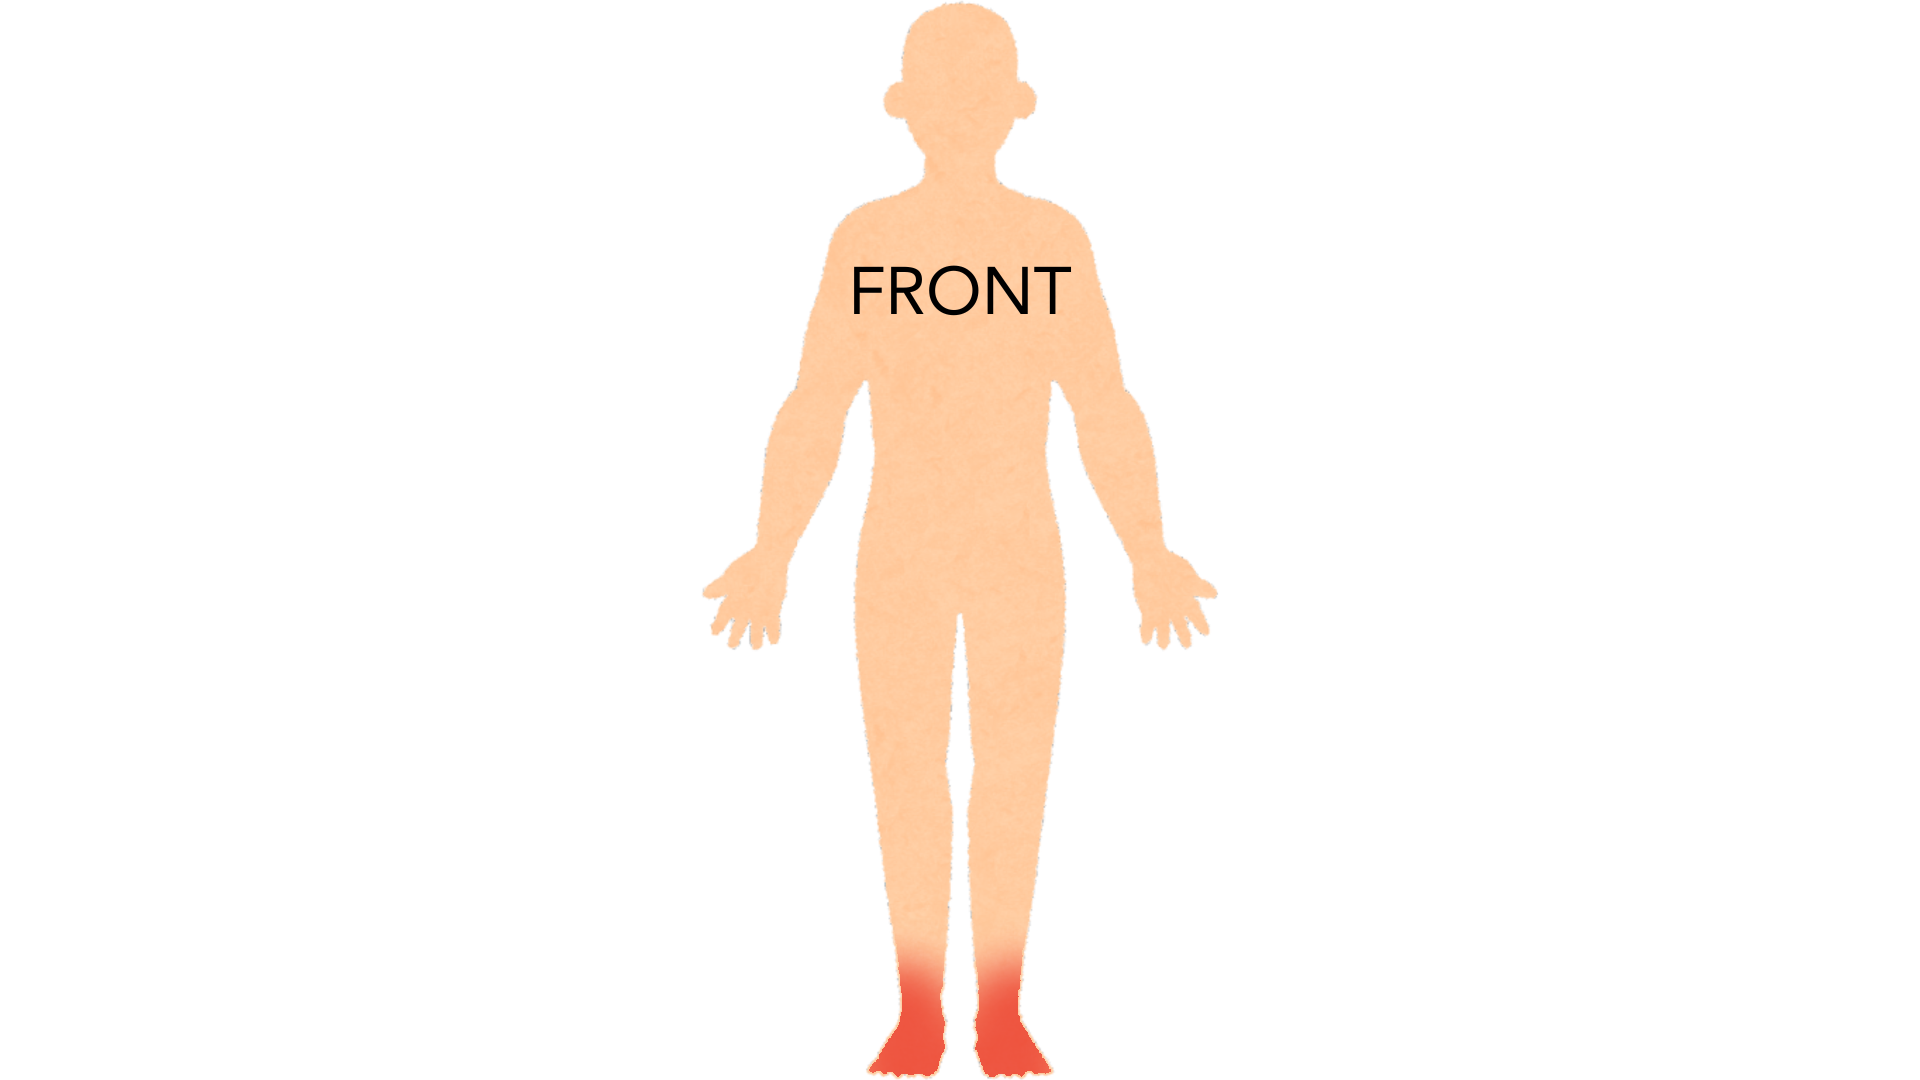
It starts between the toes, most often in the tight web beside the little toe, and spreads to the sole, the heel and the sides of the foot. It can move to the toenails. If a hand is involved it is usually only one, from scratching the feet.
Athlete's Foot
Spreads, and comes back
It will not clear on its own. Left alone it reaches the toenails, which are much harder to treat, and it passes to other people on shared floors.
Dry Feet
Follows the weather
Worse in winter, in dry air, and after long hot showers. Better within days of regular moisturizing. It does not spread and you cannot catch it.
Athlete's Foot
An antifungal cream
Terbinafine or clotrimazole from the drugstore, rubbed in twice a day. Keep going for a week or two after the skin looks normal, or it comes straight back.
Dry Feet
A thick urea or lactic acid cream
Put it on damp skin after a shower. Urea pulls water into hard skin and softens it. Gentle filing of a damp heel helps, a little at a time.

The most effective thing you can buy for athlete's foot, and the shortest course: once or twice a day for one to two weeks between the toes. It kills the fungus rather than just stopping it growing, which is why it works faster than the older creams. It will not clear an infected toenail, and it will not clear thick sole scale on its own.

The cheap, widely available option, applied twice a day for four weeks. It works well, it just takes longer than terbinafine, so the temptation to stop early is greater. Cover the whole foot and both feet, and carry on for one to two weeks after the skin looks normal.
Another azole cream, sold over the counter in some places and on prescription in others. It is a reasonable alternative if clotrimazole or miconazole has irritated the skin. It is no faster than they are, and the same four-week discipline applies.

A urea or salicylic acid cream thins the hard scale on the sole so an antifungal can actually reach the skin underneath. It is a helper, not a treatment: on its own it does nothing to the fungus. It is worth adding for the dry moccasin pattern, where cream otherwise sits on top of the thickened surface.

Powder keeps feet and the inside of shoes dry and lowers the amount of fungus you put back on your foot each morning. It is prevention, and it is good at it. It is not strong enough to clear an established infection, so use a cream to clear it and powder to keep it away.

An aluminum-based antiperspirant made for feet cuts the sweating that keeps the skin soft and the shoe damp. It treats the cause of recurrence rather than the infection itself. Useful for people who clear it every time and get it back every summer.

Tea tree oil has some antifungal activity and a few small studies behind it, but it clears fewer infections than the pharmacy creams and takes longer. It also causes allergic reactions on the feet often enough to matter. An antifungal cream costs about the same and works.

Both slow fungal growth in a dish, and neither reliably clears an infection on a foot. What they do reliably is dry out and damage the skin, and cracked skin on a foot is the entry point for bacteria. This is one to skip rather than to try first.
A steroid cream calms the itch, so it feels like it is helping, while the fungus spreads underneath with less to show for it. The rash it leaves is harder to recognize and harder to treat, and it makes a later scraping unreliable. Do not put a steroid on an undiagnosed foot rash.
The first-choice tablet for athlete's foot that cream cannot reach: the thick moccasin pattern, widespread infection, and infected toenails. Two weeks usually clears the skin; nails need three months and most of a year to grow out. Liver blood tests are sometimes checked, and it interacts with several common medicines, so the doctor needs your full list.
An equally effective alternative, often given as short pulses rather than daily. It is chosen when terbinafine does not suit or has not worked. It interacts with a long list of other medicines, including some heart and cholesterol drugs, so it needs a proper medication review first.
A once-weekly tablet, used for skin infection that has not cleared with cream when the other two do not suit. It is less effective than terbinafine for the dermatophytes that cause athlete's foot, and slower for nails. If you are pregnant or breastfeeding, ask the doctor managing your pregnancy before taking any antifungal tablet.

The oldest antifungal tablet. It still works, but it needs months rather than weeks, has to be taken with fatty food, and clears fewer infections than terbinafine. It is now mostly reserved for cases where the newer tablets cannot be used.

A prescription antifungal that works differently from terbinafine and the azoles, so it is a useful option when one of those has irritated the skin or has not cleared it. Applied twice a day for up to four weeks. It is no more powerful, just different.

A liquid painted on infected toenails daily for about a year, for people who cannot take antifungal tablets. It matters here because an untreated nail is the usual reason foot skin keeps getting reinfected. Cure rates are well below tablets, and it works best on nails that are only mildly affected.

An older nail lacquer, applied daily for up to a year with the build-up removed weekly. It clears only a small share of infected nails on its own. It is worth knowing about, but if the nails are the reason your feet keep flaring, tablets are the conversation to have.

Combination creams that mix a steroid with an antifungal are still prescribed for itchy foot rashes. The steroid takes the itch away quickly and lets the fungus spread wider and deeper, which is a common route to a longer, harder-to-treat infection. A plain antifungal is the better choice on a foot.
Athlete's Foot
Four weeks with no change
Also worth checking if redness is spreading up the foot, or the toenails have turned thick and yellow.
Dry Feet
Cracks that bleed
Or dryness that has not shifted after a few weeks of daily cream.
Athlete's Foot
Athlete's foot lives in that gap. You are looking for skin that is white, soft and peeling, with a split at the base of the toes. Dry skin does not do that. It builds up on the parts of the foot that take your weight and touch the floor.
Then look at the two feet side by side. Dryness is a mirror image. A fungal infection is often ahead on one foot.
Athlete's Foot
Rich cream between the toes makes athlete's foot worse. The fungus grows in damp warmth, and a thick cream in a closed space keeps the skin wet. This is the most common reason a foot gets worse after weeks of careful care.
Dry Feet
Rich cream is the treatment for dry feet. It replaces what the skin has lost and softens hard heels. Used daily, it works within a week or two.
If you are treating dry feet, keep the cream on the heels and soles and out of the toe webs.
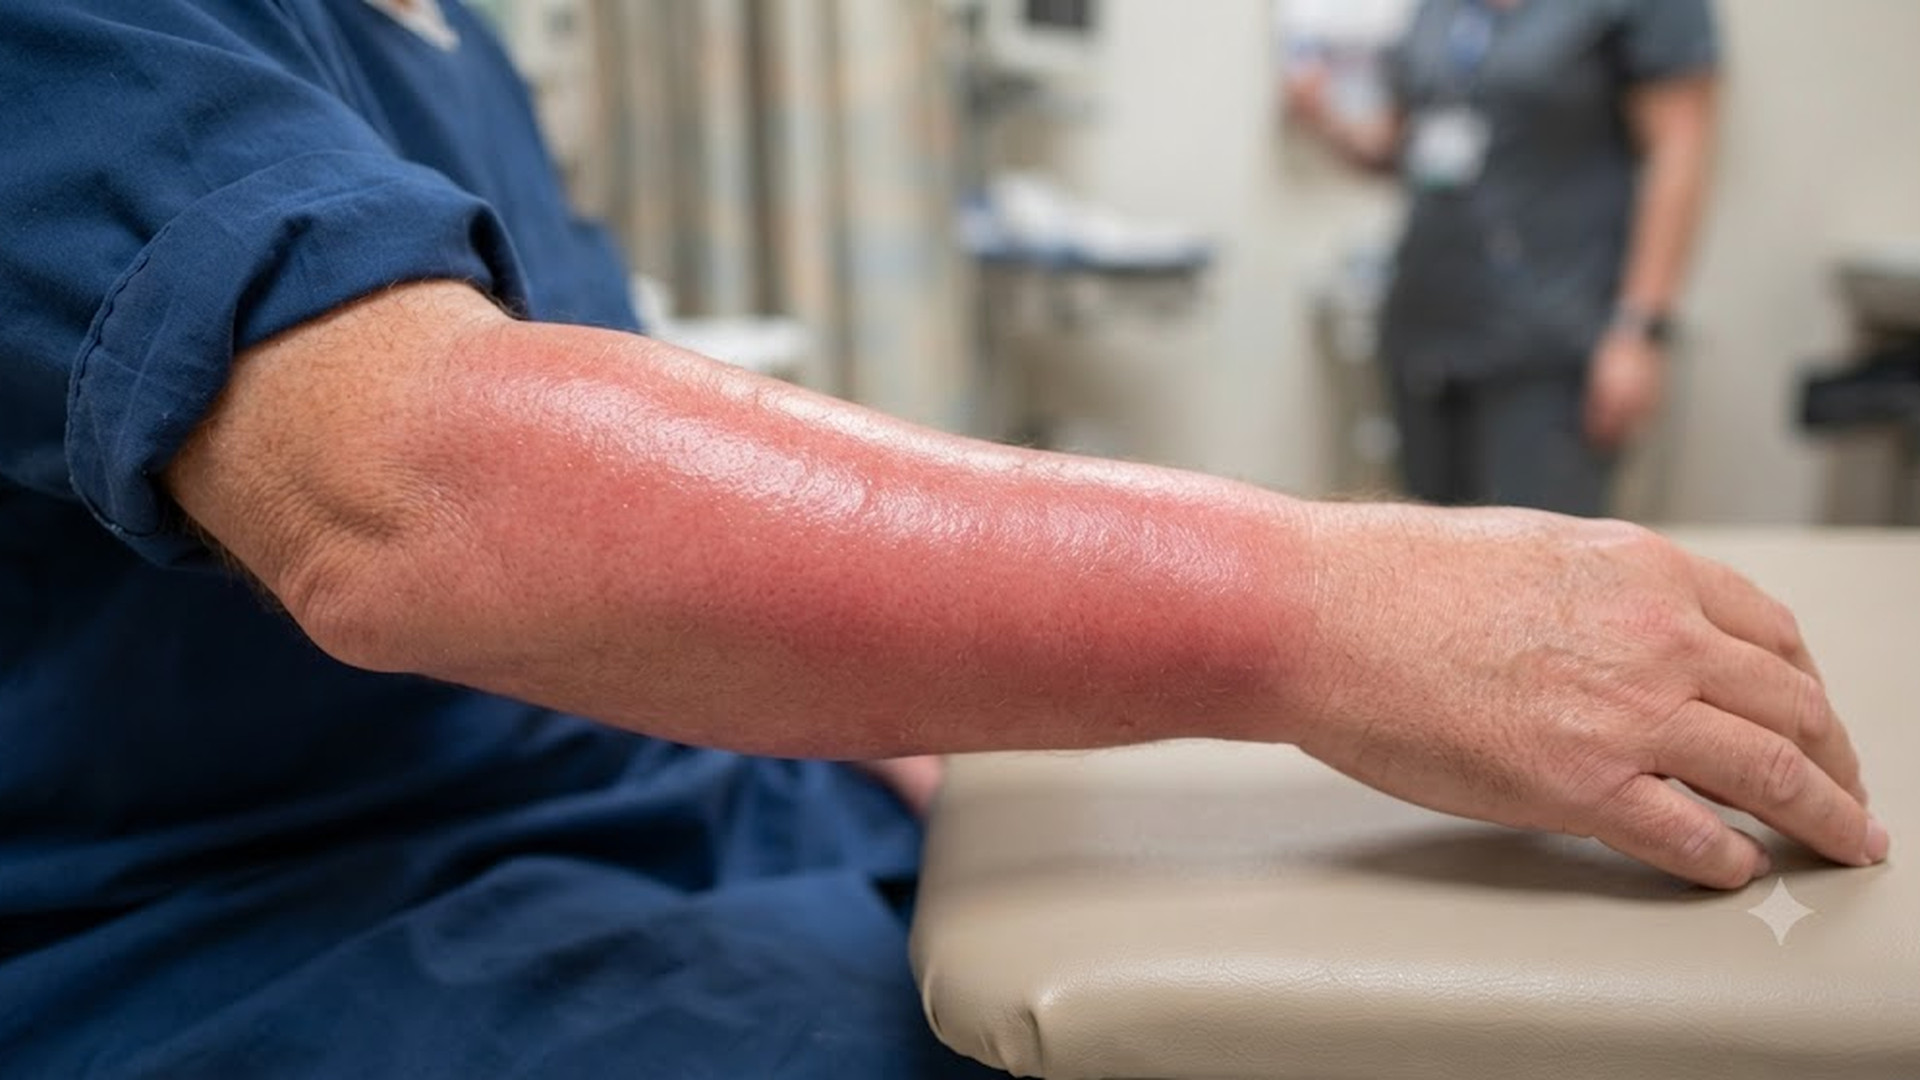
Cracks between the toes are a well-recognized way for bacteria to get into the leg, causing a hot, swollen, spreading redness that needs antibiotics. It is uncommon in healthy feet and much more likely in people with diabetes, poor circulation or a swollen leg. Treating athlete's foot promptly in those groups is mostly about closing that door.

The same fungus moves into the toenails, which become thick, crumbly and yellow-brown. Cream cannot get through a nail, so an infected nail keeps putting fungus back on the skin every time a sock goes on. It is the usual answer to why athlete's foot keeps coming back, and it takes tablets and most of a year to fix.

Eczema on the feet blisters on the sides of the toes and the arch, which is exactly where the blistering kind of athlete's foot appears. Eczema is usually on both feet evenly, spares the web spaces, and often shows up on the hands at the same time. Athlete's foot tends to favor one foot first, starts between the outer toes, and has a scaling edge. A scraping settles it, and treating eczema as fungus wastes weeks.
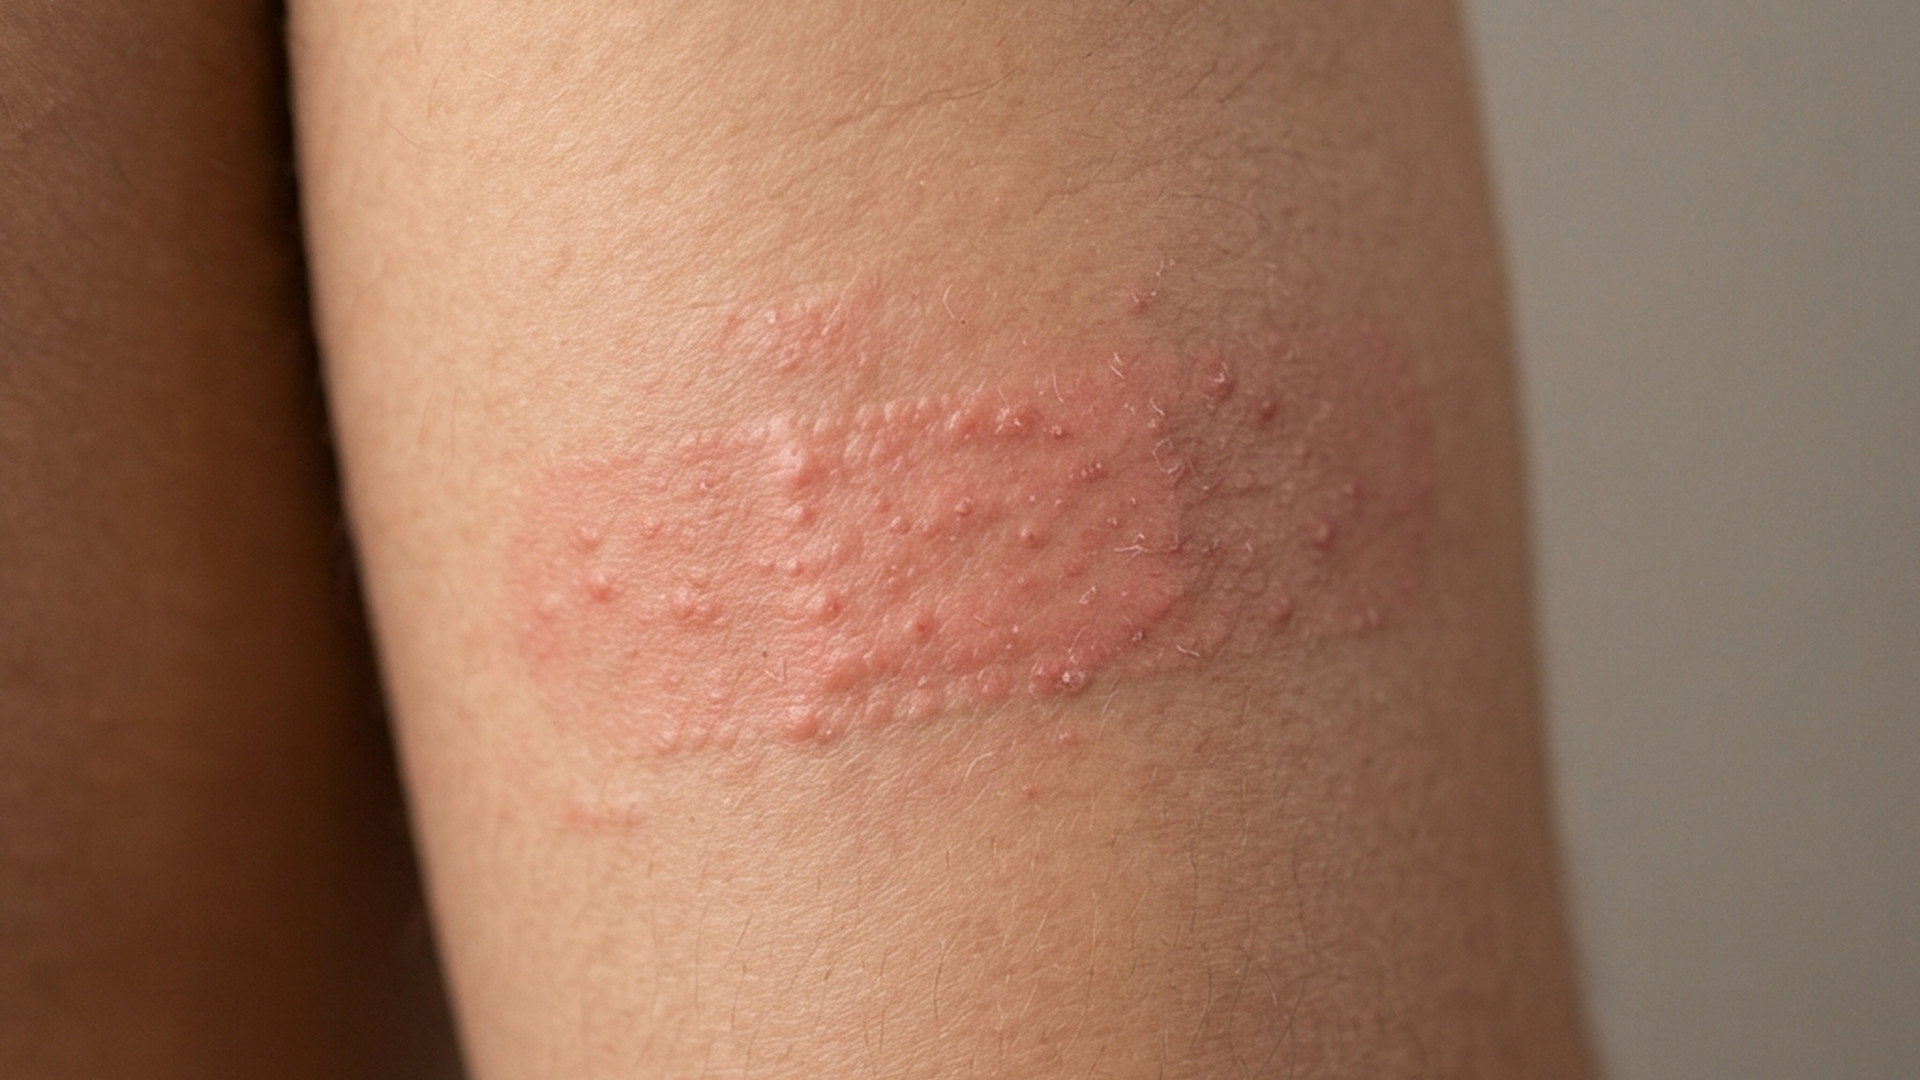
An allergy to rubber, glue or dye in a shoe makes an itchy, scaly rash that is easily called athlete's foot. The giveaway is the shape: it sits on the top of the foot in the outline of the shoe, matches on both feet, and leaves the web spaces between the toes untouched. Athlete's foot works the other way round, starting between the toes and on the sole.
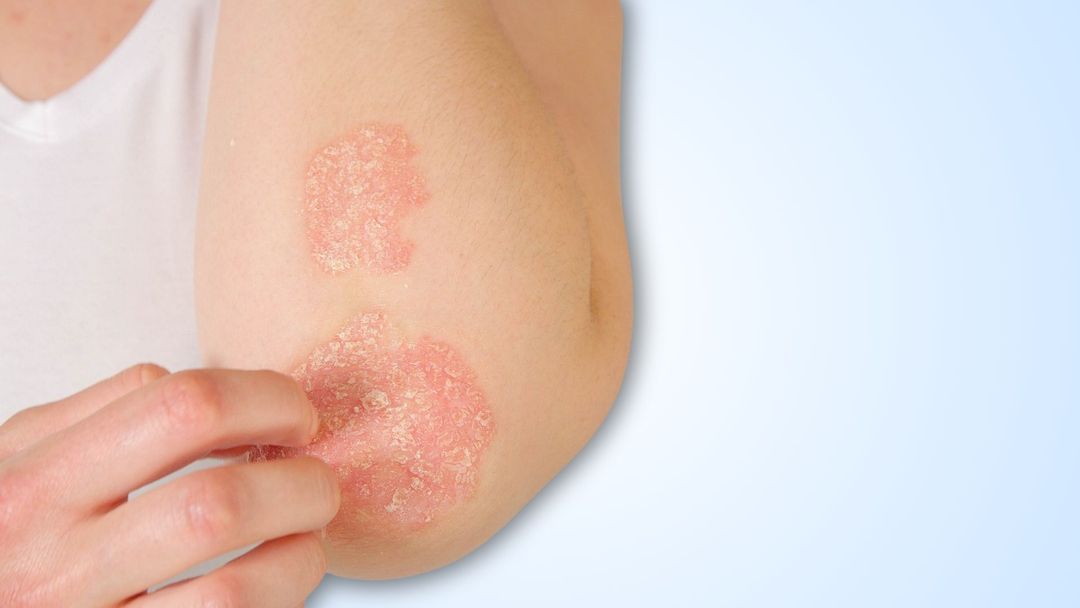
Psoriasis on the sole is dry and scaly across the whole weight-bearing area, so it reads as the moccasin kind of athlete's foot. Psoriasis scale is thicker and silvery, the edge is sharply drawn, and there is usually psoriasis somewhere else, on the elbows, knees or scalp. It also does not respond to antifungal cream, which is often the moment the question gets asked.
Common questions
Look between your toes. Athlete's foot makes the skin there white, soft and split, and it itches. Dry feet build up on the heel and the ball of the foot and rarely involve the toe webs.
No. Moisturizer treats dryness, and a thick cream between the toes keeps the skin damp, which is what the fungus needs. Athlete's foot needs an antifungal cream.
Most drugstore antifungal creams clear it in one to four weeks, depending on which one you use. Keep applying for a week or two after the skin looks normal, or it usually returns.
Yes. Athlete's foot spreads through damp shared floors, towels and shoes. Dry skin is not an infection and cannot pass to anyone.
Cold air holds less moisture, indoor heating dries it further, and the soles have no oil glands to make up the difference. A urea or lactic acid cream applied daily on damp skin is the usual fix.
Yes, and it is common. Cracked skin is easier for a fungus to get into. Treat the toe webs with an antifungal and the heels with moisturizer.